
 US Integrated Delivery Network Market | 2026-2036
US Integrated Delivery Network Market Size, Share, and Industry Trends Forecast 2026-2036
US Integrated Delivery Network Market Intelligence
Asset-light leasing arrangements for clinical infrastructure is narrowing the capital barrier for mid-scale health systems seeking geographic expansion. HCA Healthcare leverages its proprietary ambulatory surgery center network to sustain margin advantages in high-volume procedural markets. Kaiser Permanente anchors competitive positioning through captive insurance integration and vertical control over primary-to-tertiary care pathways. CommonSpirit Health operates the largest nonprofit hospital footprint by bed count, extending reach across rural and urban catchment zones simultaneously.
A US Integrated Delivery Network represents a formal organizational structure comprising hospitals, physician groups, post-acute facilities, and ancillary services under unified governance with shared electronic infrastructure and centralized contracting. These networks coordinate patient flow across acute and non-acute settings while managing global risk contracts through consolidated payer negotiations. Hospital services generate the dominant revenue base within service-type segmentation, though ambulatory services capture expanding margin pools as surgical migration accelerates. Telemedicine infrastructure within technology segmentation is displacing traditional access models fastest, while EHR analytics platforms concentrate vendor spending among systems pursuing population health contracts.
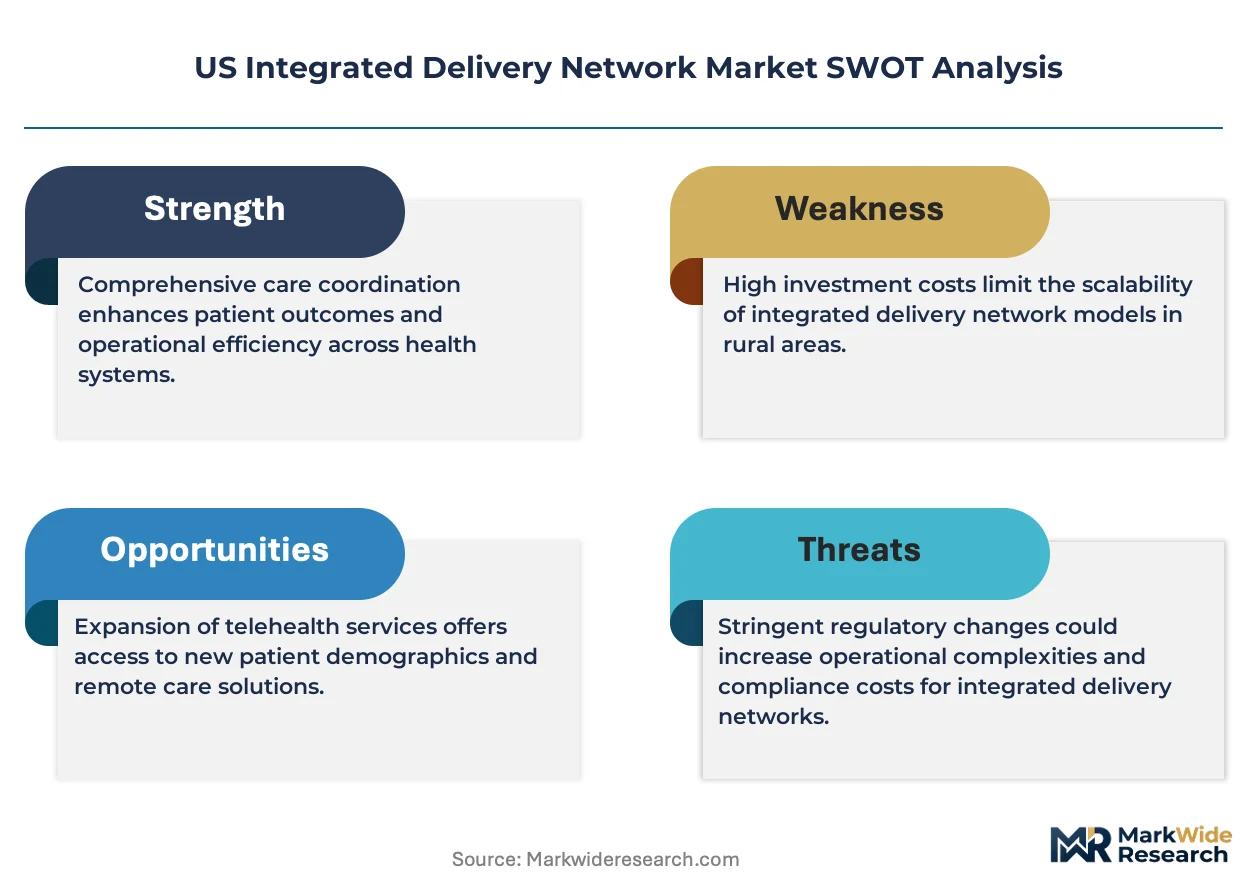
FDA oversight of digital health software as medical devices intersects with CMS reimbursement determinations to shape technology adoption timelines within IDN capital budgets. HIPAA interoperability mandates and the ONC information blocking rules are forcing standardized data exchange architectures across previously siloed delivery platforms. OSHA workplace safety requirements and state-level certificate-of-need regulations further constrain facility expansion geography. Stakeholders must monitor whether Medicare Advantage penetration thresholds trigger mandatory downside risk participation in CMS innovation models.
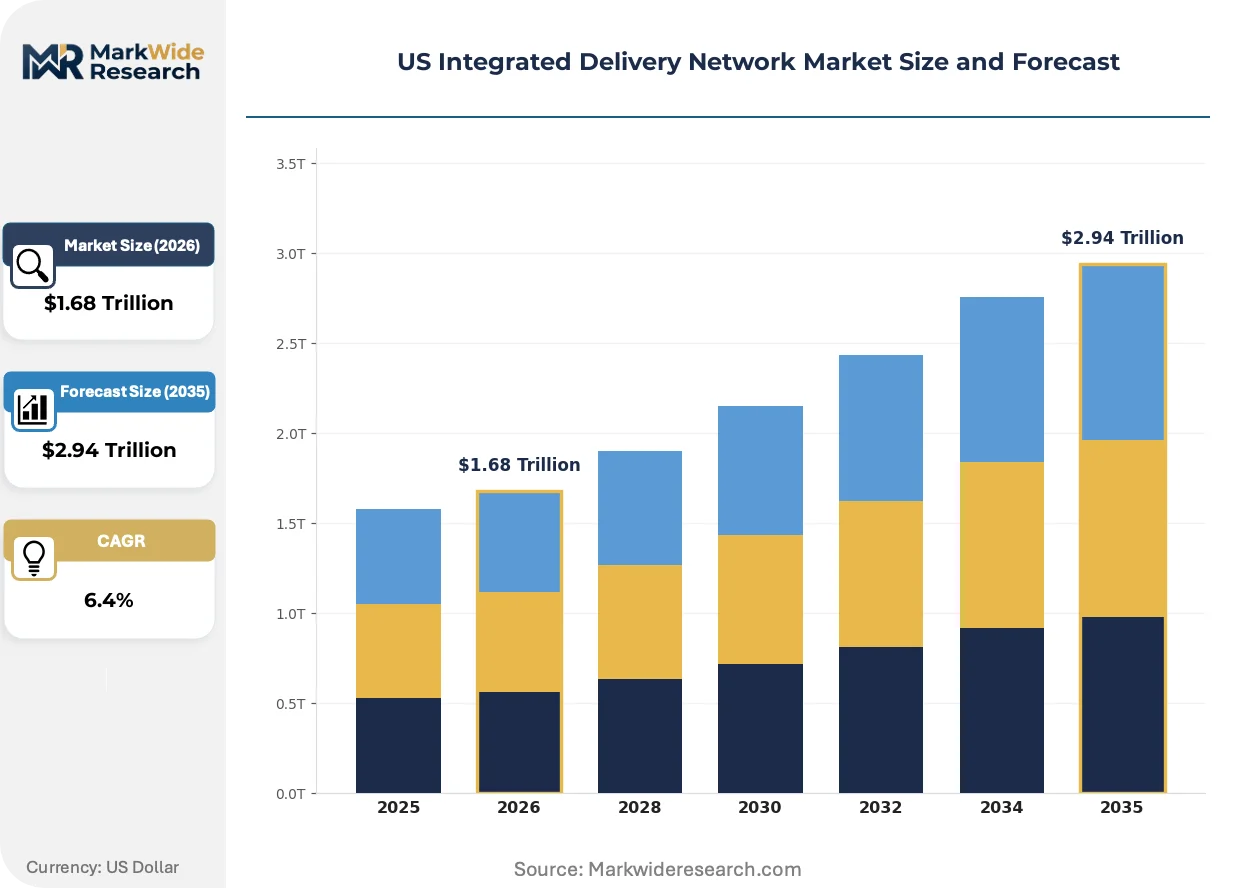
Market Dynamics
CMS value-based payment mandates are compressing fee-for-service revenue structures, forcing IDNs to reconfigure care delivery around bundled reimbursement and population health accountability.
Growth Catalysts
- Medicare Advantage Enrollment Surge:Senior populations in Texas and Florida are migrating toward managed care products, concentrating IDN investment in Medicare-focused service lines and ambulatory infrastructure.
- HIPAA Interoperability Mandates:The ONC information blocking rules are standardizing data exchange protocols, reducing friction for multi-site care coordination and enabling consolidated payer negotiations.
- Telemedicine Platform Maturation:Virtual care infrastructure is extending IDN reach into rural catchment zones without proportional capital deployment in brick-and-mortar capacity.
Market Restraints
- Certificate-of-Need Constraints:State-level CON regulations in 35 states restrict facility expansion geography, protecting incumbents but blocking mid-scale systems from entering high-demand metropolitan corridors.
- Clinical Workforce Scarcity:Registered nurse and specialized physician shortages concentrate in Sun Belt growth markets, inflating labor costs faster than reimbursement rate adjustments.
- EHR Vendor Concentration:Epic and Cerner dominance creates switching costs and integration barriers for IDNs seeking best-of-breed point solutions.
Strategic Opportunities
- Rural Hospital Distress Acquisition:Financially distressed critical access hospitals in the Southeast and Midwest present turnkey expansion targets for systems with capital reserves and telemedicine backbone.
- CMS Innovation Model Participation:Mandatory downside risk thresholds in Medicare Advantage penetration zones create first-mover advantages for IDNs with actuarial infrastructure and captive insurance capabilities.
- Ambulatory Surgery Center Rollouts:Procedural migration from inpatient to outpatient settings enables margin capture in high-volume orthopedic and ophthalmic service lines without acute care overhead.
Industry Challenges
- Legacy EHR Integration Complexity:Merged health systems face multi-year data harmonization timelines when consolidating disparate electronic infrastructure across acquired facilities.
- Specialized Physician Recruitment:Cardiothoracic surgery, neurosurgery, and maternal-fetal medicine subspecialists remain concentrated in academic medical centers, constraining service line expansion for community-based IDNs.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | US Integrated Delivery Network Market |
| Market Size in 2026 | $1.68 Trillion |
| Market Size in 2035 | $2.94 Trillion |
| CAGR (2026 – 2036) | 6.4% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: Ambulatory Services, Emergency Care, Hospital Services, Home Health Care Technology: Telemedicine, EHR, Analytics Platforms, Digital Health End User: Healthcare Providers, Payers, Patients, Government Agencies Application: Care Coordination, Population Health Management, Revenue Cycle Management, Quality Improvement |
| Companies Covered | CommonSpirit Health, UNITEDHEALTH GROUP, HCA Healthcare, UPMC, Providence, Kaiser Permanente, Trinity Health, Cleveland Clinic, Ascension Health, Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
US Integrated Delivery Network Market Strategic Shifts & Innovations
Digital infrastructure is reconfiguring patient access patterns while regulatory pressure accelerates risk-based contracting adoption across US delivery networks.
Cloud-native telehealth platforms are virtualizing traditional site-of-care requirements, enabling IDNs to deliver specialist consultations and chronic disease management without physical facility dependency. Medicare Advantage plans and self-insured employers are adopting these platforms fastest, contracting directly with virtual-first provider networks. This virtualization is compressing geographic moats that previously protected regional hospital systems from out-of-market competition.
OSHA workplace safety requirements intersect with CMS hospital-acquired condition penalties to intensify investment in clinical workforce protection and patient safety infrastructure. The industrial consequence is capital reallocation toward environmental monitoring systems and staffing ratio compliance technology. Post-acute and skilled nursing segments face the steepest compliance cost escalations as dual enforcement mechanisms expand.
Patient navigation and care coordination services are unbundling from traditional inpatient admission packages, with payers and employers contracting these functions separately from acute episode reimbursement. Digital health vendors and specialized care management firms are capturing this spend, displacing hospital-based case management as the default coordination layer. This pattern concentrates in Medicare Advantage markets where star rating performance directly influences plan revenue.
US Integrated Delivery Network Market Segmentation
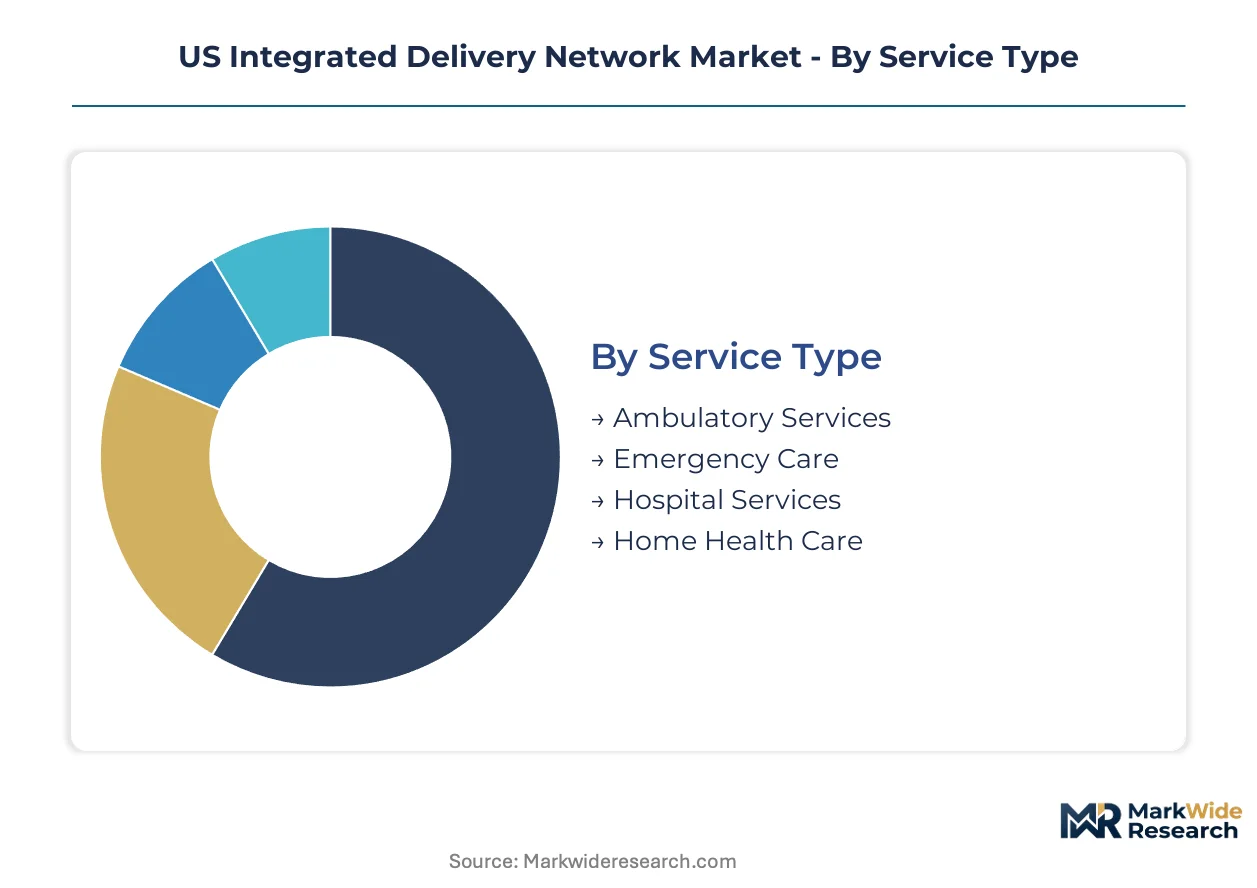
Segmentation reveals how capital allocation and regulatory pressure concentrate across distinct operational layers of US delivery networks. Each dimension exposes different margin structures and competitive moats that shape system-level strategy.
Service Type:
Mature acute services dominate revenue bases while emerging ambulatory platforms capture margin expansion.
- Hospital Services:Inpatient admissions, surgical suites, and intensive care units constitute the foundational revenue engine. Demand concentrates in Texas and Florida where population growth outpaces bed capacity expansion, though labor scarcity inflates operating costs faster than CMS reimbursement adjustments.
- Ambulatory Services:Outpatient surgical centers, infusion clinics, and diagnostic imaging facilities operate at lower fixed-cost intensity. Orthopedic and ophthalmic procedural migration from inpatient settings drives fastest expansion, particularly among Medicare Advantage populations seeking site-neutral pricing advantages.
- Emergency Care:Freestanding emergency departments and micro-hospitals extend geographic reach without full-scale acute infrastructure deployment.
- Home Health Care:Post-acute skilled nursing and chronic disease monitoring reduce readmission exposure under bundled payment models.
Hospital services retain volume leadership; ambulatory services hold the steepest expansion curve.
Technology:
Cost tier differentiation separates capital-intensive infrastructure from lightweight platform deployments.
- EHR:Electronic health record systems anchor clinical workflow standardization and payer data submission requirements. Epic and Cerner concentration creates switching cost barriers, though HIPAA interoperability mandates are forcing API-based integration with third-party modules.
- Telemedicine:Virtual visit platforms and remote patient monitoring compress geographic access constraints. Rural hospital distress acquisitions increasingly bundle telemedicine backbone as turnkey infrastructure, extending specialist reach without physical facility investment.
- Analytics Platforms:Population health risk stratification and predictive readmission algorithms support value-based contract performance.
- Digital Health:FDA-regulated software-as-medical-device applications intersect with CMS reimbursement determinations to shape adoption timelines.
EHR retains volume leadership; telemedicine holds the steepest expansion curve.
End User:
Customer type determines contracting complexity and payment velocity across network relationships.
- Healthcare Providers:Physician groups, hospitals, and post-acute facilities consume infrastructure for care delivery coordination. IDN governance structures consolidate purchasing power for these entities, though merged systems face multi-year EHR harmonization timelines.
- Payers:Medicare Advantage plans and commercial insurers drive risk-based contracting specifications. Downside risk thresholds in high-penetration markets force provider investment in actuarial infrastructure and captive insurance capabilities.
- Patients:Direct-to-consumer navigation tools and price transparency platforms reshape access patterns.
- Government Agencies:CMS innovation models and state Medicaid programs mandate reporting standardization.
Healthcare providers retain volume leadership; payers hold the steepest expansion curve.
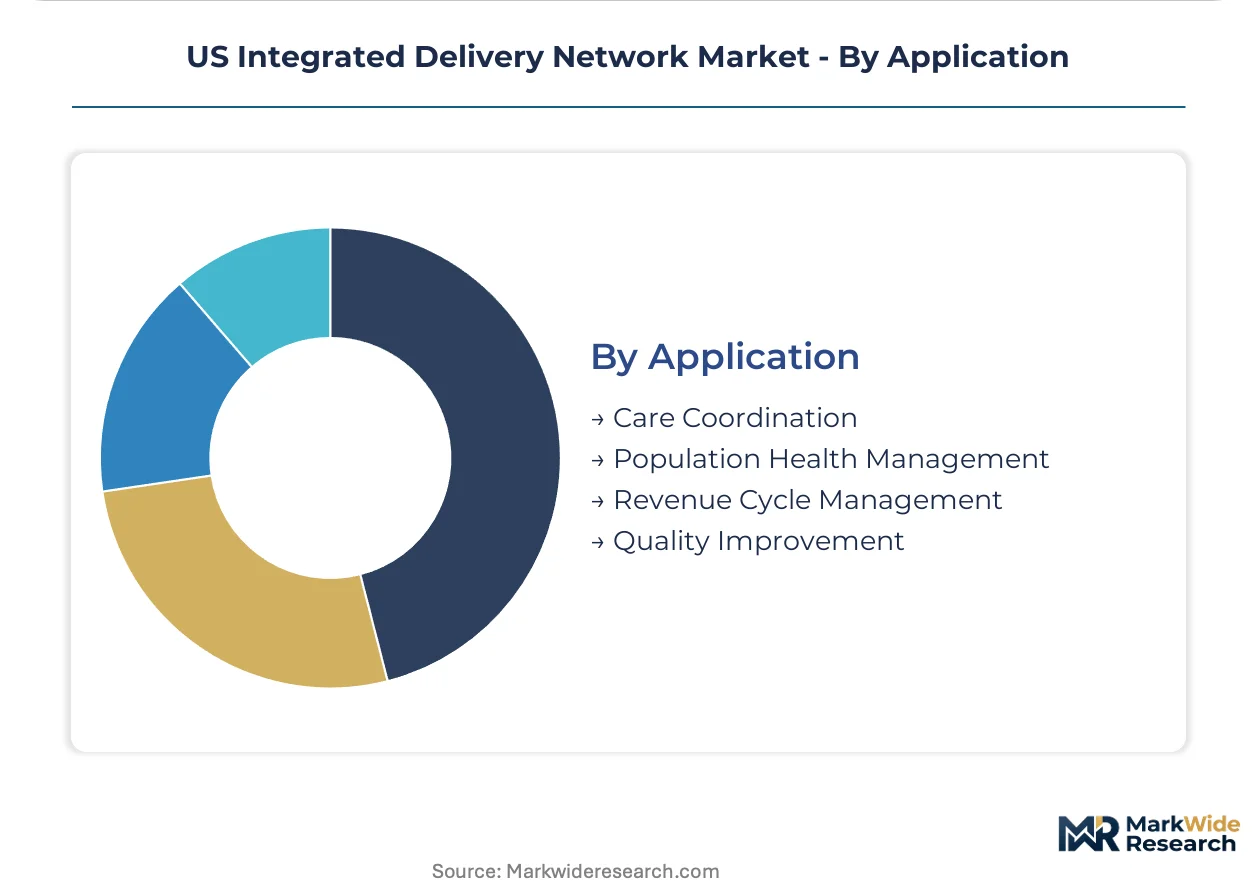
Application:
Margin concentration varies by functional layer from revenue optimization to clinical outcome accountability.
- Care Coordination:Patient navigation and transition management reduce fragmentation across acute and post-acute settings. Medicare Advantage star rating performance concentrates demand in markets where plan revenue ties directly to quality metrics.
- Revenue Cycle Management:Claims processing, prior authorization automation, and denial management protect fee-for-service yield. Prior authorization automation and denial management protect fee-for-service yield as CMS compresses traditional reimbursement structures.
- Population Health Management:Risk stratification and chronic disease registries support global budget accountability.
- Quality Improvement:Clinical pathway standardization and safety event reporting satisfy OSHA and CMS hospital-acquired condition requirements.
Revenue cycle management retains volume leadership; care coordination holds the steepest expansion curve.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Capital flows within the US Integrated Delivery Network Market concentrate where population expansion outstrips hospital capacity, creating import-like demand for external system entry. Texas and Florida absorb disproportionate investment as domestic migration patterns reshape service line economics.
Texas
Medicare Advantage enrollment among senior migrants from California and the Northeast drives ambulatory surgery center deployment across Dallas-Fort Worth and Houston. State-level CON regulations remain absent, permitting rapid facility expansion by out-of-market systems. The Texas Medical Center in Houston anchors specialist concentration while Austin's tech corridor attracts direct-to-employer contracting models.
Florida
Snowbird populations and retiree migration sustain year-round demand for orthopedic and cardiac service lines in Tampa and Orlando metro corridors. Medicaid managed care expansion under state waiver authority pressures safety-net hospitals toward IDN affiliation. Jacksonville and Miami-Dade host competing system footprints from for-profit and nonprofit operators seeking Medicare Advantage market share.
California
Kaiser Permanente's integrated model dominates Northern and Southern catchments, compressing margins for competing systems seeking commercial payer contracts. Office of Statewide Health Planning and Development certificate-of-need requirements constrain greenfield hospital development in Los Angeles and San Francisco Bay Area markets. Sacramento and Central Valley regions present acquisition targets for systems with Medi-Cal managed care capabilities.
Ohio
Cleveland Clinic and competing academic medical centers anchor tertiary referral patterns extending into Pennsylvania and West Virginia. State budget pressures on Medicaid expansion create partnership opportunities for systems with risk-bearing infrastructure. Columbus and Cincinnati metro areas concentrate ambulatory expansion as procedural migration accelerates site-neutral reimbursement capture.
Pennsylvania
UPMC and competing Pittsburgh-Philadelphia systems extend telemedicine networks into rural Appalachian counties with physician supply deficits. Pennsylvania Department of Health CON regulations protect incumbent hospital positions in saturated urban markets. Hershey and Allentown corridor facilities serve as geographic bridge points for multi-state network integration.
US Integrated Delivery Network Market Key Industry Players
On the supply side, the industry is consolidating around scale-driven operators with captive insurance capabilities and geographic density in high-growth Sun Belt corridors. Three archetypes dominate competitive positioning: vertically integrated closed systems with owned payer arms, for-profit multi-state chains with ambulatory-heavy asset profiles, and nonprofit federations with rural-safety-net mission obligations. M&A activity targets distressed critical access hospitals and specialty physician practices, while telemedicine infrastructure investments compress traditional geographic moats.
Within the integrated closed-system tier, Kaiser Permanente anchors competitive positioning through captive insurance integration and vertical control over primary-to-tertiary care pathways. HCA Healthcare exemplifies the for-profit multi-state archetype with proprietary ambulatory surgery center networks sustaining margin advantages in high-volume procedural markets. CommonSpirit Health occupies the nonprofit federation position, operating the largest hospital footprint by bed count while extending simultaneous reach across rural and urban catchment zones.
| Leading Market Players |
|---|
| CommonSpirit Health |
| UNITEDHEALTH GROUP |
| HCA Healthcare |
| UPMC |
| Providence |
| Kaiser Permanente |
| Trinity Health |
| Cleveland Clinic |
| Ascension Health |
| Others |
Cost & Logistics Intelligence
Houston's Texas Medical Center anchors specialist capacity concentration that translates directly into downstream pricing leverage for procedural service lines. Medicare Advantage plan negotiation power compresses margins in ambulatory settings while acute care retains rate-setting autonomy in supply-constrained corridors.
Pricing Analysis
Industrial OEM buyers anchor contract-based long-term offtake structures with tiered pricing separating academic medical centers from community hospital systems and critical access facilities. Price differentiation rests on CMS star rating performance and Medicare Advantage penetration density, with rural markets showing highest price sensitivity due to payer mix concentration. Cost compression in outpatient surgical tiers is intensifying because site-neutral reimbursement policies erase historical inpatient premiums. Large employer direct contracting demonstrates lowest price sensitivity, prioritizing network adequacy over per-unit economics.
Supply Chain Analysis
Upstream feedstock dependencies in clinical workforce supply draw from India, the Philippines, and domestic nursing education pipelines constrained by accreditation bottlenecks. EHR software components and telemedicine platform modules hinge on concentrated vendor ecosystems in California and Washington state. Single-source vulnerability in specialized physician recruitment creates geographic access inequities. Distribution runs through GPO contracts consolidating procurement leverage for multi-hospital systems while independent facilities face premium sourcing costs.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
This market functions as a defensive-moat story where regulatory entrenchment through certificate-of-need protections and Medicare Advantage plan licensing creates durable incumbent advantages. Network effects from EHR interoperability and captive payer integration compound switching costs for displaced patients.
For Market Incumbents: Insulate market position by accelerating ambulatory surgery center deployment in Texas and Florida corridors ahead of CON liberalization threats. Deepen backward integration into telemedicine infrastructure to offset virtual-first entrant displacement of traditional access models. Prioritize actuarial capability investment to capture mandatory downside risk contracts as CMS penetration thresholds trigger innovation model participation.
For New Entrants and Emerging Players: Rural Appalachian and Central Valley California geographies present white-space targets where physician supply deficits exceed incumbent telemedicine reach. Medicare Advantage star rating optimization services offer penetrable entry points against hospital-based case management legacy structures. Direct-to-employer contracting in Austin's tech corridor provides viable go-to-market angle bypassing traditional payer intermediation.
For Investors and Strategic Acquirers: Mid-cycle technology positioning favors systems with captive insurance capabilities and demonstrated population health infrastructure. Long-term viability over the projection horizon rests on actuarial sophistication and geographic density in Sun Belt migration corridors. Acquisition target archetypes include distressed critical access hospitals with turnkey telemedicine backbone and specialty physician practices in orthopedic and ophthalmic service lines. Watch Medicare Advantage penetration thresholds as inflection indicator triggering mandatory risk model participation.
| Strategic Initiative | Industry Significance |
|---|---|
| Ambulatory Surgery Center Rollout | Captures site-neutral reimbursement migration in Texas and Florida Medicare Advantage markets. |
| Telemedicine Infrastructure Investment | Extends specialist reach into rural catchment zones without proportional brick-and-mortar deployment. |
| Captive Insurance Capability Buildout | Enables mandatory downside risk participation in high Medicare Advantage penetration corridors. |
| Distressed Hospital Acquisition | Secures turnkey geographic expansion with existing CMS certification and community referral relationships. |
| EHR Interoperability Certification | Satisfies HIPAA mandates while reducing friction for multi-site care coordination and payer data exchange. |
Research Approach
Findings reconcile primary fieldwork against secondary review of CMS Medicare cost reports, hospital procurement databases, GPO contract filings, and state CON regulatory filings. Primary interviews engaged health system strategy officers, Medicare Advantage plan actuaries, GPO contracts managers, and clinical workforce directors. Bottom-up facility-level capacity modeling triangulates against top-down payer expenditure analysis across service line segmentation.
Forecast inputs incorporate hospital bed capacity expansion permits, Medicare Advantage enrollment migration patterns, and ambulatory procedural volume shifts across the analysis window. Segmentation dimensions model service type intensity, technology deployment tier, end-user contracting complexity, and application functional layer. CAGRs derive from facility investment pipeline tracking and reimbursement rate trajectory analysis. Workforce scarcity indices and EHR vendor concentration metrics inform supply-side constraint modeling.
The forecast holds incumbent behavior within observed patterns; aggressive moves by virtual-first provider networks or Amazon-style direct-to-employer entrants would shift outcomes. Cross-checking against CMS innovation model participation thresholds and state-level Medicaid managed care waiver approvals is advised before commitment-grade decisions.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Healthcare Services
Hospice and Palliative Care Centers Market
Healthcare Services
Assisted Living Market
Healthcare Services
Tissue Banking Market
Healthcare Services
Medical Case Management Services Market
Healthcare Services
Health Care Supply Chain Management Market
Healthcare Services
Retail Clinics Market
Healthcare Services
Global Corporate Wellness Solutions Market
Healthcare Services
Australia Senior Living Market
Healthcare Services
US Primary Care Physicians Market
Healthcare Services
Medical Devices and Equipment Logistics Market
Healthcare Services
Hospital Command Center Operations Market
Healthcare Services
In-Home Senior Care Franchises Market
Healthcare Services
Michigan Urgent Care Center Market
Healthcare Services
Vaccine Logistics Market
Healthcare Services
US Medical Billing Outsourcing Market
Healthcare Services
US Cord Blood Banking Services Market