
 US Primary Care Physicians Market | 2026-2036
US Primary Care Physicians Market Size, Share, and Industry Trends Forecast 2026-2036
US Primary Care Physicians Market Intelligence
CMS Medicare Shared Savings Program is hardening accountability standards for primary care networks. UnitedHealth Group leverages its Optum Care platform to sustain vertical integration across ambulatory services. MDVIP anchors its concierge membership model in affluent suburban markets. ChenMed specializes in capitated senior care, controlling medical costs through high-touch chronic disease management.
Primary care physicians deliver first-contact, continuous, comprehensive, and coordinated medical care across undifferentiated patient presentations. These clinicians manage approximately 90% of patient encounters without referral, serving as gatekeepers to specialty services and hospital-based interventions. Family Medicine and Internal Medicine segments dominate visit volume, while Value-Based Care and Direct Primary Care payment models represent the fastest-growing structural categories where margin pools concentrate through risk-bearing contracts. EHR Systems and Telehealth technology utilization segments show accelerating deployment as practices seek HITECH Act compliance and remote patient monitoring reimbursement pathways.
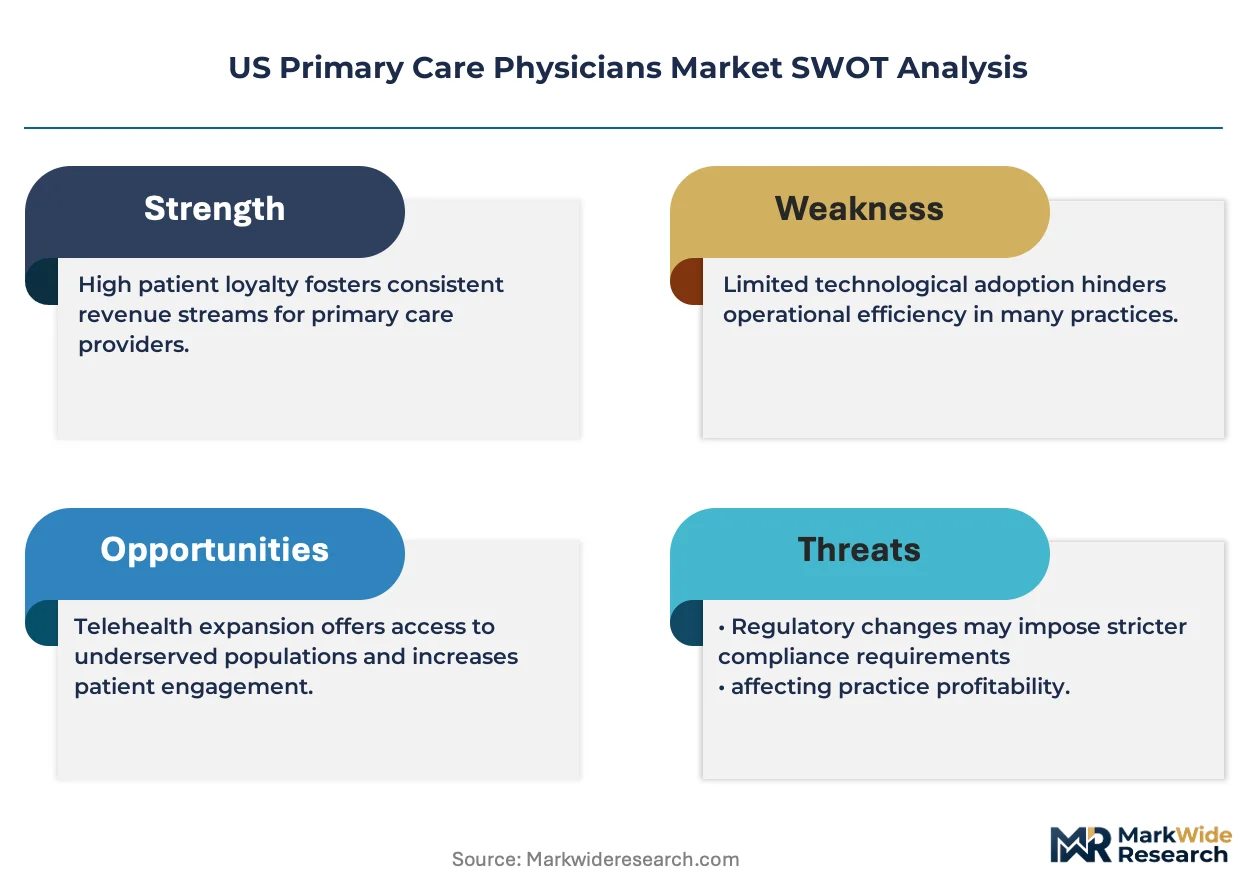
FDA oversight shapes clinical decision support tools, while CMS reimbursement rules determine practice viability across payment models. HIPAA privacy requirements constrain telehealth platform architectures, and state medical boards govern licensure reciprocity for interstate virtual care. Stakeholders must monitor CMS Innovation Center model expansions and state-level scope-of-practice reforms to anticipate competitive positioning shifts.
Market Dynamics
CMS value-based payment models are hardening accountability standards, forcing primary care networks to restructure around risk-bearing contracts rather than fee-for-service reimbursement. Medicare Advantage expansion and Medicaid managed care penetration are accelerating this structural pivot.
Growth Catalysts
- Medicare Advantage Network Requirements:CMS mandates for broader physician access are compelling health plans to contract with independent primary care practices, expanding addressable patient pools for ambulatory providers.
- Remote Patient Monitoring Reimbursement:CMS-established CPT codes for continuous glucose monitoring and blood pressure surveillance are creating new revenue streams for practices investing in connected care infrastructure.
- Texas and Florida Population Surge:Metropolitan growth corridors in Houston, Dallas-Fort Worth, Miami, and Orlando are outpacing primary care supply, generating demand concentration for new practice entrants.
Market Restraints
- EHR Switching Costs:Epic and Cerner platform migrations impose six-figure capital outlays and 12-18 month workflow disruptions that freeze technology adoption cycles for mid-sized group practices.
- Physician Supply Concentration:Graduate medical education residency slots remain capped by the 1997 Balanced Budget Act, constraining annual board-certified primary care output regardless of demand signals.
- Prior Authorization Burden:Commercial payers including Anthem and Cigna impose escalating documentation requirements that consume 15-20 hours of physician time weekly, compressing clinical capacity.
Strategic Opportunities
- Direct Primary Care Subscription Models:Employer-sponsored DPC arrangements in North Carolina and Colorado are bypassing traditional insurance intermediaries, capturing margin through monthly membership fees.
- CMS Innovation Center ACO REACH:The redesigned direct contracting model offers enhanced benchmarking for practices serving high-acuity Medicare populations in underserved rural counties.
- Telehealth-Physical Convergence:Hybrid visit protocols combining asynchronous digital triage with in-person follow-up are opening suburban retail clinic locations previously uneconomical for pure brick-and-mortar operations.
Industry Challenges
- Interoperability Fragmentation:HL7 FHIR implementation gaps between hospital systems and independent practices perpetuate information blocking, forcing redundant testing and care coordination failures.
- Prior Authorization Automation:Payer-specific portal requirements lack standardization, requiring practices to maintain parallel workflows despite CMS mandates for electronic prior authorization adoption by 2026.
- Workforce Pipeline Constraints:Medical school debt loads averaging $200,000 steer graduates toward higher-reimbursing specialties, depressing family medicine match rates at programs in the Northeast and Midwest.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | US Primary Care Physicians Market |
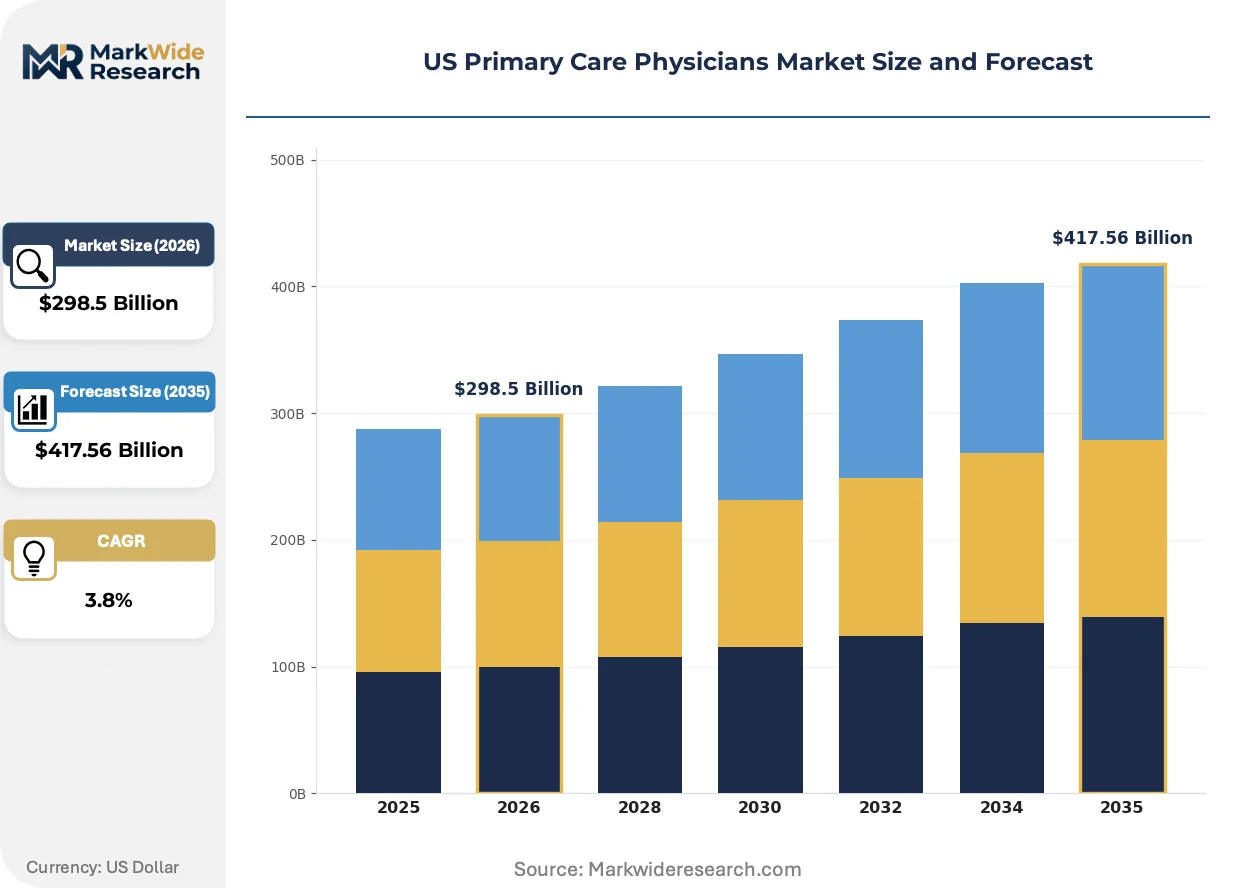
| Market Size in 2026 | $298.5 Billion |
| Market Size in 2035 | $417.56 Billion |
| CAGR (2026 – 2036) | 3.8% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Practice Type: Family Medicine, Internal Medicine, Pediatrics, Geriatrics Payment Model: Fee-for-Service, Capitation, Value-Based Care, Direct Primary Care Technology Utilization: EHR Systems, Telehealth, Decision Support Tools, Patient Portals Patient Demographics: Adults, Children, Seniors, Women |
| Companies Covered | UnitedHealth Group, MDVIP, 1Life Healthcare, Inc. (One Medical Group), ChenMed LLC, Duly Health and Care, Optum, Inc., Kaiser Permanente, CVS Health, Crossover Health Medical Group, Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
US Primary Care Physicians Market Strategic Shifts & Innovations
Artificial intelligence documentation tools and risk-adjustment analytics are compressing administrative burden while CMS accelerates value-based contract penetration. These forces are restructuring how primary care practices capture and retain patient populations.
Ambient clinical intelligence using natural language processing is electrifying exam room workflows. Primary care groups in Arizona and Nevada are deploying these tools to auto-generate encounter notes, reducing documentation time by approximately 50%. This compression is enabling physicians to expand daily visit volumes without extending hours or adding clinical staff.
CMS Medicare Shared Savings Program redesign is hardening quality benchmarks and introducing health equity adjustments. Practices must now report stratified outcome measures by race and ethnicity to qualify for maximum shared savings rates. Networks serving Medicaid-dominant populations in Georgia and Louisiana face the steepest compliance ramps.
Employer-sponsored direct primary care arrangements are displacing traditional PPO networks for mid-market companies. Manufacturing and logistics employers in Indiana and Ohio are contracting with DPC practices for on-site or near-site clinics, unbundling primary care from comprehensive major medical plans. This channel shift concentrates patient volume with capitated practices outside conventional insurance exchange structures.
US Primary Care Physicians Market Segmentation
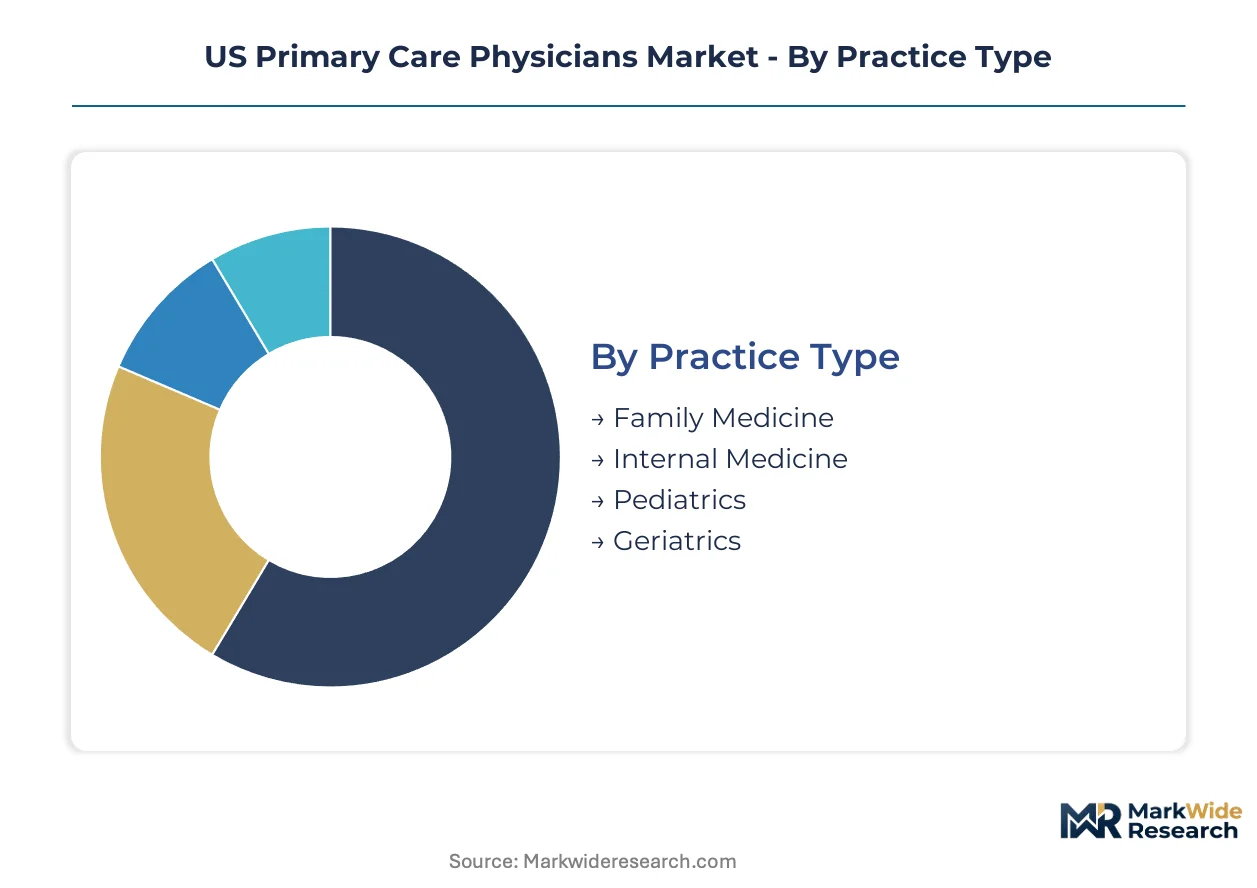
Primary care market structure determines where capital flows and margin pools form. Payment model selection and technology deployment intensity separate high-performing practices from commodity operators.
Practice Type:
Supply concentration tilts toward adult-serving specialties where reimbursement complexity favors scale.
- Family Medicine:Broad-scope training enables whole-family panel management across acute, chronic, and preventive services. Demand concentrates in Texas and Florida exurban corridors where new construction outpaces specialist penetration. Family physicians anchor Medicare Advantage network adequacy requirements in these markets.
- Internal Medicine:Adult-focused pathophysiology expertise positions these clinicians for complex chronic disease management. Hospital-owned groups in Houston and Miami recruit internists aggressively to capture downstream specialty referrals and imaging revenue. Internal medicine represents the fastest-growing trajectory among practice types as population aging accelerates.
- Pediatrics:Medicaid-dependent reimbursement compresses margins despite stable visit volumes.
- Geriatrics:Fellowship-trained supply scarcity limits expansion regardless of demographic tailwinds.
Today's leader: Family Medicine. Tomorrow's challenger: Internal Medicine.
Payment Model:
Cost tier stratification separates risk-bearing innovators from fee-for-service incumbents facing margin erosion.
- Fee-for-Service:Legacy reimbursement ties revenue to visit volume rather than outcomes. Practices in the Northeast and Midwest remain tethered to this model due to payer mix inertia and EHR switching costs that freeze operational transformation.
- Value-Based Care:CMS Medicare Shared Savings Program and commercial ACO contracts tie compensation to quality metrics and total cost of care reduction. ChenMed and similar groups in Georgia and Louisiana are gaining share fastest through capitated senior arrangements.
- Capitation:Per-member-per-month payments align incentives with population health management.
- Direct Primary Care:Employer-sponsored arrangements in North Carolina and Colorado bypass insurance intermediaries entirely.
Today's leader: Fee-for-Service. Tomorrow's challenger: Value-Based Care.
Technology Utilization:
Application intensity varies by practice scale and payer technology reimbursement policies.
- EHR Systems:Epic and Cerner platform dominance creates switching cost barriers that freeze mid-sized group adoption cycles. Practices seeking HITECH Act meaningful use compliance face six-figure capital outlays and 12-18 month workflow disruptions.
- Telehealth:CMS-established CPT codes for virtual visits and remote patient monitoring are expanding addressable service delivery models. Arizona and Nevada practices deploy hybrid protocols combining asynchronous triage with in-person follow-up.
- Decision Support Tools:FDA oversight shapes clinical algorithm deployment for diagnostic assistance.
- Patient Portals:HIPAA privacy requirements constrain architecture choices for interstate virtual care.
Today's leader: EHR Systems. Tomorrow's challenger: Telehealth.
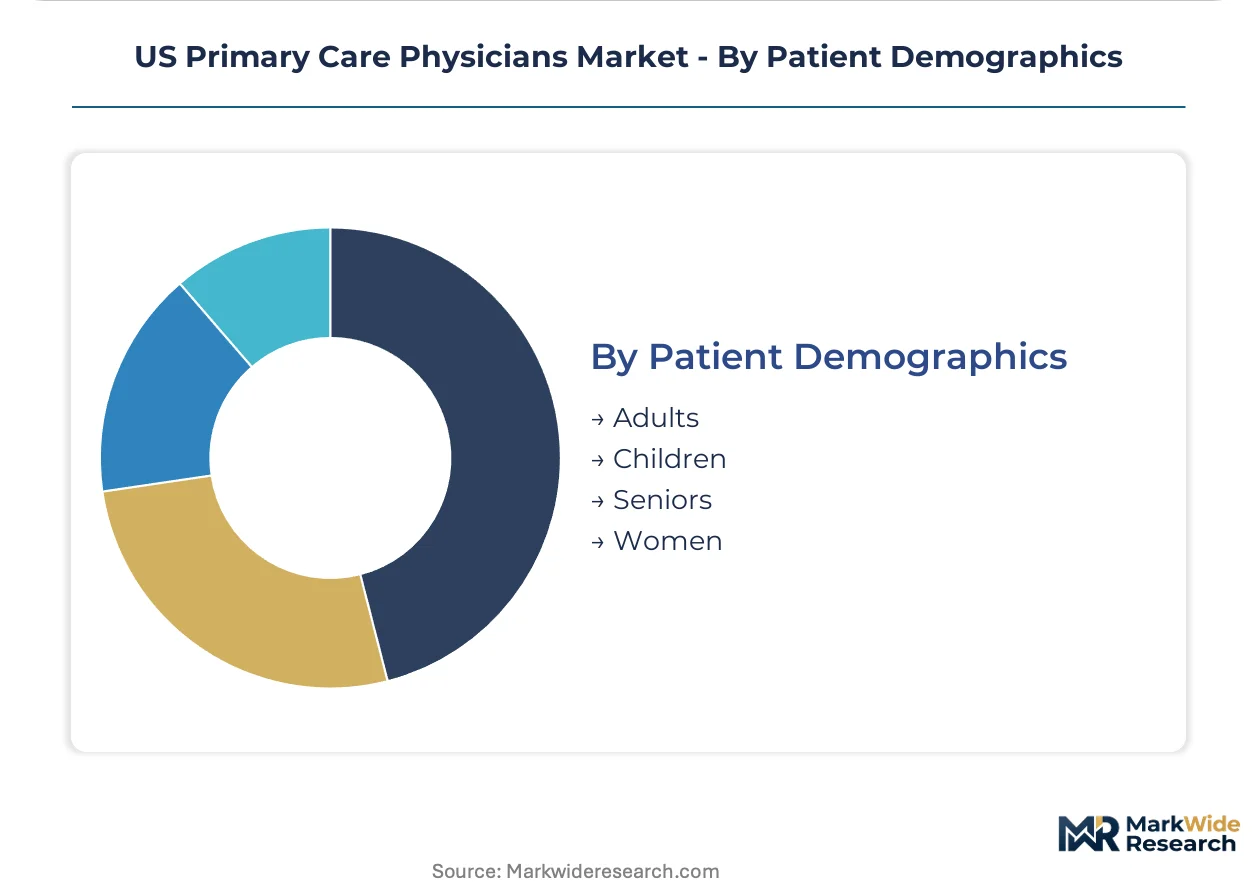
Patient Demographics:
Volume concentration tracks population aging and women's health service bundling.
- Seniors:Medicare Advantage penetration and Medicaid managed care expansion concentrate demand for high-touch chronic disease management. ChenMed specializes in this demographic through capitated arrangements controlling medical costs.
- Adults:Commercially insured working-age populations drive employer-sponsored DPC adoption in Indiana and Ohio manufacturing corridors.
- Women:OB-GYN integration and preventive service bundling create distinct panel management requirements.
- Children:Pediatric volume ties to Medicaid eligibility cycles and school-based health center availability.
Today's leader: Adults. Tomorrow's challenger: Seniors.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Physician supply concentrates in metropolitan corridors where population aging and Medicare Advantage penetration create demand intensity. Texas and Florida anchor expansion dynamics as migration inflows outpace residency program output.
Texas
Houston and Dallas-Fort Worth corridors drive demand as Medicare Advantage enrollment swells among relocating retirees. CMS mandates for network adequacy compel plans to contract with independent practices in exurban counties. ChenMed operates multiple senior-focused clinics in Houston, capturing capitated revenue through high-touch chronic disease management.
Florida
Miami and Orlando metropolitan areas face acute primary care shortages amid rapid population growth. State Medicaid managed care expansion funnels patients into risk-bearing physician organizations. MDVIP anchors concierge membership models in affluent Palm Beach and Naples suburbs, bypassing traditional reimbursement structures.
California
Los Angeles and San Francisco Bay Area markets exhibit saturated specialist penetration but fragmented primary care access. HIPAA compliance requirements constrain telehealth platform architectures for interstate virtual care delivery. Kaiser Permanente's integrated model dominates Northern California, while independent practices struggle with Epic EHR switching costs.
New York
Downstate Medicaid-dominant payer mix compresses margins for community health centers. Graduate medical education residency caps limit annual board-certified output regardless of demand signals. Hospital-owned groups in New York City recruit aggressively to capture downstream specialty referrals.
North Carolina
Research Triangle and Charlotte manufacturing corridors spur employer-sponsored direct primary care adoption. Duke University Health System anchors academic medical center influence, while independent DPC practices bypass insurance intermediaries through monthly membership fees. CMS Innovation Center ACO REACH pilots target rural counties in the Piedmont region.
US Primary Care Physicians Market Key Industry Players
Capital-heavy integrated delivery systems compete with asset-light membership-based practices for patient panel control. Market structure tilts toward consolidation as Medicare Advantage penetration rewards scale-dependent risk-bearing capabilities. Three archetypes dominate: vertically integrated payer-providers, concierge subscription operators, and capitated senior specialists. Competitive intensity centers on network adequacy contracting and value-based contract acquisition rather than pure price competition.
Within the integrated delivery tier, UnitedHealth Group and Kaiser Permanente exemplify closed-system models where insurance and clinical operations share balance sheet risk. MDVIP and 1Life Healthcare occupy the subscription-based vector, converting commercial and Medicare patients into recurring revenue streams outside traditional fee-for-service structures. ChenMed represents the capitated senior specialist archetype, concentrating on high-acuity Medicare populations through per-member-per-month arrangements. Each archetype captures margin through distinct structural advantages: UnitedHealth Group through Optum Care's vertical control, MDVIP through affluent market positioning, ChenMed through medical cost management in complex chronic disease.
| Leading Market Players |
|---|
| UnitedHealth Group |
| MDVIP |
| 1Life Healthcare, Inc. (One Medical Group) |
| ChenMed LLC |
| Duly Health and Care |
| Optum, Inc. |
| Kaiser Permanente |
| CVS Health |
| Crossover Health Medical Group |
| Others |
Cost & Logistics Intelligence
Physician compensation benchmarks from the Medical Group Management Association cascade through practice economics, compressing margins for fee-for-service operators while amplifying pricing power for risk-bearing networks. CMS-established reimbursement rates tether commercial contract negotiations, creating tiered service economics where capitated arrangements capture premium yields against commodity visit volumes.
Pricing Analysis
The bundled-vs-unbundled service split separates capitated Medicare Advantage contracts from itemized fee-for-service encounters. Three-tier pricing structure across concierge, value-based, and traditional reimbursement levels stratifies by patient acuity and risk-bearing capacity. Pricing pressure stems from prior authorization automation mandates consuming administrative bandwidth. Employer-sponsored direct primary care buyers exhibit lowest price sensitivity due to unbundled benefit structures, while Medicaid-dependent practices face acute cost compression.
Supply Chain Analysis
Workforce availability constraints in Texas, Florida, and California medical education corridors tighten specialist pipeline flows into primary care channels. Residency slot allocations draw from capped Balanced Budget Act provisions, while clinical staffing depends on interstate licensure reciprocity and nurse practitioner scope-of-practice variability. Supply chain risk centers on single-source vulnerability from Epic and Cerner EHR platform dominance. Distribution runs through hospital-owned group networks, independent practice associations, and direct employer contracting channels.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
This market represents a late-cycle quality story as Medicare Advantage penetration shifts demand toward capitated, high-touch chronic disease management specifications that reward integrated care infrastructure.
For Market Incumbents: Lock in value-based contract portfolios before CMS hardens quality benchmarking thresholds. Acquire independent practices in Houston and Dallas-Fort Worth corridors to secure network adequacy positioning against UnitedHealth Group's Optum Care expansion. Prioritize EHR interoperability investments to deflect information blocking penalties. For New Entrants and Emerging Players: Begin with employer-sponsored direct primary care arrangements in North Carolina and Colorado manufacturing corridors, where benefits unbundling creates white-space outside traditional payer networks. Target mid-market logistics employers seeking on-site clinic alternatives to PPO structures. Lead with monthly membership fee transparency against opaque coinsurance designs. For Investors and Strategic Acquirers: Consolidation pressure builds where capitated senior care capabilities concentrate in underserved Medicare Advantage markets. Long-term viability favors platforms with risk-adjustment analytics infrastructure and CMS Innovation Center model participation. Watch ACO REACH benchmarking adjustments as inflection signals for rural practice valuation premiums.| Strategic Initiative | Industry Significance |
|---|---|
| Risk-Bearing Contract Acquisition | Capitated Medicare Advantage arrangements with ChenMed and similar operators capture margin pools shifting from fee-for-service. |
| EHR Interoperability Investment | HL7 FHIR compliance deflects CMS information blocking penalties while enabling remote patient monitoring revenue streams. |
| Workforce Pipeline Partnership | Family medicine residency affiliations in Texas and Florida secure physician supply against Balanced Budget Act caps. |
| Employer Direct Contracting Channel | Near-site clinic arrangements with Indiana and Ohio manufacturers bypass traditional insurance exchange intermediaries. |
| Telehealth-Physical Hybrid Model | Arizona and Nevada asynchronous triage protocols open suburban retail locations previously uneconomical for pure brick-and-mortar. |
Research Approach
Direct dialogue with primary care practice administrators, CMS policy specialists, Medicare Advantage plan contracting officers, and hospital system strategy executives grounds qualitative assessment in operational reality. Secondary validation draws from CMS Medicare Shared Savings Program public use files, American Medical Association physician workforce data, state medical board licensure statistics, and HITECH Act meaningful use compliance reports. Bottom-up practice economics modeling triangulates against top-down payer expenditure projections.
Bottom-up segmentation analysis by payment model, practice type, technology utilization intensity, and patient demographic cluster structures volume and value outputs across the projection horizon. CAGRs derive from regression-adjusted historical reimbursement trend extrapolation, incorporating Medicare Advantage penetration trajectories and Medicaid managed care expansion schedules. Forecast inputs include residency program output constraints, interstate telehealth licensure reciprocity patterns, and employer-sponsored DPC adoption curves.
Several conditions sit outside the modeled scope, including unanticipated CMS Innovation Center model cancellations, state-level scope-of-practice liberalization reversals, and macroeconomic shifts altering employer benefits unbundling appetite. Forecasts reflect documented assumptions regarding population migration patterns and Medicare Advantage star rating stability. Material deviation in named triggers warrants pause and re-evaluation.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Healthcare Services
Healthcare Physician Staffing Market
Healthcare Services
Canada Corporate Wellness Market
Healthcare Services
Healthcare Staffing Market
Healthcare Services
US Registered Nurses Market
Healthcare Services
Healthcare Cold Chain Logistics Market
Healthcare Services
Prescription Delivery Services Market
Healthcare Services
Healthcare Transportation Services Market
Healthcare Services
Global Pharmaceutical Contract Sales Outsourcing (CSO) Market
Healthcare Services
US Care Services Market
Healthcare Services
Vaccine Logistics Market
Healthcare Services
Direct-To-Patient Healthcare Logistics Market
Healthcare Services
IVD Contract Manufacturing Services Market
Healthcare Services
Europe Pharmaceutical Logistics Market
Healthcare Services
Specialty Pharma Home Delivery and Patient Support Logistics Market
Healthcare Services
Patient Throughput and Capacity Management Market
Healthcare Services
Canada Senior Living Market