
 US Burn Care Centers Market | 2026-2036
US Burn Care Centers Market Size, Share, and Industry Trends Forecast 2026-2036
US Burn Care Centers Market Intelligence
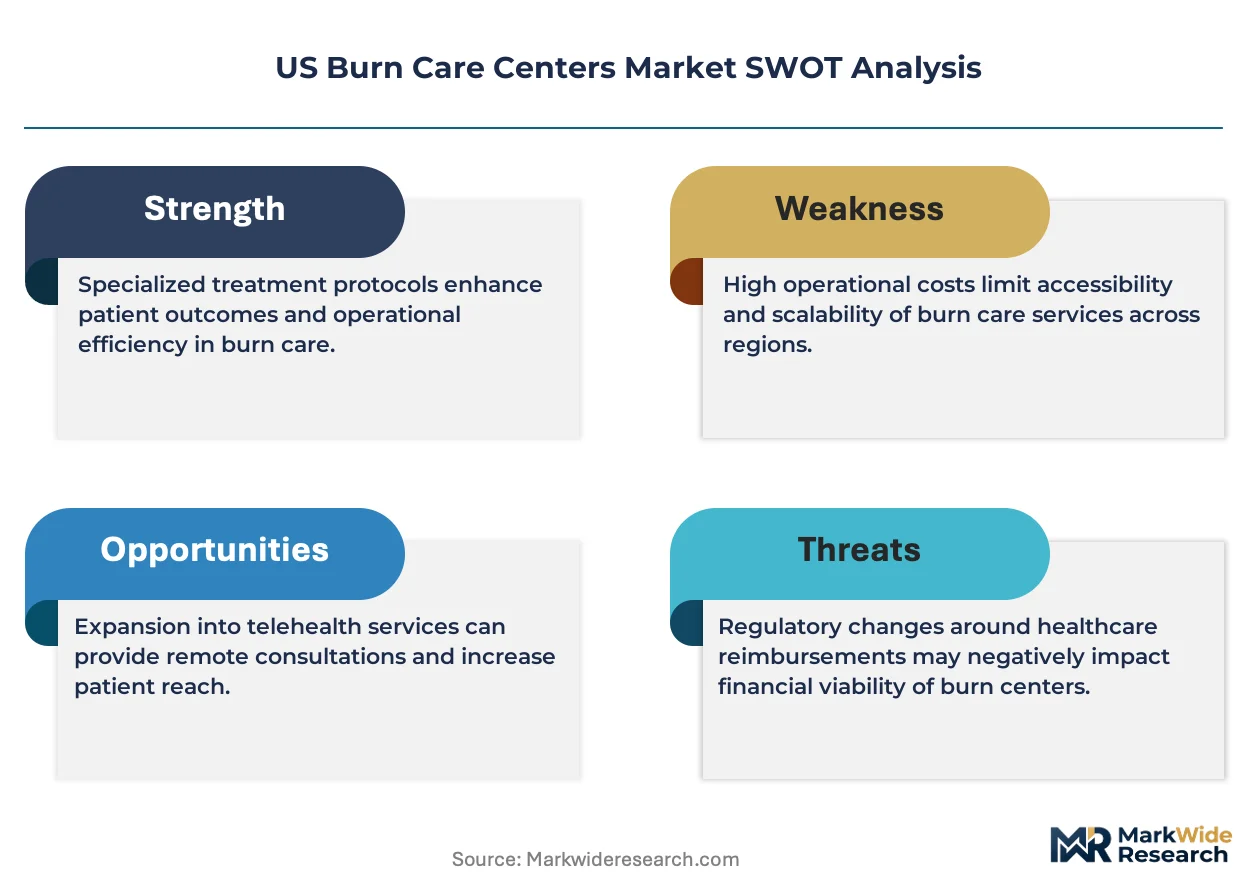
Subscription-based telemedicine triage for burn assessment is recalibrating how regional hospitals access specialist expertise without maintaining full-time burn surgeon rosters. Shriners Hospitals for Children leverages its national pediatric burn network to sustain referral flows across non-urban catchments. Parkland Memorial Hospital Regional Burn Center anchors North Texas trauma volume through its Level I verification and helicopter transport agreements. University of Miami Jackson Memorial Hospital Burn Center competes on complex reconstruction cases, differentiating through microvascular flap capabilities that general trauma centers cannot replicate.
US Burn Care Centers constitute specialized medical facilities delivering acute resuscitation, surgical reconstruction, and rehabilitative services for thermal, chemical, electrical, and radiation injuries, typically maintaining American Burn Association verification requiring dedicated ICU beds, on-site operating suites, and continuous nursing ratios exceeding standard ICU staffing. The primary purpose centers on reducing mortality from large total body surface area injuries while restoring functional and cosmetic outcomes through staged grafting and scar management protocols. Inpatient Facilities and Specialty Burn Units command the deepest margin pools due to bundled reimbursement for complex surgical episodes and extended ICU stays. Outpatient Clinics represent the fastest-expanding care setting as negative-pressure wound therapy and biosynthetic dressings enable earlier discharge with remote monitoring follow-up.
FDA oversight of skin substitute products and grafting materials shapes product availability and clinical adoption pathways in burn centers, while CMS reimbursement rules under the Inpatient Prospective Payment System directly determine facility investment in dedicated burn unit beds versus general trauma capacity. OSHA workplace safety standards and state-level trauma designation requirements from agencies like the Texas Department of State Health Services further structure market access for new center development. Stakeholders must monitor how ABA verification standards evolve to incorporate outpatient metrics and whether CMS will unbundle wound care device payments from facility fees.
Market Dynamics
Medicare reimbursement migration toward value-based bundled payments is compressing traditional fee-for-service margins while forcing hospital systems to restructure burn unit economics around episode-of-care efficiency rather than bed-day maximization.
Growth Catalysts
- CMS Innovation Center Models:The CMS Innovation Center's Bundled Payments for Care Improvement Advanced program incentivizes coordinated burn care episodes, driving hospital investment in outpatient wound management infrastructure to capture shared savings.
- Telemedicine Triage Networks:Regional trauma systems are deploying store-and-forward imaging platforms to extend burn specialist consultation into rural emergency departments without maintaining full-time surgical rosters.
- Sun Belt Population Concentration:Texas, Florida, and Arizona trauma catchment areas are expanding as demographic migration increases thermal injury incidence in high-temperature industrial and residential settings.
Market Restraints
- Skin Substitute Cost Volatility:Advanced biological dressings derived from neonatal fibroblasts and collagen matrices carry per-application costs exceeding standard autograft procedures by substantial multiples, constraining adoption in cost-sensitive Medicaid populations.
- Burn Surgeon Supply Concentration:Fellowship-trained burn surgeons cluster in verified academic medical centers, leaving community hospitals dependent on locum tenens coverage or general plastic surgery consultation for moderate injuries.
- ABA Verification Barriers:American Burn Association verification requirements for continuous nursing ratios and on-site operating suite availability create capital barriers exceeding general ICU construction costs.
Strategic Opportunities
- Post-Acute Rehabilitation Integration:Scar management and functional restoration services remain fragmented between acute hospitals and outpatient therapy networks, creating white space for coordinated step-down facilities.
- Home-Based Negative-Pressure Therapy:Portable vacuum-assisted closure devices enable earlier discharge for partial-thickness injuries, expanding addressable patient volume beyond traditional inpatient bed constraints.
- Pediatric Network Extension:Shriners Hospitals for Children maintains non-urban referral infrastructure that commercial systems can leverage through affiliation agreements for complex pediatric reconstruction cases.
Industry Challenges
- Burn Surgeon Workforce Pipeline:Fellowship positions in burn surgery have contracted as trainees gravitate toward cosmetic and reconstructive subspecialties with more predictable lifestyle and compensation profiles.
- Legacy EHR Integration:Specialized wound documentation modules for total body surface area calculation and graft tracking often require manual interface with enterprise electronic health record platforms, creating workflow friction.
- Multidisciplinary Coordination Complexity:Optimal outcomes for electrical and chemical injuries require synchronized input from trauma surgery, toxicology, ophthalmology, and hand surgery services that resist standardized care pathway implementation.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | US Burn Care Centers Market |
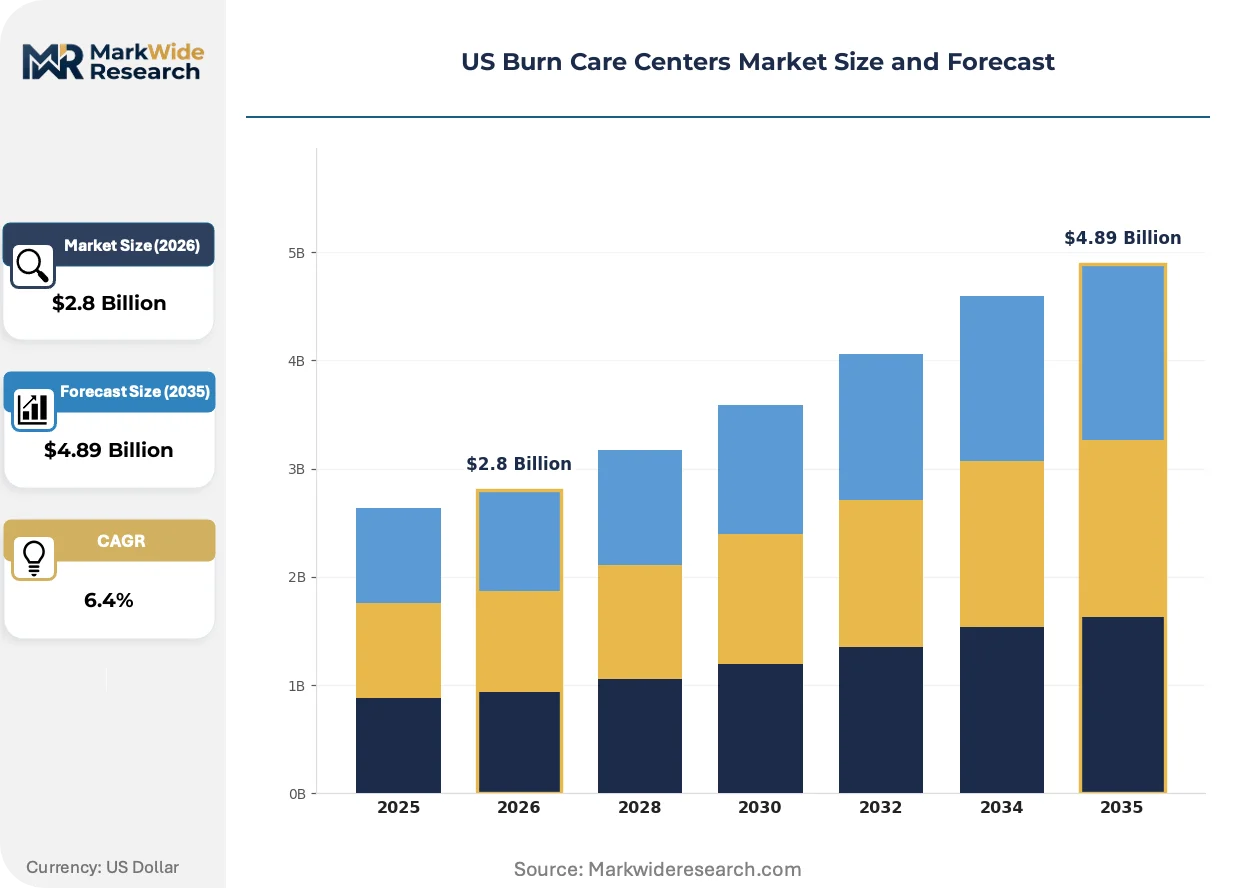
| Market Size in 2026 | $2.8 Billion |
| Market Size in 2035 | $4.89 Billion |
| CAGR (2026 – 2036) | 6.4% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Care Setting: Outpatient Clinics, Inpatient Facilities, Specialty Burn Units, Rehabilitation Centers Patient Type: Pediatric Patients, Adult Patients, Geriatric Patients, Trauma Patients Treatment Modality: Wound Care, Surgical Intervention, Pain Management, Psychological Support Equipment Type: Dressings, Grafting Instruments, Monitoring Devices, Surgical Equipment |
| Companies Covered | LAC+USC Medical Burn Center, Tampa General Hospital, MedStar Washington Hospital Center, St. Barnabas Burn Center, University of Chicago Burn Center, Parkland Memorial Hospital Regional Burn Center, University of Miami Jackson Memorial Hospital Burn Center, Brigham and Women's Hospital Burn Center, Shriners Hospitals for Children, Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
US Burn Care Centers Market Strategic Shifts & Innovations
Biosynthetic skin substitutes and remote monitoring platforms are converging to compress length-of-stay metrics while expanding the treatable injury severity threshold outside traditional inpatient settings.
Decellularized dermal matrices derived from porcine and bovine sources are absorbing market share from autologous split-thickness grafting in partial-thickness burn management. Community hospital burn units in Texas and Florida are adopting these products to reduce donor site morbidity and operative time. The technology is absorbing surgical capacity that previously required dedicated operating room block time, enabling smaller facilities to manage moderate injuries without full grafting infrastructure.
CMS Inpatient Prospective Payment System refinements are recalibrating relative weight values for burn-specific diagnosis-related groups, compressing reimbursement for uncomplicated thermal injuries while preserving enhanced payments for complex multi-trauma cases. Hospital systems are responding by stratifying patient triage protocols to route moderate injuries toward observation status or outpatient surgical centers. The policy shift most acutely affects standalone burn units without sufficient surgical volume to absorb fixed cost structures under revised payment weights.
Regional trauma networks are consolidating burn referral decisions through centralized telemedicine hubs that displace traditional physician-to-physician consultation patterns. Emergency departments in non-verified facilities now transmit digital wound photographs to academic center specialists before initiating transfer protocols. This behavioral shift concentrates surgical volume in verified centers while reducing unnecessary inter-facility transfers, with the most pronounced adoption visible across Arizona and New Mexico catchment areas where geographic distances previously drove default transfer behavior.
US Burn Care Centers Market Segmentation
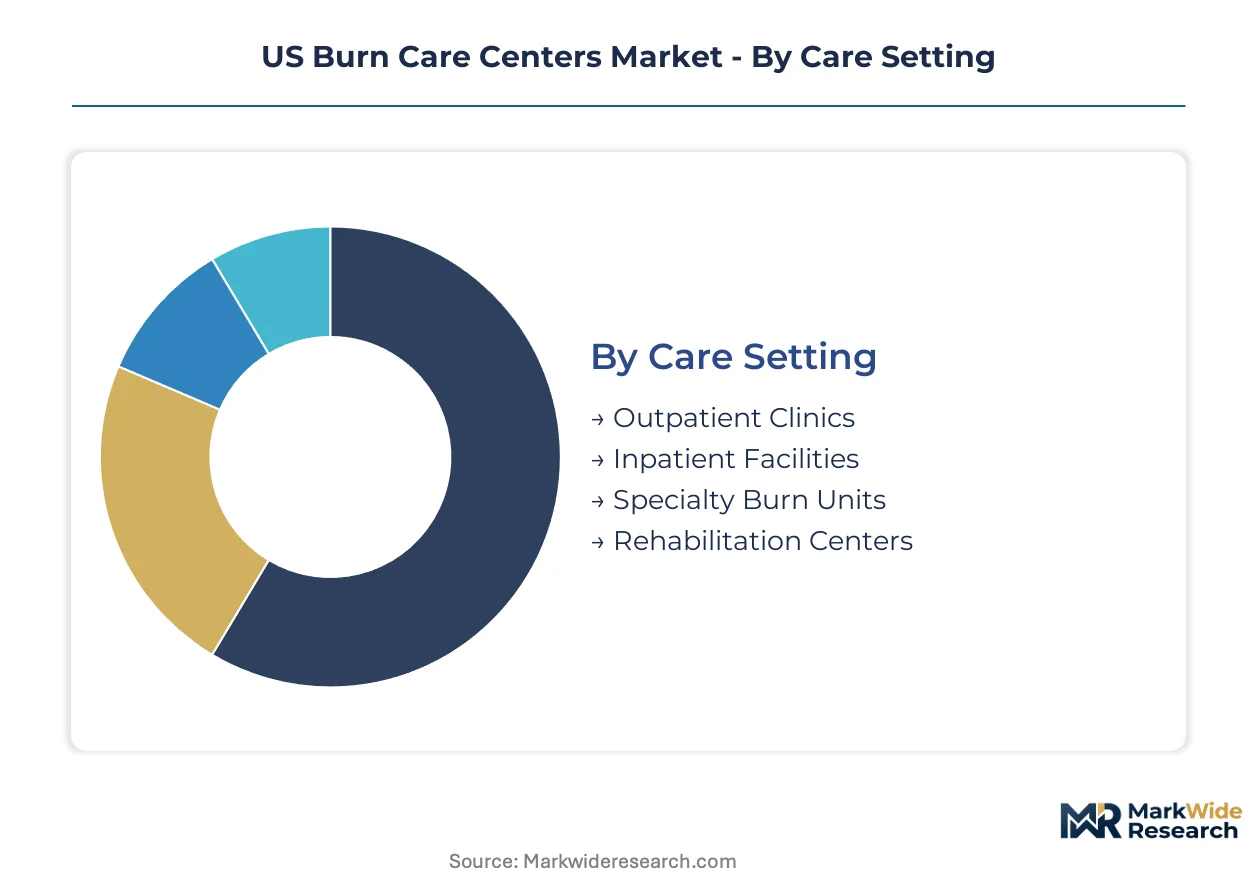
Burn care economics diverge sharply across care settings and patient populations. Medicare reimbursement tiers and ABA verification requirements create distinct margin profiles that reshape capital allocation decisions.
Care Setting:
ABA verification standards impose escalating capital burdens from outpatient through inpatient tiers, with CMS reimbursement weights tracking these compliance costs.
- Outpatient Clinics:These facilities deliver debridement, dressing changes, and scar management without overnight admission. Demand clusters in Sun Belt metros where biosynthetic dressings and portable negative-pressure devices enable earlier discharge from acute settings.
- Inpatient Facilities:General hospitals with dedicated burn beds provide acute resuscitation and staged grafting procedures. Texas and Florida health systems are expanding this capacity as trauma designation requirements tighten across their respective state health departments.
- Specialty Burn Units:ABA-verified centers maintain continuous nursing ratios and on-site operating suites for complex injuries. Parkland Memorial and University of Miami Jackson Memorial anchor regional referral networks through Level I verification status.
- Rehabilitation Centers:Post-acute facilities focus on functional restoration and contracture prevention. Shriners Hospitals for Children sustains pediatric-focused rehabilitation infrastructure across non-urban catchments.
Leading the category by volume: Inpatient Facilities. Growing fastest: Outpatient Clinics.
Patient Type:
Pediatric cases command premium reimbursement through dedicated DRG weights, while geriatric volumes strain fixed cost structures due to comorbidity complexity.
- Pediatric Patients:Children require specialized airway management and fluid resuscitation protocols distinct from adult algorithms. Shriners maintains national network dominance through non-urban referral infrastructure and donor-subsidized care models.
- Adult Patients:Working-age adults with occupational thermal and electrical injuries generate the highest surgical case mix. OSHA workplace safety enforcement in Texas manufacturing and Arizona construction sectors shapes injury severity distributions.
- Geriatric Patients:Elderly patients present elevated mortality risk from smaller total body surface area burns due to skin thinning and cardiovascular comorbidity. Medicare Advantage penetration rates in Florida and California determine payer mix for this segment.
- Trauma Patients:Multi-trauma cases with concomitant burn injuries require coordinated trauma surgery and burn specialist input. CMS maintains enhanced reimbursement weights for these complex episodes under revised IPPS calculations.
Dominant by revenue: Adult Patients. Expanding most quickly: Geriatric Patients.
Treatment Modality:
FDA device approvals and CMS coverage determinations segment available interventions by reimbursement certainty.
- Wound Care:Advanced biological dressings derived from neonatal fibroblasts and collagen matrices reduce operative burden. Cost volatility constrains adoption in Medicaid-dominant patient populations.
- Surgical Intervention:Autologous grafting and microvascular flap reconstruction restore functional and cosmetic outcomes. Fellowship-trained surgeon concentration limits geographic availability outside verified academic centers.
- Pain Management:Opioid-sparing protocols incorporating regional anesthesia and adjunctive medications address acute and chronic pain trajectories. DEA scheduling requirements shape medication availability.
- Psychological Support:Post-traumatic stress and body image interventions address long-term quality of life. Integration with acute care episodes remains fragmented across most health systems.
Highest margin pool: Surgical Intervention. Gaining share fastest: Wound Care.
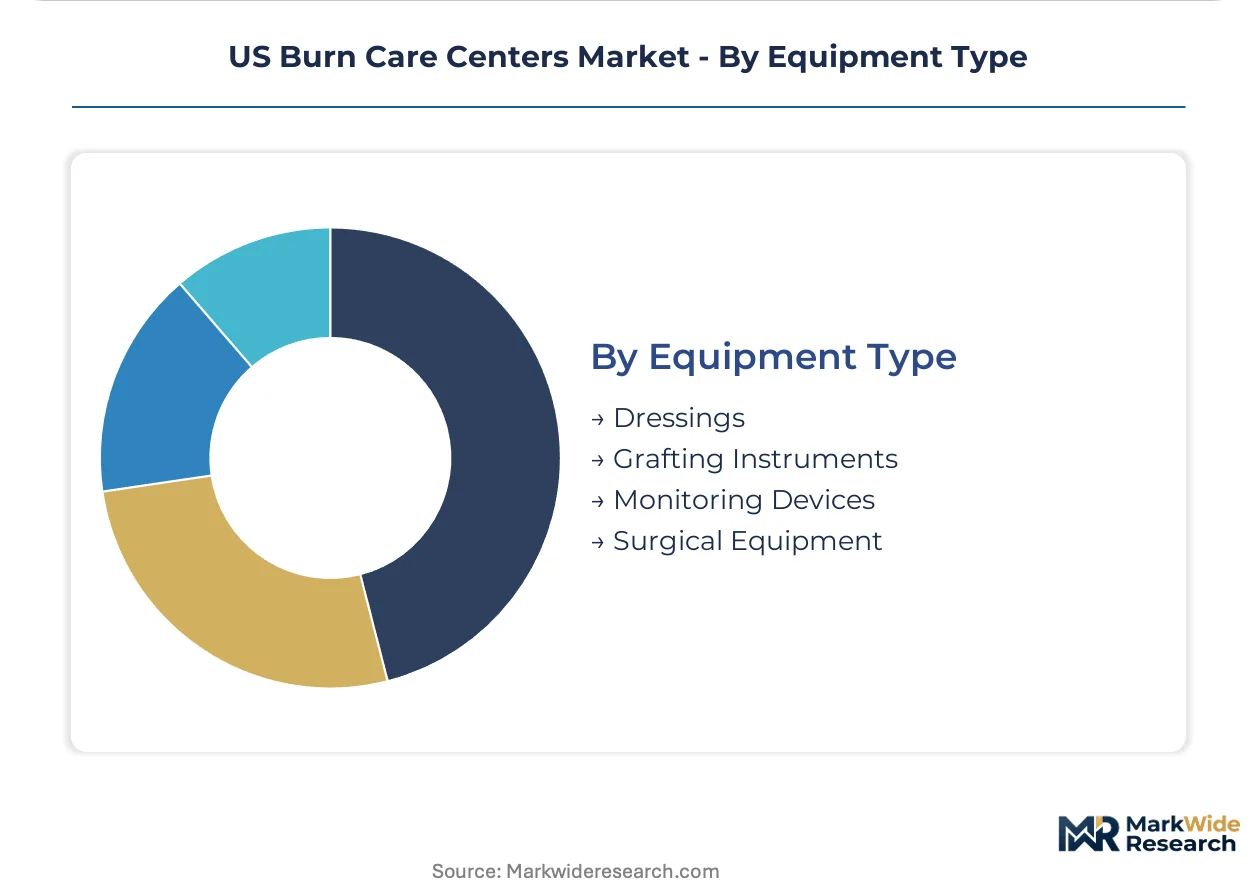
Equipment Type:
Supply chain concentration for advanced biological products creates procurement leverage disparities between large health systems and standalone burn units.
- Dressings:Biosynthetic and decellularized matrices absorb surgical capacity previously requiring autograft procedures. Texas community hospitals adopt these products to manage moderate injuries without full grafting infrastructure.
- Grafting Instruments:Dermatome and meshing devices enable standardized split-thickness harvest. Equipment standardization supports training efficiency across expanding regional networks.
- Monitoring Devices:Continuous hemodynamic and tissue perfusion monitoring guides resuscitation endpoints. Integration with enterprise EHR platforms requires specialized wound documentation modules.
- Surgical Equipment:Operating suites require dedicated instrumentation for excision and reconstruction. ABA verification mandates on-site availability rather than shared general surgery resources.
Largest procurement volume: Dressings. Steepest technology shift: Monitoring Devices.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Texas anchors US burn care capacity through Dallas-Fort Worth and Houston trauma corridors, where industrial thermal injury incidence and aging infrastructure drive replacement investment.
Texas
Petrochemical refining and oilfield operations along the Gulf Coast generate concentrated occupational burn trauma. OSHA Process Safety Management enforcement shapes injury prevention protocols across Houston Ship Channel facilities. Parkland Memorial Hospital Regional Burn Center in Dallas maintains Level I verification status and helicopter transport agreements covering North Texas catchments.
Florida
Geriatric scald injuries from residential settings dominate admission patterns as Medicare Advantage penetration deepens. State trauma designation requirements from the Florida Department of Health tighten licensing standards for new burn unit development. University of Miami Jackson Memorial Hospital Burn Center competes on complex reconstruction cases through microvascular flap capabilities in South Florida.
California
Wildland-urban interface fires and agricultural thermal injuries sustain demand across Central Valley and Southern California. Cal/OSHA workplace safety standards govern agricultural worker protection and injury reporting thresholds. Grossman Burn Center in Los Angeles and regional academic centers maintain verified capacity serving Pacific Coast trauma networks.
Arizona
Extreme heat exposure and construction sector electrical injuries concentrate Phoenix-Tucson patient volumes. Arizona Department of Health Services trauma designation requirements structure regional referral hierarchies. Telemedicine triage hubs now connect rural emergency departments to Phoenix-based specialists before transfer decisions.
New York Metro
Multi-trauma cases from industrial accidents and residential fires sustain academic medical center admission patterns. New York State Department of Health certificate-of-need regulations constrain new burn bed construction in downstate regions. St. Barnabas Burn Center and metropolitan academic anchors serve dense urban catchments with complex case mixes.
US Burn Care Centers Market Key Industry Players
Capital-heavy academic medical centers compete with asset-light specialty networks for regional referral dominance. The market structures around ABA verification tiers, with Level I centers capturing complex surgical episodes while community hospitals manage moderate injuries through telemedicine-backed protocols. Three archetypes dominate: verified academic anchors, pediatric specialty networks, and regional trauma system integrators. Consolidation through hospital system affiliation and telemedicine network expansion represent the primary competitive vectors reshaping market access.
Among verified academic anchors, Parkland Memorial Hospital Regional Burn Center and University of Miami Jackson Memorial Hospital Burn Center exemplify the capital-intensive verification tier sustaining regional referral monopolies. Shriners Hospitals for Children occupies a distinct position as a pediatric-focused network leveraging donor-subsidized infrastructure across non-urban catchments. These three organizations represent the structural poles around which regional trauma systems reorganize patient flows and surgical capacity.
| Leading Market Players |
|---|
| LAC+USC Medical Burn Center |
| Tampa General Hospital |
| MedStar Washington Hospital Center |
| St. Barnabas Burn Center |
| University of Chicago Burn Center |
| Parkland Memorial Hospital Regional Burn Center |
| University of Miami Jackson Memorial Hospital Burn Center |
| Brigham and Women's Hospital Burn Center |
| Shriners Hospitals for Children |
| Others |
Cost & Logistics Intelligence
Fellowship-trained burn surgeon concentration in Texas and Florida academic centers widens labor-cost differentials between ABA-verified units and community hospitals, forcing pricing-tier spreads that stratify access to complex grafting procedures.
Pricing Analysis
Episode-of-care reimbursement anchors US burn care pricing, with CMS bundled payment models compressing margins for uncomplicated thermal injuries while preserving enhanced weights for multi-trauma cases. Price differentiation separates Level I verified centers commanding premium surgical episode rates from observation-status facilities managing moderate injuries through telemedicine protocols. Cost compression in outpatient wound care is intensifying as biosynthetic dressings displace operative grafting for partial-thickness injuries. Medicaid-dominant populations exhibit highest price sensitivity to advanced biological dressing costs, while Medicare Advantage penetration in Sun Belt metros reduces out-of-pocket exposure for geriatric volumes.
Supply Chain Analysis
Single-source vulnerability sits with neonatal fibroblast-derived biological dressings manufactured through concentrated US biologics production networks. Advanced wound care products draw from domestic tissue processing facilities and porcine-derived decellularized matrix suppliers in the US and Switzerland. Supply chain risk centers on FDA lot-release bottlenecks for cell-based therapies that delay availability during demand surges. Distribution runs through GPO contracts and hospital system central procurement offices, with Shriners Hospitals for Children maintaining separate donor-subsidized supply channels for pediatric cases.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
US burn care is consolidating into three-tier verification hierarchies, with CMS reimbursement compression forcing standalone community units toward affiliation or exit.
For Market Incumbents: Anticipate telemedicine network expansion as the primary defensive perimeter, extending specialist consultation reach without proportional surgeon headcount growth. Lock in backward integration into outpatient wound management infrastructure to capture shared savings under BPCI-A models. Counter biosynthetic dressing cost volatility through multi-source procurement agreements with both domestic and Swiss matrix suppliers. For New Entrants and Emerging Players: Telemedicine triage platforms represent the most penetrable entry vector, enabling rural emergency departments to access verified center expertise without ABA verification capital burdens. Target post-acute rehabilitation integration as fragmented scar management services create white space for coordinated step-down facilities. Pursue affiliation agreements with Shriners pediatric networks to leverage existing non-urban referral infrastructure. For Investors and Strategic Acquirers: Re-rating potential sits with regional trauma system integrators given CMS Innovation Center model expansion accelerating coordinated care episode capture. Five-to-ten year viability favors health systems with demonstrated outpatient volume migration and negative-pressure therapy home deployment capabilities. Monitor ABA verification standard evolution toward outpatient metrics as the signal for reimbursement unbundling of wound care device payments.| Strategic Initiative | Industry Significance |
|---|---|
| Telemedicine Triage Network Expansion | Extends Parkland Memorial-level specialist access to rural Texas emergency departments without full surgical rosters. |
| Outpatient Wound Management Infrastructure | Captures CMS shared savings under BPCI-A through biosynthetic dressing protocols and remote monitoring platforms. |
| Post-Acute Rehabilitation Integration | Addresses fragmented scar management between acute hospitals and therapy networks across Sun Belt metros. |
| Pediatric Network Affiliation | Leverages Shriners donor-subsidized infrastructure for complex reconstruction cases outside urban academic centers. |
| Home-Based Negative-Pressure Therapy Deployment | Expands treatable patient volume beyond inpatient bed constraints through portable vacuum-assisted closure devices. |
Research Approach
Multi-period observation of ABA verification status changes, CMS reimbursement rule refinements, and telemedicine adoption curves anchored the trend analysis, supplemented by interviews with burn surgeons, hospital procurement managers, GPO contract specialists, and CMS policy researchers. Secondary validation drew from CMS Medicare cost reports, ABA facility verification databases, FDA 510(k) clearance records for skin substitutes, and state health department trauma designation filings. Bottom-up facility capacity modeling triangulated against top-down health system expenditure estimates.
Input-output matrices mapped patient volume flows across care settings, treatment modalities, and payer mixes throughout the forecast period. Segmentation dimensions modeled included care setting tier, patient age cohort, treatment modality category, and regional trauma network structure. CAGRs derived from regression analysis of historical bed expansion patterns and reimbursement weight trajectory projections. Workforce pipeline constraints and biosynthetic dressing cost curves served as industry-specific forecast inputs.
The model holds under stable CMS Innovation Center program continuity and ABA verification standard gradualism; deviation in Medicare Advantage penetration rates or FDA accelerated approval pathways for advanced biological products would shift volume and value distributions. Forecasts reflect documented assumptions regarding telemedicine reimbursement parity and state trauma designation tightening timelines. Outcomes are best read as a band of plausibility, not a single trajectory.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Wound Care
Wound Cleanser Products Market
Wound Care
Post-Operative Wound Treatment Market
Wound Care
Advanced Wound Care and Dressings Market
Wound Care
Dental Wound Dressings Market
Wound Care
Philippines Wound Care Market
Wound Care
United States Negative Pressure Wound Therapy Market
Wound Care
South Korea Wound Care Market
Wound Care
Europe Negative Pressure Wound Therapy Market
Wound Care
Antimicrobial Wound Dressings Market
Wound Care
Topical Wound Agents Market
Wound Care
Wound Closure Market
Wound Care
Liquid Bandages Market
Wound Care
Moist Wound Dressings Market
Wound Care
Wound Healing Supplement Market
Wound Care
US Wound Care Management Devices Market
Wound Care
Wound Management Market