
 US Academic Medical Centers Market | 2026-2036
US Academic Medical Centers Market Size, Share, and Industry Trends Forecast 2026-2036
US Academic Medical Centers Market Insights
Software-defined clinical analytics is hardening into a core revenue layer for academic medical centers, shifting value capture from episodic procedures to continuous data monetization. Mayo Clinic leverages its longitudinal patient registry to anchor multi-site research partnerships. Johns Hopkins Hospital sustains competitive differentiation through deep specialization in gene therapy protocols. Massachusetts General Hospital dominates translational research licensing, converting laboratory discoveries into commercial therapeutic platforms.
Academic medical centers constitute tertiary care institutions integrated with accredited medical schools and federally funded research programs, typically maintaining bed capacities exceeding 400 and operating Level I trauma verification alongside NIH-designated Cancer Center status. Their primary purpose spans clinician training, biomedical investigation, and advanced patient care for complex disease presentations. Inpatient Care represents the mature revenue base where reimbursement compression is most acute, while Telemedicine emerges as the fastest-expanding service modality reshaping ambulatory access patterns. Healthcare Analytics concentrates margin pools through predictive risk stratification and operational efficiency tools deployed across enterprise EHR environments.
FDA oversight of investigational new drugs and CMS reimbursement policy through the Inpatient Prospective Payment System directly shape clinical trial economics and service line viability for these institutions. HIPAA privacy requirements and the 21st Century Cures Act interoperability mandates impose substantial compliance infrastructure costs while enabling data liquidity for research consortia. Stakeholders must monitor how NIH funding appropriations and Medicare graduate medical education payment reforms recalibrate the financial architecture sustaining teaching and research missions.
Market Dynamics
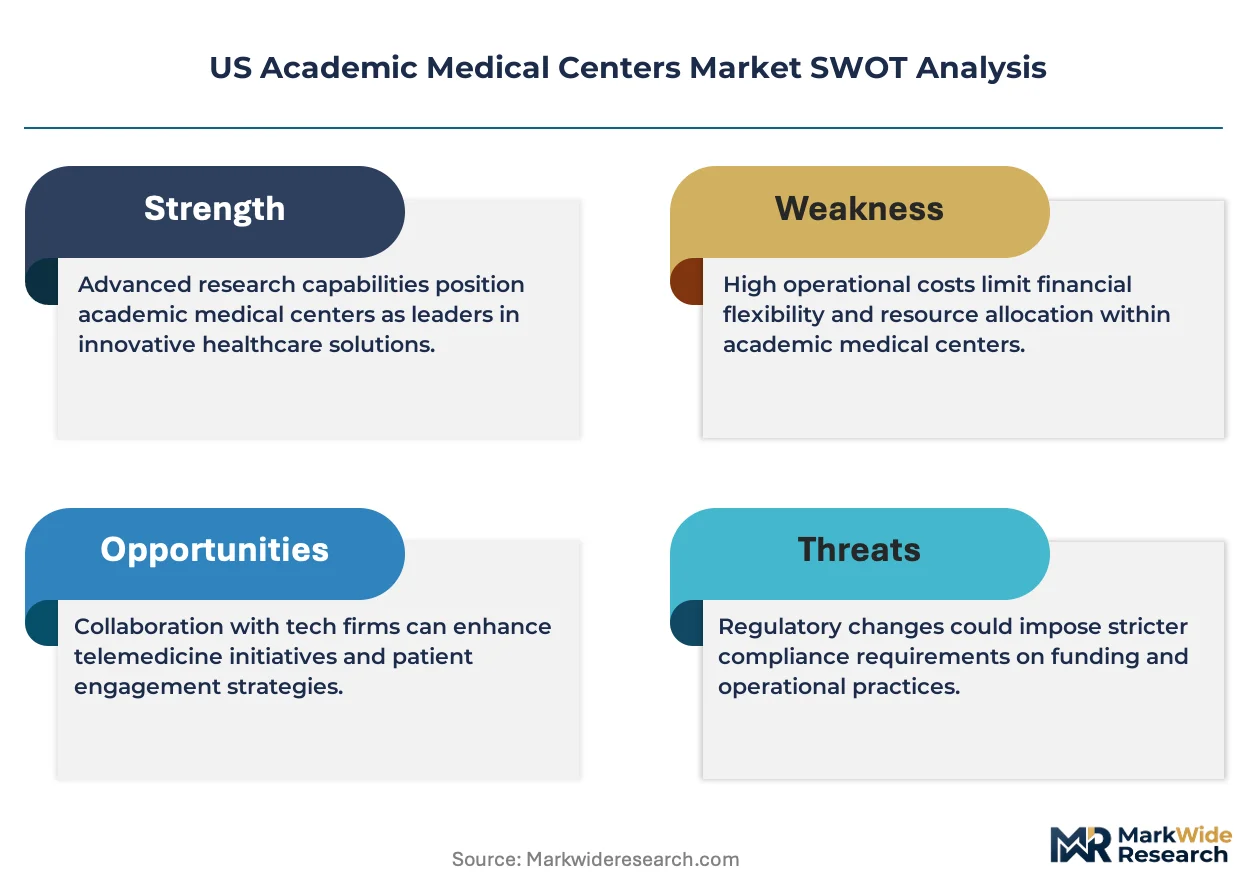
Federal reimbursement compression through CMS Inpatient Prospective Payment System revisions is forcing academic medical centers to restructure cost bases while preserving research and teaching missions. NIH grant volatility adds further uncertainty to operational planning cycles.
Growth Catalysts
- NIH Research Funding:Expanding appropriations for precision medicine and gene therapy trials attract principal investigators and industry partnerships to major AMC campuses.
- Telemedicine Infrastructure:CMS expanded reimbursement for remote patient monitoring creates new ambulatory revenue streams beyond traditional hospital walls.
- California Biomedical Corridor:Concentrated venture capital and biotech presence around Stanford and UCSF accelerates translational research commercialization.
Market Restraints
- Specialized Labor Shortages:Constrained supply of board-certified academic physicians and PhD researchers drives compensation inflation across clinical and research tracks.
- Regulatory Compliance Burden:HIPAA privacy rule enforcement and 21st Century Cures Act interoperability mandates impose fixed IT infrastructure costs regardless of patient volume.
- Reimbursement Compression:Medicare graduate medical education payment caps limit expansion of residency programs that feed clinical staffing pipelines.
Strategic Opportunities
- Healthcare Analytics Licensing:Proprietary algorithms developed from longitudinal patient registries generate recurring revenue through SaaS models sold to community hospital networks.
- FDA Breakthrough Therapy Designation:Expedited review pathways for cell and gene therapies position AMCs as preferred trial sites for sponsor companies seeking accelerated approval.
- Remote Clinical Trial Models:Decentralized study designs using wearable devices and home nursing extend geographic recruitment reach beyond traditional catchment areas.
Industry Challenges
- EHR Integration Complexity:Legacy electronic health record architectures resist seamless data extraction for research warehousing and external interoperability requirements.
- Principal Investigator Retention:Competition from well-funded biotech startups and foreign research institutions threatens stability of established laboratory programs.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | US Academic Medical Centers Market |
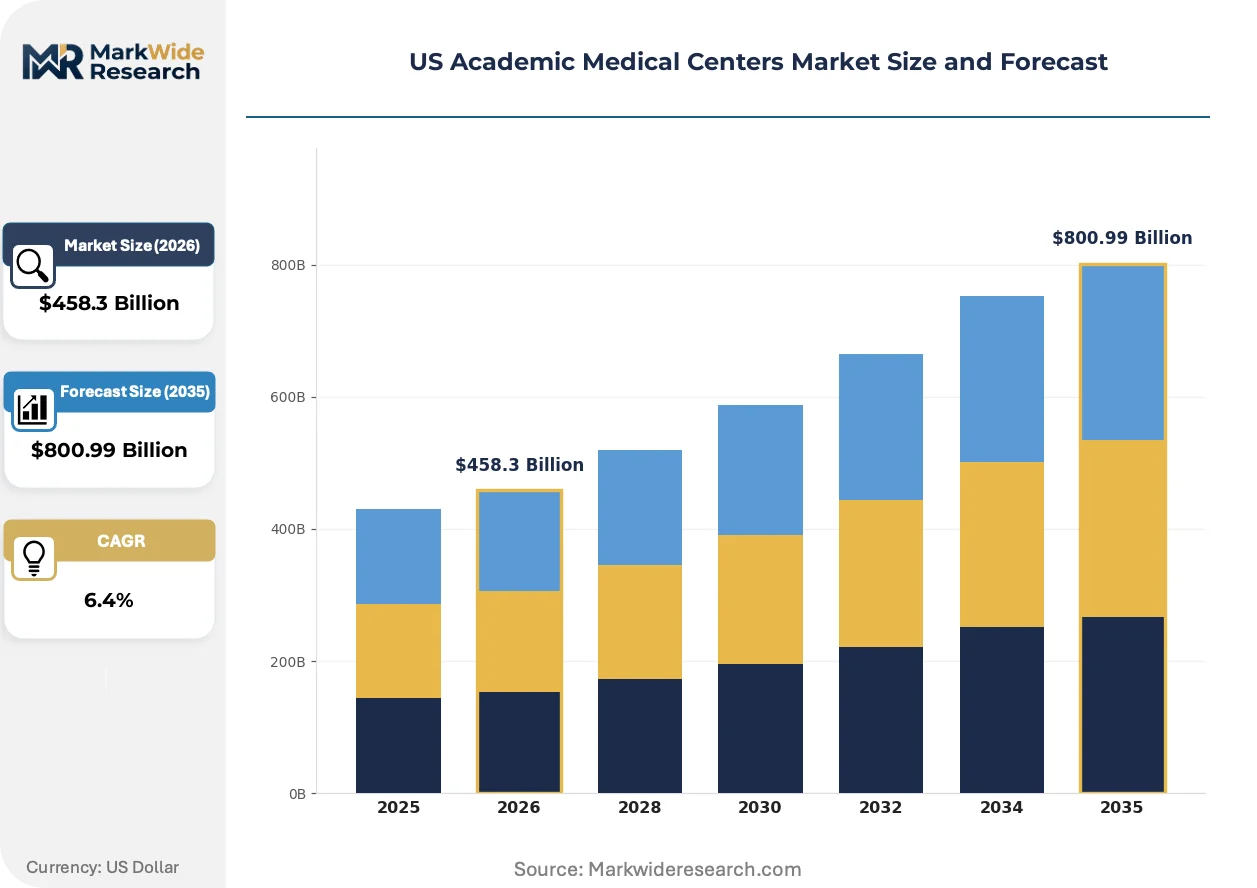
| Market Size in 2026 | $458.3 Billion |
| Market Size in 2035 | $800.99 Billion |
| CAGR (2026 – 2036) | 6.4% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | End User: Teaching Hospitals, Research Institutions, Medical Schools, Specialty Clinics Service Type: Inpatient Care, Outpatient Services, Surgical Procedures, Diagnostic Imaging Technology: Telemedicine, Electronic Health Records, Clinical Decision Support, Healthcare Analytics Funding Source: Government Grants, Private Donations, Tuition Fees, Sponsored Research |
| Companies Covered | Mayo Clinic, Johns Hopkins Hospital, Massachusetts General Hospital, Stanford Health Care, UCSF Medical Center, Cleveland Clinic, New York-Presbyterian Weill Cornell Medical Center, Vanderbilt University Medical Center, Cedars-Sinai Health System, Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
US Academic Medical Centers Market Trends and Innovations
Software-defined clinical infrastructure is redrawing competitive boundaries between academic medical centers and technology platforms. Data monetization models now rival procedure volume as a determinant of institutional valuation.
Artificial intelligence diagnostic tools are consolidating radiology and pathology workflows into centralized reading platforms. Major AMCs deploy FDA-cleared algorithms for mammography screening and chest X-ray triage across multi-site networks. This consolidation compresses specialist labor requirements while standardizing diagnostic quality across community affiliates.
CMS Inpatient Prospective Payment System annual rulemaking now incorporates quality metrics tied to readmission penalties and value-based purchasing adjustments. AMCs with elevated case complexity indices face disproportionate financial exposure. Massachusetts and California systems have responded by investing in post-acute care networks to manage total episode costs.
Research sponsorship procurement now favors institutions with integrated data science capabilities over traditional clinical trial site metrics. Biopharma sponsors evaluate electronic health record interoperability and real-world evidence generation infrastructure as primary selection criteria. This behavioral shift concentrates trial awards within a narrow tier of AMCs that invested early in cloud-native research platforms.
US Academic Medical Centers Market Segmentation
Academic medical centers operate across multiple operational axes simultaneously, requiring granular segmentation to capture how clinical delivery, research infrastructure, and educational missions intersect. Each dimension reveals distinct margin profiles and capital intensity requirements that shape strategic positioning.
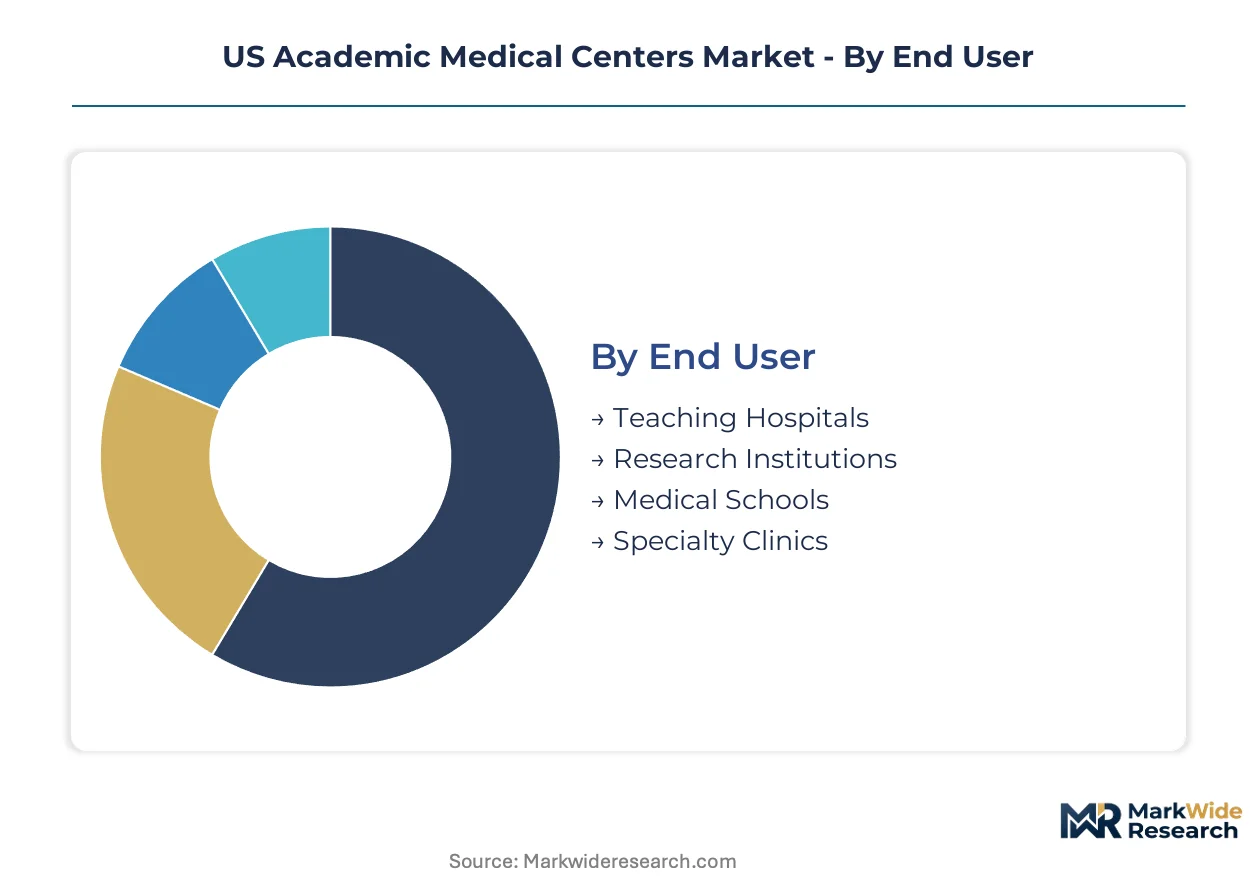
End User:
Technology integration depth varies sharply across institutional archetypes, with research intensity and patient acuity driving divergent IT and staffing specifications.
- Teaching Hospitals:These facilities combine Level I trauma certification with ACGME-accredited residency programs exceeding 1,000 trainees. CMS graduate medical education payments and disproportionate share hospital adjustments sustain operations across California's biomedical corridor and the Northeast academic belt. Reimbursement compression through Inpatient Prospective Payment System revisions forces continuous cost restructuring.
- Research Institutions:Standalone NIH-designated research centers without owned hospital assets rely on sponsored funding for 70-85% of operating budgets. Principal investigator retention depends on core facility access and institutional review board efficiency. Gene therapy and precision medicine consortia concentrate at Stanford and Johns Hopkins satellite campuses.
- Medical Schools:Preclinical education infrastructure requires anatomy laboratories and simulation centers with fixed capital costs regardless of enrollment fluctuations. Tuition revenue covers roughly 15-25% of total educational mission costs.
- Specialty Clinics:NCT-designated cancer centers and transplant institutes operate as semi-autonomous profit centers with dedicated philanthropy pipelines.
Teaching hospitals lead on scale; research institutions lead on momentum.
Service Type:
Revenue concentration and margin vulnerability distribute unevenly across the care continuum, with site-of-service arbitrage reshaping investment priorities.
- Inpatient Care:Mature revenue base with acute reimbursement compression through DRG-based payments. Complex case indices at Massachusetts General and Mayo Clinic sustain relative performance, but length-of-stay reduction imperatives constrain bed expansion. Post-acute integration investments aim to control total episode costs.
- Outpatient Services:Ambulatory surgical centers and infusion suites capture site-of-service differentials as CMS expands hospital-at-home waivers. Telemedicine integration enables geographic extension beyond traditional catchment areas.
- Surgical Procedures:Robotic platform standardization and enhanced recovery protocols reduce variation. Cardiac and orthopedic service lines concentrate at high-volume centers.
- Diagnostic Imaging:AI-augmented radiology workflows compress specialist labor requirements while standardizing quality across multi-site networks.
Inpatient care dominates current revenue; outpatient services claim the steepest expansion trajectory.
Technology:
Capital allocation intensity and implementation risk vary substantially across the digital infrastructure stack, with cloud-native architectures displacing legacy on-premise deployments.
- Telemedicine:CMS expanded reimbursement for remote patient monitoring and asynchronous consultations creates sustainable revenue outside hospital walls. Licensing requirements vary by state medical boards, complicating multi-state affiliate networks.
- Electronic Health Records:Epic and Cerner dominance creates interoperability constraints for research data extraction. 21st Century Cures Act mandates impose fixed compliance costs regardless of institutional scale.
- Clinical Decision Support:FDA-cleared algorithms for sepsis detection and medication dosing reduce adverse events while generating liability questions around algorithmic accountability.
- Healthcare Analytics:Predictive risk stratification tools and operational efficiency platforms concentrate margin pools. Proprietary algorithms from longitudinal registries enable SaaS licensing to community hospital networks.
Electronic health records anchor current infrastructure spend; healthcare analytics is gaining share fastest.
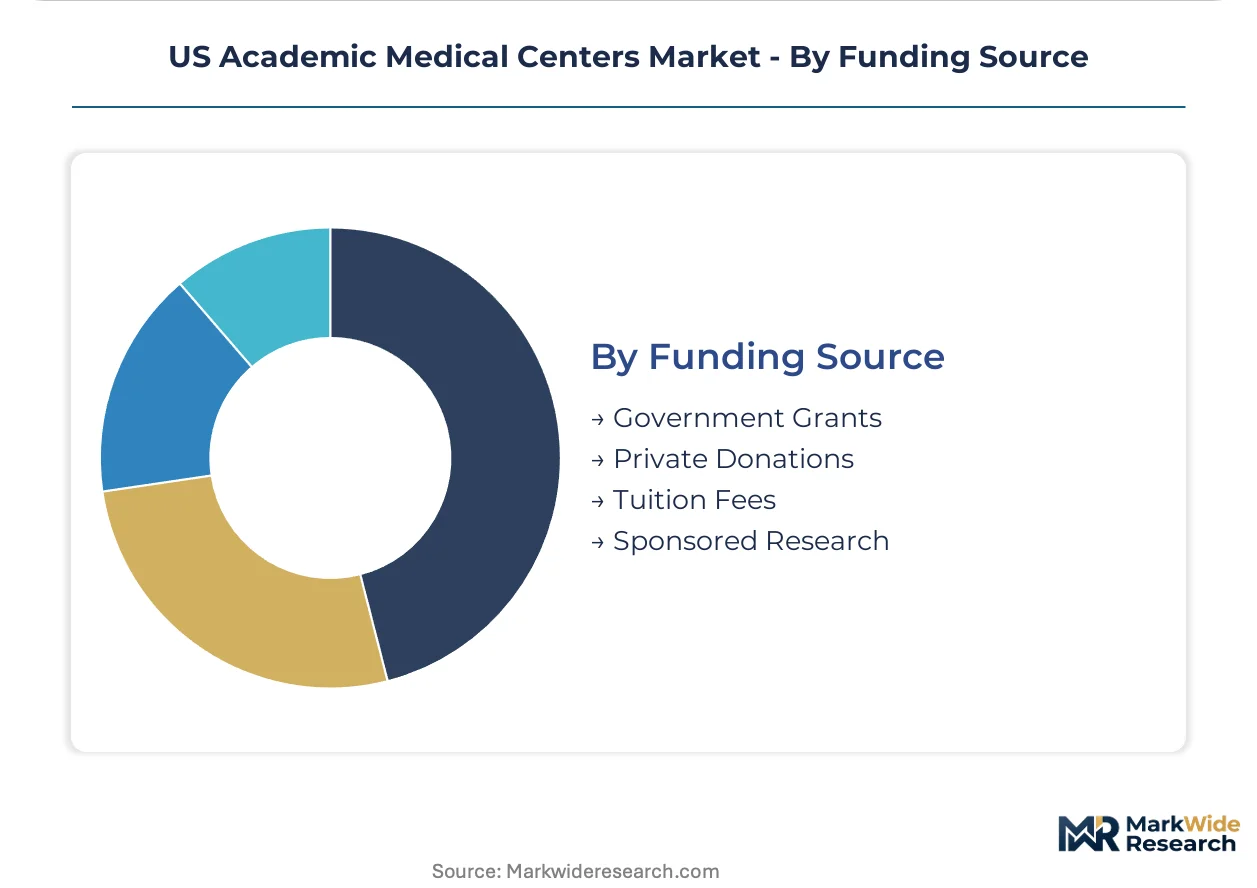
Funding Source:
Revenue stability and growth predictability diverge sharply across funding mechanisms, with federal appropriations cycles introducing operational planning uncertainty.
- Government Grants:NIH appropriations volatility affects principal investigator recruitment and core facility staffing. Precision medicine and gene therapy initiatives attract concentrated funding to California and Massachusetts corridors.
- Private Donations:Named endowments for cancer centers and cardiovascular institutes provide restricted revenue with donor stewardship obligations. Major gift cultivation cycles extend 18-36 months.
- Tuition Fees:Medical education debt loads approaching $250,000 per graduate constrain applicant pools and diversity objectives.
- Sponsored Research:Industry-sponsored trials favor institutions with integrated data science capabilities and real-world evidence generation infrastructure over traditional site metrics.
Government grants lead on scale; sponsored research leads on momentum.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Regulatory arbitrage in academic medical center economics manifests through state-level Medicaid expansion decisions and graduate medical education funding formulas that redistribute principal investigator talent across jurisdictions with favorable reimbursement environments.
California
NIH grant concentration and venture capital proximity drive precision medicine expansion across Stanford Health Care and UCSF Medical Center operations. The state's Medicaid 1115 waiver programs enable enhanced reimbursement for safety-net academic hospitals. The San Francisco Bay Area anchors gene therapy commercialization with biotech co-location advantages.
Massachusetts
Massachusetts General Hospital dominates translational research licensing with laboratory-to-therapeutic-platform conversion pipelines. The state's health reform legacy sustains above-average commercial insurance penetration supporting academic hospital cost structures. Greater Boston concentrates FDA breakthrough therapy trial density.
New York
New York-Presbyterian Weill Cornell Medical Center leverages metropolitan catchment scale for complex case referral networks. CMS Inpatient Prospective Payment System adjustments hit high-cost-of-labor markets disproportionately. The New York Metro corridor maintains residency program volume despite Medicare GME payment caps.
Ohio
Cleveland Clinic exports clinical protocols through international affiliate licensing. The state's Medicaid managed care restructuring pressures academic hospital operating margins. The Midwest biomedical corridor concentrates cardiac and orthopedic specialty volume.
Tennessee
Vanderbilt University Medical Center anchors regional referral patterns across the Southeast. State-level certificate-of-need regulations limit competitor entry in tertiary services. Nashville's health services corporate headquarters proximity facilitates industry-sponsored trial procurement.
US Academic Medical Centers Market Competitive Landscape
Branded specialists and contract manufacturers split share differently across segments, with integrated academic health systems commanding premium positioning in complex care while regional teaching hospitals compete on access and cost. Market structure concentrates around multi-site networks with NIH-designated Cancer Center status and Level I trauma verification. Three archetypes dominate: vertically integrated research-to-bedside platforms, specialty-focused high-acuity centers, and geographically distributed community-affiliated teaching networks. Principal competitive moves center on principal investigator recruitment through endowed chair funding and EHR interoperability investments that attract industry-sponsored trials.
Within the vertically integrated tier, Mayo Clinic, Johns Hopkins Hospital, and Stanford Health Care exemplify archetypes that convert longitudinal patient registries into multi-site research partnerships. These institutions occupy positions where data science capabilities and real-world evidence infrastructure determine biopharma sponsor selection criteria. Geographic distribution spans the Upper Midwest, Mid-Atlantic, and California biomedical corridor respectively.
| Leading Market Players |
|---|
| Mayo Clinic |
| Johns Hopkins Hospital |
| Massachusetts General Hospital |
| Stanford Health Care |
| UCSF Medical Center |
| Cleveland Clinic |
| New York-Presbyterian Weill Cornell Medical Center |
| Vanderbilt University Medical Center |
| Cedars-Sinai Health System |
| Others |
Pricing and Supply Chain Analysis
Captive integration into Epic and Cerner electronic health record ecosystems anchors supply positioning and pricing power for academic medical centers, with institutional scale determining discount tiers and implementation cost absorption. CMS reimbursement compression through Inpatient Prospective Payment System revisions feeds back into vendor consolidation decisions, favoring systems with sufficient capital reserves to negotiate enterprise-wide licensing.
Pricing Analysis
Direct-to-institution enterprise licensing dominates software procurement, with pricing stratifying across academic medical center, community hospital, and ambulatory network tiers based on bed count and research intensity. Brand premiums attach to FDA-cleared clinical decision support modules and proprietary analytics platforms developed from longitudinal registries. Cost compression in core EHR infrastructure intensifies as Epic and Cerner extend market dominance, squeezing margins for third-party interoperability vendors. Community hospital affiliates demonstrate highest price sensitivity, while NIH-designated Cancer Centers with dedicated philanthropy pipelines absorb premium pricing for specialized research modules.
Supply Chain Analysis
Single-source vulnerability sits with Epic Systems Corporation for integrated clinical and research infrastructure across the US academic medical center tier. Hardware components draw from Taiwan semiconductor fabrication, US-based server assembly, and Chinese medical device manufacturing for diagnostic peripherals. Tariff exposure runs through imported imaging equipment and precision medicine consumables. Distribution runs through direct vendor-to-institution contracts with professional services bundled, bypassing traditional healthcare distribution intermediaries for enterprise software deployments.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
The US academic medical centers market represents a late-cycle quality story as demand shifts toward integrated data science capabilities that attract biopharma sponsorship over traditional clinical trial metrics.
For Market Incumbents: Cement principal investigator retention through endowed chair funding and core facility access guarantees, countering poaching threats from well-funded biotech startups. Deepen backward integration into cloud-native research platforms to capture industry-sponsored trial awards that increasingly favor real-world evidence generation infrastructure over site capacity metrics.
For New Entrants and Emerging Players: Capture white-space opportunity in decentralized clinical trial infrastructure serving mid-tier academic medical centers lacking capital for in-house wearable device integration and home nursing networks. Telemedicine-enabled remote patient monitoring for rural affiliate hospitals offers the most penetrable entry point, with SaaS licensing models avoiding capital-intensive EHR replacement cycles.
For Investors and Strategic Acquirers: Roll-up economics work for regional teaching hospital networks with Level I trauma verification and ACGME-accredited residency programs because Medicare graduate medical education payment caps create distressed sellers seeking scale efficiencies. Long-term viability hinges on data monetization infrastructure that converts longitudinal patient registries into recurring analytics revenue. Watch NIH appropriations volatility as the primary inflection indicator for research-dependent valuations.
| Strategic Initiative | Industry Significance |
|---|---|
| Healthcare Analytics Licensing | Mayo Clinic's longitudinal registry anchors multi-site SaaS partnerships with community hospital networks. |
| FDA Breakthrough Therapy Designation | Massachusetts General Hospital's gene therapy protocols attract sponsor companies seeking accelerated approval pathways. |
| Telemedicine Infrastructure Expansion | Stanford Health Care's remote patient monitoring captures CMS reimbursement beyond traditional hospital walls. |
| Principal Investigator Endowment | Johns Hopkins Hospital's endowed chair funding counters biotech startup poaching of established laboratory programs. |
| Post-Acute Care Network Integration | California systems invest in episode cost control to manage readmission penalties under value-based purchasing. |
Research Methodology
Bottom-up service line modeling reconciled against top-down NIH funding and CMS reimbursement tracking forms the analytical core of this study. Primary interviews with chief medical information officers, biomedical research directors, GPO contracts managers, and biopharma clinical operations leads combined with secondary validation against FDA 510(k) filings, CMS Medicare cost reports, NIH RePORTER grant databases, and hospital procurement records. Triangulation between institutional financial disclosures and federal appropriations data ensures methodological rigor.
Input-output matrices map bed capacity, research intensity, and technology adoption across segmentation dimensions including end-user archetype, service modality, digital infrastructure tier, and funding source stability. CAGRs derive from regression analysis of historical NIH appropriations cycles, Medicare payment rulemaking trajectories, and telemedicine reimbursement expansion patterns. Forecast inputs incorporate principal investigator migration trends and EHR interoperability investment cycles as leading indicators of research sponsorship capture.
NIH funding volatility, CMS Inpatient Prospective Payment System revision timing, and gene therapy regulatory pathway uncertainty are the dominant revision risks to modeled projections. Forecasts reflect documented assumptions about federal reimbursement policy continuity and precision medicine investment sustainability. Outcomes are best read as a band of plausibility, not a single trajectory.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Medical Research
Global Human Liver Models Market
Medical Research
Malaria Vaccine Market
Medical Research
Lab Automation in Drug Discovery Market
Medical Research
Metabolomics Market
Medical Research
Epigenetics Market
Medical Research
Global in Vitro Lung Model Market
Medical Research
Methicillin-Resistant Staphylococcus Aureus (MRSA) Drugs Market
Medical Research
Antibody-Mediated Rejection Prevention Market
Medical Research
Medical Device Contract Research Organization Market
Medical Research
Human Osteoblasts Market
Medical Research
FFPE Tissue Samples Market
Medical Research
Clinical Genomics Market
Medical Research
Epigenomics Market
Medical Research
Global Patient Derived Xenograft Models Market
Medical Research
Cancer Mouse Models Market
Medical Research
Life Science R&D Infrastructure Outsourcing Market