
 US Gender Reassignment Surgery Market | 2026-2036
US Gender Reassignment Surgery Market Size, Share, and Industry Trends Forecast 2026-2036
US Gender Reassignment Surgery Market Insights
The US gender reassignment surgery market is rebalancing between boutique cosmetic practices and high-volume academic medical centers with multidisciplinary care teams. Mount Sinai Centre for Transgender Medicine and Surgery leverages its integrated psychiatric, endocrine, and surgical services to sustain patient throughput across the full transition pathway. Cleveland Clinic anchors its position through systematic outcomes tracking and fellowship-trained reconstructive teams. Mayo Clinic competes on geographic reach, operating transplant-grade sterile facilities across multiple states with established referral networks.
Gender reassignment surgery encompasses vaginoplasty, phalloplasty, breast augmentation, and hysterectomy performed under general anesthesia with hospital stays ranging from same-day discharge to five-day admissions depending on procedure complexity and complication risk. These interventions resolve gender dysphoria by aligning physical anatomy with gender identity, requiring hormonal priming and mental health clearance per WPATH standards. Phalloplasty commands the highest resource intensity and longest operative times, concentrating margin pools in hospitals with microsurgical flap expertise. Breast augmentation and hysterectomy are maturing toward ambulatory settings, while vaginoplasty remains split between specialty clinics and academic centers based on surgeon volume and insurance contracting.
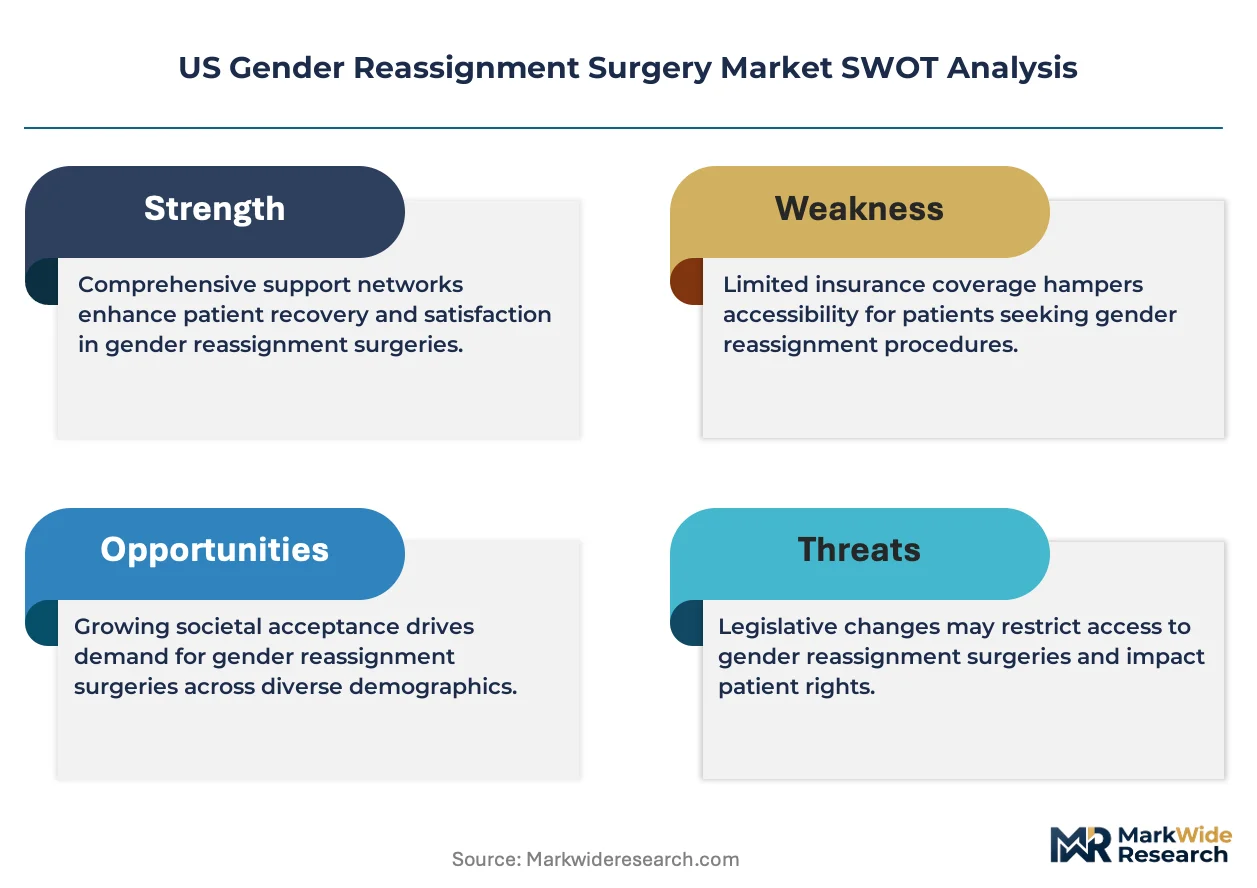
FDA regulates breast implant devices and tissue expanders used in chest reconstruction, while state Medicaid programs determine coverage eligibility through medical necessity criteria that vary by jurisdiction. CMS reimbursement schedules shape hospital investment decisions, particularly for inpatient stays exceeding two days. Stakeholders must monitor state legislative sessions for coverage expansion or restriction bills that directly alter addressable patient populations.
Market Dynamics
State Medicaid coverage expansions are redrawing patient access boundaries faster than hospital systems can scale surgical capacity, forcing academic medical centers to prioritize fellowship pipelines and insurance contracting over facility expansion.
Growth Catalysts
- WPATH Standards of Care:Version 8 protocols have broadened mental health clearance pathways, accelerating pre-surgical patient throughput at qualified centers.
- California Medicaid Expansion:Medi-Cal's removal of lifetime surgery caps has unlocked pent-up demand for vaginoplasty and phalloplasty procedures in the nation's largest state market.
- Robotic-Assisted Platforms:Da Vinci systems are shortening operative times for hysterectomy and orchiectomy, allowing same-day discharge protocols that expand surgical scheduling density.
Market Restraints
- Microsurgical Flap Scarcity:Phalloplasty requires specialized free-flap expertise concentrated in fewer than 40 US surgeons, creating procedural bottlenecks.
- Silicone Implant Volatility:Breast augmentation costs fluctuate with medical-grade silicone supply constraints and FDA-mandated safety study requirements.
- State Legislative Friction:Tennessee and Alabama have enacted Medicaid coverage exclusions that remove addressable populations from surgical queues.
Strategic Opportunities
- Telehealth Pre-Operative Pathways:Virtual mental health clearance and hormone monitoring are extending geographic reach into Mountain West and Great Plains states lacking specialized centers.
- IRA Hospital Infrastructure Funding:Federally subsidized facility upgrades enable transplant-grade sterile environments in secondary markets previously unable to support microsurgical programs.
- Ambulatory Hysterectomy Migration:Outpatient surgery centers in Texas and Florida are capturing breast augmentation and orchiectomy volume from inpatient settings.
Industry Challenges
- Fellowship Pipeline Constraints:Gender-affirming surgery training slots remain limited to 15-20 annual graduates across six ACGME-approved programs.
- Prior Authorization Complexity:Multi-layered insurer documentation requirements for phalloplasty create 90-180 day administrative delays that compress surgical calendar utilization.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | US Gender Reassignment Surgery Market |
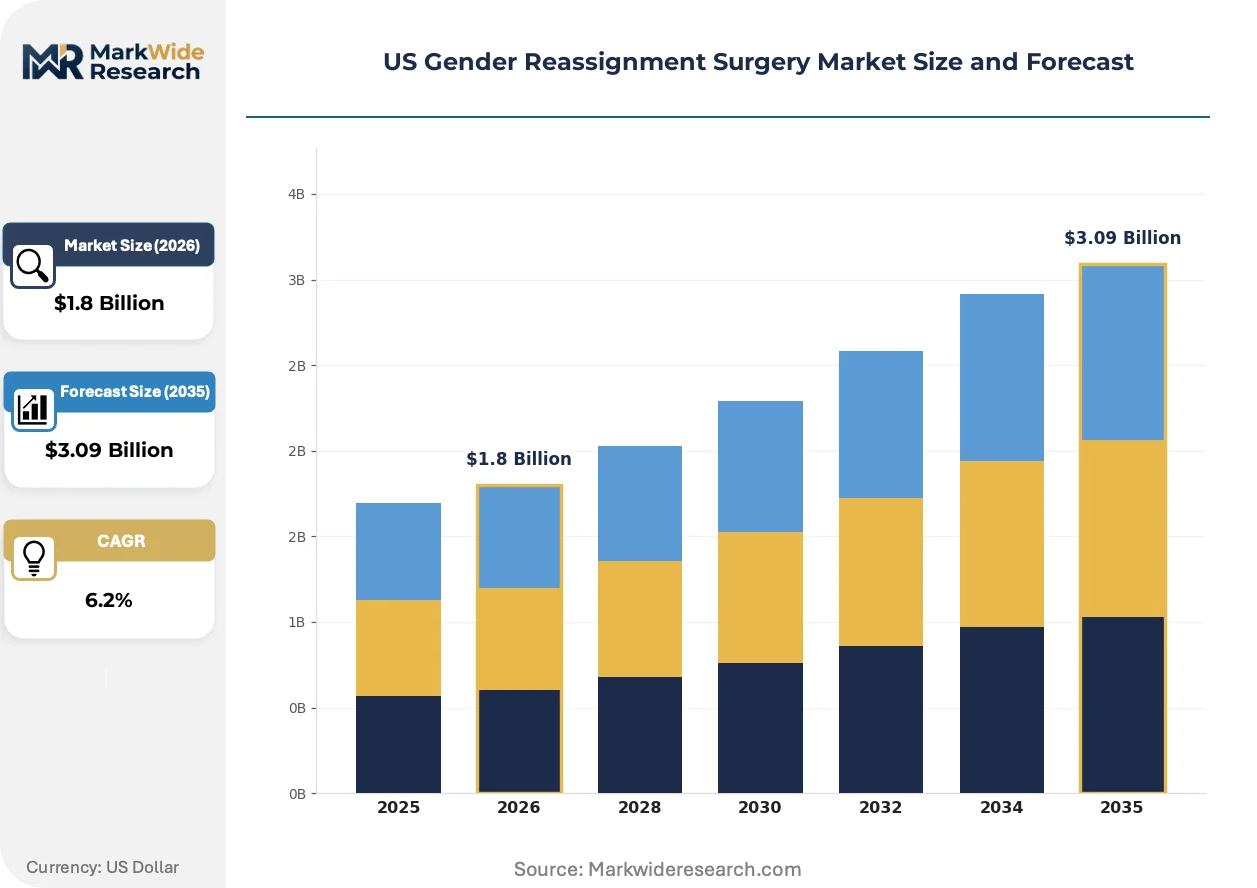
| Market Size in 2026 | $1.8 Billion |
| Market Size in 2035 | $3.09 Billion |
| CAGR (2026 – 2036) | 6.2% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Procedure Type: Vaginoplasty, Phalloplasty, Breast Augmentation, Hysterectomy Patient Demographics: Adults, Adolescents, Non-Binary Individuals, Transgender Women Healthcare Setting: Hospitals, Specialty Clinics, Ambulatory Surgical Centers, Private Practices Insurance Coverage: Medicaid, Medicare, Private Insurance, Self-Pay |
| Companies Covered | Rumer Cosmetic Surgery, Mount Sinai Centre for Transgender Medicine and Surgery, Cedars-Sinai, Boston Medical Center, The International Center for Transgender Care, Cleveland Clinic, Transgender Surgery Institute, The Johns Hopkins University, Mayo Clinic, Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
US Gender Reassignment Surgery Market Trends and Innovations
Peritoneal flap vaginoplasty techniques and 3D-printed surgical guides are compressing operative timelines while state-level policy experimentation creates divergent coverage landscapes.
Peritoneal pull-through vaginoplasty is decentralizing access by eliminating the need for full-thickness skin graft harvesting, reducing operative time from six to four hours. Community hospitals in Oregon and Washington are adopting this technique faster than academic centers, enabling standalone gender clinics to maintain patient volumes without microsurgical backup. The method is decentralizing procedure location from major metropolitan teaching hospitals to regional medical centers with standard laparoscopic capabilities.
CMS reimbursement schedule revisions for 2024 have elevated vaginoplasty from inpatient-only to outpatient-eligible status in select DRG classifications. This policy shift pressures hospitals to reconfigure surgical workflows toward 23-hour observation models rather than multi-day admissions. California and New York facilities are responding fastest, restructuring nursing ratios and discharge protocols to capture the revised payment differential.
Patient navigation through social media-informed provider selection is displacing traditional referral networks. Younger cohorts in Massachusetts and Illinois now prioritize surgeon-published outcome photography and peer forum testimonials over primary care referrals. This behavioral shift concentrates volume with transparency-oriented practices while marginalizing hospitals without digital presence investment.
US Gender Reassignment Surgery Market Segmentation
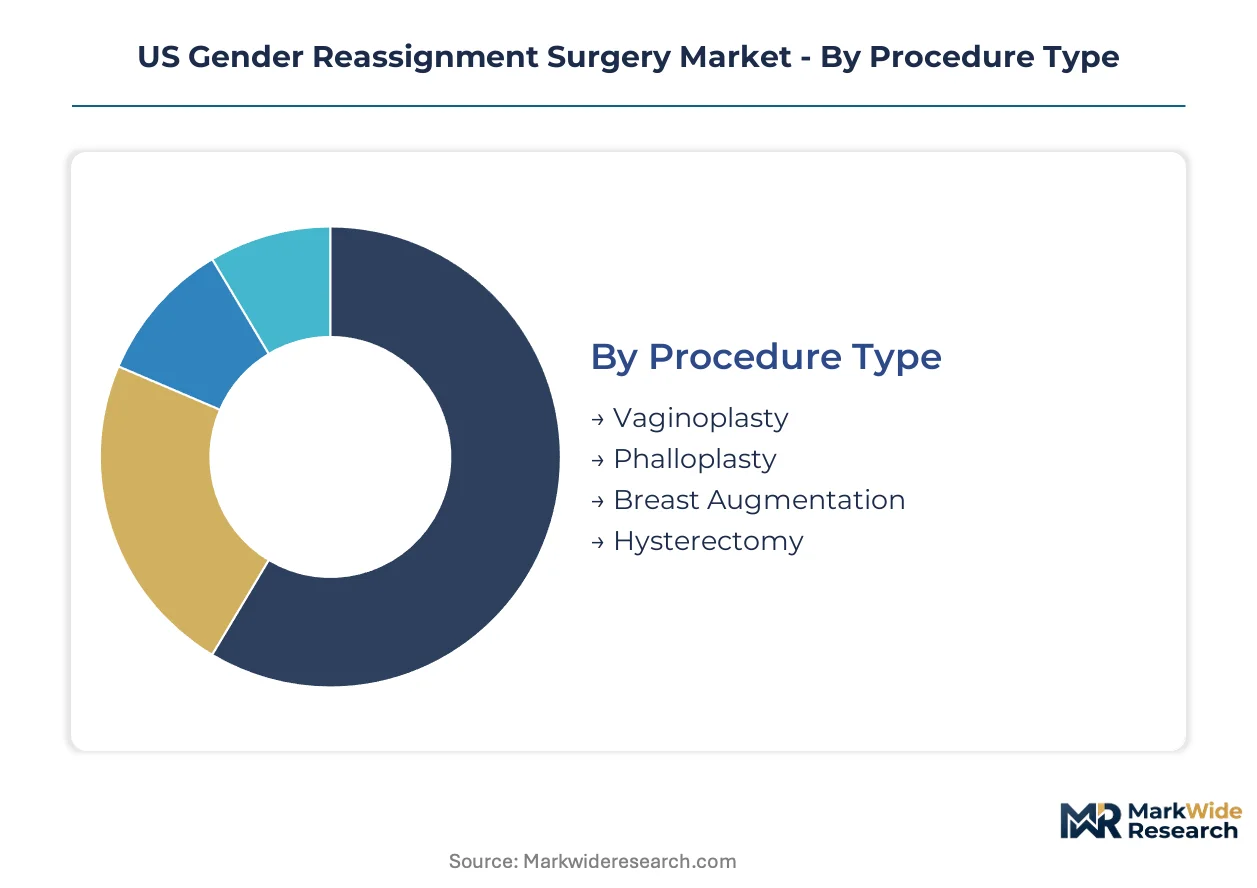
Procedure complexity and reimbursement pathways fragment the US gender reassignment surgery market into distinct operational segments. Each dimension shapes capital allocation, staffing models, and geographic expansion strategies for surgical providers.
Procedure Type:
Vaginoplasty and phalloplasty command premium resource intensity while breast augmentation and hysterectomy migrate toward high-volume, lower-margin protocols.
- Vaginoplasty:Penile inversion and peritoneal pull-through techniques require specialized pelvic reconstruction expertise. California and New York academic centers concentrate demand due to WPATH-trained surgeon density and Medicaid coverage depth. CMS outpatient eligibility expansion pressures workflow reconfiguration toward 23-hour observation models.
- Phalloplasty:Radial forearm free-flap and anterolateral thigh flap reconstructions demand microsurgical teams with transplant-grade sterile facilities. Fewer than 40 US surgeons possess requisite expertise, creating procedural bottlenecks and extended waitlists at Cleveland Clinic and Mount Sinai.
- Breast Augmentation:Chest masculinization and feminization procedures utilize FDA-regulated silicone implants or tissue expanders, migrating rapidly to ambulatory settings in Texas and Florida.
- Hysterectomy:Robotic-assisted platforms enable same-day discharge protocols, expanding surgical scheduling density at high-volume centers.
Mature deployment sits with breast augmentation. Newer deployment is concentrated in peritoneal flap vaginoplasty techniques decentralizing access to community hospitals.
Patient Demographics:
Adult transgender women drive current surgical volume while adolescent pathways and non-binary demand reshape eligibility protocols and informed consent frameworks.
- Adults:Patients aged 18-64 constitute the primary surgical cohort with established hormonal priming histories and mental health clearance documentation. California Medi-Cal expansion has unlocked pent-up demand among previously capped populations.
- Adolescents:Patients under 18 access chest reconstruction and hormone suppression under evolving endocrinologic protocols, with genital surgery restricted to exceptional cases pending skeletal maturity.
- Non-Binary Individuals:Customized surgical plans combining selective masculinization or feminization procedures challenge standardized reimbursement coding and prior authorization pathways.
- Transgender Women:Feminizing procedure demand concentrates vaginoplasty and facial feminization volume at coastal specialized centers.
Volume concentration rests with adult transgender women. Steepest expansion trajectory appears in non-binary customized surgical planning requiring payer negotiation innovation.
Healthcare Setting:
Academic medical centers anchor complex reconstruction while ambulatory surgical centers capture maturing procedure categories through cost-efficient protocols.
- Hospitals:Inpatient facilities with transplant-grade sterile environments dominate phalloplasty and complex vaginoplasty due to microsurgical backup and multi-day admission requirements. Mayo Clinic leverages geographic reach across multiple states.
- Specialty Clinics:Standalone gender centers in Oregon and Washington adopt peritoneal flap techniques faster than academic centers, maintaining volume without full hospital infrastructure.
- Ambulatory Surgical Centers:Outpatient facilities in Texas and Florida capture breast augmentation and orchiectomy volume through streamlined same-day protocols.
- Private Practices:Boutique cosmetic practices compete on digital transparency and social media-informed provider selection among younger cohorts in Massachusetts and Illinois.
Complex reconstruction remains hospital-anchored. Fastest share gain belongs to ambulatory surgical centers as hysterectomy and breast procedures migrate from inpatient settings.
Insurance Coverage:
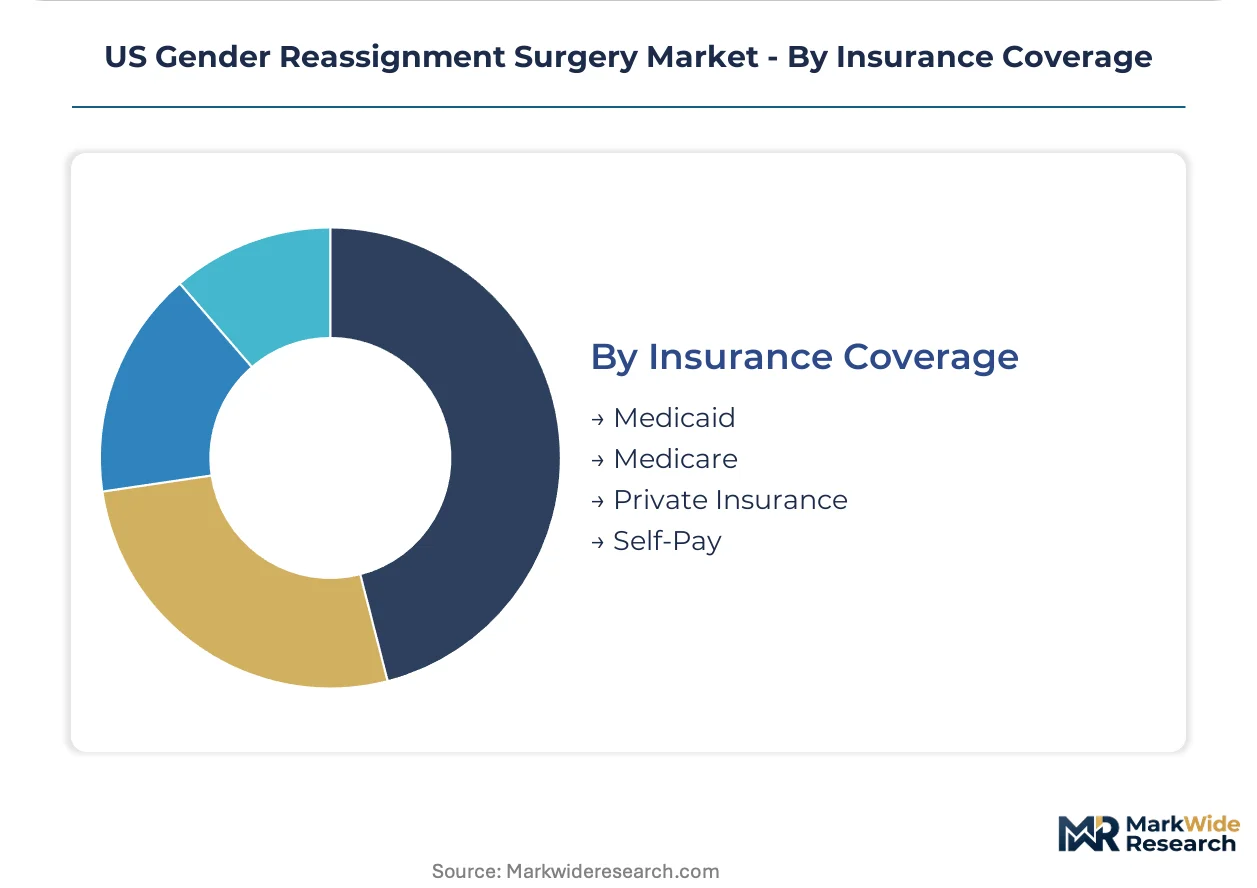
State Medicaid policy divergence creates coverage patchworks that directly alter addressable patient populations and hospital investment decisions.
- Medicaid:State-level coverage expansions in California and New York contrast with exclusions in Tennessee and Alabama, redrawing patient access boundaries faster than surgical capacity scaling.
- Medicare:Federal coverage applies to patients over 65 and disabled populations, with reimbursement schedules shaping hospital investment in inpatient infrastructure.
- Private Insurance:Employer-sponsored plans vary by state mandate requirements, with prior authorization complexity creating 90-180 day administrative delays for phalloplasty.
- Self-Pay:Out-of-pocket financing concentrates at boutique practices with transparent pricing models, particularly for facial feminization and revision procedures.
Established volume flows through private insurance. Coverage expansion is concentrated in Medicaid program redesigns across progressive state jurisdictions.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Manhattan anchors the highest surgical volume concentration, with Mount Sinai Centre for Transgender Medicine and Surgery operating integrated psychiatric, endocrine, and surgical services that sustain patient throughput across full transition pathways.
California
Los Angeles and San Francisco Bay Area academic medical centers drive vaginoplasty and phalloplasty demand following Medi-Cal's removal of lifetime surgery caps. FDA oversight of breast implant devices shapes silicone sourcing for Cedars-Sinai's chest reconstruction programs. Cedars-Sinai anchors West Coast capacity expansion through fellowship-trained reconstructive teams.
Massachusetts
Boston Medical Center concentrates New England surgical volume with systematic outcomes tracking that supports prior authorization navigation. State Medicaid coverage depth exceeds neighboring jurisdictions, drawing cross-border patient flows from Vermont and New Hampshire. The Longwood Medical Area cluster maintains WPATH-trained surgeon density above national averages.
Ohio
Cleveland Clinic anchors Midwest complex reconstruction through microsurgical flap expertise concentrated in fewer than 40 US surgeons. Ohio's Medicaid coverage stability contrasts with exclusion jurisdictions, extending addressable populations across Great Lakes states. The Cleveland facility operates transplant-grade sterile environments that support multi-day phalloplasty admissions.
Minnesota
Mayo Clinic leverages geographic reach across multiple states with established referral networks compensating for lower regional population density. Minnesota's progressive Medicaid policies sustain surgical calendar utilization despite distance from coastal demand centers. Rochester's sterile facilities capture Mountain West and Great Plains patients through telehealth pre-operative pathways.
Texas
The International Center for Transgender Care and standalone Dallas-Fort Worth gender clinics capture ambulatory migration of breast augmentation and orchiectomy from inpatient settings. Texas Medicaid exclusion policies compress addressable populations, forcing centers toward self-pay and private insurance models. Houston and Austin specialty clinics adopt peritoneal flap vaginoplasty faster than academic centers to maintain volume without full hospital infrastructure.
US Gender Reassignment Surgery Market Competitive Landscape
Premium-margin players sit above commodity-margin players across procedure complexity and insurance contracting depth. Academic medical centers with multidisciplinary teams command higher reimbursement rates for phalloplasty and complex vaginoplasty, while ambulatory surgery centers compete on throughput for maturing hysterectomy and breast augmentation categories. Three strategic archetypes dominate: integrated academic systems with fellowship pipelines, standalone specialty clinics with technique specialization, and boutique cosmetic practices with digital transparency investments. Competitive moves concentrate on insurance network expansion and robotic platform acquisition to compress operative timelines.
Among academic medical center systems, Mount Sinai Centre for Transgender Medicine and Surgery, Cleveland Clinic, and Mayo Clinic exemplify the integrated-care archetype through consolidated psychiatric, endocrine, and surgical service lines. These institutions occupy positions where WPATH-trained surgeon density and transplant-grade facility infrastructure create procedural bottlenecks that limit competitor entry. Cedars-Sinai and Boston Medical Center represent West Coast and New England regional anchors respectively, each sitting within markets where state Medicaid policy divergence directly alters addressable patient populations faster than surgical capacity scaling.
| Leading Market Players |
|---|
| Rumer Cosmetic Surgery |
| Mount Sinai Centre for Transgender Medicine and Surgery |
| Cedars-Sinai |
| Boston Medical Center |
| The International Center for Transgender Care |
| Cleveland Clinic |
| Transgender Surgery Institute |
| The Johns Hopkins University |
| Mayo Clinic |
| Others |
Pricing and Supply Chain Analysis
Microsurgical flap expertise concentration in fewer than 40 US surgeons creates extreme labor-cost differentials between phalloplasty centers and ambulatory breast augmentation providers, driving pricing-tier spreads that separate transplant-grade academic hospitals from high-volume outpatient surgery centers.
Pricing Analysis
Outcome-based pricing anchors phalloplasty reimbursement to surgical success metrics and complication rates rather than procedural codes alone. Three-tier pricing structure across premium academic centers, standard regional hospitals, and economy-focused ambulatory facilities reflects WPATH certification depth and microsurgical team availability. Cost compression in breast augmentation and hysterectomy tiers is intensifying because robotic platforms enable same-day discharge protocols that expand scheduling density. Self-pay patients seeking facial feminization and revision procedures exhibit highest price sensitivity, while Medicaid-covered vaginoplasty patients demonstrate lowest sensitivity due to state-mandated coverage floors.
Supply Chain Analysis
Domestic-content mandates in FDA-regulated medical device sourcing reshape procurement patterns for silicone implants and tissue expanders used in chest reconstruction. Manufacturing concentrates in the United States, Germany, and Switzerland for implant-grade silicone, while surgical instrumentation draws from Pakistan and China for cost-sensitive disposable lines. Supply chain risk centers on single-source vulnerability for microsurgical sutures and specialized laparoscopic staplers. Distribution runs through GPO contracts at academic medical centers and direct manufacturer agreements at standalone gender clinics.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
This market operates as a cost-of-compliance story where WPATH Standards of Care Version 8 protocols create barrier-to-entry moats that protect fellowship-trained surgical programs from unqualified competitors.
For Market Incumbents: Lock in microsurgical team retention through equity participation and dedicated research time, while securing exclusive GPO contracts that block ambulatory surgery center encroachment on hysterectomy volume. Prior authorization complexity for phalloplasty represents the primary margin threat, requiring investment in dedicated reimbursement navigation staff. For New Entrants and Emerging Players: Non-binary individuals seeking customized surgical combinations present the most penetrable patient archetype, as standardized reimbursement coding gaps force incumbent hospitals toward lengthy payer negotiations. Peritoneal flap vaginoplasty technique specialization offers entry into community hospital settings without transplant-grade infrastructure requirements. For Investors and Strategic Acquirers: Re-rating potential sits with ambulatory surgery center platforms given CMS outpatient eligibility expansion for vaginoplasty procedures. Long-term viability hinges on state Medicaid coverage trajectory rather than procedural demand fundamentals. Monitor state legislative session calendars as the critical inflection signal for addressable population expansion or contraction.| Strategic Initiative | Industry Significance |
|---|---|
| Fellowship Pipeline Expansion | ACGME-approved program growth alleviates microsurgical flap scarcity bottlenecks at Cleveland Clinic and Mount Sinai. |
| Telehealth Pre-Operative Platform | Virtual mental health clearance extends geographic reach into Mountain West states lacking specialized centers. |
| Robotic Platform Acquisition | Da Vinci system deployment compresses hysterectomy operative timelines toward same-day discharge protocols. |
| Medicaid Contracting Depth | California Medi-Cal network participation unlocks pent-up demand from previously lifetime-capped populations. |
| Peritoneal Flap Technique Adoption | Laparoscopic vaginoplasty methods enable community hospital entry without microsurgical backup requirements. |
Research Methodology
Trade association data, regulatory filings, and customs records anchored secondary inputs, supplemented by structured interviews with gender-affirming surgeons, hospital procurement managers, GPO contracts specialists, and state Medicaid policy officers. Primary fieldwork combined with CMS reimbursement schedule analysis, FDA device registration databases, and WPATH protocol documentation. Bottom-up procedure volume estimates triangulated against top-down hospital capacity assessments.
Data-stream reconciliation across surgical scheduling density, payer mix distributions, and geographic referral patterns shaped the analytical framework. Segmentation dimensions modeled include procedure complexity tier, healthcare setting type, insurance coverage category, and patient demographic cohort. CAGRs derived from capacity-constrained demand projections and policy-driven eligibility expansion scenarios. Forecast inputs incorporated fellowship graduation rates and state legislative tracking.
Revisions become necessary when state Medicaid coverage exclusions expand, microsurgical fellowship programs accelerate output, or robotic platform adoption curves steepen beyond modeled assumptions. Forecasts reflect documented eligibility criteria, reimbursement schedule stability, and surgical workforce pipeline constraints. Within these boundaries, the analytical envelope holds.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Cosmetic Surgery
Saudi Arabia Cosmetic Surgery Market
Cosmetic Surgery
Cosmetic Surgery Market
Cosmetic Surgery
Liposuction Market
Cosmetic Surgery
India Cosmetic Surgery Market
Cosmetic Surgery
Spain Cosmetic Surgery Market
Cosmetic Surgery
Reconstructive Surgery Market
Cosmetic Surgery
UK Cosmetic Surgery Market
Cosmetic Surgery
China Cosmetic Surgery Market
Cosmetic Surgery
Cosmetic Surgery Products Market
Cosmetic Surgery
Brachioplasty Market
Cosmetic Surgery
Gynecomastia Procedures Market
Cosmetic Surgery
Minimally Invasive Cosmetic Procedures Market
Cosmetic Surgery
Germany Cosmetic Surgery Market
Cosmetic Surgery
Global Plastic Surgery and Integumentary System Procedures Market
Cosmetic Surgery
Breast Reconstruction Surgery and Treatment Market
Cosmetic Surgery
Global Mastopexy Market