
 US Gastroenterology Ambulatory Surgery Center Market | 2026-2036
US Gastroenterology Ambulatory Surgery Center Market Size, Share, and Industry Trends Forecast 2026-2036
US Gastroenterology Ambulatory Surgery Center Market Intelligence
The US gastroenterology ASC landscape is decoupling into two distinct operational tiers. High-throughput networks with captive anesthesia and pathology capabilities capture premium case mixes, while smaller independent centers compete on convenience and lower fixed costs. HCA Healthcare anchors this bifurcation through scale-driven supply chain leverage across dozens of facilities. AMSURG differentiates via joint-venture partnerships with physician groups that retain clinical autonomy. United Digestive specializes in multi-specialty integration, extending service depth beyond pure GI procedures.
A gastroenterology ambulatory surgery center delivers same-day procedural care for digestive tract examination and intervention, typically employing endoscopic platforms with high-definition imaging, carbon dioxide insufflation systems, and electrosurgical compatibility to enable polypectomy, tissue biopsy, and bleeding control without hospital admission. Colonoscopy volumes dominate procedure type revenue due to screening adherence campaigns and commercial payer mandates, though polypectomy yields higher per-case margins when pathology conversion occurs. Diagnostic service offerings mature fastest as commoditization pressures intensify, while therapeutic segments retain pricing power through sedation complexity and device intensity. Medicare and Medicaid payment models increasingly determine site selection, with Medicare fee schedule differentials between ASC and hospital outpatient department rates steering case migration toward freestanding settings.
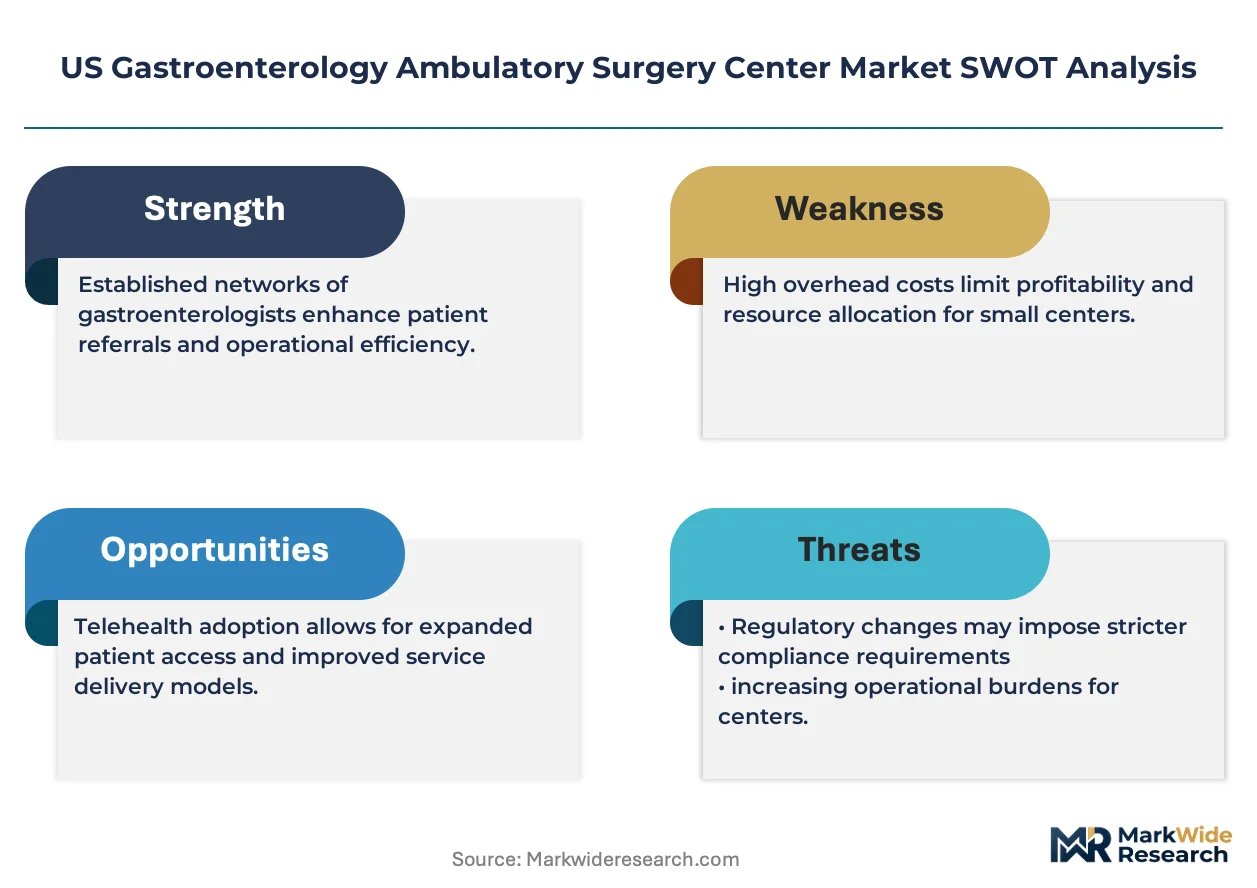
FDA device clearance pathways for endoscopic innovations and CMS conditions for coverage shape capital deployment timelines and technology adoption thresholds. State-level certificate-of-need regulations, particularly in remaining restricted jurisdictions, govern competitive entry and expansion permissions. OSHA bloodborne pathogen standards and HIPAA privacy requirements impose operational compliance costs that scale disproportionately for smaller operators. Stakeholders must monitor Medicare Advantage carve-out negotiations and state Medicaid managed care ASC carve-in decisions that will determine reimbursement trajectory and facility investment viability.
Market Dynamics
CMS site-of-service payment differentials between ASC and hospital outpatient settings are accelerating patient volume migration toward freestanding facilities, compressing traditional hospital-based endoscopy service lines.
Growth Catalysts
- Certificate-of-need reform:Florida and Texas eliminated CON restrictions for ambulatory surgery centers, enabling physician groups to develop greenfield facilities without state approval delays.
- Medicare Advantage expansion:Commercial payers now mandate colonoscopy site flexibility, steering commercially insured patients toward lower-cost ASC settings.
- Carbon dioxide insufflation:Next-generation endoscopic platforms reduce procedure recovery times and post-procedure discomfort, expanding same-day discharge eligibility.
Market Restraints
- Anesthesiologist supply concentration:Rural and secondary metro markets face CRNA staffing shortages that limit procedural throughput expansion.
- Pathology lab dependency:Independent ASCs without captive histology partnerships face margin erosion on polypectomy cases requiring external biopsy processing.
- OSHA bloodborne pathogen compliance:Smaller operators absorb disproportionate per-procedure costs for staff training, equipment sterilization, and documentation systems.
Strategic Opportunities
- Medicaid managed care carve-in:State-level ASC inclusion in Medicaid managed care networks opens access to previously excluded patient populations in Texas and Florida expansion counties.
- Multi-specialty integration:GI-focused centers can extend service depth into pain management and ophthalmology, improving fixed cost absorption.
- AI-assisted polyp detection:Computer-aided diagnosis integration with high-definition endoscopes enhances adenoma detection rates and supports value-based quality bonuses.
Industry Challenges
- Gastroenterologist succession planning:Aging physician-owner demographics create ownership transition complexity for independent joint-venture structures.
- EMR interoperability:ASC-specific documentation systems require costly integration with hospital-based referral networks for seamless care coordination.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | US Gastroenterology Ambulatory Surgery Center Market |
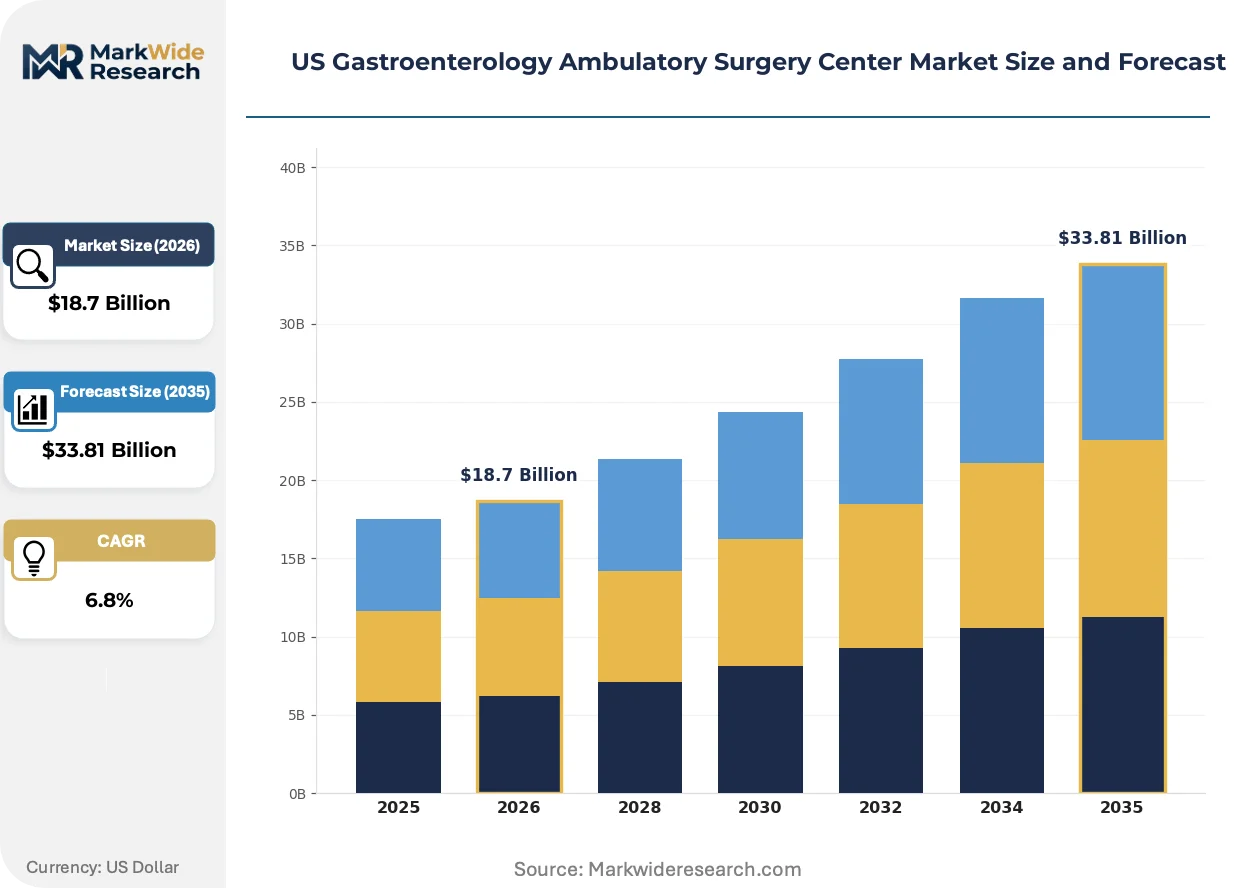
| Market Size in 2026 | $18.7 Billion |
| Market Size in 2035 | $33.81 Billion |
| CAGR (2026 – 2036) | 6.8% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Procedure Type: Colonoscopy, Endoscopy, Gastroscopy, Polypectomy Patient Demographics: Adults, Pediatric, Elderly, Middle-aged Service Offering: Diagnostic, Surgical, Therapeutic, Preventive Payment Model: Out-of-pocket, Insurance, Medicare, Medicaid |
| Companies Covered | Virtua Health, HCA Healthcare, AMSURG, Baptist Health, BayCare, Borland Groover, HonorHealth, Manatee Surgical Center, United Digestive, Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
US Gastroenterology Ambulatory Surgery Center Market Strategic Shifts & Innovations
Endoscopic technology convergence with artificial intelligence and value-based payment mechanics are compressing the traditional diagnostic-therapeutic care pathway into consolidated same-day episodes.
High-definition imaging platforms with integrated narrow-band imaging and autofluorescence capabilities are unifying diagnostic and therapeutic functions into single-procedure workflows. Large physician-owned networks deploy these systems to capture pathology conversion revenue without patient transfer. The technology is unifying previously separate diagnostic and interventional service lines into consolidated ASC encounters.
FDA breakthrough device designation pathways for AI-assisted endoscopic tools accelerate clearance timelines for computer-aided detection systems. This regulatory mechanism compresses the gap between clinical validation and commercial deployment for polyp detection algorithms. GI-focused ASC networks in Florida and Texas are prioritizing these cleared devices to qualify for Medicare quality reporting bonuses.
Commercial payer pre-authorization automation is displacing manual case-by-case approval processes for routine screening colonoscopy. Large employer-sponsored plans now mandate automated eligibility verification through real-time EDI transactions. This behavioral shift concentrates volume toward ASC networks with integrated revenue cycle technology stacks.
US Gastroenterology Ambulatory Surgery Center Market Segmentation
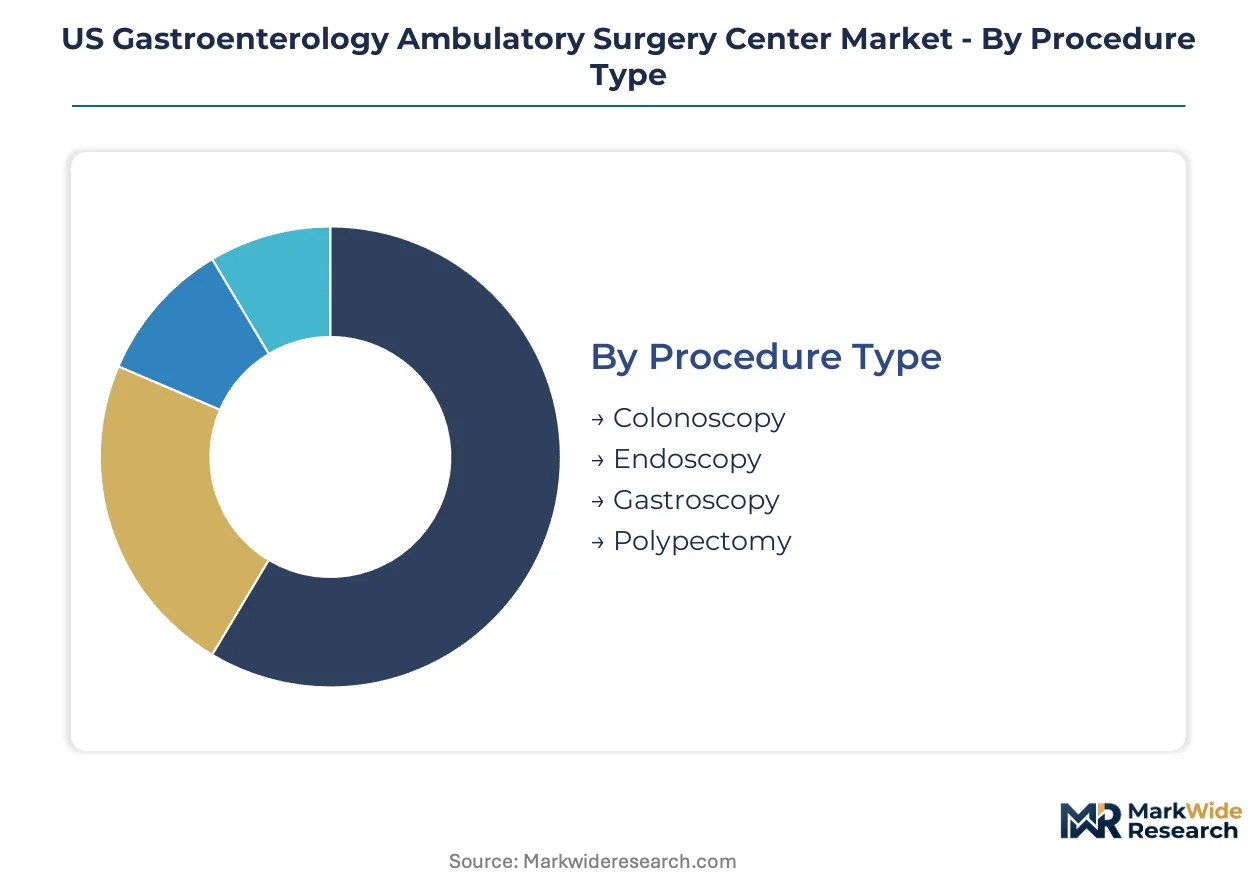
Procedure mix and payment model configuration determine capital allocation and staffing ratios across US gastroenterology ASCs. Demographic targeting and service breadth positioning separate high-throughput networks from convenience-focused independents. Each segmentation dimension carries distinct margin implications and regulatory exposure.
Procedure Type:
Supply concentration in polypectomy and colonoscopy volumes shapes equipment procurement and anesthesia staffing models across freestanding facilities.
- Colonoscopy:Screening and diagnostic lower gastrointestinal examination using flexible sigmoidoscopes with high-definition white-light and narrow-band imaging. Demand clusters in Florida and Texas expansion counties where certificate-of-need elimination permits greenfield development and commercial payer steerage accelerates site migration.
- Polypectomy:Therapeutic tissue resection during index procedures employing snare electrocautery, cold forceps, or endoscopic mucosal resection techniques. Captive pathology integration determines margin capture in Texas markets where independent labs face reimbursement compression.
- Endoscopy:Upper and lower tract examination procedures spanning esophagogastroduodenoscopy and flexible sigmoidoscopy.
- Gastroscopy:Upper gastrointestinal diagnostic and interventional procedures requiring specialized sedation protocols.
Today's leader: Colonoscopy. Tomorrow's challenger: Polypectomy.
Patient Demographics:
Cost tier stratification across age bands dictates scheduling density, preoperative screening intensity, and recovery monitoring protocols.
- Elderly:Patients aged 65 and above requiring enhanced cardiovascular monitoring and extended post-anesthesia observation. Medicare Advantage penetration in Florida concentrates commercially insured volume toward ASC settings with anesthesia depth monitoring capabilities.
- Middle-aged:Adults aged 45-64 representing peak screening colonoscopy eligibility under commercial payer prevention mandates. Texas employer-sponsored plans mandate automated pre-authorization for this cohort, favoring networks with integrated revenue cycle systems.
- Adults:General adult population under 45 presenting symptomatic indications.
- Pediatric:Pediatric gastroenterology cases requiring specialized anesthesia and facility accreditation.
Current volume anchor: Middle-aged. Fastest-expanding cohort: Elderly.
Service Offering:
Application breadth determines fixed cost absorption and physician recruitment scope across single-specialty and multi-specialty configurations.
- Diagnostic:Screening and surveillance procedures with standardized protocols and commoditized reimbursement profiles. AI-assisted polyp detection platforms in Florida ASCs qualify for Medicare quality reporting bonuses, differentiating high-technology networks.
- Therapeutic:Interventional procedures including polypectomy, hemostasis, and stricture dilation with device-intensive supply chains. Medicaid managed care carve-in decisions in Texas expansion counties open access to previously excluded patient populations for therapeutic service lines.
- Surgical:Advanced interventional procedures requiring specialized equipment and extended recovery protocols.
- Preventive:Population health screening programs and surveillance protocols for high-risk cohorts.
Revenue concentration: Diagnostic. Margin expansion: Therapeutic.
Payment Model:
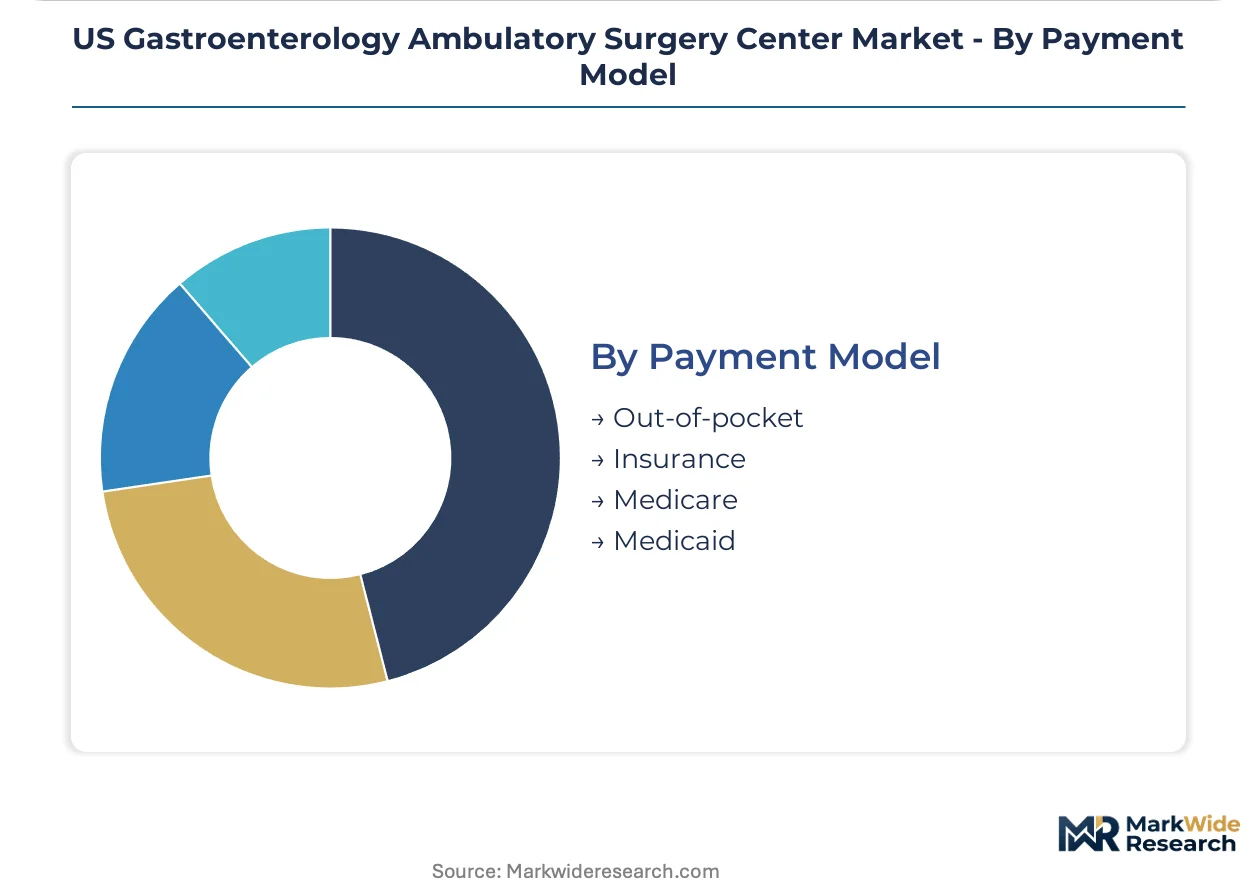
Customer type segmentation governs prior authorization burden, collection risk, and site-of-service flexibility negotiations.
- Insurance:Commercial payer coverage with automated eligibility verification and pre-authorization requirements. Large employer plans in Texas mandate real-time EDI transactions, concentrating volume toward ASC networks with integrated technology stacks.
- Medicare:Federal fee-for-service and Medicare Advantage reimbursement with site-of-service differentials steering case migration. CMS conditions for coverage and quality reporting programs determine technology adoption thresholds in Florida facilities.
- Medicaid:State-administered coverage with managed care carve-in variability across expansion and non-expansion states.
- Out-of-pocket:Self-pay procedures with transparent pricing and direct consumer contracting.
Present dominance: Insurance. Emerging leverage: Medicare.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Florida and Texas dominate ASC development through certificate-of-need elimination, while California's regulatory complexity constrains greenfield expansion despite larger patient populations.
Florida
Medicare Advantage penetration and aging retiree demographics concentrate demand in Tampa Bay and South Florida corridors. CMS conditions for coverage on quality reporting programs determine technology adoption thresholds for colonoscopy screening networks. Orlando and Miami-Dade clusters attract physician-group joint ventures seeking site-of-service flexibility from commercial payers.
Texas
Employer-sponsored plan mandates for automated pre-authorization steer middle-aged screening volumes toward integrated revenue cycle networks. State Medicaid managed care carve-in decisions in expansion counties open therapeutic service lines to previously excluded populations. Dallas-Fort Worth and Houston medical centers anchor multi-specialty ASC development with captive anesthesia capabilities.
California
OSHA bloodborne pathogen compliance costs and seismic retrofit requirements disproportionately burden smaller independent operators. HIPAA privacy enforcement and state-level facility licensing create extended approval timelines for greenfield projects. Los Angeles and San Francisco Bay Area markets concentrate volume within hospital-affiliated outpatient departments due to site neutrality pressures.
Arizona
Snowbird seasonal migration patterns create demand volatility requiring flexible staffing models across Phoenix and Tucson metro areas. Medicare fee schedule differentials between ASC and hospital outpatient settings accelerate case migration toward freestanding facilities. Scottsdale and Mesa clusters specialize in cash-pay preventive screening programs for out-of-state retirees.
Georgia
Remaining certificate-of-need restrictions in Atlanta constrain competitive entry while permitting expansion in secondary markets. Commercial payer steerage campaigns concentrate commercially insured colonoscopy volumes within network-affiliated ASCs. Augusta and Savannah corridors attract regional physician partnerships seeking joint-venture structures with retained clinical autonomy.
US Gastroenterology Ambulatory Surgery Center Market Key Industry Players
Top-tier vendors anchor scale-driven supply chain leverage, while mid-tier physician partnerships compete on clinical autonomy and convenience positioning. The market bifurcates between high-throughput networks with captive pathology and anesthesia capabilities versus independent centers with lower fixed cost structures. Strategic archetypes include hospital-affiliated consolidators, physician-owned joint ventures, and multi-specialty integrators. Dominant competitive moves encompass state-level certificate-of-need exploitation and Medicare Advantage network contracting.
Within the hospital-affiliated consolidator tier, HCA Healthcare exemplifies scale-driven procurement leverage across dozens of facilities, while AMSURG occupies a position representing joint-venture partnerships that retain physician clinical autonomy. United Digestive anchors the multi-specialty integration archetype, extending service depth beyond pure GI procedures into complementary ambulatory service lines.
| Leading Market Players |
|---|
| Virtua Health |
| HCA Healthcare |
| AMSURG |
| Baptist Health |
| BayCare |
| Borland Groover |
| HonorHealth |
| Manatee Surgical Center |
| United Digestive |
| Others |
Cost & Logistics Intelligence
Carbon dioxide insufflation system pricing benchmarks cascade through ASC equipment procurement tiers, compressing capital deployment schedules for high-definition endoscopic platforms while elevating per-procedure cost structures for independent operators lacking group purchasing leverage.
Pricing Analysis
Capacity additions in Florida and Texas are reshaping price floors for colonoscopy screening services as certificate-of-need elimination permits greenfield facility development without state approval delays. Pricing stratifies across premium, standard, and economy tiers based on anesthesia depth monitoring capabilities and pathology integration depth. Cost compression in the standard tier intensifies because commercial payer pre-authorization automation concentrates volume toward networks with integrated revenue cycle technology stacks. Employer-sponsored plans in Texas exhibit highest price sensitivity, while Medicare Advantage beneficiaries in Florida demonstrate lowest sensitivity due to site-of-service flexibility mandates.
Supply Chain Analysis
Endoscope refurbishment and remanufacturing flows create secondary supply channels that extend equipment lifecycle value for independent ASCs facing capital constraints. Manufacturing concentrates in Japan, Germany, and the United States for high-definition imaging platforms and electrosurgical accessories. Supply chains draw from specialized optical sensor arrays, carbon dioxide insufflation canisters, and single-use polypectomy snares. Single-source vulnerability persists for narrow-band imaging modules produced by limited qualified suppliers. Distribution runs through manufacturer-direct sales forces and regional medical equipment distributors serving hospital-affiliated and independent ASC networks.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
This market functions as a stable compounder, with Medicare fee schedule differentials between ASC and hospital outpatient settings providing durable volume migration tailwinds across the analysis window.
For Market Incumbents: Lock in anesthesia and pathology partnerships before CRNA staffing shortages intensify in secondary metro markets. Pursue backward integration into captive histology processing to capture polypectomy margin erosion from external lab dependency. Defend against independent joint-venture structures by accelerating multi-specialty integration into pain management and ophthalmology service lines. For New Entrants and Emerging Players: Begin with Medicaid managed care carve-in opportunities in Texas expansion counties where therapeutic service lines remain underpenetrated. Target physician-group joint ventures in Georgia secondary markets where remaining certificate-of-need restrictions constrain competitive entry. Deploy AI-assisted polyp detection platforms as a go-to-market differentiator for Medicare quality reporting bonus qualification. For Investors and Strategic Acquirers: Consolidation pressure builds where aging physician-owner demographics create ownership transition complexity for independent joint-venture structures. Five-to-ten year viability favors multi-specialty integrators with captive anesthesia capabilities over pure-play GI diagnostics. Target acquisition archetype: physician-owned networks in Florida and Texas with established commercial payer contracts and site-of-service flexibility agreements. Monitor state Medicaid managed care ASC carve-in decisions as the critical inflection signal for therapeutic volume accessibility.| Strategic Initiative | Industry Significance |
|---|---|
| Certificate-of-Need Exploitation | Florida and Texas CON elimination permits rapid greenfield facility deployment without regulatory delays. |
| Medicare Advantage Network Contracting | Commercial payer site flexibility mandates steer commercially insured volume toward lower-cost ASC settings. |
| AI-Assisted Detection Platform Deployment | FDA-cleared computer-aided diagnosis systems qualify facilities for CMS quality reporting bonus programs. |
| Captive Pathology Integration | In-house histology processing captures polypectomy margin erosion from external lab reimbursement compression. |
| Multi-Specialty Service Expansion | Pain management and ophthalmology integration improves fixed cost absorption across underutilized capacity blocks. |
Research Approach
Coverage spans Florida, Texas, California, Arizona, and Georgia, with primary inputs from each state cluster combined with secondary validation across hospital procurement databases, CMS Medicare fee schedule filings, and state certificate-of-need regulatory records. Primary interviews engaged ASC administrators, gastroenterology practice managers, anesthesia group contracting officers, and commercial payer network directors. Secondary sources included GPO contracts, FDA device clearance databases, and state Medicaid managed care plan amendments. Bottom-up facility count modeling triangulated against top-down procedure volume estimates from CMS claims data.
Rate-of-change decomposition separates volume drivers from pricing dynamics across the projection horizon. Segmentation dimensions modeled include procedure type, patient demographics, service offering breadth, and payment model configuration. CAGRs were derived from historical Medicare claims trajectory analysis and commercial payer contract renewal patterns. Industry-specific forecast inputs encompass colonoscopy screening adherence campaign intensity and Medicare Advantage penetration rate assumptions by state market.
Several conditions sit outside the modeled scope, including federal site neutrality policy reversals, state-level Medicaid expansion rollbacks, and disruptive endoscopic technology platforms achieving FDA breakthrough designation outside current clearance pathways. Forecasts reflect documented assumptions regarding CMS reimbursement stability and commercial payer steerage durability. Practitioners should monitor state certificate-of-need reform momentum and Medicare Advantage carve-out negotiation outcomes for early signals of volume trajectory revision.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Gastroenterology
Necrotic Enteritis Treatment Market
Gastroenterology
Gallstone Market
Gastroenterology
Peptic Ulcer Market
Gastroenterology
High Definition Ultrasound Gastroscope Market
Gastroenterology
Hyperemesis Gravidarum Treatment Market
Gastroenterology
Digestive Health Market
Gastroenterology
Malabsorption Syndrome Treatment Market
Gastroenterology
Disposable Intestinal Wash Bags Market
Gastroenterology
Stomach Cancer Market
Gastroenterology
Inflammatory Bowel Disease Treatment Market
Gastroenterology
Gastroesophageal Junction Adenocarcinoma Therapeutics Market
Gastroenterology
Chronic Liver Diseases Therapeutics Market
Gastroenterology
Gastroesophageal Reflux Disease Therapeutics Market
Gastroenterology
Polyps Market
Gastroenterology
Fecal Incontinence Market
Gastroenterology
Gluten Intolerance Treatment Market