
 Medical Professional Liability Insurance Market | 2026-2036
Medical Professional Liability Insurance Market Size, Share, and Industry Trends Forecast 2026-2036
Medical Professional Liability Insurance Market Analysis
Telemedicine integration into clinical workflows is fragmenting traditional risk assessment models that underwriters relied upon for decades. MedPro Group leverages proprietary data pools to price remote consultation exposure. Doctors Company Group sustains dominance in physician-owned captive structures. CNA Insurance Group competes through hospital system master policies that bundle employed and affiliated providers.
Medical professional liability insurance indemnifies healthcare providers against legal claims alleging negligence, breach of duty, or patient harm arising from clinical services, with policies typically specifying per-claim limits, aggregate caps, and consent-to-settle provisions. Its primary commercial purpose is to protect individual practitioners and institutional employers from asset depletion due to litigation defense costs, settlement payments, and jury awards. Claims-made coverage dominates the market as it aligns premium collection with active exposure periods, though occurrence policies retain share among retiring physicians seeking long-term tail protection. Private insurers anchor the provider type landscape, while risk retention groups capture niche segments where commercial markets have retracted.
US state insurance commissioners, the EU's EIOPA framework, and China's NMPA clinical liability guidelines collectively shape capital reserve requirements, policy form standards, and cross-border coverage recognition. State-level tort reform caps in the US directly compress loss ratios in favorable jurisdictions, while EIOPA's Solvency II equivalence assessments constrain European carrier expansion strategies. Stakeholders must monitor how artificial intelligence diagnostic tools reclassify liability between human clinicians and algorithm vendors.
Market Dynamics
Telemedicine integration is fragmenting traditional risk assessment models that underwriters relied upon for decades, forcing carriers to rebuild pricing frameworks around remote consultation exposure and virtual care delivery chains.
Growth Catalysts
- EU Medical Device Regulation:The MDR tightens liability exposure for healthcare providers using connected diagnostic equipment, expanding coverage requirements for device-related patient harm claims.
- Specialty surgical centers:Rising patient acuity at ambulatory facilities drives expanded coverage purchases as these sites assume cases previously reserved for hospitals.
- Artificial intelligence diagnostics:Algorithm-assisted decision tools create new liability layers between clinicians and software vendors, generating demand for cyber-endorsements and technology E&O riders.
Market Restraints
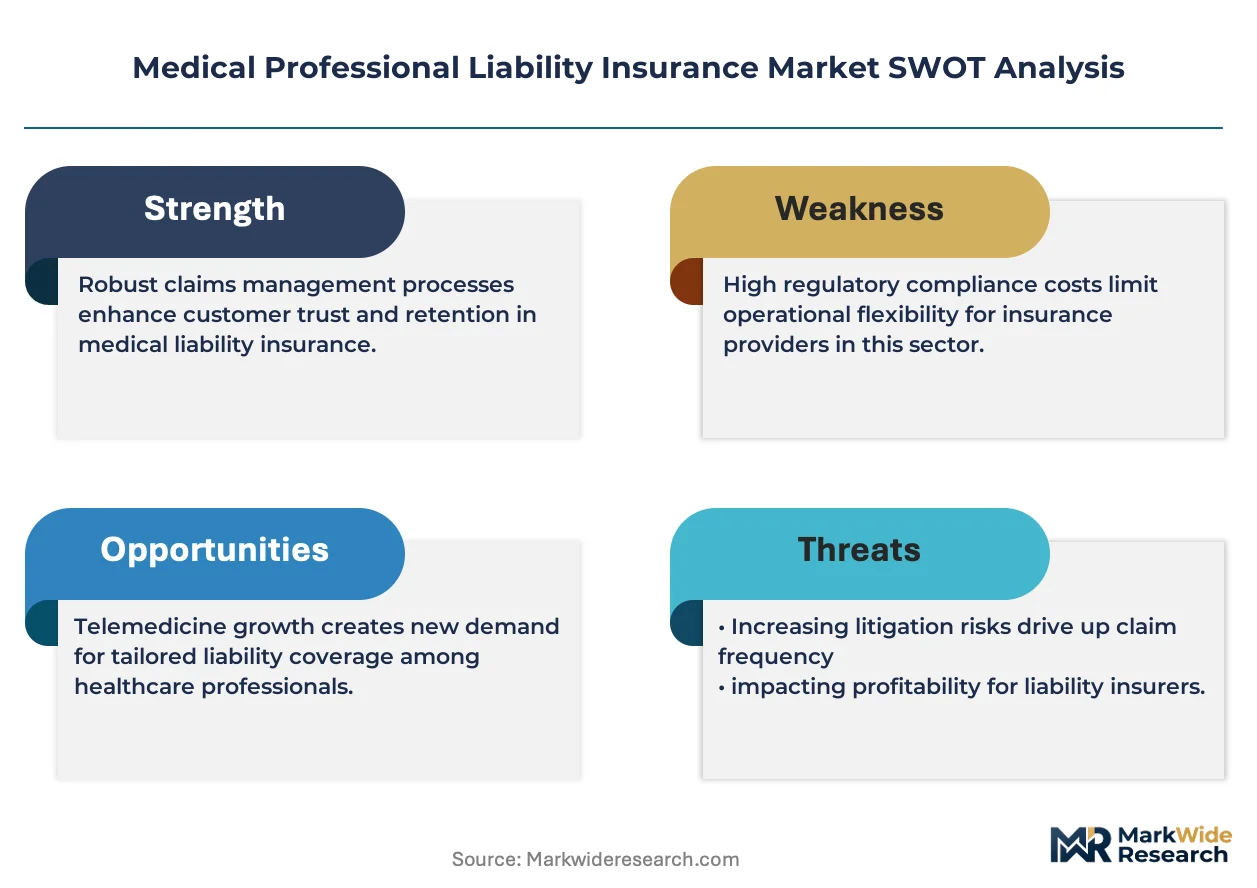
- Litigation cost volatility:Defense expenditure unpredictability in US jurisdictions with uncapped non-economic damages compresses carrier underwriting margins and destabilizes loss ratio projections.
- Reinsurance capacity concentration:Bermuda and London market capacity constraints limit primary carriers' ability to lay off peak severity exposure, forcing retention of larger net lines.
- Long-tail liability duration:Claims-made coverage creates persistent tail obligation uncertainty, particularly for retiring physicians seeking run-off protection in high-frequency litigation states.
Strategic Opportunities
- Captive insurance structures:Physician-owned risk retention groups offer premium stability and dividend participation, attracting specialists in orthopedic surgery and obstetrics facing commercial market withdrawal.
- Parametric trigger products:Index-based coverage tied to peer review outcomes or sentinel event frequencies enables proactive risk financing for health systems with robust quality infrastructure.
- Cross-border telemedicine:Interstate and international virtual care delivery creates demand for multi-jurisdictional coverage forms addressing licensing board complaints across state lines.
Industry Challenges
- Actuarial data scarcity:Limited historical experience with telehealth-specific claims frequency and severity impairs pricing accuracy for remote consultation endorsements.
- Consent-to-settle coordination:Policyholder control over settlement decisions conflicts with carrier loss mitigation objectives, generating friction in claims management workflows and reserving methodologies.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Medical Professional Liability Insurance Market |
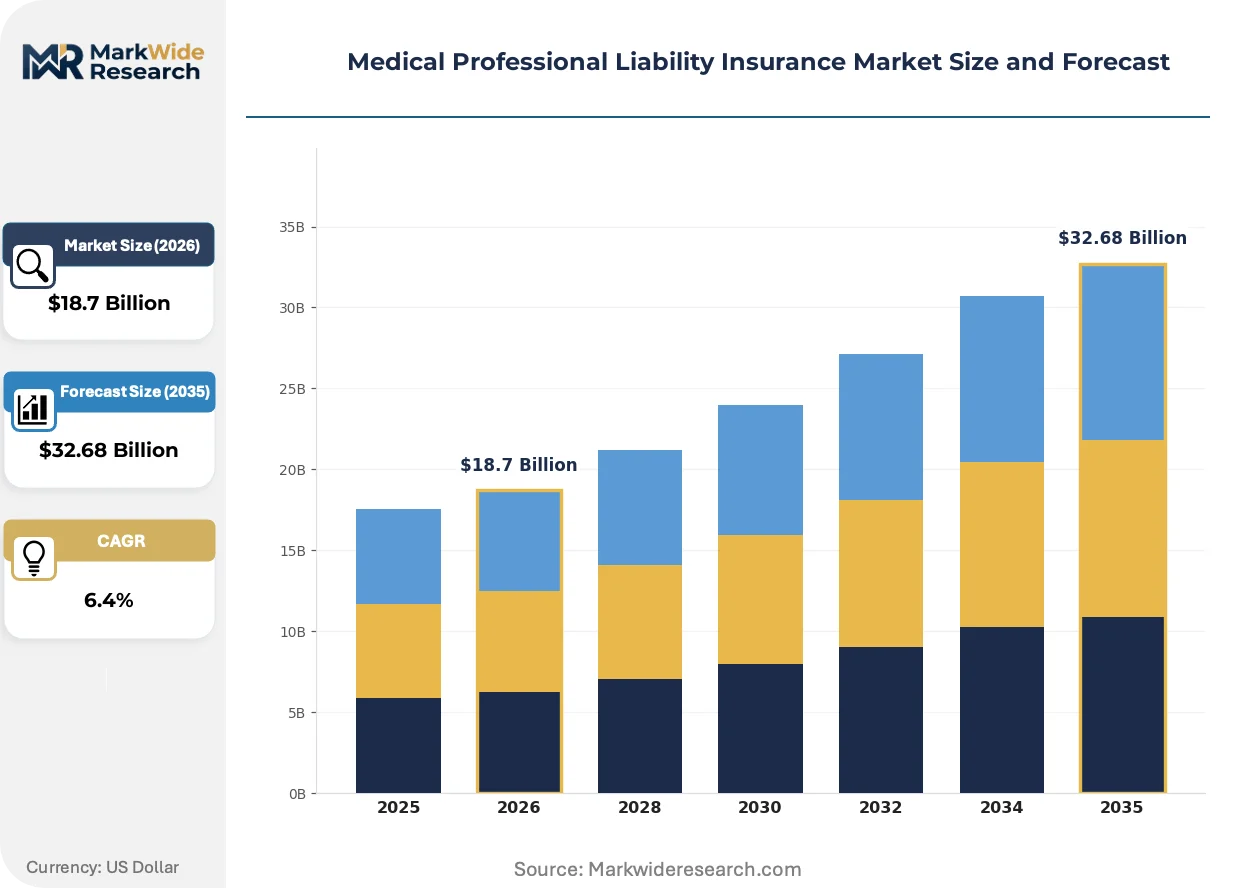
| Market Size in 2026 | $18.7 Billion |
| Market Size in 2035 | $32.68 Billion |
| CAGR (2026 – 2036) | 6.4% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Coverage Type: Claims-Made, Occurrence, Full Retroactive, Tail Coverage Premium Structure: Annual, Monthly, Pay-As-You-Go, Incremental Provider Type: Private Insurers, Public Insurers, Captive Insurance Companies, Risk Retention Groups Claim Type: Negligence, Breach of Duty, Misrepresentation, Others |
| Companies Covered | Berkshire Hathaway Group, Doctors Company Group, CNA Insurance Group, ProAssurance Corp Group, MAG Mutual Insurance Group, Coverys Group, MedPro Group, WR Berkley Corporation, The Hartford, Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Medical Professional Liability Insurance Market Emerging Trajectories
Digital health deployment is collapsing traditional boundaries between medical malpractice and technology liability, requiring carriers to engineer hybrid coverage architectures that address algorithmic decision support, remote monitoring failures, and platform security breaches within unified policy structures.
Machine learning diagnostic algorithms are collapsing the historical separation between clinical judgment errors and software malfunction claims. Hospital systems deploying FDA-cleared AI imaging tools now face overlapping liability exposure to both patient plaintiffs and algorithm vendors. This convergence is forcing MedPro Group and Doctors Company Group to restructure policy exclusions and develop sublimits for algorithm-related cognitive errors.
The EU AI Act establishes risk-tiered liability frameworks for healthcare applications of artificial intelligence, with high-risk systems subject to conformity assessment and post-market surveillance obligations. EIOPA's Solvency II equivalence assessments are constraining European carrier capital treatment of AI-related reserves. German and French health insurers are responding by segregating algorithmic risk into standalone captive structures.
Consolidation among US health systems is compressing procurement cycles for professional liability coverage, with employed physician groups surrendering individual policy control to master hospital contracts. Three-year policy terms are displacing annual renewals as dominant purchasing patterns. This concentration is most pronounced in Texas and Florida, where hospital-employed specialists now represent the majority of new premium volume.
Medical Professional Liability Insurance Market Segmentation
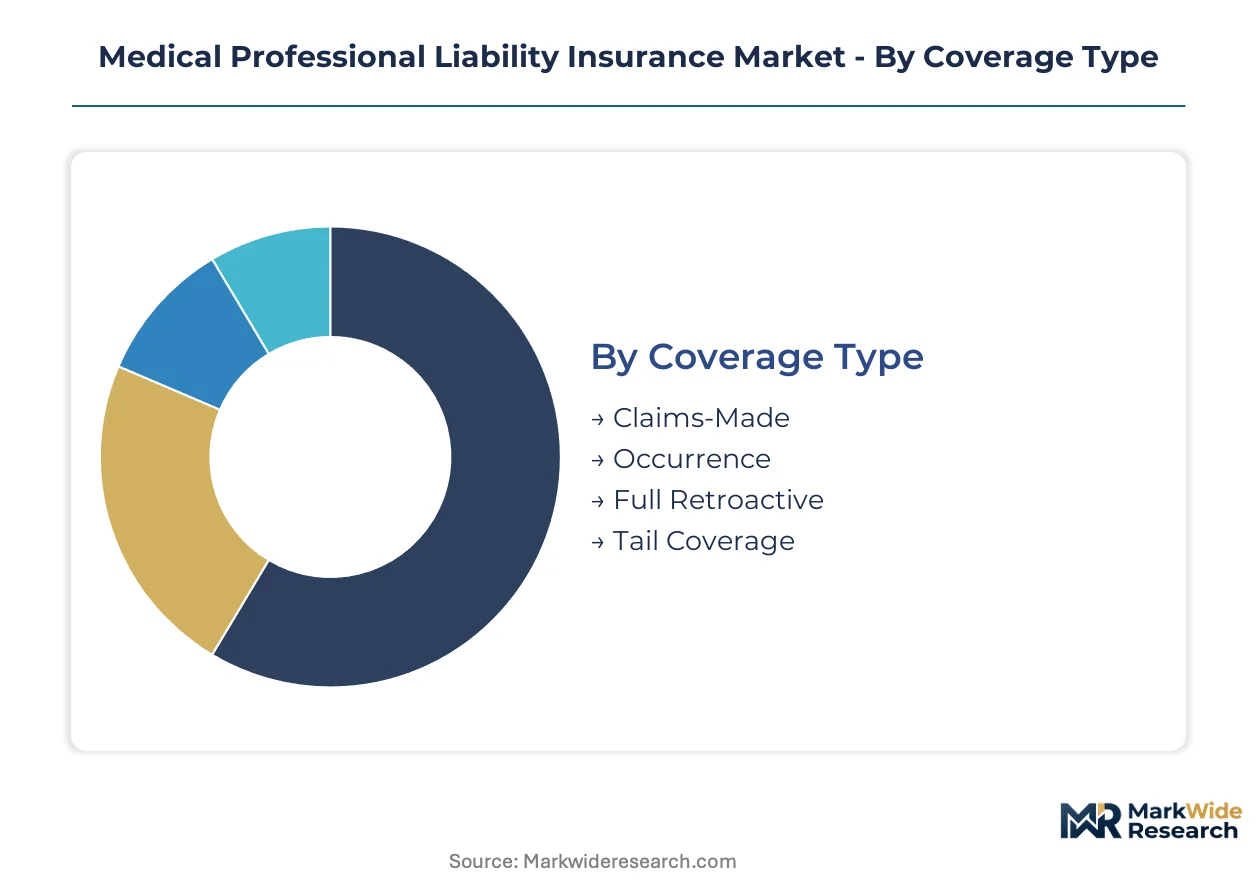
Medical professional liability insurance segments fragment along risk duration, payment timing, and capital structure lines. Each category carries distinct pricing mechanics and regulatory capital requirements that shape carrier underwriting strategies.
Coverage Type:
Claims-made policies turn over fastest with annual premium resets, while occurrence contracts lock pricing for decades and tail coverage extends protection into retirement.
- Claims-Made:Coverage activates when claims are reported during the policy period, regardless of when the incident occurred. Premiums step up over the first five years as exposure matures, then stabilize. Hospital systems in Texas and Florida favor this structure for employed physician groups, aligning cost with active practice periods.
- Occurrence:Policies cover incidents happening during the coverage year irrespective of reporting date. Retiring physicians in high-litigation states purchase these for permanent protection without tail obligations. Premiums run higher upfront but eliminate run-off uncertainty.
- Full Retroactive:Extends coverage backward to a specified prior acts date, enabling physicians switching carriers to maintain continuous protection. Demand concentrates among specialists relocating between states with divergent tort environments.
- Tail Coverage:Standalone policies covering claims reported after claims-made coverage terminates. OB/GYNs and orthopedic surgeons facing market withdrawal pressure rely on tail products from state patient compensation funds.
Claims-made dominates installed base. Tail coverage is where expansion concentrates.
Premium Structure:
Payment frequency correlates with customer liquidity and regulatory reserve timing, with monthly structures appealing to solo practitioners and incremental products matching hospital budget cycles.
- Annual:Lump-sum payment at policy inception, standard for established practices with predictable cash flow. Captive insurance companies and risk retention groups require annual commitments to maintain dividend eligibility.
- Monthly:Spreads premium obligations across twelve installments, attracting new entrants and locum tenens physicians with irregular revenue streams. Administrative fees elevate total cost.
- Pay-As-You-Go:Ties premium to actual patient encounter volume or revenue, common among telemedicine platforms with variable utilization. Requires real-time reporting infrastructure.
- Incremental:Structured increases tied to policy maturation or claims experience adjustments. Step-rated claims-made policies use this mechanism to align early-career premiums with evolving exposure.
Annual payment dominates installed base. Pay-as-you-go is climbing the fastest.
Provider Type:
Capital backing and ownership structure determine pricing stability, with physician-owned vehicles offering dividend participation and commercial carriers providing balance sheet depth.
- Private Insurers:Stock and mutual companies with diversified liability portfolios. MedPro Group and CNA Insurance Group leverage proprietary data pools and hospital system master contracts to capture employed physician volume.
- Public Insurers:State-sponsored patient compensation funds operating as insurers of last resort. Florida's Birth-Related Neurological Injury Compensation Plan and Virginia's Birth Injury Program provide alternative liability channels.
- Captive Insurance Companies:Wholly-owned subsidiaries writing parent organization risk. Large health systems in California and New York deploy captives to retain predictable layers and access reinsurance directly.
- Risk Retention Groups:Member-owned entities authorized under federal Liability Risk Retention Act. Doctors Company Group sustains dominance in physician-owned structures, particularly for obstetrics and orthopedic surgery.
Private insurers dominate installed base. Risk retention groups are gaining share fastest.
Claim Type:
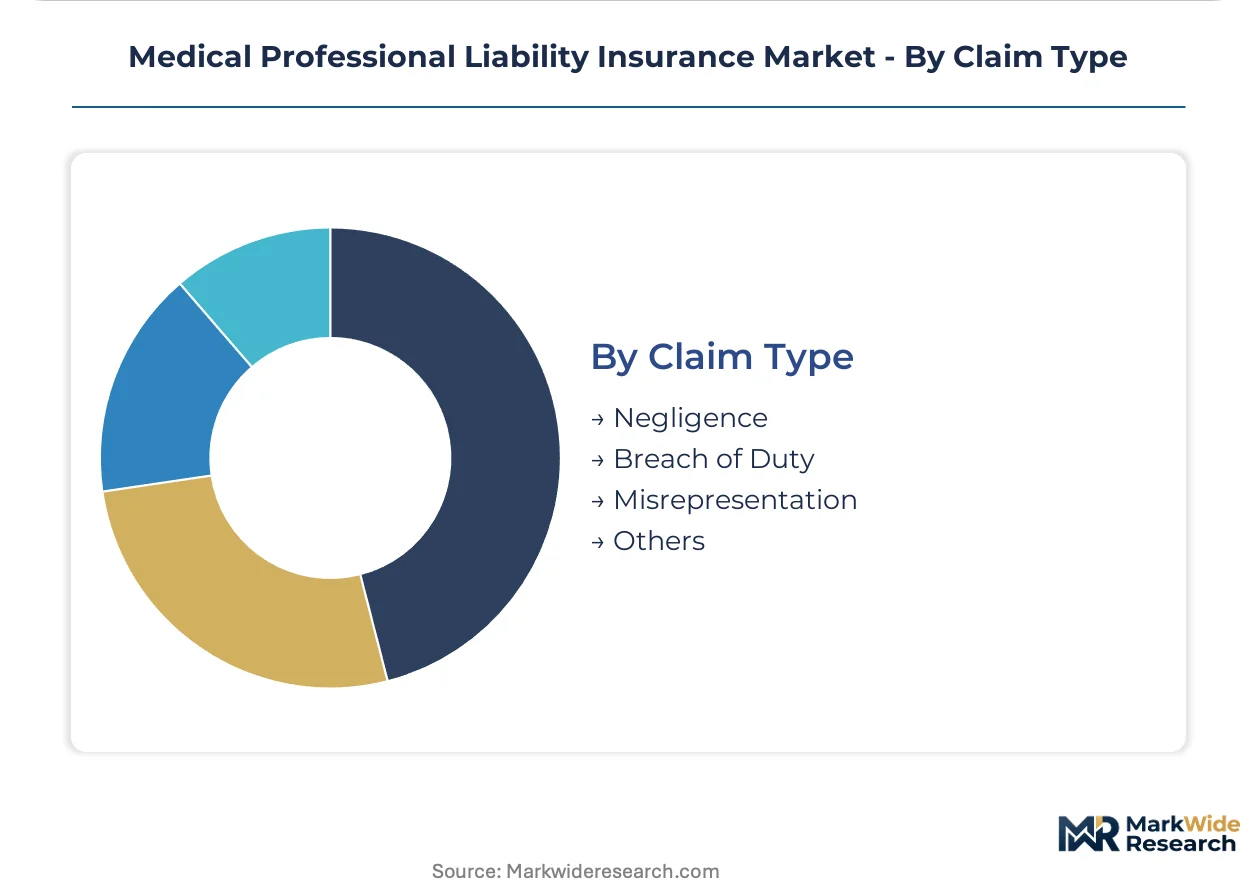
Allegation severity and defense cost profiles vary sharply across claim categories, with negligence claims driving severity and misrepresentation exposure expanding through informed consent documentation.
- Negligence:Allegations of substandard care causing patient harm. Surgical specialties and emergency medicine generate highest frequency. Defense costs escalate in jurisdictions with uncapped non-economic damages.
- Breach of Duty:Claims asserting violation of fiduciary or contractual obligations to patients. Telemedicine platforms face novel exposure around duty-of-care establishment across state lines.
- Misrepresentation:Informed consent failures and outcome disclosure disputes. Rising patient acuity at ambulatory surgical centers intensifies documentation requirements.
- Others:Battery, defamation, and privacy violations under HIPAA. Cyber liability endorsements increasingly address electronic health record breaches.
Negligence claims dominate installed base. Misrepresentation is where expansion concentrates.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Hospital systems and physician-owned captives concentrate premium volume in jurisdictions with elevated litigation frequency. State-level tort environments and federal telemedicine licensing frameworks determine carrier expansion priorities.
United States
Texas and Florida hospital-employed specialists generate the majority of new premium volume through master policy structures. State insurance commissioners in these jurisdictions enforce capital reserve requirements that favor claims-made coverage for employed physician groups. The Southeast cluster including Georgia and South Carolina sees rising captive formation among orthopedic surgery practices.
Germany
German health insurers segregate algorithmic risk into standalone captive structures following EIOPA's Solvency II equivalence assessments. The EU AI Act's risk-tiered liability frameworks for healthcare applications tighten conformity assessment obligations. The Baden-Württemberg medical technology corridor drives demand for device-related professional liability extensions.
United Kingdom
NHS Resolution's indemnification schemes compete with commercial carriers for physician coverage, compressing private market share in secondary care. The Clinical Negligence Scheme for Trusts shapes pricing benchmarks for independent practitioner policies. London's reinsurance market provides capacity for peak severity exposure layers.
France
French mutual insurers face pressure from ANSM post-market surveillance obligations on connected diagnostic equipment. The EU Medical Device Regulation tightens liability exposure for healthcare providers using high-risk devices. The Paris-Île-de-France hospital network concentrates procurement of master professional liability contracts.
China
NMPA clinical liability guidelines shape coverage recognition standards for domestic and cross-border telemedicine services. Rising patient acuity at tier-one hospital outpatient centers drives expanded coverage purchases. The Yangtze River Delta medical cluster sees accelerated captive formation among private hospital chains.
Medical Professional Liability Insurance Market Vendor Landscape
Channel-controlling players compete with product-specialist players across hospital system master policies and physician-owned captive structures. The market exhibits tiered concentration, with national carriers dominating employed physician volume while risk retention groups capture high-severity specialty niches. Two strategic archetypes prevail: balance-sheet-driven commercial insurers leveraging proprietary data pools, and member-owned vehicles offering dividend participation and premium stability. Competitive moves center on hospital system consolidation into multi-year master contracts and captive formation in obstetrics and orthopedic surgery segments.
Among US-based national carriers, Berkshire Hathaway Group and CNA Insurance Group occupy positions anchored by diversified liability portfolios and hospital system relationships. Doctors Company Group exemplifies the physician-owned archetype, sustaining dominance in risk retention group structures for high-severity specialties. These three entities represent the primary competitive vectors: commercial scale, captive participation, and data-driven pricing infrastructure.
| Leading Market Players |
|---|
| Berkshire Hathaway Group |
| Doctors Company Group |
| CNA Insurance Group |
| ProAssurance Corp Group |
| MAG Mutual Insurance Group |
| Coverys Group |
| MedPro Group |
| WR Berkley Corporation |
| The Hartford |
| Others |
Supply Flow & Price Mechanics
The Lloyd's of London reinsurance corridor channels capital from Bermuda and London into primary carrier balance sheets, with its cost dynamics compressing net retention limits and forcing three-tier pricing differentiation across claims-made, occurrence, and captive-structured policies. Supply concentration among physician-owned risk retention groups in Texas and Florida creates asymmetric pricing power that hospital systems exploit through multi-year master contract procurement.
Pricing Analysis
Cost-plus contract patterns with medical malpractice loss cost indexation dominate hospital system master policies, aligning premium adjustments with jurisdiction-specific severity trends. Three-tier pricing structure across premium, standard, and economy levels separates occurrence policies for retiring physicians from claims-made coverage for employed specialists and tail coverage for market-withdrawn OB/GYNs. Pricing pressure stems from defense cost volatility in uncapped non-economic damage states, compressing underwriting margins. Solo practitioners and locum tenens physicians exhibit highest price sensitivity, while captive-structured orthopedic surgery groups demonstrate lowest sensitivity due to dividend participation.
Supply Chain Analysis
Supplier-financing through extended premium payment terms and state patient compensation fund backstops stabilizes tail coverage availability for retiring physicians in high-frequency litigation jurisdictions. Capital supply concentrates in the United States, Bermuda, and the United Kingdom, with Lloyd's syndicates and Bermuda reinsurers providing peak severity capacity. Raw material dependencies include actuarial data pools, proprietary claims databases, and regulatory capital reserves. Single-source vulnerability to Bermuda market capacity constraints threatens primary carriers' ability to lay off catastrophic layers. Distribution runs through independent agent networks for individual practitioners and direct procurement teams for hospital systems.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
This market sits in early-cycle expansion as telemedicine penetration fragments traditional risk assessment models and creates demand for multi-jurisdictional coverage forms that legacy pricing infrastructure cannot serve.
For Market Incumbents: Build proprietary data moats around telehealth-specific claims frequency and remote consultation exposure pricing. MedPro Group's data pool advantage and CNA Insurance Group's hospital system master contract relationships exemplify defensible positioning. Threats from algorithmic diagnostic tools reclassifying liability between clinicians and software vendors demand cyber-endorsement product development. Channel control through three-year policy terms displacing annual renewals represents the critical lever for employed physician volume retention. For New Entrants and Emerging Players: Cross-border telemedicine platforms serving interstate virtual care delivery represent the most penetrable entry point, with licensing board complaint exposure across state lines creating coverage gaps that incumbent claims-made structures fail to address. Parametric trigger products tied to peer review outcomes or sentinel event frequencies offer white-space positioning for health systems with robust quality infrastructure. Go-to-market execution should target risk retention group formation in obstetrics and orthopedic surgery segments where commercial market withdrawal concentrates specialist demand. For Investors and Strategic Acquirers: Mid-cycle technology positioning favors physician-owned captive structures with dividend participation mechanics and premium stability guarantees. Long-term viability hinges on exposure to telemedicine integration tailwinds rather than traditional hospital system consolidation headwinds. Acquisition targets should display proprietary data infrastructure for remote consultation pricing or established risk retention group platforms in high-severity specialties. The signal to watch is FDA clearance velocity for AI diagnostic tools, which accelerates liability reclassification and hybrid coverage architecture demand.| Strategic Initiative | Industry Significance |
|---|---|
| Cyber Endorsement Development | Addresses algorithmic diagnostic liability gaps between clinicians and FDA-cleared AI vendors. |
| Captive Structure Formation | Physician-owned risk retention groups capture premium stability in orthopedic and obstetric specialties. |
| Multi-Jurisdictional Coverage Launch | Telemedicine platforms require licensing board complaint protection across state lines. |
| Parametric Trigger Product Introduction | Index-based coverage aligns with health system quality infrastructure and peer review outcomes. |
| Three-Year Master Contract Conversion | Hospital system consolidation favors extended terms over annual renewal procurement cycles. |
Methodological Framework
Cross-validation between primary interviews with underwriting executives, claims managers, and hospital procurement officers anchors the qualitative findings, while secondary triangulation draws from NAIC statutory filings, state insurance commissioner rate filings, and EU EIOPA solvency disclosures. Primary fieldwork captured perspectives from captive insurance managers, risk retention group administrators, and telemedicine platform compliance leads. Secondary sources include hospital procurement databases, GPO professional liability contracts, and CMS Medicare malpractice cost reports. Bottom-up premium volume estimates by coverage type and provider structure reconcile with top-down market sizing from carrier financial disclosures.
Calibration against historical loss ratio trends by state jurisdiction and specialty class informs the analytical framework across the analysis window. Segmentation dimensions modeled include coverage type duration mechanics, premium structure payment frequency, provider capital backing, and claim allegation severity profiles. CAGRs derive from premium volume trajectories by employed versus independent physician segments, telemedicine endorsement attachment rates, and captive formation velocity in high-litigation states. Industry-specific inputs incorporate FDA AI diagnostic clearance pipelines and EU MDR liability exposure tightening.
Practitioners should monitor telemedicine claims frequency emergence and Bermuda reinsurance capacity contraction for early signals of pricing inflection. Forecasts reflect assumptions around litigation cost volatility persistence and state tort reform durability. Macroeconomic interest rate shifts affecting captive investment income, regulatory deviation in EU AI Act implementation timelines, or technological disruption from autonomous diagnostic algorithms would prompt revision.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Insurance
Compulsory Third Party (CTP) Insurance Market
Insurance
United Kingdom Car Insurance Market
Insurance
Spain Group Health Insurance Market
Insurance
Saudi Arabia Travel Insurance Market
Insurance
Marine Crew Insurance Market
Insurance
Germany Travel Insurance Market
Insurance
China Business Income Insurance Market
Insurance
Norway Property and Casualty Insurance Market
Insurance
Europe Entertainment Insurance Market
Insurance
New Zealand Property and Casualty Insurance Market
Insurance
Jewelry Insurance Market
Insurance
India Dental Insurance Market
Insurance
Insurance Aggregators Market
Insurance
Event Insurance Market
Insurance
AI in Insurance Market
Insurance
Asia-Pacific Insurance Aggregators Market