
 Global Gastroenterology Ambulatory Surgery Center Market | 2026-2036
Global Gastroenterology Ambulatory Surgery Center Market Size, Share, and Industry Trends Forecast 2026-2036
Global Gastroenterology Ambulatory Surgery Center Market Foresight
Joint Commission accreditation is collapsing the window for new entrants lacking ambulatory health care credentials. GE Healthcare leverages integrated imaging platforms to sustain its installed base across North American surgery centers. Koninklijke Philips N.V. dominates endoscopy visualization systems, while Medtronic anchors therapeutic device supply chains through direct ASC contracting programs.
A gastroenterology ambulatory surgery center delivers same-day digestive procedures using conscious sedation, fluoroscopy-compatible suites, and sterile processing cycles under 45 minutes. These facilities reduce per-case costs by eliminating overnight stays while maintaining throughput above hospital outpatient departments. Colonoscopy volumes lead procedure type segments due to age-based screening guidelines, while ERCP cases concentrate margin pools because of anesthesia complexity and device intensity. Value-based care payment models are growing fastest as CMS bundles colonoscopy reimbursement, shifting financial risk toward facility operators.
FDA 510(k) clearance requirements govern endoscopic device introductions, while CMS Conditions for Coverage dictate ASC operational standards in the United States. EMA medical device regulations and national CE marking enforcement shape European market access for equipment suppliers. Stakeholders must monitor Medicare reimbursement rulemaking and site-neutral payment proposals that could reallocate procedure volumes between hospital outpatient departments and freestanding centers.
Market Dynamics
Medicare Advantage site-of-service migration is compressing hospital outpatient revenue while redirecting colonoscopy and endoscopic retrograde cholangiopancreatography volumes toward freestanding centers. This payment-driven volume shift is restructuring capital deployment across the United States, Germany, and Japan.
Growth Catalysts
- CMS site-neutral payment proposals:Bundled reimbursement models are pulling complex procedures out of hospital outpatient departments and into ASCs across the United States.
- Aging demographic screening mandates:Japan's colorectal cancer screening program and Germany's statutory health insurance preventive care expansions are expanding eligible patient pools.
- Conscious sedation protocols:Propofol-based anesthesia workflows are enabling same-day discharge for ERCP and advanced endoscopic mucosal resection cases.
Market Restraints
- Capital intensity of fluoroscopy suites:Lead-lined construction and C-arm installation costs exceed $2 million per procedure room, creating barrier thresholds for new entrants.
- Joint Commission accreditation concentration:United States facilities face 18-month credentialing windows that freeze expansion timelines for operators lacking existing ambulatory health care certifications.
- Anesthesiologist supply constraints:CRNA supervision requirements and board-certified gastroenterologist shortages in rural United States counties limit throughput scaling.
Strategic Opportunities
- India's underpenetrated screening infrastructure:National health mission colorectal cancer programs and rising medical tourism flows create first-mover positioning for JCI-accredited facilities.
- AI-assisted polyp detection integration:Computer-aided diagnosis systems are converging with 4K endoscopy platforms to reduce miss rates and justify premium reimbursement.
- United Kingdom independent sector provider framework:NHS England elective recovery contracts are opening procurement channels for day-case endoscopy capacity.
Industry Challenges
- Sterile processing cycle compression:FDA 510(k) cleared high-level disinfection systems must complete turnover in under 45 minutes to maintain morning-afternoon scheduling density.
- EMR-ASC integration complexity:Hospital-owned centers face Epic or Cerner interoperability friction when migrating cases from inpatient to freestanding settings.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Global Gastroenterology Ambulatory Surgery Center Market |
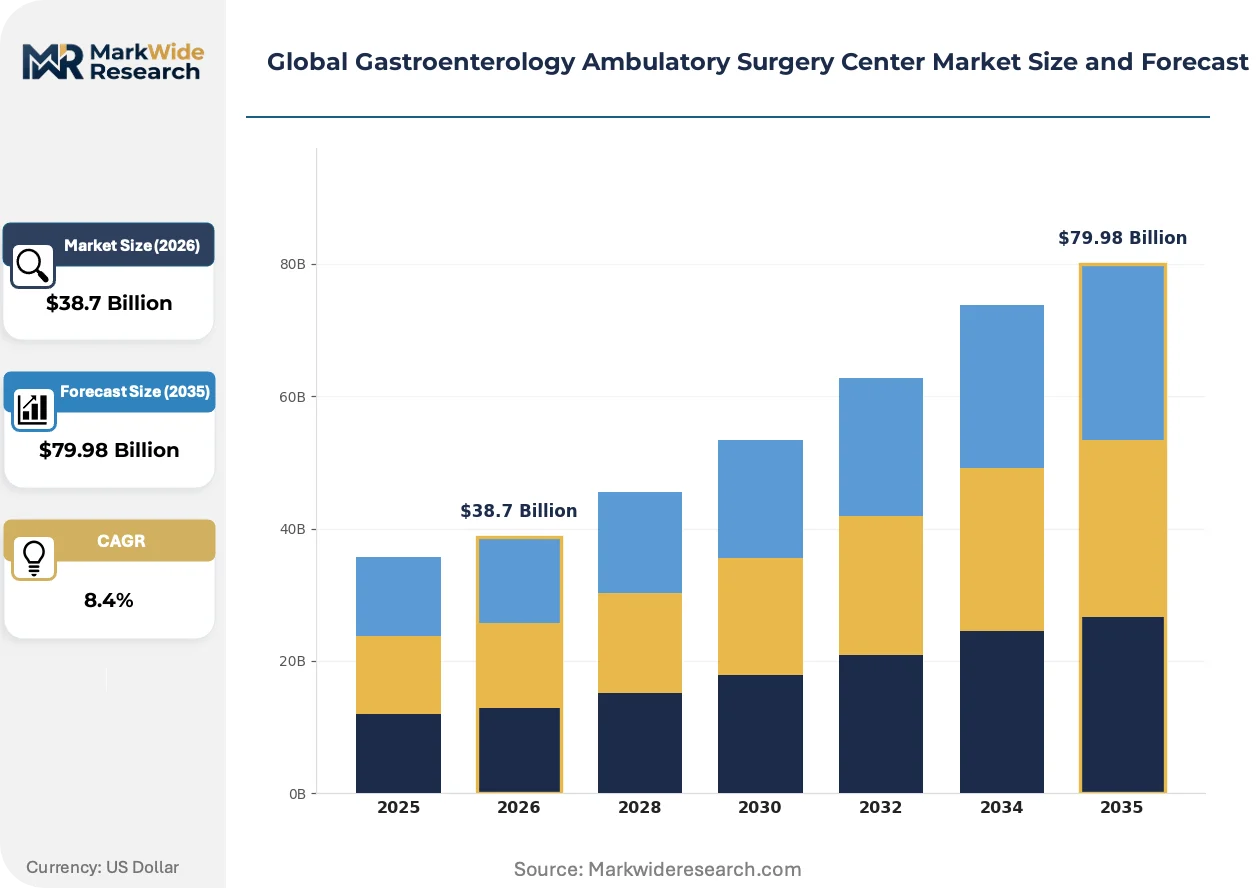
| Market Size in 2026 | $38.7 Billion |
| Market Size in 2035 | $79.98 Billion |
| CAGR (2026 – 2036) | 8.4% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Procedure Type: Endoscopy, Colonoscopy, ERCP, Capsule Endoscopy, Polypectomy, Sclerotherapy Facility Type: Physician-Owned, Hospital-Affiliated, Independent, Multi-Specialty Clinics, Freestanding Centers Payment Model: Private Insurance, Self-Pay, Government Reimbursement, Managed Care, Value-Based Care Patient Demographic: Adults, Geriatric, Pediatric, High-Risk Patients, Outpatients |
| Companies Covered | GE Healthcare, Gastro Health LLC, Koninklijke Philips N.V., Ontario Advanced Surgery Center, Universal Health Services Inc, Medtronic, Ohio Gastroenterology Group Inc, Alfa Surgery Center LLC, Becton Dickinson and Company, Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Global Gastroenterology Ambulatory Surgery Center Market Shifts & Advancements
Disposable endoscope technology and AI-assisted imaging are decomposing the traditional capital equipment-reuse service model. These shifts are compressing infection control liability while expanding procedure accessibility in lower-acuity settings.
Single-use duodenoscopes and colonoscopes are decomposing the established reprocessing infrastructure that has dominated gastroenterology supply chains for three decades. United States ASCs are adopting these devices fastest in ERCP workflows where sterilization failure liability concentrates. The structural consequence is a shift from capital expenditure cycles toward per-procedure consumable cost structures that alter margin mathematics.
EMA Medical Device Regulation (MDR) Article 120 transition timelines are forcing European ASCs to recertify legacy endoscopic equipment or accelerate replacement purchases. Manufacturers must submit updated technical documentation for devices previously cleared under the Active Implantable Medical Devices Directive. German and French facilities are responding by consolidating procurement around suppliers with established notified body relationships.
Direct-to-employer contracting is bypassing traditional payer intermediaries for routine screening colonoscopy bundles. Large self-insured employers in the United States are negotiating flat-rate per-case agreements with ASC networks, displacing percentage-based fee-for-service arrangements. This pattern is most visible in Texas and Florida metropolitan corridors where employer concentration supports dedicated carve-out networks.
Global Gastroenterology Ambulatory Surgery Center Market Segmentation
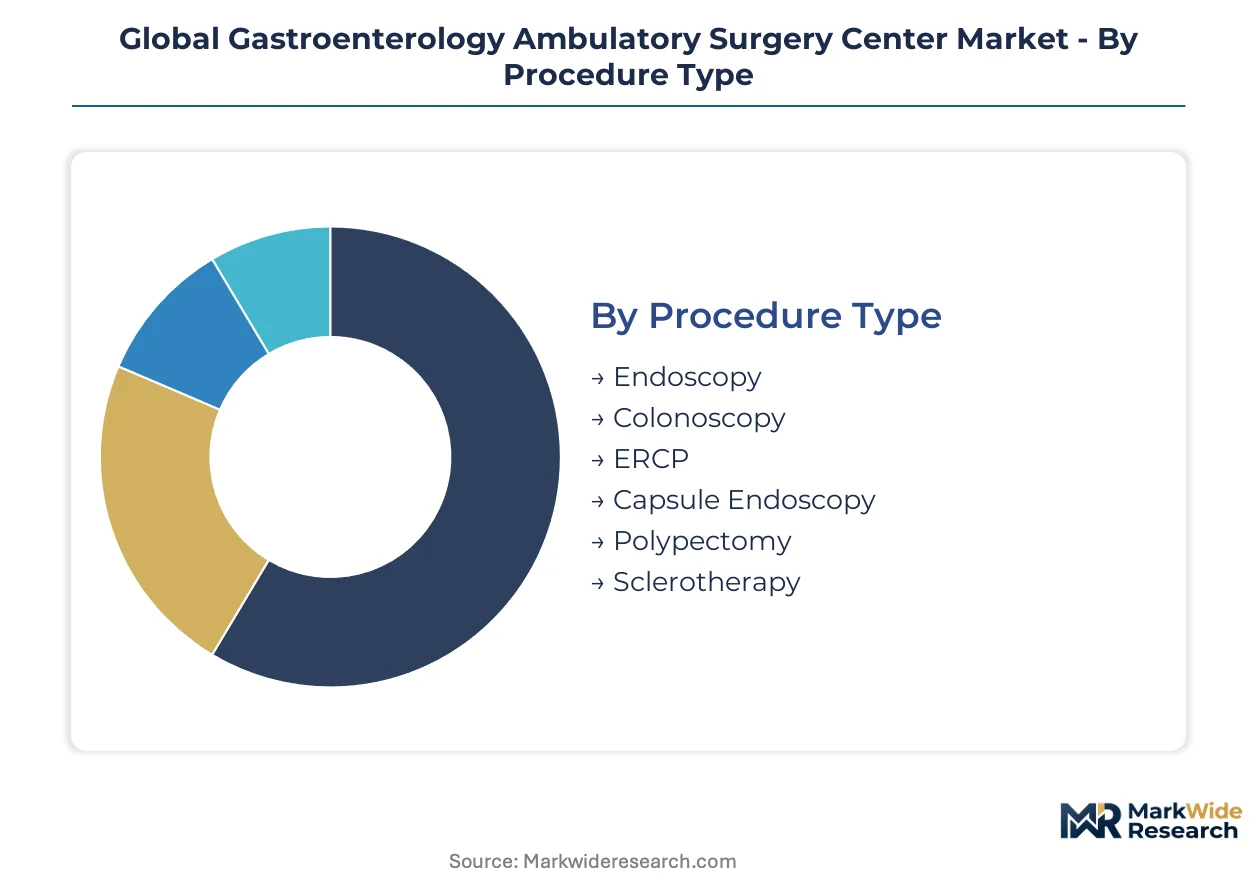
Procedure mix and facility ownership structure determine capital deployment patterns and reimbursement capture across gastroenterology ASCs. Payment model fragmentation creates divergent margin profiles that reshape competitive positioning in mature versus emerging markets.
Procedure Type:
Colonoscopy volumes concentrate in domestic screening programs across the United States, Germany, and Japan, while ERCP and advanced therapeutic procedures travel to specialized export corridors serving medical tourism flows.
- Colonoscopy:Age-based screening guidelines in the United States and Japan drive bulk procedure volumes through Medicare Advantage and statutory insurance channels. Japanese prefectural screening programs and German preventive care expansions anchor demand concentration in aging populations.
- ERCP:Therapeutic biliary interventions require anesthesia complexity and fluoroscopy suites that limit site eligibility. Cases concentrate in hospital-affiliated centers across the United States and tertiary referral networks in Germany where device intensity justifies premium reimbursement.
- Endoscopy:Diagnostic upper GI procedures serve reflux and dyspepsia workups through high-throughput workflows.
- Capsule Endoscopy:Small bowel visualization targets obscure GI bleeding in specialized referral settings.
- Polypectomy:Therapeutic removal during index colonoscopy captures margin uplift without separate facility fees.
- Sclerotherapy:Variceal bleeding interventions concentrate in liver disease referral centers with interventional gastroenterology depth.
Colonoscopy commands the established base. The steepest expansion runs through ERCP as site-neutral payment pulls complex cases toward freestanding settings.
Facility Type:
Ownership structure determines access to capital, payer contracting leverage, and referral network integration across cost tiers from lean physician practices to capital-intensive multi-specialty platforms.
- Physician-Owned:Gastroenterologist partnerships dominate United States suburban markets with lean overhead and direct payer relationships. Medicare Advantage site-of-service incentives and direct-to-employer contracting in Texas and Florida metropolitan corridors accelerate volume capture outside hospital systems.
- Hospital-Affiliated:Health system subsidiaries leverage EMR integration and captive referral bases to defend procedural share. Epic and Cerner interoperability requirements in United States markets create switching costs that freeze independent competition.
- Independent:Freestanding operators without system affiliation compete on price transparency and scheduling density.
- Multi-Specialty Clinics:Shared overhead across GI, ophthalmology, and orthopedics spreads fixed costs in saturated markets.
- Freestanding Centers:Purpose-built ASCs with dedicated sterile processing and anesthesia staffing target high-volume screening contracts.
Hospital-affiliated facilities command the established base. The steepest expansion runs through physician-owned models as Medicare Advantage site-of-service migration accelerates.
Payment Model:
Reimbursement mechanism determines patient access, pricing power, and administrative burden across government, commercial, and self-funded channels.
- Government Reimbursement:CMS Medicare Physician Fee Schedule and national health insurance schemes in Japan and Germany set benchmark rates that compress margins but guarantee volume. CMS site-neutral payment proposals and bundled colonoscopy reimbursement in United States markets shift financial risk toward facility operators.
- Value-Based Care:Bundled payments and quality-linked contracts reward outcome efficiency over procedure volume. United States ASCs with HEDIS screening metrics and polyp detection rate benchmarks capture shared savings in Medicare Advantage and commercial risk arrangements.
- Private Insurance:Commercial fee-for-service maintains premium pricing in employer-sponsored markets.
- Managed Care:PPO and HMO networks negotiate discounted rates for narrow-panel access.
- Self-Pay:Direct consumer payment concentrates in cosmetic and screening procedures outside insurance mandates.
Government reimbursement commands the established base. Value-based care contracts are gaining share fastest as CMS bundles colonoscopy reimbursement and employers seek fixed-cost screening solutions.
Patient Demographic:
Age and risk stratification determine procedure complexity, anesthesia requirements, and site-of-service eligibility across screening versus diagnostic indications.
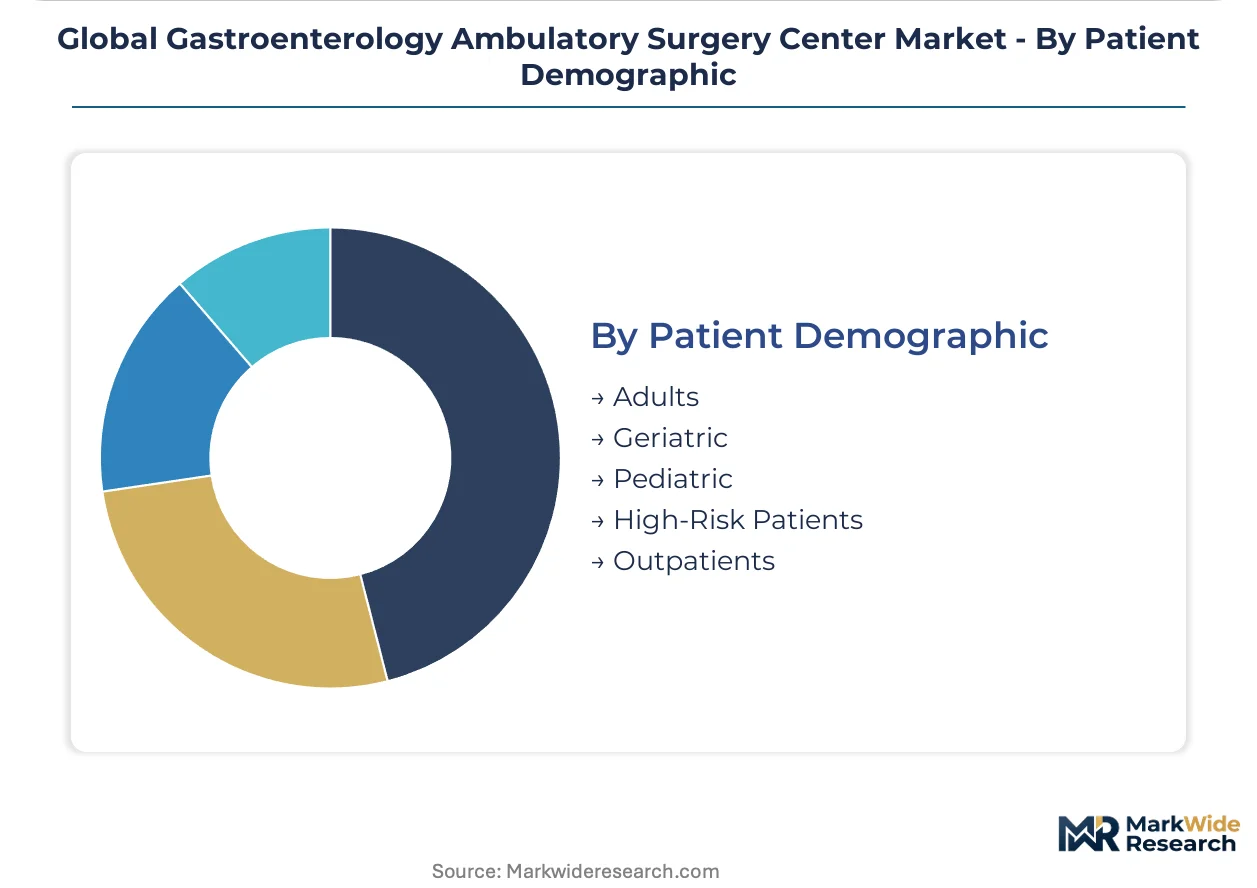
- Geriatric:Patients over 65 generate dominant procedure volumes through age-triggered screening guidelines and surveillance intervals. United States Medicare eligibility, Japanese national screening programs, and German statutory preventive care expansions concentrate demand in this cohort.
- High-Risk Patients:Family history, inflammatory bowel disease, and prior adenoma surveillance drive accelerated screening protocols. Complex comorbidity profiles in United States markets restrict site eligibility to hospital-affiliated centers with anesthesia backup and emergency response capabilities.
- Adults:Working-age screening and symptomatic workups fill midweek scheduling capacity.
- Outpatients:Same-day discharge candidates dominate ASC-eligible volume.
- Pediatric:Congenital and inflammatory conditions in specialized referral centers represent niche demand.
Geriatric screening commands the established base. The steepest expansion runs through high-risk surveillance protocols as genetic risk stratification and prior adenoma detection expand eligible pools.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Buyer concentration clusters around Medicare Advantage plans in the United States, statutory health insurance funds in Germany, and prefectural screening programs in Japan. These three archetypes drive site-of-service migration toward freestanding centers.
United States
Medicare Advantage enrollment growth pushes colonoscopy volumes toward ASCs through site-of-service incentives. CMS Conditions for Coverage govern ASC operational standards while bundled reimbursement models shift financial risk to facility operators. Texas and Florida metropolitan corridors host dense networks of physician-owned centers capturing direct-to-employer contracts.
Germany
Statutory health insurance preventive care expansions widen eligible pools for colorectal cancer screening. EMA Medical Device Regulation recertification timelines pressure ASCs to replace legacy endoscopic equipment. Bavarian and North Rhine-Westphalian facilities consolidate procurement around suppliers with established notified body relationships.
Japan
Prefectural colorectal cancer screening programs anchor demand in aging populations. PMDA device clearance requirements shape endoscopy platform introductions. Kanto and Kansai regions concentrate specialized ERCP capacity in tertiary referral networks with anesthesia backup capabilities.
India
National health mission colorectal cancer programs and medical tourism flows create positioning opportunities for JCI-accredited facilities. CDSCO medical device regulations govern endoscopic equipment market access. Maharashtra and Karnataka host emerging private ASC networks targeting corporate health screening contracts.
United Kingdom
NHS England elective recovery contracts open procurement channels for day-case endoscopy capacity. MHRA post-Brexit device regulations diverge from EU MDR timelines. London and Southeast England concentrate independent sector providers competing for fixed-price screening bundles.
Global Gastroenterology Ambulatory Surgery Center Market Competitive Landscape
Player mix skews toward integrated imaging platform suppliers and therapeutic device manufacturers with direct ASC contracting programs. Market structure concentrates around equipment vendors with installed base maintenance capabilities and service networks spanning multiple geographies. Three archetypes dominate: capital equipment suppliers with fluoroscopy-compatible suite integration, disposable endoscope specialists decomposing reprocessing infrastructure, and facility management operators scaling multi-site networks. Consolidation through ASC chain acquisitions and technology licensing partnerships represent the dominant competitive vectors.
Within the integrated imaging tier, GE Healthcare and Koninklijke Philips N.V. occupy anchor positions through platform breadth. Medtronic exemplifies the therapeutic device archetype with direct contracting programs. Among facility operators, Gastro Health LLC represents the physician partnership model scaling across suburban United States markets.
| Leading Market Players |
|---|
| GE Healthcare |
| Gastro Health LLC |
| Koninklijke Philips N.V. |
| Ontario Advanced Surgery Center |
| Universal Health Services Inc |
| Medtronic |
| Ohio Gastroenterology Group Inc |
| Alfa Surgery Center LLC |
| Becton Dickinson and Company |
| Others |
Supply & Pricing Matrix
Capacity utilization at fluoroscopy-compatible suite manufacturers in the United States and Germany compresses procurement timelines for ASC operators while establishing price floors for lead-lined construction and C-arm installations. This scale concentration rewards multi-site networks with volume-based equipment discounts and penalizes single-facility entrants facing per-unit premiums on sterilization systems and anesthesia platforms.
Pricing Analysis
Cost-plus contracts with annual PPI indexation dominate capital equipment procurement for United States gastroenterology ASCs, with GE Healthcare and Koninklijke Philips N.V. embedding service attach rates that inflate lifetime ownership costs. Price differentiation rests on Joint Commission accreditation status and procedural volume tiers, with hospital-affiliated centers capturing preferential rates through bundled purchasing consortiums. Pricing pressure intensifies as disposable endoscope adoption shifts margin pools from capital cycles toward per-procedure consumable costs. Physician-owned suburban facilities exhibit highest price sensitivity due to lean overhead structures, while hospital-affiliated centers absorb premiums for EMR interoperability guarantees.
Supply Chain Analysis
The United States and Germany anchor fluoroscopy suite manufacturing and high-level disinfection system production, with Japan supplying specialized endoscopic imaging sensors and propofol anesthesia delivery platforms. Raw material dependencies center on lead shielding for procedure rooms, germanium-based scintillation crystals for C-arm detectors, and medical-grade polymers for single-use endoscope sheaths. Supply chain risk concentrates in single-source vulnerability for PMDA-cleared imaging components subject to extended regulatory review timelines. Distribution runs through manufacturer-direct sales forces for capital equipment and GPO-aggregated channels for consumables and disposables.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Service-attach revenue streams including sterilization system maintenance contracts and AI-assisted polyp detection software subscriptions are expanding faster than hardware sales, transforming capital equipment vendors into recurring-revenue platforms. This shift rewards operators who bundle procedural workflows with predictive analytics and remote technical support.
For Market Incumbents: Secure direct ASC contracting relationships before disposable endoscope specialists decompose established reprocessing infrastructure. Defend installed base through backward integration into sterile processing consumables and predictive maintenance software layers. Consolidate procurement leverage by acquiring physician-owned networks in Texas and Florida metropolitan corridors where Medicare Advantage site-of-service migration concentrates. For New Entrants and Emerging Players: Anchor in India's underpenetrated screening infrastructure where national health mission colorectal cancer programs and JCI accreditation gaps create first-mover positioning. Target corporate health screening contracts in Maharashtra and Karnataka with mobile endoscopy units and flat-rate per-case pricing. Deploy direct-to-employer sales channels bypassing traditional payer intermediaries. For Investors and Strategic Acquirers: Mid-cycle technology positioning favors facility management operators scaling multi-site networks with standardized sterile processing protocols and anesthesia staffing models. Long-term viability hinges on capturing shared savings in value-based care arrangements as CMS bundled reimbursement expands. Monitor Medicare site-neutral payment rulemaking as the primary inflection signal for volume reallocation between hospital outpatient departments and freestanding centers.| Strategic Initiative | Industry Significance |
|---|---|
| Disposable Endoscope Transition | Decomposes three-decade reprocessing infrastructure while shifting margin pools toward per-procedure consumables. |
| AI-Assisted Polyp Detection Integration | Reduces miss rates and justifies premium reimbursement through computer-aided diagnosis systems. |
| Direct-to-Employer Contracting | Bypasses traditional payer intermediaries with flat-rate screening bundles in self-insured employer markets. |
| Joint Commission Accreditation Investment | Collapses entry windows for uncredentialed operators while freezing expansion timelines at 18-month credentialing cycles. |
| Reimbursement Strategy Alignment | Captures shared savings in Medicare Advantage risk arrangements as CMS bundles colonoscopy payments. |
Research Methodology
Desk research of FDA 510(k) clearance databases, CMS Medicare Physician Fee Schedule rulemaking archives, and EMA Medical Device Regulation technical documentation preceded structured interviews with ASC medical directors, GPO contracts managers, biomedical equipment procurement leads, and sterile processing technicians. Primary fieldwork across United States, German, and Japanese facilities validated capital deployment patterns and reimbursement capture mechanisms. Secondary sources included hospital procurement databases, GPO contract disclosures, and CMS Conditions for Coverage regulatory filings. Bottom-up facility-level capacity modeling triangulated against top-down national screening program volume projections.
Variance decomposition across procedure type, facility ownership structure, payment model, and patient demographic segments structured the analytical framework over the projection horizon. CAGRs derived from logistic diffusion curves fitted to Medicare Advantage enrollment trajectories and statutory insurance screening expansion timelines. Forecast inputs incorporated fluoroscopy suite installation backlogs, anesthesiologist supply constraints by United States county, and EMA MDR recertification compliance deadlines for legacy endoscopic equipment.
Decision-makers should treat outputs as directional under assumptions of sustained CMS site-neutral payment momentum and stable Joint Commission accreditation timelines; material deviation in regulatory rulemaking or reimbursement bundling scope would warrant model refresh. Recalibration cycles align with material shifts in Medicare Advantage penetration rates, disposable endoscope cost curves, and AI-assisted imaging regulatory clearances.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Surgical Instruments
Surgical Drainage Devices Market
Surgical Instruments
Dermal Curettes Market
Surgical Instruments
Global Urology Surgical Instruments Market
Surgical Instruments
Non-Absorbable Sutures Market
Surgical Instruments
Surgical Stents Market
Surgical Instruments
Dissolvable Sutures Market
Surgical Instruments
Surgical Hemostats Market
Surgical Instruments
Laparoscopic Gynecological Procedures Market
Surgical Instruments
Ultrasound Needle Guides Market
Surgical Instruments
Global Pain Management and Surgical Devices Market
Surgical Instruments
Laparoscopic Power Morcellators Market
Surgical Instruments
Surgical Hand-Access Port Market
Surgical Instruments
Dental Surgical Microscopes Market
Surgical Instruments
Global Surgical Lasers Market
Surgical Instruments
Neurosurgery Surgical Power Tools Market
Surgical Instruments
Robotic Surgery Market