
 Community Acquired Bacterial Pneumonia (CABP) Treatment Market | 2026-2036
Community Acquired Bacterial Pneumonia (CABP) Treatment Market Size, Share, and Industry Trends Forecast 2026-2036
Community Acquired Bacterial Pneumonia (CABP) Treatment Market Outlook
A widening capital-intensity gap between large-cap pharmaceutical conglomerates and specialized antibacterial developers is reorganizing competitive dynamics in CABP therapeutics. Pfizer Inc leverages its established hospital formulary relationships to sustain broad-spectrum antibiotic distribution across acute-care networks. Nabriva Therapeutics specializes in late-stage pleuromutilin development, occupying a narrow but defensible niche against macrolide-resistant pathogens.
Community Acquired Bacterial Pneumonia treatment encompasses antibacterial, vaccine, and supportive interventions targeting pathogens acquired outside healthcare settings, with intravenous-to-oral step-down protocols representing a critical clinical parameter for reducing hospital length-of-stay. The primary purpose centers on reducing mortality from Streptococcus pneumoniae and atypical bacterial infections while curbing antimicrobial resistance propagation. Antibiotics dominate current revenue pools, though vaccines command superior margins through pediatric and geriatric immunization schedules. Oral delivery modes capture the fastest expansion as outpatient facilities expand observation-based management of moderate CABP cases.
The FDA's QIDP framework and EMA's priority medicines scheme shape development incentives for novel antibacterial classes, while the CDC's antimicrobial resistance tracking networks influence hospital prescribing protocols. These regulatory architectures determine market access timelines and reimbursement positioning for new entrants against entrenched generic macrolides and fluoroquinolones. Stakeholders must monitor resistance surveillance data and pipeline progression against WHO-prioritized pathogen targets to anticipate shifts in standard-of-care protocols.
Market Dynamics
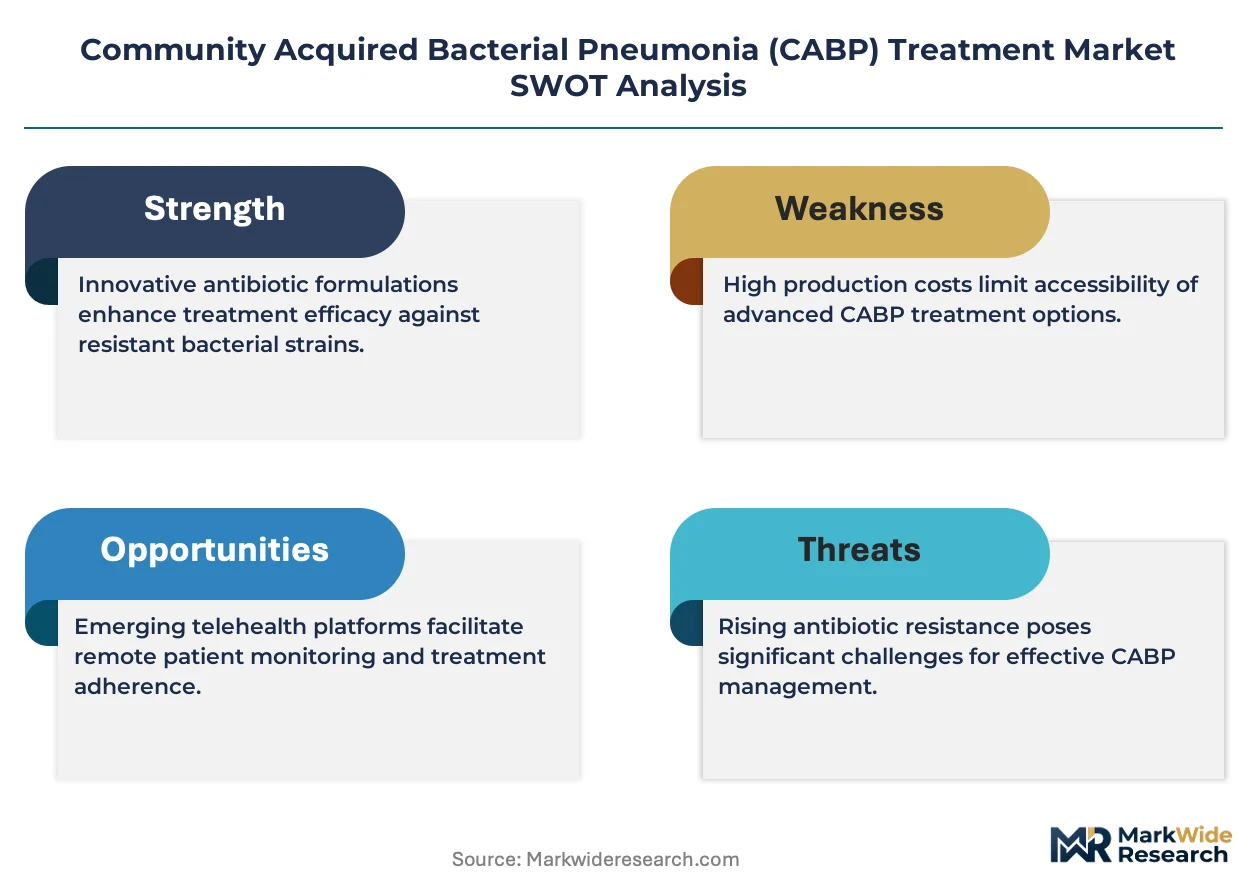
The FDA's QIDP designation pathway is compressing development timelines for novel antibacterial classes, while hospital formulary consolidation concentrates purchasing power among integrated delivery networks seeking standardized step-down protocols.
Growth Catalysts
- Aging Demographics:The United States Census Bureau projects expanded geriatric populations requiring inpatient CABP management, sustaining demand for intravenous antibiotic administration in acute-care settings.
- QIDP Acceleration:The FDA's Qualified Infectious Disease Product framework grants priority review and extended exclusivity, incentivizing development against resistant Streptococcus pneumoniae strains.
- Antimicrobial Resistance Surveillance:The CDC's Emerging Infections Program tracks macrolide and fluoroquinolone resistance patterns, driving formulary updates toward newer therapeutic classes.
Market Restraints
- Generic Erosion:Patent expiration for legacy respiratory fluoroquinolones has collapsed pricing power, constraining revenue pools for follow-on innovators.
- Reimbursement Compression:Medicare's Hospital-Acquired Condition reduction program penalizes extended length-of-stay, limiting premium pricing for novel intravenous therapies.
- Clinical Trial Complexity:Non-inferiority study designs for CABP require large patient populations and radiographic endpoint adjudication, elevating development costs.
Strategic Opportunities
- Outpatient Observation Expansion:United States ambulatory surgical centers are adding overnight antibiotic infusion capabilities, creating new channel access beyond traditional hospital admission.
- Pediatric Formulation Gaps:The EMA's priority medicines scheme offers regulatory support for age-appropriate dosing of pleuromutilin derivatives in community-acquired infections.
- Diagnostic-Therapeutic Pairing:Rapid molecular pneumococcal detection platforms enable pathogen-directed therapy selection, creating integration partnerships between assay developers and antibiotic manufacturers.
Industry Challenges
- Specialized Infectious Disease Talent:Clinical trial investigator networks for CABP protocols require board-certified ID physicians, creating recruitment bottlenecks in non-academic sites.
- Pharmacovigilance Infrastructure:Post-marketing surveillance for novel antibacterial classes demands expanded safety databases to detect rare adverse events in real-world use.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Community Acquired Bacterial Pneumonia (CABP) Treatment Market |
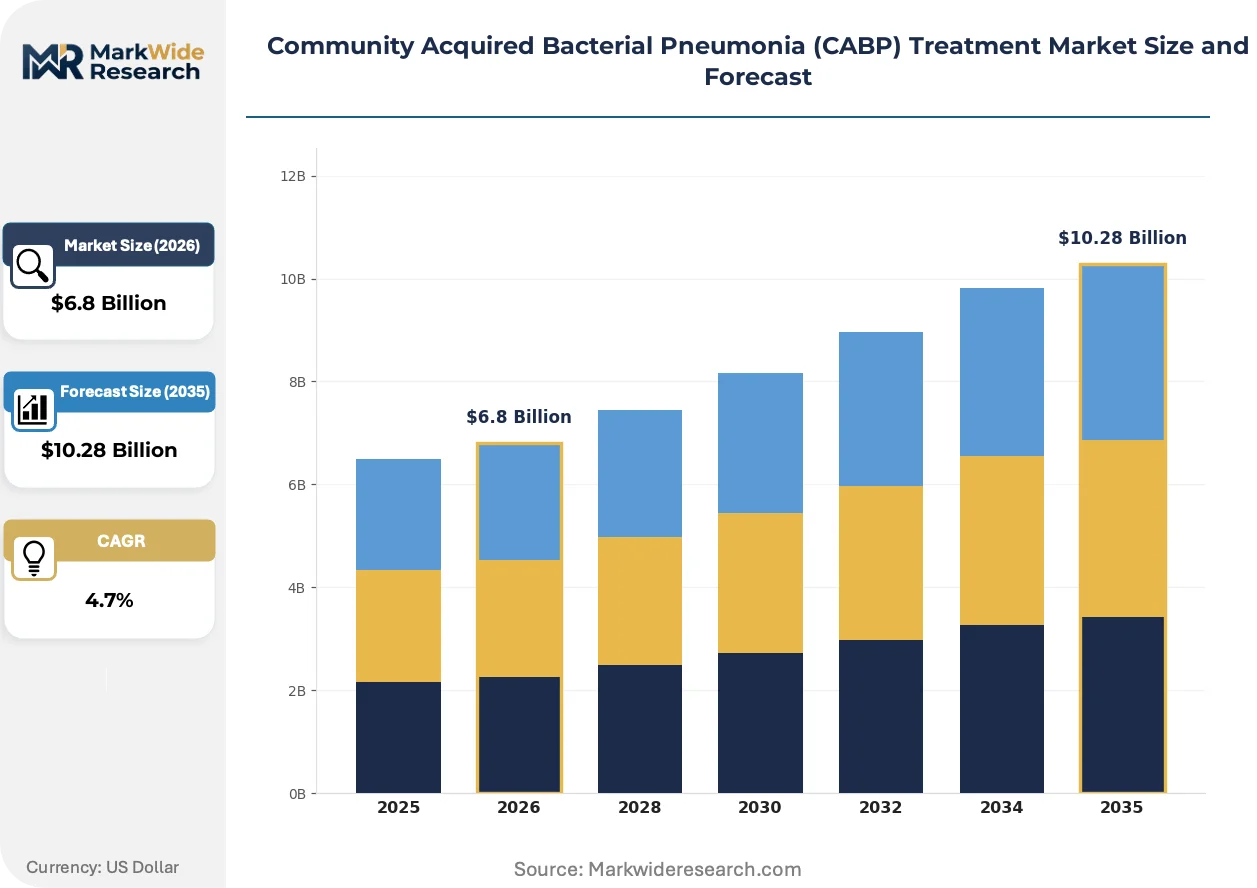
| Market Size in 2026 | $6.8 Billion |
| Market Size in 2035 | $10.28 Billion |
| CAGR (2026 – 2036) | 4.7% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Product Type: Antibiotics, Vaccines, Supportive Care, Combination Therapy End User: Hospitals, Outpatient Facilities, Home Healthcare, Clinics Delivery Mode: Oral, Intravenous, Inhalation, Topical Therapy Area: Respiratory Infections, Infectious Diseases, Pulmonary Disorders, Others |
| Companies Covered | Pfizer Inc, Merck & Co Inc, AstraZeneca plc, GlaxoSmithKline plc, Sanofi S.A., Bayer AG, Novartis AG, Nabriva Therapeutics, Paratek Pharmaceuticals Inc, Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Community Acquired Bacterial Pneumonia (CABP) Treatment Market Strategic Shifts
Antibiotic development is fragmenting across delivery-mode specialization, with oral bioavailability optimization competing against hospital-centric intravenous formulations for clinical and commercial positioning.
Pleuromutilin chemistry is decomposing traditional macrolide positioning in CABP therapy. Hospital pharmacy committees are adopting lefamulin for beta-lactam-allergic patients requiring atypical coverage. This molecular class is decomposing the historical dichotomy between community and hospital-acquired pneumonia treatment algorithms.
The FDA's QIDP pathway extends market exclusivity for qualified antibacterial products, altering competitive duration calculations for development-stage assets. Sponsors are prioritizing pathogen-specific indications over broad-spectrum labels to secure designation. Early-stage pipelines are responding with narrowed target product profiles against resistant Streptococcus pneumoniae.
Integrated delivery networks are consolidating antibiotic procurement through centralized pharmacy and therapeutics committees. Independent hospitals are surrendering formulary autonomy to system-wide protocols, compressing vendor access points. This concentration is most pronounced in the United States, where Catholic health systems and for-profit chains now control majority inpatient bed capacity.
Community Acquired Bacterial Pneumonia (CABP) Treatment Market Segmentation
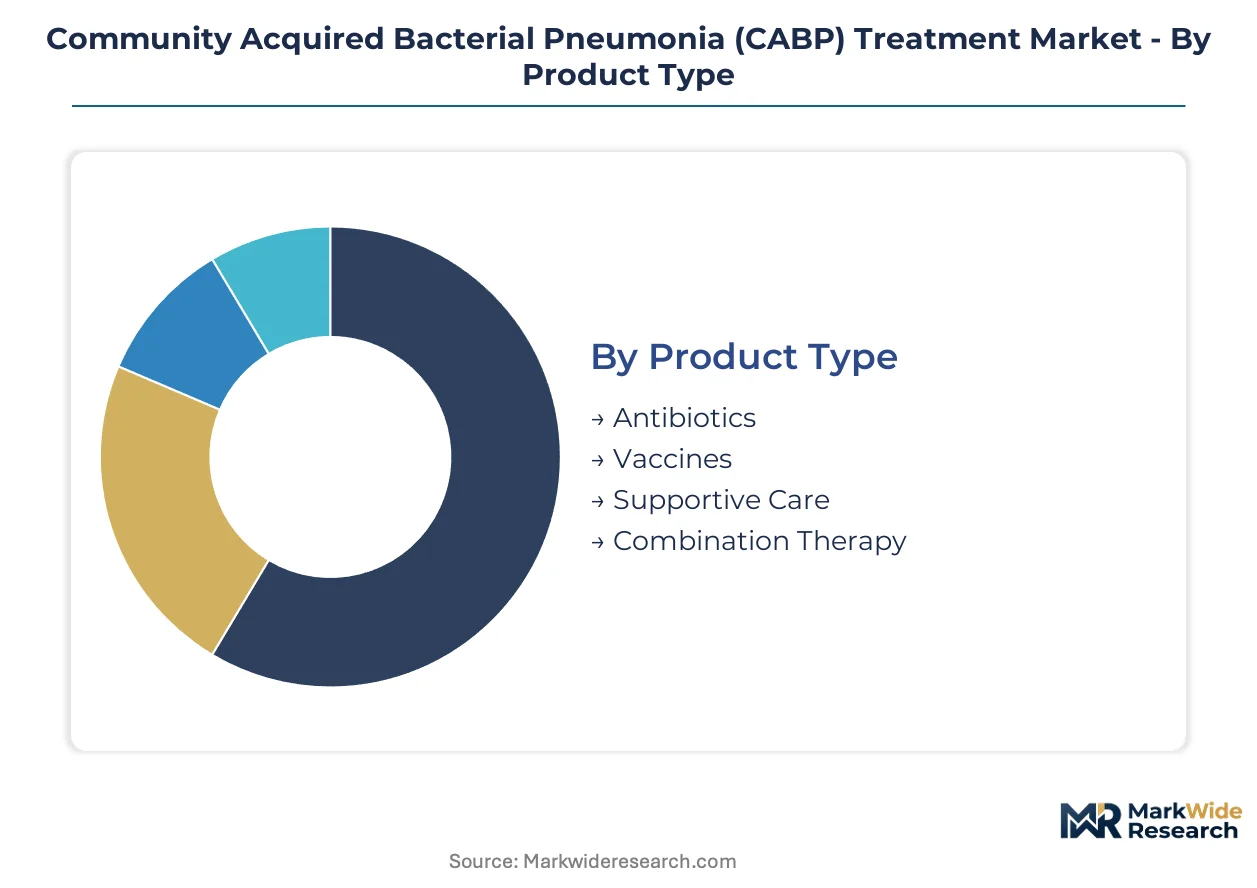
CABP treatment revenue pools fragment across product chemistry, care setting economics, and administration logistics. Understanding margin concentration across these dimensions reveals where pharmaceutical sponsors and health systems allocate capital for competitive positioning.
Product Type:
Antibiotics command the deepest margin pools through hospital formulary premiums and QIDP-extended exclusivity, while vaccines generate superior per-dose profitability through pediatric and geriatric immunization schedules.
- Antibiotics:Beta-lactams, macrolides, fluoroquinolones, and pleuromutilins constitute the therapeutic backbone. United States hospital systems concentrate procurement through integrated delivery networks seeking standardized step-down protocols. Resistance surveillance by the CDC's Emerging Infections Program accelerates formulary turnover toward novel classes.
- Vaccines:Pneumococcal conjugate and polysaccharide formulations target prevention in high-risk populations. Pediatric and geriatric immunization schedules in the United States sustain volume through CDC Advisory Committee on Immunization Practices recommendations.
- Supportive Care:Oxygen therapy, bronchodilators, and corticosteroids manage acute respiratory symptoms. These adjunctive interventions capture reimbursement through diagnosis-related group bundling rather than standalone pharmaceutical margins.
- Combination Therapy:Dual-agent regimens pair beta-lactams with atypical coverage for severe cases. Hospital pharmacy committees scrutinize these protocols for length-of-stay impact under Medicare reimbursement compression.
The dominant share belongs to Antibiotics, while Vaccines are closing the gap fastest through expanded age indication approvals.
End User:
Care setting determines reimbursement architecture and pricing power, with hospital-based administration commanding premium intravenous rates versus compressed outpatient fee schedules.
- Hospitals:Acute-care facilities manage severe CABP through emergency department admission and step-down protocols. United States integrated delivery networks consolidate purchasing power across Catholic health systems and for-profit chains controlling majority inpatient bed capacity.
- Outpatient Facilities:Ambulatory surgical centers and observation units administer short-course intravenous therapy. Overnight infusion capabilities in United States outpatient settings are expanding channel access beyond traditional admission.
- Home Healthcare:Home infusion services deliver parenteral antibiotics post-discharge. Medicare reimbursement constraints limit penetration to commercially insured populations with care coordination support.
- Clinics:Primary care and urgent care settings manage uncomplicated cases through oral prescribing. Generic macrolide and fluoroquinolone dominance compresses revenue per prescription in this channel.
Hospitals retain the largest volume position, though Outpatient Facilities are expanding most quickly through observation-status billing optimization.
Delivery Mode:
Route of administration shapes clinical trial design requirements, manufacturing complexity, and competitive differentiation through bioavailability engineering.
- Oral:Tablet and suspension formulations enable outpatient completion of therapy courses. Oral bioavailability optimization competes against intravenous development for sponsor investment priority.
- Intravenous:Hospital-administered infusion dominates severe case management. Shorter intravenous-to-oral transition protocols represent a critical clinical parameter for reducing length-of-stay penalties.
- Inhalation:Nebulized delivery targets localized pulmonary drug concentration. Limited approved agents constrain current revenue contribution despite theoretical pharmacokinetic advantages.
- Topical:Minimal relevance in CABP therapy given pathogen dissemination patterns. Development pipelines show negligible activity in this delivery mode.
Intravenous formulations hold the incumbent position, while Oral delivery is gaining share fastest through outpatient observation expansion.
Therapy Area:
Specialty designation influences regulatory pathway access, investigator recruitment, and reimbursement coding precision.
- Respiratory Infections:Pulmonology and critical care specialists drive prescribing decisions. Academic medical centers anchor clinical trial networks for novel antibacterial classes.
- Infectious Diseases:Board-certified ID physicians adjudicate formulary placement and resistance-guided therapy. Recruitment bottlenecks for CABP protocols concentrate in non-academic sites lacking specialized talent.
- Pulmonary Disorders:COPD and asthma comorbidity management intersects with CABP treatment. Hospital readmission risk programs target this overlap population.
- Others:General internal medicine and emergency medicine handle undifferentiated community-acquired pneumonia. Diagnostic uncertainty in this segment sustains empiric broad-spectrum prescribing.
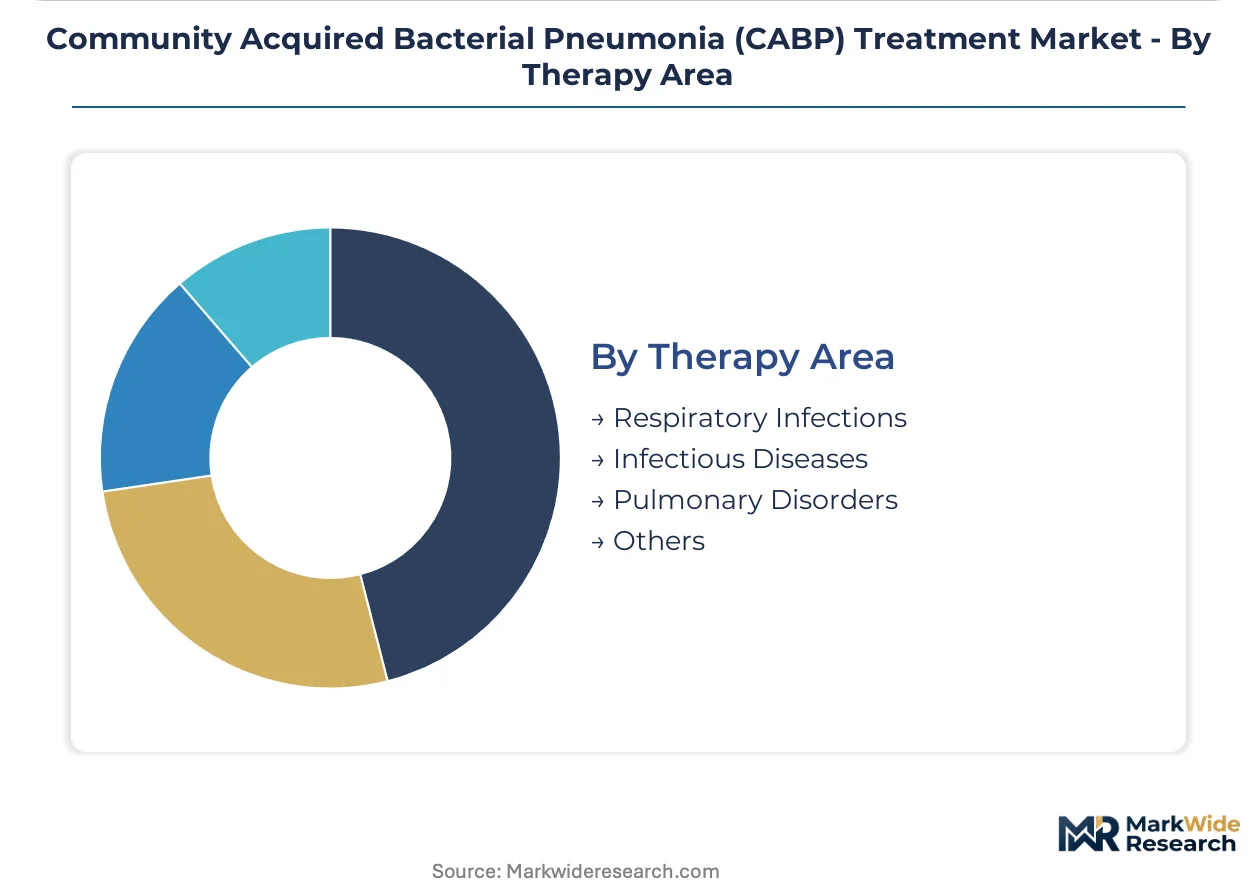
Respiratory Infections captures the dominant clinical focus, while Infectious Diseases is climbing the fastest through antimicrobial stewardship program expansion.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Hospital formulary consolidation and resistance surveillance intensity vary sharply by geography, with the United States driving intravenous-to-oral protocol innovation while European systems emphasize outpatient stewardship and Asian markets scale diagnostic-therapeutic pairing.
United States
Aging demographics and integrated delivery network purchasing concentration sustain inpatient antibiotic volumes. The FDA's QIDP designation accelerates novel antibacterial approvals against resistant Streptococcus pneumoniae. Boston and San Francisco anchor clinical trial networks for pleuromutilin development.
Germany
Hospital pharmacy committees prioritize step-down protocols under DRG reimbursement pressure. The EMA's priority medicines scheme supports pediatric formulation development for community-acquired infections. Baden-Württemberg and Bavaria concentrate antimicrobial stewardship program implementation.
Japan
Geriatric pneumonia burden drives demand for rapid intravenous-to-oral transitions in acute-care settings. PMDA's Sakigake designation pathway compresses review timelines for novel antibacterial classes. Tokyo and Osaka metropolitan areas host the majority of infectious disease clinical trial sites.
United Kingdom
NHS England's antimicrobial resistance strategy shapes hospital prescribing protocols toward narrow-spectrum agents. NICE technology appraisals determine reimbursement access for novel therapeutics. London and the Greater Manchester health system pilot diagnostic-directed therapy programs.
India
Rising private hospital capacity and antimicrobial resistance surveillance expansion create demand for branded respiratory antibiotics. CDSCO's accelerated approval pathway for QIDP-recognized products enables faster market entry. Mumbai and Bangalore concentrate contract research organization activity for CABP trials.
Community Acquired Bacterial Pneumonia (CABP) Treatment Market Competitive Environment
A small set of integrated leaders sits above a broader specialist tier in CABP therapeutics. Large-cap pharmaceutical conglomerates leverage established hospital formulary relationships and broad-spectrum antibiotic portfolios across acute-care networks. Specialized antibacterial developers occupy defensible niches against macrolide-resistant pathogens through novel chemistry classes. Dominant competitive moves include diagnostic-therapeutic integration partnerships and geographic expansion into outpatient observation channels.
Among diversified pharmaceutical leaders, Pfizer Inc and Merck & Co Inc exemplify the integrated tier through hospital-centric distribution scale, while Nabriva Therapeutics occupies a position within the specialized developer archetype focused on pleuromutilin chemistry innovation.
| Leading Market Players |
|---|
| Pfizer Inc |
| Merck & Co Inc |
| AstraZeneca plc |
| GlaxoSmithKline plc |
| Sanofi S.A. |
| Bayer AG |
| Novartis AG |
| Nabriva Therapeutics |
| Paratek Pharmaceuticals Inc |
| Others |
Value Chain & Pricing Dynamics
Hospital formulary consolidation in the United States generates procurement scale economies that compress price floors for generic macrolides while sustaining premium positioning for QIDP-designated novel antibacterials. This concentration dynamic reshapes manufacturer incentives toward extended exclusivity strategies rather than volume-driven commoditization.
Pricing Analysis
After-sales revenue from hospital step-down protocol advisory services and resistance surveillance data subscriptions drives lifetime value for pleuromutilin developers. Contract-based long-term formulary agreements dominate the pricing structure, with differentiation anchored in FDA QIDP certification tier and integrated delivery network volume scale. Cost compression in the generic fluoroquinolone tier intensifies as patent cliffs deepen, while Medicare reimbursement constraints heighten price sensitivity among safety-net hospital systems versus less constrained academic medical centers.
Supply Chain Analysis
Active pharmaceutical ingredient manufacturing for respiratory antibacterials concentrates in India, China, and Italy, with fermentation-derived pleuromutilin precursors drawing from specialized European biotechnology capacity. Key dependencies include beta-lactam intermediate supply from Indian contract manufacturers, macrolide fermentation feedstock from Chinese producers, and sterile fill-finish capabilities concentrated in Germany and the United States. Single-source vulnerability for pleuromutilin active pharmaceutical ingredients creates exposure to regulatory inspection delays. Distribution runs through integrated delivery network centralized pharmacy and therapeutics committees, with direct-to-hospital contracting displacing traditional wholesale channels.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Community Acquired Bacterial Pneumonia therapeutics sits at a platform-economics inflection where diagnostic-therapeutic pairing ecosystems are displacing empiric prescribing protocols. Rapid molecular pneumococcal detection platforms from Cepheid and BioFire now interoperate with formulary decision support, reshaping competitive moats.
For Market Incumbents: Secure diagnostic-therapeutic integration partnerships before atypical coverage commoditization accelerates. Pfizer and Merck must deepen backward integration into rapid resistance testing platforms to defend formulary positioning against pleuromutilin challengers. Capacity addition in United States outpatient observation channels represents a critical lever as ambulatory surgical centers expand overnight infusion capabilities.
For New Entrants and Emerging Players: Pediatric formulation gaps in pleuromutilin derivatives expose an under-served service layer where incumbents lack age-appropriate dosing infrastructure. Nabriva-class specialists should target EMA priority medicines scheme support for community-acquired infection indications in pediatric populations. A go-to-market angle anchored in antimicrobial stewardship program partnerships with mid-sized Catholic health systems offers the most penetrable entry vector.
For Investors and Strategic Acquirers: Mid-cycle technology positioning favors specialized antibacterial developers with QIDP-extended exclusivity rather than diversified pharmaceutical conglomerates facing generic erosion headwinds. Long-term viability across the analysis window rests on resistance surveillance data ownership and diagnostic-therapeutic pairing capabilities. The signal to watch is CDC Emerging Infections Program macrolide resistance threshold breaches that trigger formulary turnover toward novel therapeutic classes.
| Strategic Initiative | Industry Significance |
|---|---|
| Diagnostic-Therapeutic Partnership | Integration with Cepheid/BioFire platforms enables pathogen-directed therapy selection and formulary premium capture. |
| Pediatric Formulation Development | EMA priority medicines scheme support unlocks regulatory acceleration for age-appropriate pleuromutilin dosing. |
| Outpatient Observation Channel Expansion | Ambulatory surgical center overnight infusion capabilities create new revenue pools beyond traditional hospital admission. |
| Antimicrobial Stewardship Program Integration | Partnerships with IDN pharmacy committees embed products into resistance-guided prescribing protocols. |
| QIDP Designation Pursuit | FDA priority review and extended exclusivity alter competitive duration calculations for development-stage assets. |
Study Parameters
Cross-validation between primary interviews with infectious disease physicians and formulary directors anchors the qualitative findings, with secondary triangulation through FDA QIDP designation databases and CDC Emerging Infections Program resistance surveillance reports. The analysis draws from structured conversations with hospital procurement managers, payer access specialists, and antimicrobial stewardship program leads, combined with bottom-up and top-down reconciliation across clinical trial registries, SEC pharmaceutical filings, and integrated delivery network pharmacy committee protocols.
Sensitivity analysis across patient population, administration route, and regional regulatory cluster dimensions shapes the analytical framework over the projection horizon. CAGRs derive from segmented volume-demand modeling incorporating aging demographic projections, resistance surveillance trend extrapolation, and formulary turnover velocity assumptions. Industry-specific forecast inputs include QIDP designation pipeline progression and Medicare Hospital-Acquired Condition penalty impact on length-of-stay optimization incentives.
Underlying assumptions cover stable FDA QIDP framework continuity and CDC resistance surveillance network expansion, with deviation risk concentrated in Medicare reimbursement compression acceleration and generic macrolide pricing collapse velocity. Practitioners should keep alternative scenarios live as antimicrobial stewardship program mandate scope and diagnostic-therapeutic pairing adoption curves evolve.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Specialty Medicine
Eosinophilia Therapeutics Market
Specialty Medicine
Genital Warts (Condyloma Acuminatum) Market
Specialty Medicine
Glioma Therapeutics Market
Specialty Medicine
Barotrauma Market
Specialty Medicine
Breakthrough Therapy Designation Market
Specialty Medicine
Sporothrix Schenckii Infection Treatment Market
Specialty Medicine
Metabolic Disorders Therapeutics Market
Specialty Medicine
Open Angle Glaucoma Market
Specialty Medicine
Grand Mal Seizure Market
Specialty Medicine
Global Chondrosarcoma Market
Specialty Medicine
Global Occupational Medicines Market
Specialty Medicine
Tularemia Therapeutics Market
Specialty Medicine
Axillary Hyperhidrosis Treatment Market
Specialty Medicine
Hidradenitis Suppurativa (HS) Treatment Market
Specialty Medicine
Systemic Lupus Erythematosus (SLE) Market
Specialty Medicine
Hereditary Angioedema Market