
 Italy Bariatric Surgery Market | 2026-2036
Italy Bariatric Surgery Market Size, Share, and Industry Trends Forecast 2026-2036
Italy Bariatric Surgery Market Foresight
The capital-intensity divergence between robotic-capable systems and standard laparoscopic setups is collapsing as mid-tier surgical centers acquire da Vinci-compatible platforms. Medtronic Plc leverages its integrated energy device portfolio to sustain service contracts across northern Italy's hospital networks. B. Braun Melsungen AG anchors its position through specialized suturing and stapling lines designed for bariatric anatomy. Olympus Corporation competes by extending its endoscopic visualization systems into revision procedures where tissue planes prove challenging.
Bariatric surgery encompasses metabolic and gastrointestinal operations that reduce stomach volume or alter nutrient absorption to treat morbid obesity and related comorbidities, typically requiring pneumoperitoneum insufflation at 12-15 mmHg and ports ranging 5-12 mm in diameter. Sleeve gastrectomy dominates procedure volumes due to its relative technical simplicity and lower complication profile compared to gastric bypass, though the latter retains higher reimbursement rates per case. Robotic surgery represents the fastest-growing technology segment as Italian surgeons seek enhanced dexterity in super-obese patients with thickened abdominal walls, while endoscopic techniques attract investment for outpatient-eligible revisions.
Italy's Ministry of Health sets national essential levels of care (LEA) that determine regional reimbursement for bariatric procedures, with AIFA regulating device market access and CE-marking requirements under the EU MDR transition. The National Institute of Health (Istituto Superiore di Sanità) publishes clinical guidelines that shape hospital credentialing and volume thresholds for surgical teams. Stakeholders must monitor how Italy's regional health agencies (Aziende Sanitarie Locali) allocate funds between centralized hub hospitals and distributed surgical centers as obesity prevalence strains existing capacity.
Market Dynamics
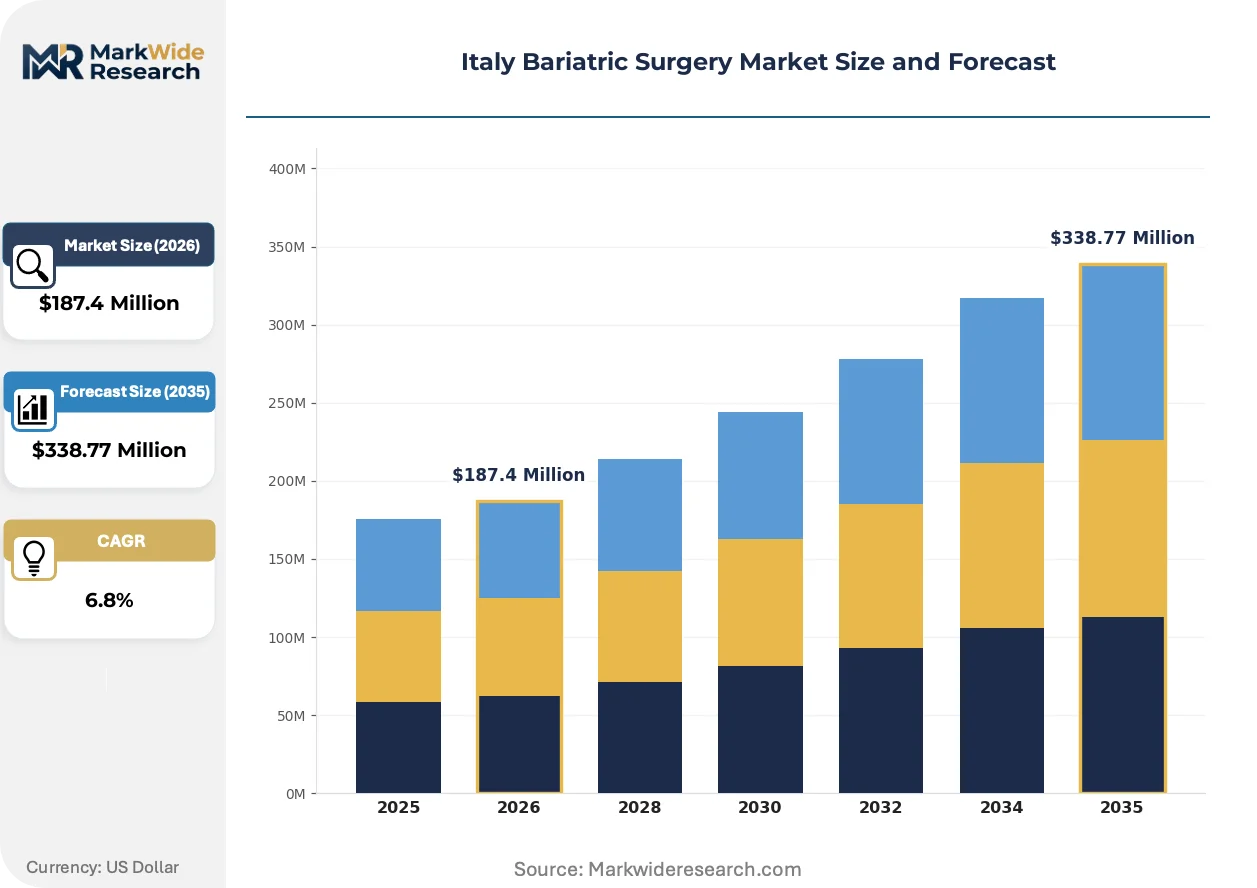
Italy's bariatric surgery market pivots on the Ministry of Health's expanding LEA coverage for metabolic procedures, which is redistributing procedure volumes from private clinics toward public hospital networks with robotic capability.
Growth Catalysts
- AIFA Reimbursement Expansion:The Italian Medicines Agency's broadened criteria for metabolic surgery now covers BMI thresholds down to 35 with comorbidities, pulling eligible patients into surgical pathways previously restricted to pharmaceutical intervention.
- Robotic Platform Diffusion:da Vinci-compatible installations at mid-tier surgical centers in Emilia-Romagna and Veneto are collapsing the historical concentration of complex procedures within Milan's IRCCS networks.
- Lombardy Referral Consolidation:Milan's Policlinico and San Raffaele hospitals anchor northern Italy's patient funnel, generating volume thresholds that sustain specialized bariatric nursing teams and dedicated ICU protocols.
Market Restraints
- EU MDR Compliance Burden:The Medical Device Regulation's recertification timelines for stapling and energy devices have extended market access delays by 12-18 months for non-legacy manufacturers.
- Single-Source Robotic Dependency:Intuitive Surgical's da Vinci ecosystem dominates service contracts across Italian public hospitals, limiting price negotiation leverage for procurement officers.
- Anesthesiologist Scarcity:Specialized bariatric anesthesia training programs produce fewer than 40 certified practitioners annually, capping surgical team expansion regardless of physical OR capacity.
Strategic Opportunities
- Endoscopic Revision Surgeries:Transoral outlet reduction and gastric plication techniques are creating outpatient-eligible alternatives to reoperative laparoscopy, opening ambulatory surgery centers in Tuscany and Lazio.
- Regional Hub Redistribution:Campania and Sicily's Aziende Sanitarie Locali are consolidating bariatric services into single high-volume centers, replicating Lombardy's referral density in underserved southern regions.
- Digital Prehabilitation Pathways:Telemedicine-enabled weight loss and psychological screening protocols are compressing preoperative timelines and reducing cancellation rates for publicly funded procedures.
Industry Challenges
- Surgeon Credentialing Bottlenecks:The Istituto Superiore di Sanità's volume thresholds for metabolic surgery certification require 50 supervised procedures, constraining team expansion at smaller Azienda Ospedaliera networks.
- Legacy Equipment Integration:Public hospitals in Puglia and Calabria face OR retrofit costs for robotic docking systems, delaying platform adoption despite central funding allocations.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Italy Bariatric Surgery Market |
| Market Size in 2026 | $187.4 Million |
| Market Size in 2035 | $338.77 Million |
| CAGR (2026 – 2036) | 6.8% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Procedure Type: Gastric Bypass, Sleeve Gastrectomy, Adjustable Gastric Band, Biliopancreatic Diversion End User: Hospitals, Surgical Centers, Clinics, Insurance Providers Age Group: Adults, Adolescents, Seniors, Middle-aged Technology: Laparoscopic Surgery, Robotic Surgery, Endoscopic Techniques, Traditional Surgery |
| Companies Covered | Medtronic Plc, Olympus Corporation, B. Braun Melsungen AG, ConMed Corporation, Allurion Technologies, GEM SRL, Spatz Medical, Apollo Endosurgery Inc., Johnson & Johnson, Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Italy Bariatric Surgery Market Shifts & Advancements
Technology convergence between endoscopic platforms and minimally invasive surgery is compressing the boundary between primary and revision procedures, while reimbursement mechanics favor outcomes-based hospital funding.
Single-anastomosis duodeno-ileal bypass with sleeve gastrectomy (SADI-S) is supplanting traditional Roux-en-Y gastric bypass in high-volume Italian centers. Policlinico Gemelli and IRCCS Humanitas surgeons report adoption curves matching sleeve gastrectomy's 2015 trajectory. The technique is supplanting two-anastomosis procedures by reducing operative time and internal hernia risk in super-obese patients.
Italy's Ministry of Health revised LEA criteria now mandate multidisciplinary obesity management teams including endocrinologists, dietitians, and psychologists prior to surgical authorization. Hospital networks must document 12-month preoperative pathways to secure full reimbursement. Southern regions lag in team assembly, creating compliance gaps that centralized hub models in Campania are closing through telemedicine integration.
Patients are consolidating surgeon selection around publicly reported outcome metrics. The National Outcomes Evaluation Program (PNE) publishes 30-day complication rates by hospital, redirecting elective cases toward IRCCS networks with sub-3% leak rates. Private clinics in Lombardy and Veneto respond by publishing audited SAGB (Swedish Adjustable Gastric Banding) revision statistics, competing on transparency where public data remains sparse.
Italy Bariatric Surgery Market Segmentation
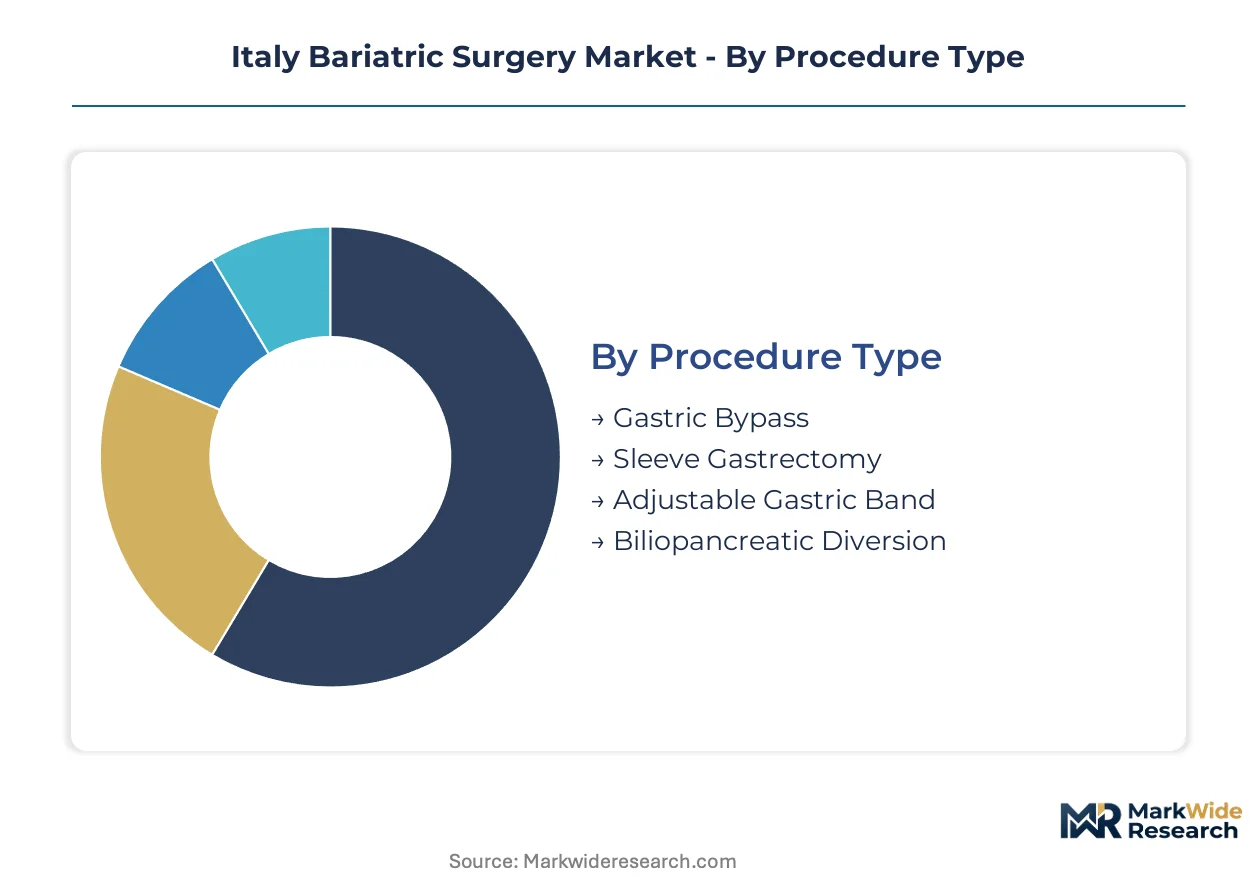
Italy's bariatric surgery market segments along four distinct axes that shape procurement patterns and reimbursement flows. Procedure type determines technical complexity and tariff levels, while technology adoption splits between capital-intensive robotic platforms and standardized laparoscopic workflows.
Procedure Type:
Gastric bypass and sleeve gastrectomy dominate Lombardy's IRCCS networks, while adjustable gastric banding concentrates in private Veneto clinics serving cross-border patients from Switzerland and Austria.
- Sleeve Gastrectomy:Resects approximately 80% of the greater curvature to create a tubular gastric remnant, preserving pyloric function and avoiding intestinal rerouting. Milan's Policlinico and San Raffaele hospitals anchor national volumes, driven by AIFA reimbursement parity with gastric bypass and shorter operative times that maximize throughput in constrained OR schedules.
- Gastric Bypass:Constructs a 15-30ml gastric pouch with Roux-en-Y gastrojejunostomy, delivering superior long-term weight loss and diabetes remission. IRCCS Humanitas and Policlinico Gemelli concentrate complex cases, particularly for super-obese patients with BMI exceeding 50 where metabolic outcomes justify higher complication risks.
- Adjustable Gastric Band:Laparoscopic placement of a silicone prosthesis with subcutaneous port access for saline adjustment. Swiss and Austrian patients seeking reversible, low-morbidity options drive demand at private Bergamo and Verona facilities.
- Biliopancreatic Diversion:Combines distal gastrectomy with long-limb intestinal bypass for malabsorptive effect. Selected Italian centers reserve this for revisional cases after sleeve gastrectomy failure, constrained by protein-calorie malnutrition monitoring requirements.
Sleeve gastrectomy commands the established base. The steepest expansion runs through gastric bypass as diabetes remission data hardens reimbursement justification.
End User:
Public hospital networks absorb the majority of AIFA-reimbursed volumes, while surgical centers and private clinics capture self-pay and supplemental insurance cases from affluent northern regions.
- Hospitals:Azienda Ospedaliera networks in Lombardy, Emilia-Romagna, and Veneto perform complex metabolic surgery under LEA coverage, with IRCCS-designated institutions required to maintain multidisciplinary teams and publish PNE outcome data.
- Surgical Centers:Independent ambulatory facilities in Tuscany and Lazio specialize in endoscopic revisions and band adjustments, operating outside essential care levels with faster scheduling for privately insured patients.
- Clinics:Private bariatric practices in Milan and Rome concentrate on preoperative counseling and long-term follow-up, often partnering with hospital networks for the surgical episode itself.
- Insurance Providers:Supplemental health insurers in northern Italy negotiate bundled payments with high-volume centers, covering robotic upgrades and single-room accommodations excluded from public tariffs.
Hospitals retain volume dominance. Surgical centers are gaining share fastest through outpatient-eligible revision procedures.
Age Group:
Middle-aged adults generate the bulk of surgical volumes, though adolescent pathways are expanding under revised Ministry of Health criteria for early metabolic intervention.
- Adults:Patients aged 18-64 with BMI thresholds of 35-40 and comorbidities constitute the standard eligible population, with Campania and Sicily now building hub-and-spoke referral models to capture this demand.
- Middle-aged:The 45-64 cohort presents the highest surgical volumes, combining established obesity-related disease burden with sufficient residual life expectancy to justify invasive intervention.
- Adolescents:Patients aged 13-17 with severe obesity and failed lifestyle intervention now qualify under expanded LEA criteria, though few Italian centers maintain pediatric-metabolic surgery certification.
- Seniors:Patients over 65 face selective referral due to anesthesiologist scarcity and frailty assessment requirements, concentrating in Milan's academic hospitals with dedicated geriatric bariatric protocols.
Middle-aged patients anchor current throughput. Adolescent pathways are expanding most quickly as early-intervention evidence accumulates.
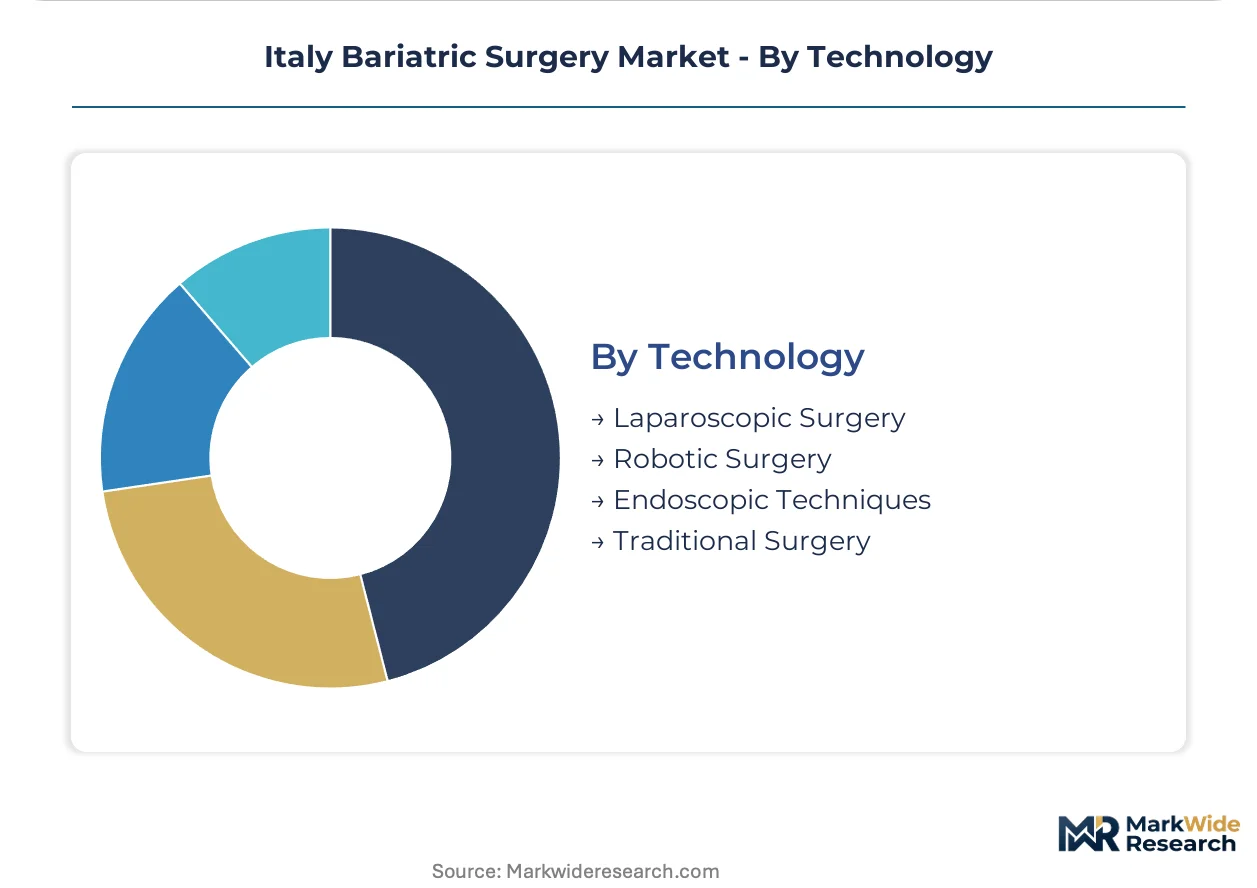
Technology:
Robotic platforms diffuse from Milan's flagship institutions into mid-tier Emilia-Romagna centers, while endoscopic techniques create ambulatory alternatives at Tuscan specialty clinics.
- Laparoscopic Surgery:Standard 5-port technique with 30-degree camera and linear stapler deployment remains the workhorse across public hospital networks, constrained by physical dexterity limits in super-obese patients with thickened abdominal walls.
- Robotic Surgery:da Vinci-compatible systems enable wristed instrumentation and 3D visualization, with installations spreading from IRCCS Humanitas to Azienda Ospedaliera networks in Bologna and Padua seeking competitive differentiation.
- Endoscopic Techniques:Transoral outlet reduction and gastric plication enable outpatient revision management, attracting investment from ambulatory surgery centers in Florence and Pisa.
- Traditional Surgery:Open approaches persist only for revisional cases with extensive adhesions or failed prior laparoscopy, concentrated in high-volume centers with specialized ICU support.
Laparoscopic surgery maintains installed-base dominance. Robotic platforms are climbing the fastest as Intuitive Surgical expands service coverage into secondary cities.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Demand elasticity varies sharply across Italian regions, with Lombardy's affluent patient base showing low price sensitivity for robotic upgrades while southern regions depend entirely on public reimbursement rates.
Lombardy
Milan's Policlinico and IRCCS Humanitas generate the highest surgical volumes nationally, driven by dense referral networks and established multidisciplinary teams. AIFA's LEA reimbursement protocols flow most efficiently through Lombardy's centralized procurement systems. The concentration of da Vinci installations at San Raffaele and Gemelli creates a technology hub that attracts complex super-obese cases from neighboring Switzerland.
Veneto
Private clinics in Verona and Bergamo capture cross-border demand from Austrian and Swiss patients seeking adjustable gastric banding. The regional health agency Azienda Zero negotiates bundled payments with high-volume centers, compressing margins for standalone practitioners. Padua's university hospital anchors public-sector volumes while independent ambulatory facilities specialize in band adjustments and revisions.
Emilia-Romagna
Bologna's Azienda Ospedaliera networks are acquiring mid-tier robotic platforms, collapsing the historical technology gap with Milan. The Istituto Superiore di Sanità's volume thresholds for metabolic surgery certification constrain team expansion at smaller facilities. Rimini and Modena are consolidating bariatric services into single high-volume centers to meet credentialing requirements.
Campania
Naples' Federico II University Hospital anchors southern Italy's emerging hub-and-spoke model, replicating Lombardy's referral density in an underserved region. The Ministry of Health's expanded LEA criteria for metabolic surgery are pulling eligible patients into surgical pathways previously restricted to pharmaceutical intervention. Regional funding allocations prioritize OR retrofit costs for robotic docking systems over new construction.
Tuscany
Florence and Pisa are developing ambulatory surgery centers specializing in endoscopic revisions, operating outside essential care levels with faster scheduling. The National Outcomes Evaluation Program's publication of 30-day complication rates redirects elective cases toward IRCCS networks, pressuring private facilities to publish audited statistics. Telemedicine-enabled prehabilitation pathways are compressing preoperative timelines for publicly funded procedures.
Italy Bariatric Surgery Market Competitive Landscape
Technology leadership and cost leadership are held by different player archetypes, with robotic platform vendors commanding premium service contracts while mid-tier surgical centers compete on throughput efficiency. The market structure concentrates around three strategic groupings: integrated medical device conglomerates with broad energy and stapling portfolios, specialized endoscopic visualization suppliers, and emerging endoluminal technology developers. Competitive moves center on service contract lock-in for robotic systems and geographic expansion of ambulatory revision capabilities.
Among the integrated device manufacturers, Medtronic Plc and Olympus Corporation exemplify contrasting archetypes—one leveraging integrated energy portfolios to sustain hospital network relationships, the other extending visualization systems into challenging revision procedures. B. Braun Melsungen AG occupies a position between these poles, anchoring its presence through specialized suturing and stapling lines designed for bariatric anatomy. These three represent the dominant competitive positions shaping procurement patterns across Italy's public hospital networks.
| Leading Market Players |
|---|
| Medtronic Plc |
| Olympus Corporation |
| B. Braun Melsungen AG |
| ConMed Corporation |
| Allurion Technologies |
| GEM SRL |
| Spatz Medical |
| Apollo Endosurgery Inc. |
| Johnson & Johnson |
| Others |
Supply & Pricing Matrix
Capital-utilization thresholds at Milan's IRCCS networks compress per-procedure costs for robotic platforms, concentrating supply negotiation leverage among high-volume centers and establishing price floors that mid-tier Emilia-Romagna facilities struggle to match under AIFA reimbursement protocols.
Pricing Analysis
After-sales service contracts for da Vinci-compatible systems capture lifetime value exceeding initial hardware placement, with Intuitive Surgical's maintenance agreements anchoring hospital procurement decisions. Three-tier pricing structure across premium robotic, standard laparoscopic, and economy open-procedure levels stratifies by technology intensity and certification grade. Cost compression in mid-tier laparoscopic device bundles is intensifying because EU MDR recertification timelines have extended supplier qualification periods. Public hospital procurement committees show highest price sensitivity, while supplemental insurers in Lombardy absorb robotic upgrade premiums with minimal friction.
Supply Chain Analysis
Just-in-time inventory preferences dominate for disposable stapler cartridges and energy device consumables, though strategic stockpiling of robotic instrument arms buffers against Intuitive Surgical's single-source service dependencies. Manufacturing concentration in Germany, Switzerland, and the United States feeds Italy's device import requirements for precision stapling mechanisms and visualization optics. Supply chain vulnerability rests on CE-marking bottlenecks under EU MDR transition timelines that delay new product introductions. Distribution runs through centralized Aziende Sanitarie Locali procurement hubs in northern regions, with southern territories dependent on fragmented regional health agency negotiations.
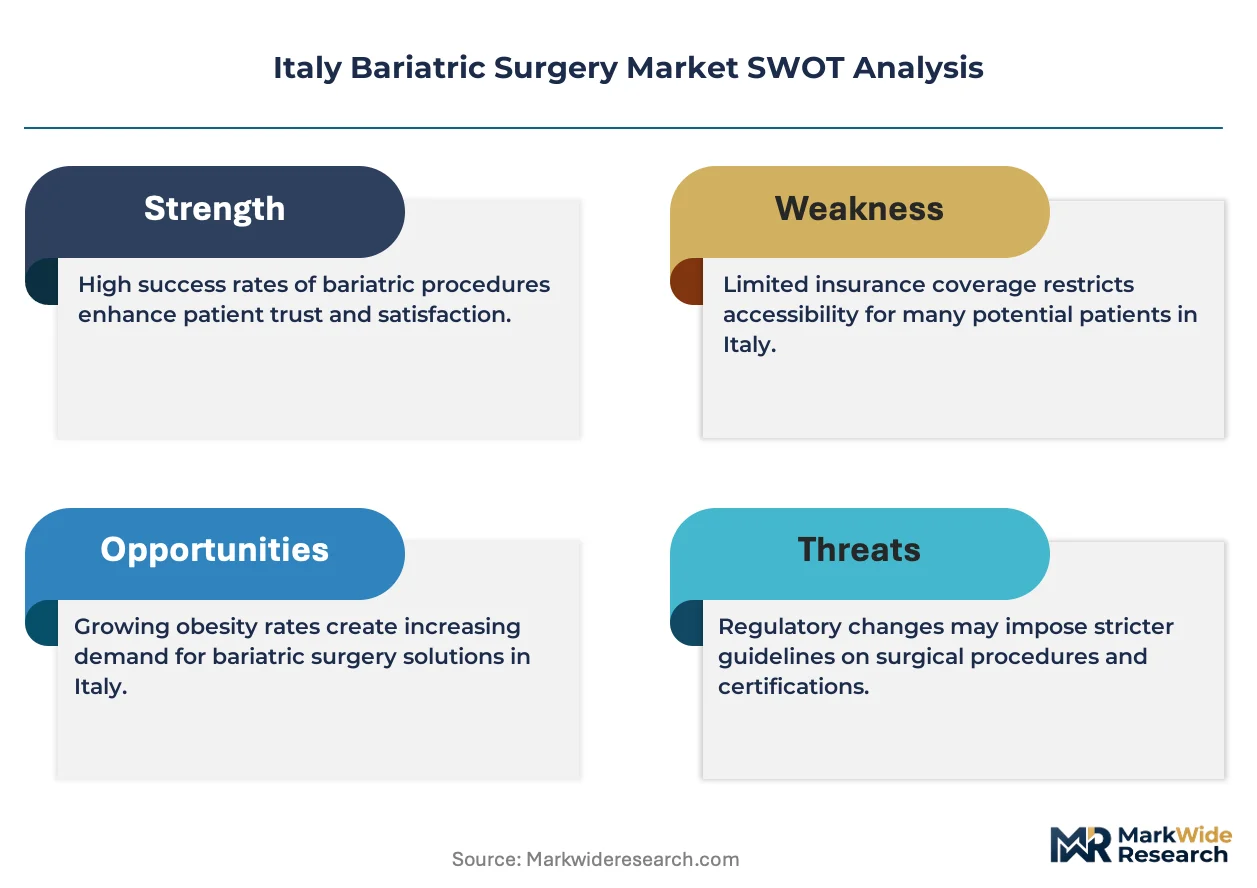
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Italy's bariatric surgery market operates as a defensive-moat structure where regulatory entrenchment through AIFA certification requirements and Istituto Superiore di Sanità volume thresholds creates durable barriers against rapid competitive displacement.
For Market Incumbents: Shield market position by deepening service contract penetration across Emilia-Romagna's emerging robotic installations before competitors establish maintenance relationships. Prioritize backward integration into specialized suturing consumables to capture margin compression from EU MDR compliance costs. The anesthesiologist scarcity caps surgical team expansion regardless of OR capacity investment, making human capital retention the critical defensive lever.
For New Entrants and Emerging Players: Anchor in Campania's hub-and-spoke consolidation, where Federico II University Hospital's emerging referral density lacks established device vendor relationships. Target endoscopic revision procedures in Tuscany's ambulatory surgery centers, where outpatient eligibility creates white-space outside IRCCS network dominance. Pursue telemedicine-enabled prehabilitation partnerships with southern Aziende Sanitarie Locali to compress preoperative timelines and differentiate on scheduling speed.
For Investors and Strategic Acquirers: Recurring-revenue conversion is highest among robotic platform service providers with locked-in hospital contracts, offering visibility through AIFA reimbursement stability. Long-term viability favors integrated device manufacturers with diversified energy and stapling portfolios capable of withstanding single-technology substitution. Monitor AIFA's LEA expansion criteria for metabolic surgery as the inflection signal—broader BMI thresholds would accelerate volume migration from pharmaceutical to surgical pathways.
| Strategic Initiative | Industry Significance |
|---|---|
| CE Marking Pathway | EU MDR recertification timelines determine 12-18 month market access delays for stapling devices. |
| Hospital System Partnership | IRCCS Humanitas and Policlinico Gemelli volume thresholds sustain specialized bariatric nursing teams. |
| Reimbursement Strategy | AIFA's expanded LEA criteria for BMI 35 with comorbidities pulls patients from pharmaceutical pathways. |
| Software Companion Development | Telemedicine-enabled prehabilitation protocols compress preoperative timelines for publicly funded procedures. |
| Backward Integration | In-house production of energy devices captures margin from service contract bundling at mid-tier centers. |
Research Methodology
Desk research of AIFA reimbursement bulletins, Istituto Superiore di Sanità clinical guidelines, and PNE outcome databases preceded structured interviews with bariatric surgeons, hospital procurement managers, biomedical engineers, and GPO contracts specialists. Secondary validation drew from EU MDR transition filings, regional health agency budget allocations, and Intuitive Surgical service contract disclosures. Bottom-up procedure volume modeling triangulated against top-down AIFA expenditure tracking.
Variance decomposition across technology adoption curves, regional reimbursement efficiency, and surgeon credentialing bottlenecks shaped the analytical framework over the projection horizon. Segmentation dimensions modeled include procedure type, technology platform, end-user facility class, and regional health agency cluster. CAGRs derived from logistic diffusion curves for robotic platform penetration and linear extrapolation of AIFA budget trajectories. Procedure volume forecasts incorporated anesthesiologist training pipeline constraints and EU MDR recertification lag effects.
Material uncertainties — AIFA reimbursement protocol revisions, EU MDR enforcement intensity shifts, and anesthesiologist workforce expansion rates — sit outside the modeled envelope. Forecasts reflect documented assumptions regarding LEA coverage stability and robotic platform service contract pricing. Revision becomes warranted when AIFA metabolic surgery eligibility criteria cross thresholds that trigger volume step-changes in public hospital procurement.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Bariatric Surgery
Bariatric Medical Chairs Market
Bariatric Surgery
India Bariatric Surgery Devices Market
Bariatric Surgery
India Bariatric Surgery Market
Bariatric Surgery
Bariatric Walkers Market
Bariatric Surgery
Bariatric Patient Room Market
Bariatric Surgery
United States Bariatric Surgery Market
Bariatric Surgery
North America Bariatric Surgery Devices Market
Bariatric Surgery
Global Bariatric Surgical Devices Market
Bariatric Surgery
Germany Bariatric Surgery Market
Bariatric Surgery
Brazil Bariatric Surgery Market
Bariatric Surgery
Global Bariatric Walking Aids Market
Bariatric Surgery
South Korea Bariatric Surgery Market
Bariatric Surgery
France Bariatric Surgery Market
Bariatric Surgery
US Medical Weight Loss Clinics Market
Bariatric Surgery
Japan Bariatric Surgery Market
Bariatric Surgery
Canada Bariatric Surgery Market