
 US Medical Weight Loss Clinics Market | 2026-2036
US Medical Weight Loss Clinics Market Size, Share, and Industry Trends Forecast 2026-2036
US Medical Weight Loss Clinics Market Insights
Clinic-to-patient access is narrowing as telehealth platforms and retail health partnerships redraw how Americans enter structured weight management programs. Rivas Weight Loss leverages physician-supervised protocols to dominate Texas markets. Cleveland Clinic anchors its national reputation through integrated bariatric and metabolic services. UCLA Health extends its reach via employer contracts across Southern California.
Medical weight loss clinics deliver physician-directed interventions combining pharmacotherapy, nutritional counseling, behavioral modification, and surgical options to reduce obesity-related morbidity. Treatment protocols typically incorporate body composition analysis, metabolic testing, and continuous monitoring to calibrate individualized care plans. Pharmaceutical services lead revenue generation as demand for GLP-1 therapies surges, while telehealth solutions represent the fastest-growing delivery channel by expanding rural and suburban access. Behavioral therapy segments command premium pricing due to specialized psychologist staffing requirements.
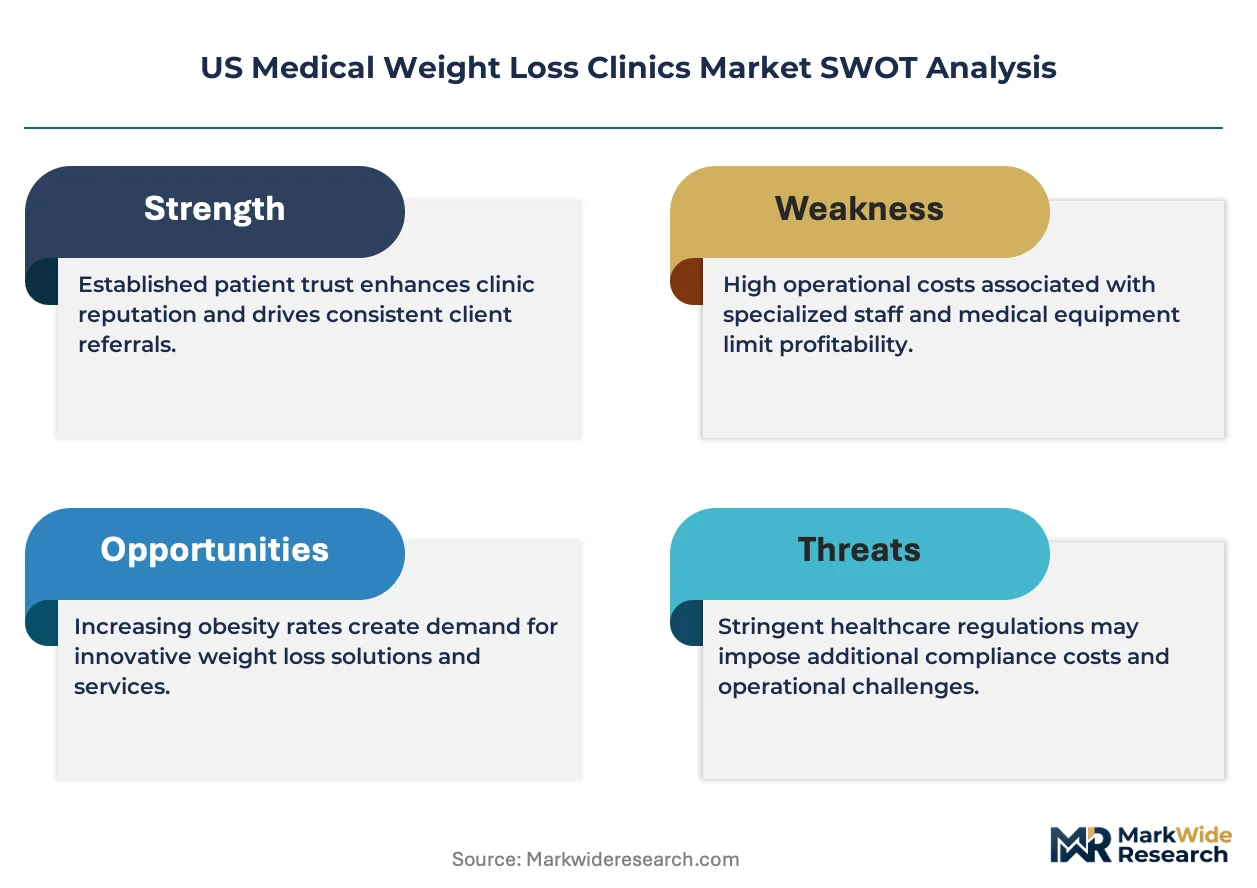
FDA oversight of anti-obesity medications and CMS reimbursement policies for intensive behavioral therapy directly determine service accessibility and clinic profitability across US markets. State medical boards and DEA scheduling requirements for controlled-substance appetite suppressants create additional compliance layers that shape operational scope. Stakeholders must monitor evolving insurance coverage determinations for pharmacological interventions to anticipate demand shifts and capacity planning needs.
Market Dynamics
GLP-1 receptor agonist FDA approvals are compressing treatment timelines and expanding clinic service lines beyond traditional surgical interventions. Pharmaceutical integration is now the dominant structural force reshaping competitive positioning and patient acquisition economics across metropolitan and suburban markets.
Growth Catalysts
- Employer Wellness Mandates:Large self-insured employers in Texas, California, and New York are directly contracting with clinic networks to reduce diabetes-related medical spend. These contracts bypass traditional payer intermediaries.
- Telehealth Infrastructure:Remote patient monitoring platforms enable continuous metabolic tracking outside brick-and-mortar locations. Rural patient access is expanding through asynchronous provider consultations and home-delivered pharmaceuticals.
- CMS Intensive Behavioral Therapy Reimbursement:Medicare coverage for physician-supervised weight management creates sustainable revenue streams for clinic operators serving patients aged 65 and older.
Market Restraints
- DEA Controlled-Substance Scheduling:Phentermine and other Schedule IV appetite suppressants require in-person prescriber visits and 30-day dispensing limits. These restrictions constrain operational scale and increase compliance overhead.
- GLP-1 Supply Concentration:Novo Nordisk and Eli Lilly manufacture nearly all FDA-approved semaglutide and tirzepatide formulations. Manufacturing bottlenecks create patient waitlists and revenue volatility for dependent clinics.
- Specialist Workforce Scarcity:Board-certified obesity medicine physicians number under 4,000 nationally. This concentration limits clinic expansion into secondary metropolitan markets.
Strategic Opportunities
- Medicaid Expansion States:States that expanded Medicaid under the ACA present untapped demand for covered medical weight management. Clinic operators can secure state contracts before competitive saturation.
- Integrated Behavioral Health:Combining licensed psychology services with pharmacotherapy addresses comorbid eating disorders. Payers increasingly bundle these services under value-based arrangements.
- Retail Health Partnerships:CVS Health and Walgreens are embedding clinic modules within pharmacy footprints. Co-location reduces patient acquisition costs and enables same-day prescription fulfillment.
Industry Challenges
- EHR Interoperability Friction:Clinic-specific platforms rarely integrate with hospital system records. Data silos complicate care coordination for bariatric surgery referrals.
- Prior Authorization Burden:GLP-1 therapies require extensive documentation of BMI thresholds and comorbidities. Administrative staffing costs consume 15-20% of pharmaceutical service revenue.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | US Medical Weight Loss Clinics Market |
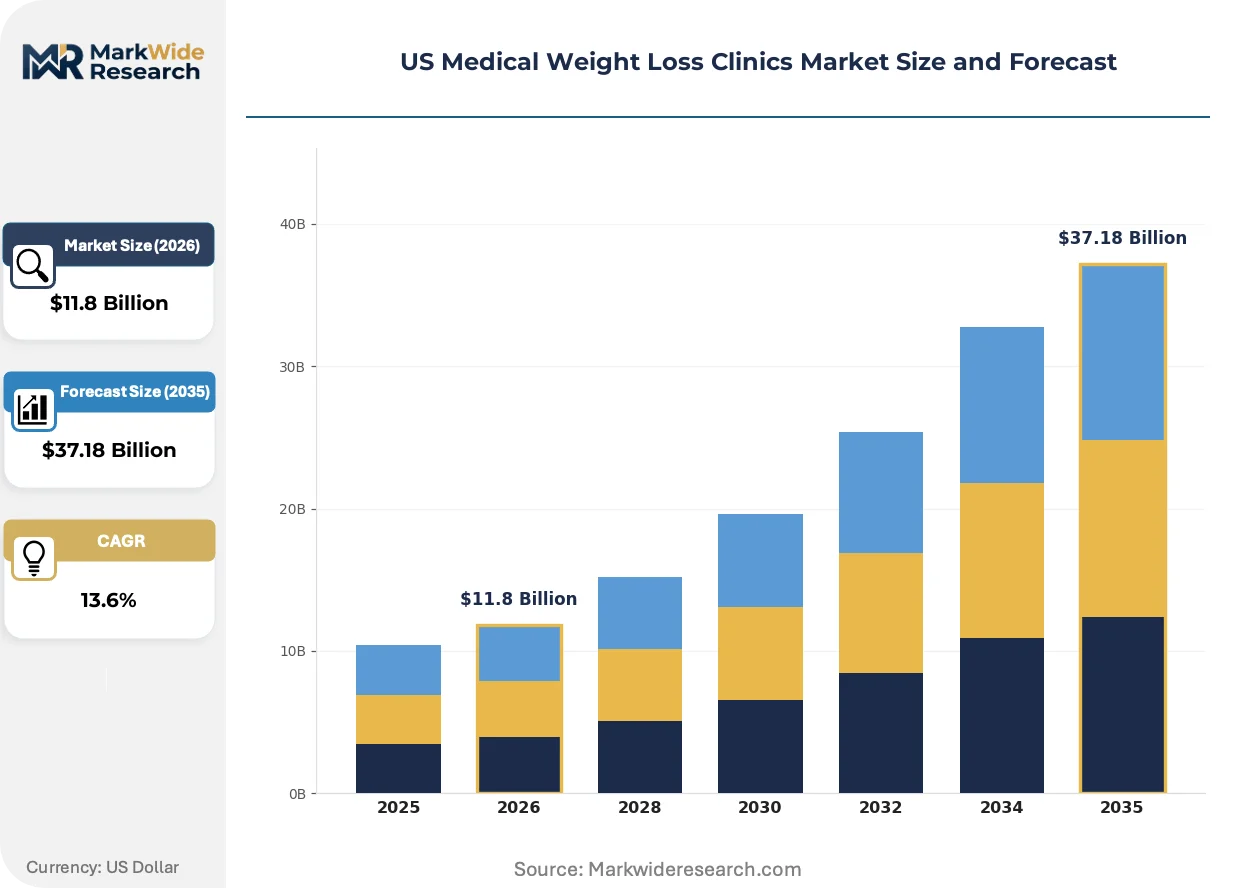
| Market Size in 2026 | $11.8 Billion |
| Market Size in 2035 | $37.18 Billion |
| CAGR (2026 – 2036) | 13.6% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: Pharmaceutical, Nutritional Counseling, Behavioral Therapy, Surgical Intervention End User: Adults, Seniors, Adolescents, Low-Income Individuals Technology: Telehealth Solutions, Monitoring Devices, Mobile Applications, Wearable Fitness Trackers Price Tier: Premium, Mid-Range, Budget, Discounted Packages |
| Companies Covered | Rivas Weight Loss, Stanford Health Care, Cleveland Clinic, Yale Center for Weight Management, UCLA Health, Medi-Weightloss, NYU Langone Hospitals, Cedars-Sinai, Medical Weight Loss Clinic, Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
US Medical Weight Loss Clinics Market Trends and Innovations
Continuous glucose monitoring and body composition analytics are migrating from diagnostic tools to real-time therapeutic adjustment mechanisms. This instrumentation shift is compressing the feedback loop between patient behavior and clinical intervention.
Dual-energy X-ray absorptiometry and bioelectrical impedance analysis are migrating from periodic assessments to weekly monitoring protocols. Employer-sponsored clinics in Houston and Los Angeles are adopting these technologies to demonstrate measurable outcomes to benefits administrators. The migration from episodic to continuous measurement is enabling outcome-based contract structures that tie clinic reimbursement to sustained patient weight reduction.
FDA's accelerated approval pathway for anti-obesity medications is shortening development timelines for combination therapies. The agency's 2023 guidance on cardiovascular outcome trials for obesity drugs is reshaping pharmaceutical service line planning. Clinics serving patients with established heart disease are now prioritizing therapies with demonstrated MACE reduction over purely weight-focused interventions.
Patients are demanding unbundled service components rather than comprehensive program enrollment. Direct-to-consumer GLP-1 prescribing through telehealth platforms is fragmenting what were previously clinic-captured relationships. This disintermediation is most pronounced among commercially insured patients aged 30-45 in suburban Atlanta, Dallas, and Phoenix markets who prioritize convenience over integrated care coordination.
US Medical Weight Loss Clinics Market Segmentation
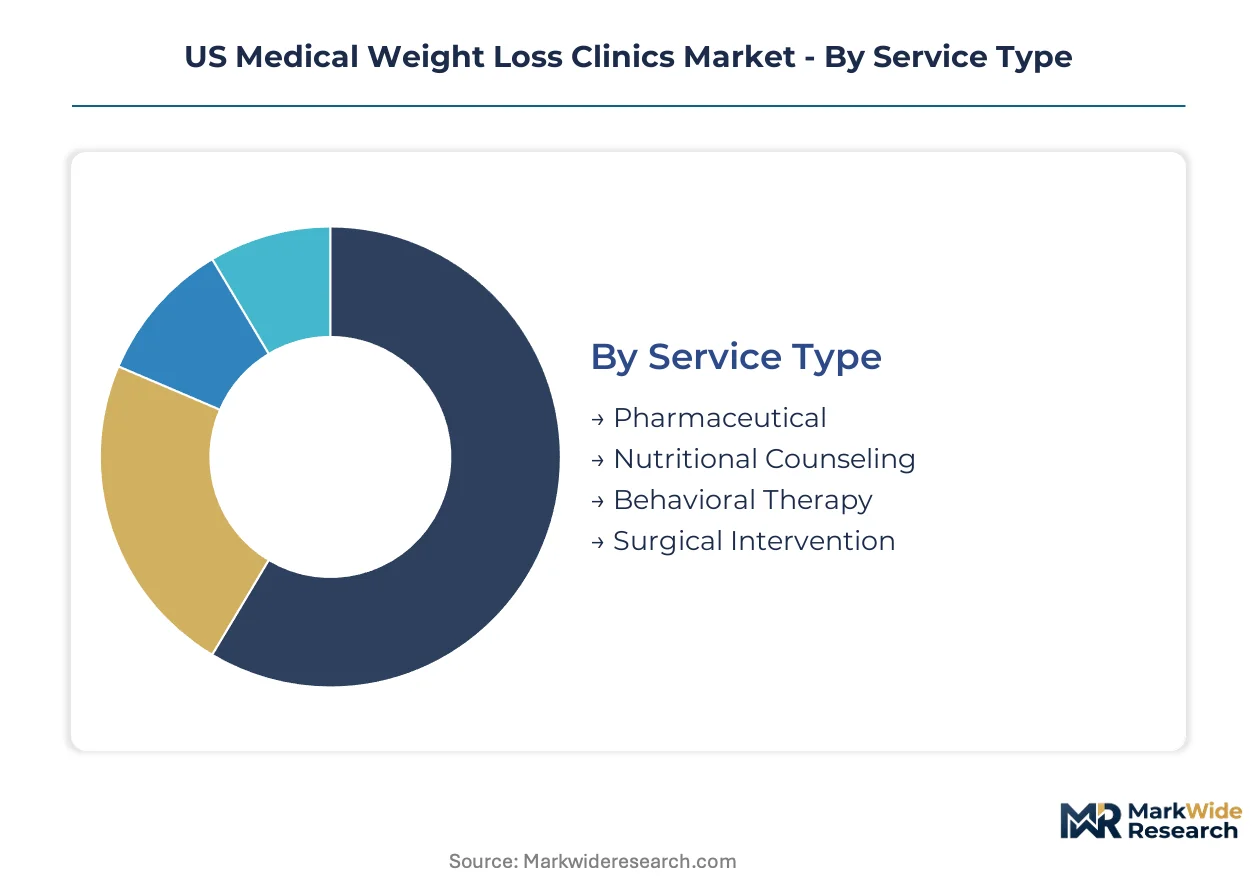
Service differentiation across US medical weight loss clinics determines patient acquisition economics and operational scalability. Segmentation reveals where pharmaceutical integration, behavioral health bundling, and technology-enabled delivery create sustainable margin structures versus commodity-priced competition.
Service Type:
Cost tier stratification separates high-touch physician services from standardized program offerings across clinic networks.
- Pharmaceutical:GLP-1 receptor agonist prescribing and medication management protocols dominate revenue composition. Texas and California metropolitan corridors concentrate demand as employer contracts prioritize pharmacotherapy outcomes over surgical alternatives.
- Nutritional Counseling:Registered dietitian-directed meal planning and metabolic optimization addresses patients with contraindications to anti-obesity medications. Medicare reimbursement for medical nutrition therapy sustains clinic viability in Florida and Arizona retirement communities.
- Behavioral Therapy:Licensed psychologist integration commands premium pricing through eating disorder comorbidity management.
- Surgical Intervention:Pre-operative evaluation and post-bariatric monitoring services anchor academic medical center offerings.
Pharmaceutical services command the established base. The steepest expansion runs through behavioral therapy bundling.
End User:
Application focus shifts clinic staffing models and marketing channels toward specific demographic risk profiles.
- Adults:Working-age patients aged 30-55 drive commercial insurance utilization and employer-sponsored program enrollment. Houston and Los Angeles corporate contracts target this segment for diabetes prevention ROI.
- Seniors:Medicare-eligible patients aged 65-plus require intensive behavioral therapy coverage and medication interaction management. CMS reimbursement policies directly determine clinic accessibility for this population.
- Adolescolescents:Pediatric obesity protocols demand specialized provider certification and family-based intervention models.
- Low-Income Individuals:Medicaid expansion state contracts create volume-based revenue streams with thinner margins.
Adult segments anchor current revenue. The steepest expansion trajectory runs through senior populations as Medicare coverage broadens.
Technology:
Volume concentration in remote delivery channels is redrawing capital deployment away from brick-and-mortar expansion.
- Telehealth Solutions:Asynchronous provider consultations and e-prescribing platforms extend clinic reach into rural Texas and Appalachian markets. DEA scheduling requirements for controlled substances constrain pure telehealth models for phentermine-based protocols.
- Monitoring Devices:Continuous glucose monitors and body composition analyzers enable real-time therapeutic adjustment. Employer-sponsored clinics in Atlanta and Dallas deploy these for outcome-based contract compliance.
- Mobile Applications:Patient engagement platforms with food logging and medication reminders support adherence tracking.
- Wearable Fitness Trackers:Integration with Apple Health and Fitbit ecosystems provides passive activity data streams.
Telehealth solutions command the established base. The steepest expansion runs through monitoring devices as continuous measurement becomes standard of care.
Price Tier:
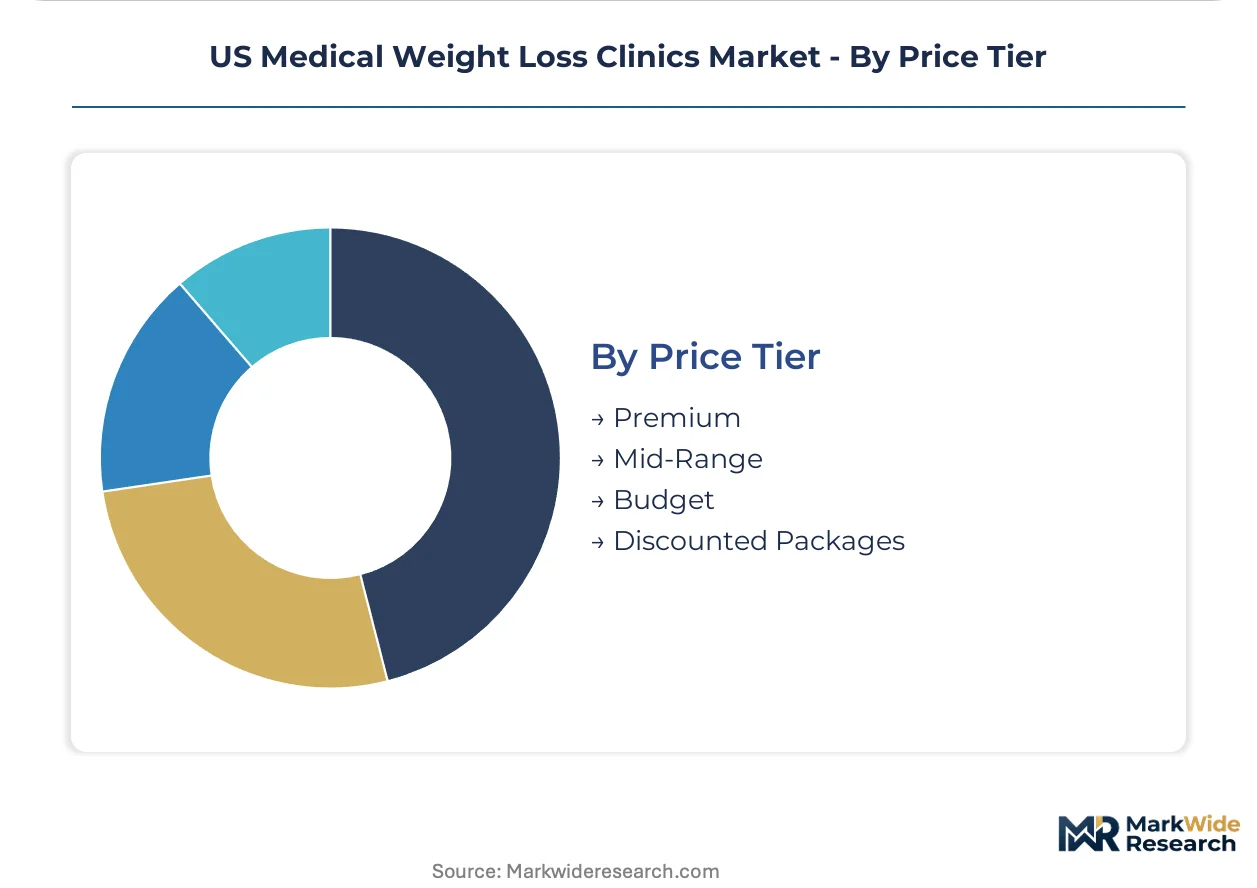
Customer type stratification separates cash-pay direct-to-consumer models from insurance-integrated service lines.
- Premium:Concierge protocols with board-certified obesity medicine physicians and unlimited access pricing target high-net-worth individuals in Manhattan, Miami, and San Francisco. Out-of-pocket spending exceeds $15,000 annually for comprehensive pharmacotherapy and behavioral health bundles.
- Mid-Range:Commercial insurance-compatible programs with defined visit limits and formulary restrictions serve suburban employed populations. Texas and California benefit administrators negotiate these tiers for self-insured employer contracts.
- Budget:Cash-pay phentermine clinics with minimal ancillary services compete on price in secondary metropolitan markets.
- Discounted Packages:Pre-paid multi-month commitments reduce per-visit costs for uninsured patients.
Mid-range tiers command the established base. The steepest expansion runs through premium concierge models as direct-pay patients prioritize access over insurance navigation.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Premium concierge clinics in Manhattan command annual fees exceeding $15,000, while budget phentermine operators in Houston suburbs compete below $200 monthly. This pricing-power asymmetry reflects divergent patient demographics, insurance penetration, and employer contract density across US metropolitan corridors.
Texas
Employer-sponsored wellness contracts in Houston and Dallas drive demand for GLP-1 integrated protocols. FDA oversight of semaglutide prescribing shapes clinic operational scope and pharmaceutical service line planning. Rivas Weight Loss anchors physician-supervised networks across the Houston metropolitan corridor.
California
Commercial insurance penetration and self-insured employer density in Los Angeles and San Francisco sustain mid-range pricing tiers. CMS reimbursement policies for intensive behavioral therapy determine clinic accessibility for Medicare-eligible populations in retirement communities. UCLA Health extends integrated metabolic services through employer contracts across Southern California.
New York
High-net-worth patient concentration in Manhattan sustains premium concierge models with unlimited access pricing. State medical board regulations for controlled-substance prescribing create compliance layers for phentermine-based protocols. NYU Langone Hospitals anchors academic medical center offerings in the New York metropolitan area.
Ohio
Medicaid expansion under the ACA creates volume-based opportunities for covered medical weight management in Cleveland and Columbus. DEA scheduling requirements for Schedule IV appetite suppressants constrain telehealth expansion and mandate in-person prescriber visits. Cleveland Clinic integrates bariatric and metabolic services to anchor regional reputation.
Florida
Medicare-eligible senior populations in Miami and Tampa drive demand for intensive behavioral therapy coverage. Reimbursement policies for medical nutrition therapy sustain registered dietitian staffing in retirement corridor clinics. Stanford Health Care extends brand recognition through telehealth-enabled consultation models reaching Florida patient populations.
US Medical Weight Loss Clinics Market Competitive Landscape
Academic medical centers and specialized clinic networks split the market into distinct competitive spheres. Academic institutions leverage integrated bariatric surgery capabilities and research reputations to anchor premium positioning. Specialized networks compete through employer contract density and pharmaceutical service line integration. Dominant competitive moves include geographic expansion through telehealth infrastructure and strategic partnerships with retail health platforms.
Within the academic medical center tier, Cleveland Clinic and UCLA Health exemplify integrated metabolic and bariatric service offerings. Among specialized clinic networks, Rivas Weight Loss occupies a position representing physician-supervised protocol dominance in Texas markets. These anchors illustrate the structural divide between research-anchored institutions and contract-driven specialized operators reshaping patient acquisition economics.
| Leading Market Players |
|---|
| Rivas Weight Loss |
| Stanford Health Care |
| Cleveland Clinic |
| Yale Center for Weight Management |
| UCLA Health |
| Medi-Weightloss |
| NYU Langone Hospitals |
| Cedars-Sinai |
| Medical Weight Loss Clinic |
| Others |
Pricing and Supply Chain Analysis
Houston's pharmaceutical distribution corridor anchors GLP-1 medication availability for Texas clinic networks, with Novo Nordisk and Eli Lilly manufacturing concentration translating directly into patient waitlist pricing power. Capacity bottlenecks at these Danish and US production facilities cascade into revenue volatility for dependent clinics, compressing margins when supply tightens and enabling premium capture when availability normalizes.
Pricing Analysis
The customization-premium spread separates concierge protocols exceeding fifteen thousand dollars annually from budget phentermine clinics operating below two hundred dollars monthly. Three-tier pricing structure across premium, standard, and economy levels reflects physician certification tier, with board-certified obesity medicine specialists commanding substantial access premiums. Cost compression in the budget tier is intensifying because DEA in-person visit requirements for Schedule IV controlled substances eliminate telehealth operational efficiencies. Uninsured patients in secondary metropolitan markets exhibit highest price sensitivity, while self-insured employer populations in Houston and Los Angeles prioritize outcome guarantees over per-visit costs.
Supply Chain Analysis
Novo Nordisk's Danish manufacturing and Eli Lilly's US production facilities hold dominant capacity for semaglutide and tirzepatide formulations. Active pharmaceutical ingredient sourcing draws from specialized peptide synthesis operations in China and India, with finished dose formulation concentrated in North American and European facilities. Single-source vulnerability pervades the GLP-1 therapeutic class, where manufacturing bottlenecks create patient waitlists extending months. Distribution runs through specialty pharmacy channels including CVS Health and Walgreens, with same-day fulfillment co-location emerging as a competitive differentiator for retail health partnerships.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Employer wellness spending cycles drive this market's recovery trajectory, with large self-insured contracts renewing on three-year benefits administration cycles that concentrate demand timing. FDA approval waves for combination anti-obesity therapies amplify these cyclical peaks by expanding reimbursable service lines.
For Market Incumbents: Entrench position through backward integration into continuous glucose monitoring device procurement, securing outcome-data advantages for employer contract renewals. Rivas Weight Loss and Cleveland Clinic demonstrate this through proprietary metabolic tracking platforms that demonstrate measurable ROI to benefits administrators. Defend against direct-to-consumer telehealth fragmentation by embedding licensed psychology services within pharmacotherapy bundles, creating switching costs that pure-play GLP-1 prescribers cannot replicate. For New Entrants and Emerging Players: Build out Medicaid expansion state presence before competitive saturation, targeting Ohio and Florida where ACA coverage expansion creates volume-based contract opportunities. Rural Texas and Appalachian markets present the most penetrable geography, with telehealth-enabled asynchronous consultations bypassing specialist physician scarcity constraints. Pursue retail health partnership models with CVS Health or Walgreens pharmacy footprints, reducing patient acquisition costs through co-located prescription fulfillment. For Investors and Strategic Acquirers: Carve-out targets emerge from academic medical center weight management divisions seeking operational focus, particularly those with underutilized bariatric surgery capacity and established employer contract relationships. Long-term viability hinges on outcome-based reimbursement migration, with sustainable returns accruing to platforms demonstrating sustained weight reduction rather than episodic pharmaceutical prescribing. Monitor GLP-1 supply normalization as the critical inflection signal, with manufacturing capacity expansion by Novo Nordisk and Eli Lilly determining whether clinic revenue volatility compresses or persists.| Strategic Initiative | Industry Significance |
|---|---|
| Employer Contract Direct Sourcing | Self-insured employers in Texas and California bypass traditional payer intermediaries, securing dedicated clinic capacity. |
| Retail Health Partnership | CVS Health and Walgreens co-location reduces patient acquisition costs and enables same-day GLP-1 prescription fulfillment. |
| Continuous Monitoring Integration | Body composition analytics and glucose monitoring compress feedback loops for outcome-based contract compliance. |
| Behavioral Health Bundling | Licensed psychologist integration addresses eating disorder comorbidities and creates switching costs against telehealth competitors. |
| Medicaid State Contracting | ACA expansion states present untapped demand before competitive saturation in Ohio and Florida corridors. |
Research Methodology
Initial hypotheses were tested against primary input from obesity medicine physicians, employer benefits administrators, specialty pharmacy procurement managers, and GLP-1 manufacturer market access leads and refined through secondary validation. FDA approval databases, CMS reimbursement policy filings, employer wellness program disclosures, and state Medicaid contract records anchored quantitative demand estimation. Bottom-up clinic capacity modeling and top-down pharmaceutical shipment analysis provided cross-verification of market sizing.
Demand-supply-balance framing structured the analytical approach across the analysis window, with patient volume projections calibrated against board-certified physician workforce constraints and GLP-1 manufacturing capacity disclosures. Segmentation dimensions modeled include service type stratification, end-user demographic profiles, technology-enabled delivery channels, and price tier positioning. CAGRs derived from historical enrollment trajectories and pharmaceutical uptake curves, incorporating employer contract renewal cycles and FDA approval timeline assumptions.
The forecast holds incumbent behavior within observed patterns; aggressive moves by direct-to-consumer telehealth platforms or retail health consolidators would shift outcomes substantially. Quarterly review of GLP-1 supply availability, employer contract renewal announcements, and state Medicaid coverage determinations is advised to detect inflection.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Bariatric Surgery
Global Bariatric Surgery Market
Bariatric Surgery
France Bariatric Surgery Market
Bariatric Surgery
Chile Bariatric Surgery Market
Bariatric Surgery
United States Bariatric Surgery Market
Bariatric Surgery
Bariatric Patient Room Market
Bariatric Surgery
China Bariatric Surgery Market
Bariatric Surgery
Bariatric Surgery Devices Market
Bariatric Surgery
Global Bariatric Walking Aids Market
Bariatric Surgery
South Africa Bariatric Surgery Market
Bariatric Surgery
Australia Bariatric Surgery Market
Bariatric Surgery
India Bariatric Surgery Market
Bariatric Surgery
India Bariatric Surgery Devices Market
Bariatric Surgery
North America Bariatric Surgery Devices Market
Bariatric Surgery
Canada Bariatric Surgery Market
Bariatric Surgery
UAE Bariatric Surgery Market
Bariatric Surgery
Brazil Bariatric Surgery Market