
 Aarskog Syndrome Treatment Market | 2026-2036
Aarskog Syndrome Treatment Market Size, Share, and Industry Trends Forecast 2026-2036
Aarskog Syndrome Treatment Market Outlook
The capital-intensity divergence between gene therapy platforms and conventional hormonal protocols is bifurcating competitive positioning in Aarskog syndrome care. Novartis AG leverages its cell and gene therapy infrastructure to anchor development of precision interventions for FGD1-related pathologies. BioMarin Pharmaceutical specializes in rare genetic disorder platforms and sustains R&D intensity through dedicated orphan disease programs. Pfizer Inc. competes via broader rare disease portfolios that extend manufacturing scale across multiple pediatric indications.
Aarskog syndrome treatment encompasses therapeutic interventions targeting FGD1 gene mutations that disrupt Rho GTPase signaling during fetal development, primarily addressing skeletal dysplasia, facial anomalies, and genital abnormalities through multidisciplinary management. Hormonal treatment with human growth hormone remains the most established modality, while gene therapy approaches aim to correct underlying FGD1 dysfunction at the molecular level. The therapy area dimension shows gene therapy representing the fastest-expanding segment as clinical pipelines mature, whereas supportive care occupies the largest current revenue pool due to its universal application across all patient stages. Delivery mode analysis reveals intravenous administration leads in gene therapy protocols, while oral hormonal agents dominate maintenance regimens in outpatient clinic settings.
FDA orphan drug designation and EMA rare disease incentives shape development economics by granting market exclusivity and protocol assistance for Aarskog syndrome candidates. Pediatric Investigation Plans under EMA and FDA requirements mandate age-appropriate formulation studies that extend timelines but ensure label suitability for the primary juvenile patient population. Stakeholders must monitor gene therapy regulatory precedents and reimbursement negotiations for ultra-rare indications to anticipate access dynamics for novel FGD1-targeted interventions.
Market Dynamics
Gene therapy platforms are compressing development timelines for FGD1-targeted interventions while FDA orphan drug incentives and EMA rare disease frameworks simultaneously reshape investment allocation across pediatric genetic disorder portfolios.
Growth Catalysts
- EMA Rare Disease Framework:Pediatric Investigation Plans accelerate label suitability for juvenile populations through protocol assistance and market exclusivity provisions that de-risk development economics for ultra-rare indications.
- Intravenous gene delivery protocols:Viral vector manufacturing scale-up at specialized biologics facilities is enabling Phase II pipeline progression for FGD1-targeted candidates previously constrained by production bottlenecks.
- United States:Clustering of specialized genetic clinics in Boston, San Francisco, and Baltimore generates concentrated referral networks that compress patient identification timelines for clinical trial enrollment.
Market Restraints
- Plasmid DNA supply concentration:Single-source dependence on North American contract manufacturers for clinical-grade viral vectors creates batch-to-batch variability risks that delay regulatory submission timelines.
- Reimbursement friction:US Centers for Medicare & Medicaid Services and European national health technology assessment bodies apply cost-effectiveness thresholds designed for common diseases that systematically undervalue one-time curative interventions for ultra-rare genetic conditions.
- FGD1 mutation heterogeneity:Variable phenotypic expression across the 150+ documented pathogenic variants complicates endpoint standardization and biomarker validation for unified regulatory approval pathways.
Strategic Opportunities
- Neonatal screening expansion:Addition of FGD1 sequencing to existing newborn screening panels in Germany, France, and the United Kingdom would compress diagnostic latency from years to weeks and expand addressable patient pools.
- Subcutaneous delivery innovation:Development of non-viral lipid nanoparticle formulations would displace intravenous infusion requirements and shift administration from hospital-based gene therapy centers to outpatient endocrinology clinics.
- FDA Rare Disease Endpoint Advancement Pilot:Qualification of novel skeletal dysplasia biomarkers as surrogate endpoints would accelerate approval pathways and reduce required clinical trial duration for pediatric growth interventions.
Industry Challenges
- Genetic counselor workforce scarcity:Specialized FGD1 expertise concentrates at fewer than forty academic medical centers globally, creating patient access bottlenecks and trial recruitment delays outside major metropolitan clusters.
- Good Manufacturing Practice facility retrofit requirements:Viral vector production suites demand capital commitments exceeding standard biologics infrastructure, constraining sponsor capacity to advance multiple concurrent programs.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Aarskog Syndrome Treatment Market |
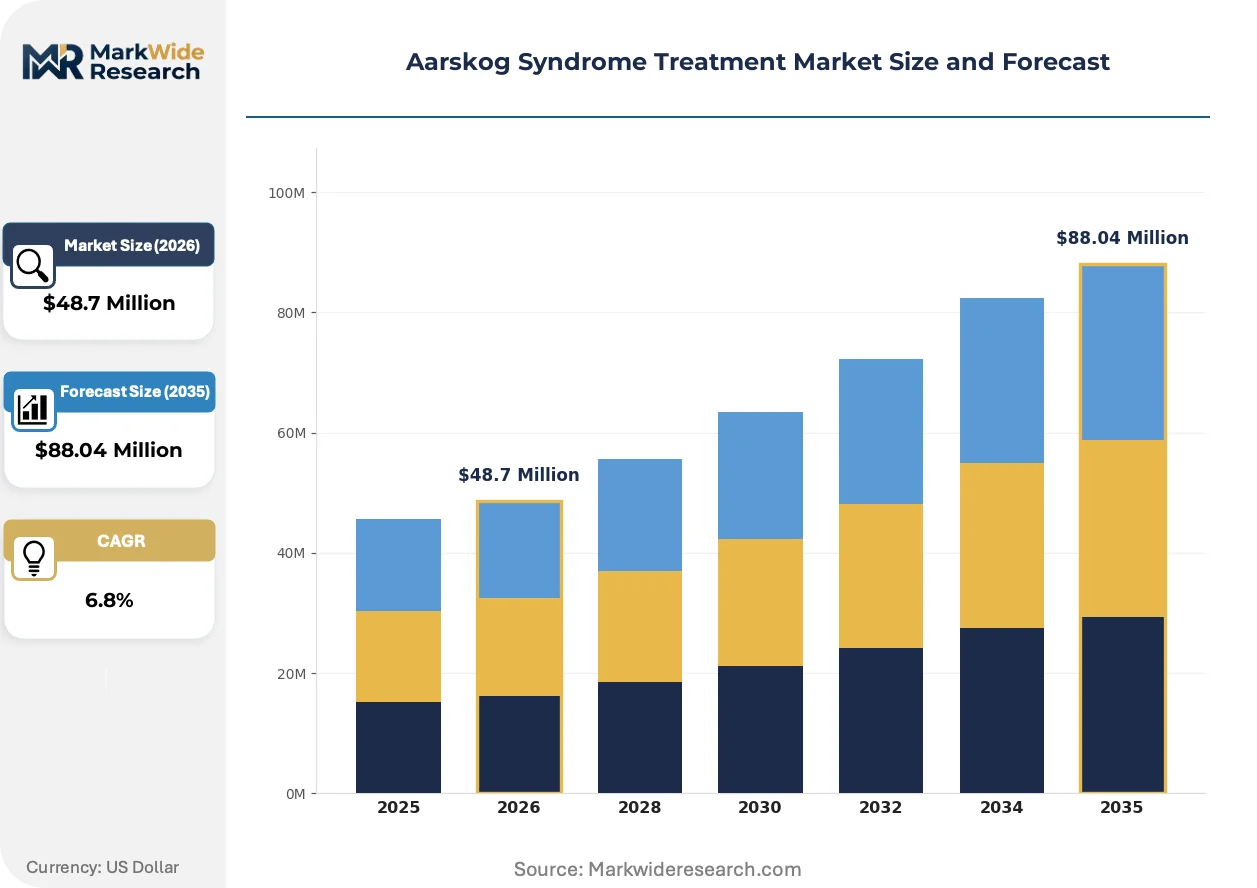
| Market Size in 2026 | $48.7 Million |
| Market Size in 2035 | $88.04 Million |
| CAGR (2026 – 2036) | 6.8% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Therapy Area: Gene Therapy, Hormonal Treatment, Supportive Care, Physiotherapy Delivery Mode: Intravenous, Oral, Topical, Injections Age Group: Pediatric, Adolescent, Adult, Geriatric Healthcare Setting: Outpatient Clinic, Hospital, Rehabilitation Center, Home Care |
| Companies Covered | Novartis AG, AstraZeneca, Takeda Pharmaceutical Company, GlaxoSmithKline, Merck & Co, Sanofi Genzyme, Orphan Biovitrum AB (Sobi), BioMarin Pharmaceutical, Pfizer Inc., Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Aarskog Syndrome Treatment Market Strategic Shifts
Delivery technology convergence and regulatory pathway innovation are compressing the gap between molecular target validation and clinical deployment for FGD1-related pathologies. Three developments merit particular attention.
CRISPR-based epigenome editing is miniaturizing the therapeutic payload requirements for FGD1 pathway modulation, enabling adeno-associated virus serotypes with smaller packaging limits to achieve functional correction. Pediatric endocrinology departments at academic medical centers in the United States and Germany are piloting these platforms for patients with partial loss-of-function mutations. The structural consequence is a shift from permanent gene insertion toward reversible expression modulation that reduces off-target liability and simplifies regulatory risk-benefit calculations.
REACH regulatory frameworks in Europe are imposing disclosure requirements on viral vector manufacturing processes that previously operated as trade secrets, forcing contract development and manufacturing organizations to document plasmid sourcing and cell bank provenance. The industrial consequence is accelerated facility qualification timelines but increased compliance costs that favor larger sponsors with dedicated quality infrastructure. Gene therapy developers targeting EMA approval are responding by verticalizing critical supply chain nodes rather than relying on multi-program contract manufacturers.
Patient advocacy organizations are consolidating procurement influence through managed access programs that negotiate post-approval pricing commitments before regulatory submission. These structures displace traditional pharmaceutical pricing negotiations conducted after approval and are most visible in the United States where the National Organization for Rare Disorders and similar entities coordinate coverage determination appeals. The behavioral shift compresses commercialization timelines but requires sponsors to commit to outcome-based rebate structures that tie reimbursement to growth velocity maintenance.
Aarskog Syndrome Treatment Market Segmentation
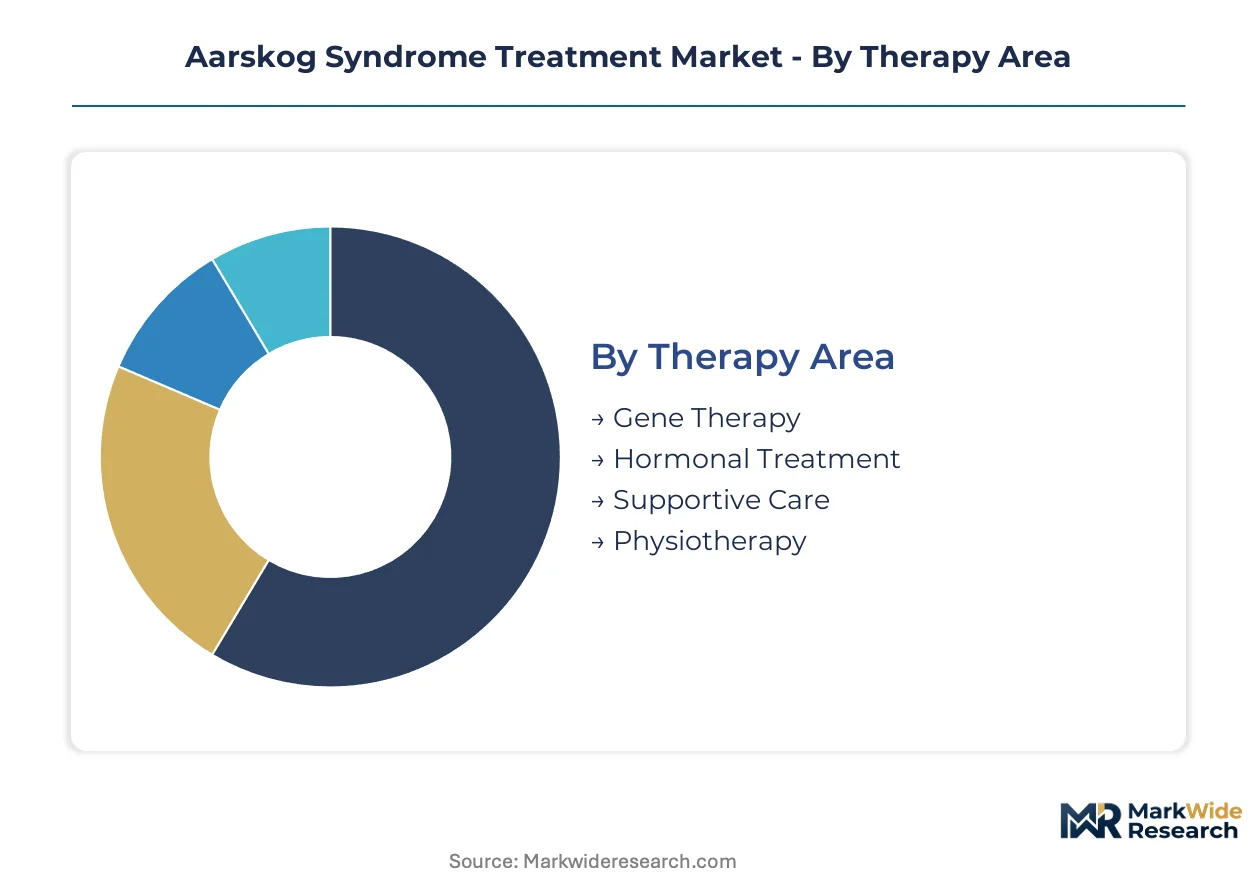
Therapy area segmentation reveals divergent investment profiles across Aarskog syndrome interventions, with gene therapy attracting venture capital while hormonal treatment sustains established revenue streams. Delivery mode and healthcare setting dimensions expose infrastructure dependencies that concentrate patient access in metropolitan corridor facilities.
Therapy Area:
Gene therapy development concentrates in United States coastal biotech clusters, whereas hormonal treatment protocols diffuse through European endocrinology networks. Supportive care and physiotherapy segments follow domestic healthcare system architectures without significant cross-border trade.
- Gene Therapy:Adeno-associated viral vectors deliver functional FGD1 constructs to correct Rho GTPase signaling defects at the molecular level. United States academic medical centers in Boston and San Francisco anchor Phase I/II trial enrollment, constrained by viral vector manufacturing bottlenecks at specialized biologics facilities.
- Hormonal Treatment:Recombinant human growth hormone protocols address statural growth deficits through daily subcutaneous administration. Germany, France, and the United Kingdom maintain the highest pediatric endocrinology specialist density, driving protocol standardization across European reference networks.
- Supportive Care:Multidisciplinary management of skeletal dysplasia, facial anomalies, and genital abnormalities through coordinated orthopedic, dental, and urological interventions.
- Physiotherapy:Targeted motor development programs addressing joint hypermobility and muscular hypotonia associated with FGD1 mutations.
Supportive care holds the largest share; momentum sits with gene therapy.
Delivery Mode:
Route of administration segmentation maps directly to care setting economics, with hospital-based infusion requirements imposing geographic access constraints that oral alternatives circumvent.
- Intravenous:Viral vector gene therapy requires specialized infusion centers with emergency response capabilities for anaphylaxis management. Hospital-based administration limits patient pool to urban corridor residents within travel distance of academic medical centers.
- Oral:Growth hormone secretagogues and maintenance medications enable decentralized prescription through community endocrinology practices. Outpatient clinic dispensing dominates in Germany and the United Kingdom where primary care gatekeeping structures prioritize oral step-therapy protocols.
- Topical:Dermatological preparations addressing cutaneous manifestations of Aarskog syndrome.
- Injections:Subcutaneous growth hormone delivery via patient-administered pen devices.
Oral delivery holds the largest share; intravenous administration is climbing the fastest.
Age Group:
Patient life-stage segmentation determines regulatory pathway complexity, with pediatric populations triggering mandatory Pediatric Investigation Plans under EMA frameworks.
- Pediatric:Patients under 12 years represent the primary addressable population for growth-modifying interventions. FDA and EMA orphan drug incentives concentrate on this segment, requiring age-appropriate formulation studies that extend development timelines.
- Adolescent:Transitional care protocols bridge pediatric endocrinology and adult genetic medicine services. United States academic medical centers pilot structured transition programs to prevent care discontinuity.
- Adult:Management of long-term orthopedic and genitourinary complications in diagnosed patients.
- Geriatric:Supportive interventions for age-related comorbidity management in older cohorts.
Pediatric holds the largest share; adolescent is gaining share fastest.
Healthcare Setting:
Facility type segmentation reflects reimbursement architecture and specialist availability, concentrating advanced interventions in tertiary referral networks.
- Outpatient Clinic:Pediatric endocrinology departments manage stable patients on hormonal protocols through scheduled monitoring visits. Community-based delivery dominates in France and Germany where regional healthcare networks decentralize chronic disease management.
- Hospital:Inpatient admission for surgical interventions, gene therapy infusion, and acute complication management. United States children's hospitals in Baltimore, Philadelphia, and Cincinnati anchor specialized FGD1 referral networks.
- Rehabilitation Center:Structured physiotherapy programs for motor development optimization.
- Home Care:Patient-administered injections and remote monitoring for stable maintenance regimens.
Hospital holds the largest share; home care shows the steepest expansion trajectory.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Consumption patterns for Aarskog syndrome treatment diverge sharply between gene therapy pioneers in United States academic corridors and hormonal protocol standard-bearers across European reference networks. Pediatric endocrinology infrastructure density determines access velocity more than patient prevalence.
United States
FDA orphan drug incentives and the Rare Disease Endpoint Advancement Pilot concentrate gene therapy development in Boston, San Francisco, and Baltimore clusters. Specialized genetic clinics at Massachusetts General Hospital and UCSF Benioff Children's Hospitals anchor Phase I/II trial enrollment for FGD1-targeted interventions. Viral vector manufacturing partnerships with North American contract development organizations sustain pipeline progression despite plasmid supply constraints.
Germany
The country's densest pediatric endocrinology specialist network drives European protocol standardization for recombinant human growth hormone regimens. EMA Pediatric Investigation Plans and national reference network structures coordinate multicenter studies across Heidelberg, Munich, and Hamburg university hospitals. REACH regulatory frameworks now mandate viral vector manufacturing disclosure that accelerates facility qualification for gene therapy sponsors.
United Kingdom
NHS England's specialized commissioning framework for rare diseases funnels Aarskog syndrome patients into London, Birmingham, and Manchester tertiary centers. The Medicines and Healthcare products Regulatory Agency's early access schemes compress regulatory timelines for FGD1-targeted candidates. Genomics England's 100,000 Genomes Project infrastructure supports newborn screening expansion discussions for FGD1 sequencing integration.
France
ANSM regulatory pathways and national rare disease plans coordinate care through Paris, Lyon, and Toulouse academic hospital networks. The country's reference center system for maladies rares centralizes multidisciplinary management protocols for skeletal dysplasia and genital abnormalities. Regional health agencies prioritize oral hormonal step-therapy protocols through community endocrinology gatekeeping structures.
Switzerland
Swissmedic's accelerated assessment procedures for advanced therapy medicinal products attract gene therapy sponsors seeking parallel EMA submission strategies. Basel and Zurich biotech clusters leverage proximity to Novartis AG infrastructure for viral vector process development. The country's compulsory health insurance system applies distinct cost-effectiveness thresholds for ultra-rare conditions that influence European pricing negotiations.
Aarskog Syndrome Treatment Market Competitive Environment
A small set of integrated leaders sits above a broader specialist tier in Aarskog syndrome treatment development. Large-cap pharmaceutical conglomerates with dedicated rare disease divisions anchor gene therapy pipelines through captive cell and gene therapy infrastructure. Mid-cap biotech specialists concentrate on single-platform precision interventions for FGD1-related pathologies. Competitive positioning hardens around manufacturing scale commitments and regulatory exclusivity capture rather than price competition. Dominant moves include vertical integration into viral vector production and strategic partnerships with academic medical centers for patient access.
Within the integrated leader tier, Novartis AG and Pfizer Inc. occupy positions shaped by cell and gene therapy infrastructure depth and broad rare disease portfolio scale. BioMarin Pharmaceutical exemplifies the specialist archetype through dedicated orphan disease program intensity. These three anchors reflect divergent capital allocation strategies: platform diversification versus indication concentration versus manufacturing scale leverage.
| Leading Market Players |
|---|
| Novartis AG |
| AstraZeneca |
| Takeda Pharmaceutical Company |
| GlaxoSmithKline |
| Merck & Co |
| Sanofi Genzyme |
| Orphan Biovitrum AB (Sobi) |
| BioMarin Pharmaceutical |
| Pfizer Inc. |
| Others |
Value Chain & Pricing Dynamics
Capacity reservation contracts with North American viral vector manufacturers lock in both supply access and price visibility for gene therapy sponsors pursuing FGD1-targeted candidates, insulating development programs from plasmid DNA spot-market volatility while anchoring cost structures for multi-year pediatric investigation timelines.
Pricing Analysis
Outcome-based rebate contracts for growth velocity maintenance drive lifetime value capture across hormonal treatment portfolios. Pricing stratifies across premium gene therapy interventions, standard recombinant human growth hormone regimens, and economy-tier supportive care bundles. Cost compression in viral vector manufacturing is intensifying because EMA disclosure requirements under REACH frameworks force contract manufacturers to document plasmid sourcing. Pediatric endocrinology departments exhibit lowest price sensitivity due to orphan drug reimbursement carve-outs, while general hospital procurement committees face highest sensitivity to one-time curative intervention costs.
Supply Chain Analysis
The United States and Germany anchor clinical-grade viral vector production for FGD1-targeted gene therapies, while Switzerland and the United Kingdom concentrate specialized biologics fill-finish operations. Manufacturing rests on plasmid DNA sourced from North American contract manufacturers, recombinant growth hormone API from European fermentation facilities, and lipid nanoparticle formulations from Swiss chemical suppliers. Single-source dependence on North American plasmid producers creates batch-to-batch variability risks. Distribution runs through hospital-based gene therapy centers for intravenous infusion protocols and community endocrinology networks for oral maintenance regimens.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Managed access program negotiations represent a service-attach opportunity expanding faster than therapeutic hardware, as patient advocacy organizations consolidate procurement influence through pre-approval pricing commitments that displace traditional post-regulatory commercialization timelines.
For Market Incumbents: Secure captive viral vector manufacturing capacity through backward integration into plasmid production or long-term offtake agreements with qualified contract development organizations. Defend gene therapy pipeline positions against mid-cap biotech entrants by accelerating FDA Rare Disease Endpoint Advancement Pilot engagement for novel skeletal dysplasia biomarkers. Channel control through academic medical center partnerships remains the critical lever for patient access concentration. For New Entrants and Emerging Players: Genetic counselor workforce scarcity in non-metropolitan regions creates a service-layer gap where telemedicine-enabled remote counseling platforms can compress diagnostic latency. Target adolescent transitional care protocols in United States academic medical centers as the most penetrable segment, where structured handoff programs between pediatric and adult services remain underdeveloped. A go-to-market angle anchored in subcutaneous delivery innovation displaces hospital-based infusion requirements and shifts administration to outpatient clinics. For Investors and Strategic Acquirers: Capital is best deployed toward gene therapy platforms with demonstrated viral vector manufacturing scale and EMA Pediatric Investigation Plan progress. Long-term viability over the five-to-ten year horizon hinges on qualification of novel surrogate endpoints that reduce clinical trial duration. The signal to watch is FDA orphan drug exclusivity grant velocity for FGD1-targeted candidates as an inflection indicator for competitive moat durability.| Strategic Initiative | Industry Significance |
|---|---|
| Clinical Trial Advancement | Phase II progression for FGD1-targeted candidates accelerates regulatory exclusivity capture timelines. |
| Manufacturing Scale-Up | Viral vector production suite expansion at specialized biologics facilities de-runs supply bottlenecks. |
| Regulatory Approval Pathway | EMA Pediatric Investigation Plan completion ensures label suitability for primary juvenile populations. |
| Pipeline Diversification | CRISPR-based epigenome editing platforms reduce off-target liability for partial loss-of-function mutations. |
| Strategic Partnership | Academic medical center alliances in Boston and San Francisco compress patient identification timelines. |
Study Parameters
Demand-side practitioners and supply-side operators were both consulted through structured primary interviews with pediatric endocrinologists, regulatory affairs leads at gene therapy sponsors, hospital procurement managers, and payer access specialists. Secondary validation drew from FDA orphan drug designations, EMA Pediatric Investigation Plan submissions, ClinicalTrials.gov registry entries, and hospital formulary databases. Bottom-up patient prevalence estimates and top-down market sizing triangulated across therapy area and delivery mode segmentation dimensions.
Across the analysis window, the forecasting framework modeled therapy area, delivery mode, age group, and healthcare setting dimensions with regional regulatory cluster overlays. CAGRs were derived from weighted pipeline progression probabilities and historical orphan drug adoption curves. Industry-specific inputs included viral vector manufacturing capacity expansion schedules and EMA rare disease framework incentive utilization rates.
Material uncertainties — regulatory submission delays, reimbursement negotiation outcomes, and plasmid supply disruptions — sit outside the modeled envelope. Forecasts reflect assumptions about Pediatric Investigation Plan completion timelines and gene therapy regulatory precedent establishment. Recalibration cycles align with material shifts in FDA orphan drug grant velocity and EMA advanced therapy medicinal product assessment throughput.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Specialty Medicine
Hermansky Pudlak Syndrome Therapeutics Market
Specialty Medicine
Narcolepsy Market
Specialty Medicine
Lamellar Ichthyosis Treatment Market
Specialty Medicine
Generalized Anxiety Disorder (GAD) Market
Specialty Medicine
Lateral Epicondylitis (Tennis Elbow) Treatment Market
Specialty Medicine
Piriformis Syndrome Market
Specialty Medicine
Global Vasculitis Treatment Market
Specialty Medicine
Benign Positional Vertigo Market
Specialty Medicine
Wilms Tumor Treatment Market
Specialty Medicine
Schizophrenia Treatment Market
Specialty Medicine
Cervical Dystonia Market
Specialty Medicine
Global Cancer Therapy Market
Specialty Medicine
North America Sports Medicine Market
Specialty Medicine
Nonerosive Reflux Disease Treatment Market
Specialty Medicine
Dyschromia Therapeutics Market
Specialty Medicine
Bronchiectasis Therapeutic Market