

Prior Authorization Workflow Orchestration Market Size, Share, and Industry Trends Forecast 2026-2036
Prior Authorization Workflow Orchestration Market Insights
Subscription-based SaaS financing is reshaping competitive entry in prior authorization workflow orchestration, lowering capital barriers for mid-tier health IT vendors. Cohere Health leverages cloud-native architecture to compete in payer-provider collaboration. Epic Systems anchors hospital-centric deployment with deep EHR integration. Optum differentiates through vertical control over both claims data and prior auth decision engines.
Prior Authorization Workflow Orchestration denotes the automated coordination of clinical documentation, payer policy matching, and approval routing across disparate health information systems, typically operating through HL7 FHIR APIs and real-time eligibility transactions. Its primary purpose is reducing administrative burden and care delays by replacing fax-and-phone workflows with rules-engine-driven digital pathways. Cloud-based deployment leads segment traction due to faster implementation cycles and lower IT overhead for specialty clinics and diagnostic centers. Integrated platforms capture disproportionate margin pools by bundling eligibility verification, medical necessity review, and claims processing into unified payer-provider workflows.
FDA interoperability standards, CMS prior authorization final rules, and HIPAA transaction set requirements collectively mandate real-time API connectivity between providers and payers, directly shaping platform architecture and procurement criteria. State Medicaid agencies and commercial health plans enforce varying documentation standards that fragment vendor certification requirements. Stakeholders must monitor regulatory divergence between federal interoperability mandates and state-level prior auth reform legislation to anticipate compliance-driven replacement cycles.
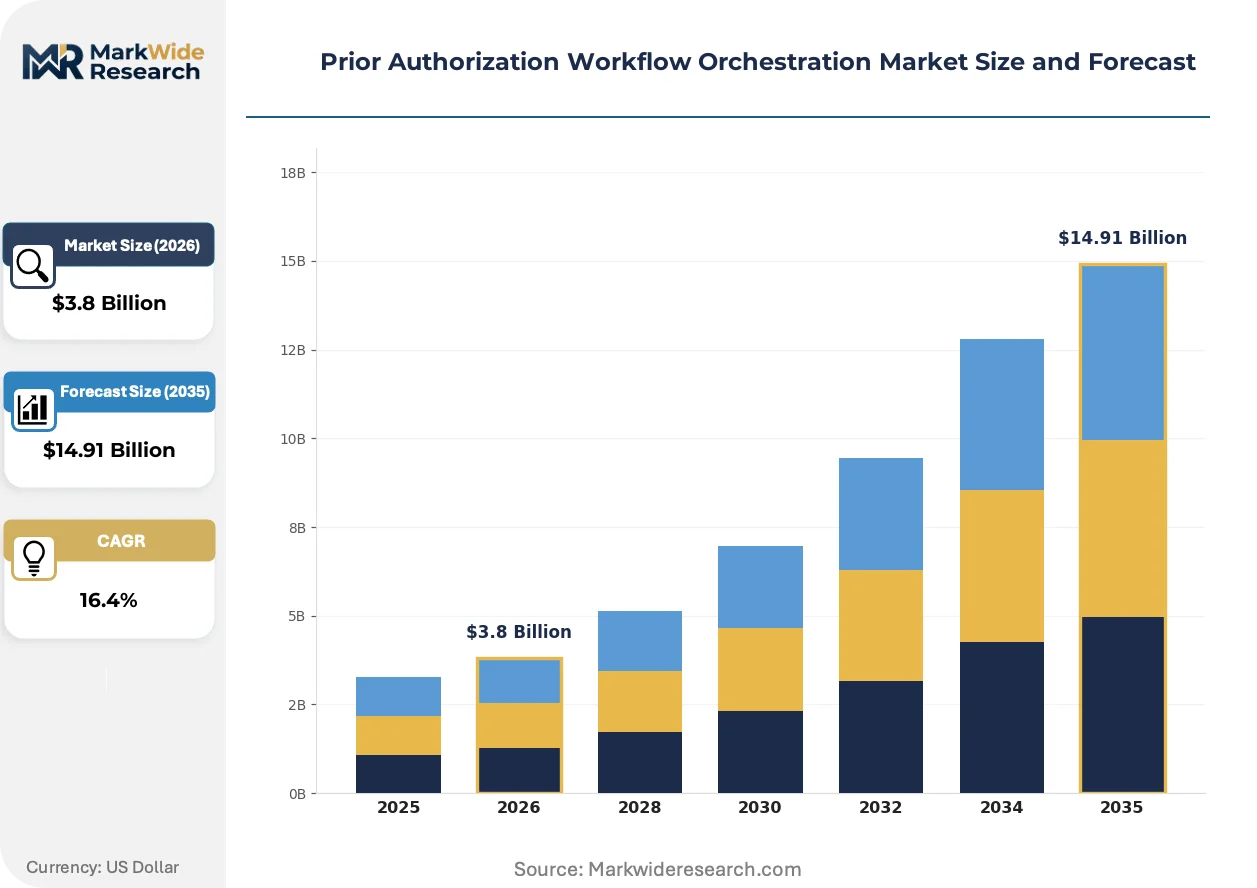
Market Dynamics
HL7 FHIR API standardization is compressing implementation timelines and forcing vendor consolidation as payers and providers rebuild connectivity layers around real-time data exchange mandates.
Growth Catalysts
- CMS Prior Authorization Final Rule:Federal mandates require Medicare Advantage plans to implement automated prior auth systems by specified deadlines, creating immediate procurement pull across integrated delivery networks.
- Specialty clinic digitization:Oncology and cardiology outpatient centers are replacing fax-based workflows with cloud-native orchestration platforms to reduce administrative overhead and accelerate patient scheduling.
- Interoperability investment:Health systems are allocating capital to API infrastructure that connects EHRs directly to payer decision engines, bypassing manual documentation bottlenecks.
Market Restraints
- Payer policy fragmentation:Commercial health plans maintain proprietary clinical criteria libraries that resist standardization, forcing vendors to build and maintain multiple rule-engine configurations.
- Legacy EHR technical debt:Hospital systems running on-premise Cerner or older Epic installations face integration complexity that delays cloud migration and API enablement.
- State Medicaid variability:Each state Medicaid agency enforces distinct documentation requirements and approval timelines, multiplying certification burden for national platform deployments.
Strategic Opportunities
- Rural health network penetration:Critical access hospitals and federally qualified health centers remain underserved by automated prior auth solutions, presenting white-space opportunity for purpose-built lightweight platforms.
- Diagnostic imaging integration:Radiation therapy and advanced imaging centers face high denial rates for prior auth, creating demand for embedded clinical decision support within PACS and RIS systems.
- AI-assisted medical necessity review:Natural language processing engines trained on historical approval patterns can pre-populate authorization requests, reducing clinical staff documentation burden.
Industry Challenges
- Clinical informaticist shortage:Health systems lack sufficient staff to map internal clinical protocols to payer-specific authorization rules, creating implementation bottlenecks and delayed go-live dates.
- Multi-payer connectivity maintenance:Platforms must sustain hundreds of individual API connections to distinct payer systems, each with unique authentication protocols and endpoint specifications.
Report Scope
MarkWide ResearchGet the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Prior Authorization Workflow Orchestration Market Trends and Innovations
Real-time eligibility verification and automated clinical documentation are converging into unified workflow layers that compress the authorization cycle from days to minutes. This integration is redefining competitive advantage around speed-to-decision rather than standalone feature depth.
Cloud-native prior auth platforms are virtualizing the traditional boundary between provider and payer systems. These architectures enable bidirectional data flow through containerized microservices. Specialty pharmacies and infusion centers are adopting these systems fastest due to high transaction volumes. The technology is virtualizing legacy hub-and-spoke integration models into distributed, API-first networks.
FDA interoperability mandates and HIPAA transaction set updates are mandating standardized data exchange formats across the US health system. These rules eliminate proprietary data formats that previously locked providers into specific vendor ecosystems. Payer organizations are responding by accelerating internal API gateway investments to meet compliance deadlines.
Subscription-based platform procurement is displacing perpetual license models as health systems prioritize operational expenditure flexibility. Chief information officers now favor vendors offering usage-based pricing tied to authorization volume. This shift is most pronounced among mid-sized health systems in the southeastern and midwestern United States seeking to minimize upfront capital deployment.
Prior Authorization Workflow Orchestration Market Segmentation
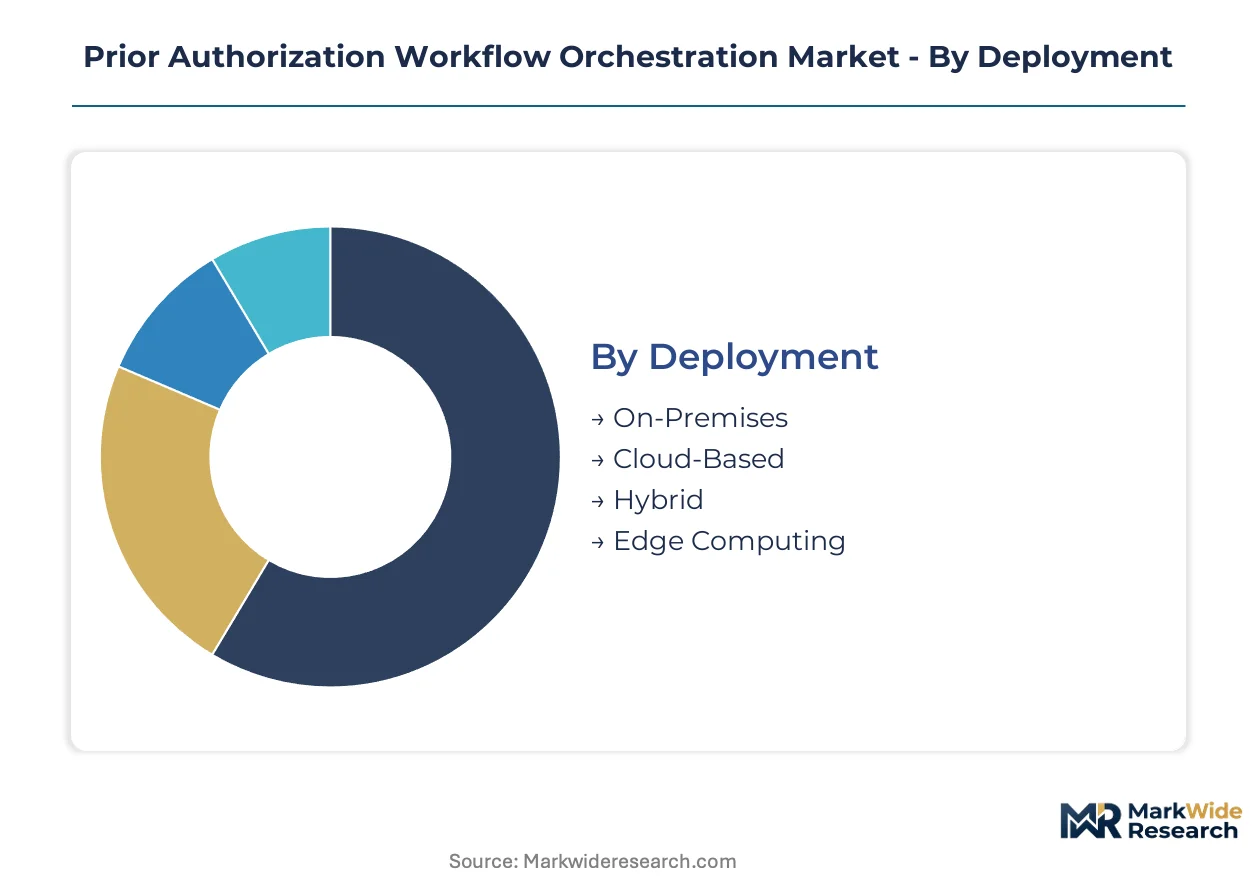
Prior authorization workflow orchestration platforms serve heterogeneous stakeholders with divergent technical requirements and compliance obligations. Segmentation reveals how deployment architecture, solution packaging, clinical application, and end-user category determine procurement criteria and margin structure across the value chain.
Deployment:
Cost tier determines infrastructure commitment and operational flexibility for healthcare organizations navigating legacy system constraints.
- Cloud-Based:Multi-tenant SaaS architectures eliminate capital expenditure for server infrastructure while enabling automatic FHIR API updates. Specialty clinics in Texas and Florida are migrating fastest to reduce IT overhead and accelerate implementation timelines.
- On-Premises:Dedicated hardware installations within health system data centers satisfy stringent HIPAA security requirements for patient data sovereignty. Large integrated delivery networks in California and New York maintain these deployments to preserve existing Cerner and Epic integration investments.
- Hybrid:Split architectures route sensitive clinical data through on-premise nodes while pushing analytics workloads to cloud environments.
- Edge Computing:Distributed processing nodes at diagnostic centers enable real-time authorization decisions without latency to central servers.
Cloud-Based holds installed capacity. Edge Computing is rotating up the share rankings.
Solution/Offering:
Application sophistication separates point solutions from unified platforms that consolidate multiple workflow stages.
- Integrated Platform:Bundled systems combine eligibility verification, medical necessity review, and claims processing into unified payer-provider workflows. Health plans in Illinois and Ohio prioritize these solutions to reduce vendor management complexity and API maintenance overhead.
- API Services:Modular connectivity layers embed prior auth functionality directly into EHR interfaces through standardized HL7 FHIR endpoints. Hospital IT departments in Pennsylvania and Massachusetts favor this approach for incremental digitization without full platform replacement.
- Standalone Software:Purpose-built applications address specific authorization stages without broader workflow integration.
- Mobile Applications:Smartphone-native interfaces enable clinical staff to initiate and track authorization requests at point of care.
- Analytics Tools:Retrospective dashboards identify denial patterns and approval velocity bottlenecks for operational improvement.
Integrated Platform dominates revenue concentration. API Services is gaining share fastest among mid-tier health systems.
Application:
Volume intensity varies across clinical workflow stages, with some applications handling thousands of daily transactions per facility.
- Prior Authorization Management:Core orchestration engines route documentation, match payer policies, and track approval status across disparate systems. Oncology and cardiology outpatient centers in Arizona and North Carolina drive demand for specialized configurations addressing high-value service lines.
- Medical Necessity Review:Clinical decision support modules apply evidence-based criteria to pre-populate authorization justifications. Radiation therapy centers face elevated denial rates that accelerate adoption of AI-assisted documentation tools.
- Insurance Verification:Real-time eligibility queries confirm patient coverage parameters before service delivery.
- Eligibility Management:Ongoing monitoring of benefit changes and authorization expiration dates prevents claim rejections.
- Claims Processing:Post-authorization submission and adjudication workflows complete the revenue cycle.
Prior Authorization Management anchors platform deployments. Medical Necessity Review shows steepest expansion trajectory as denial rates climb.
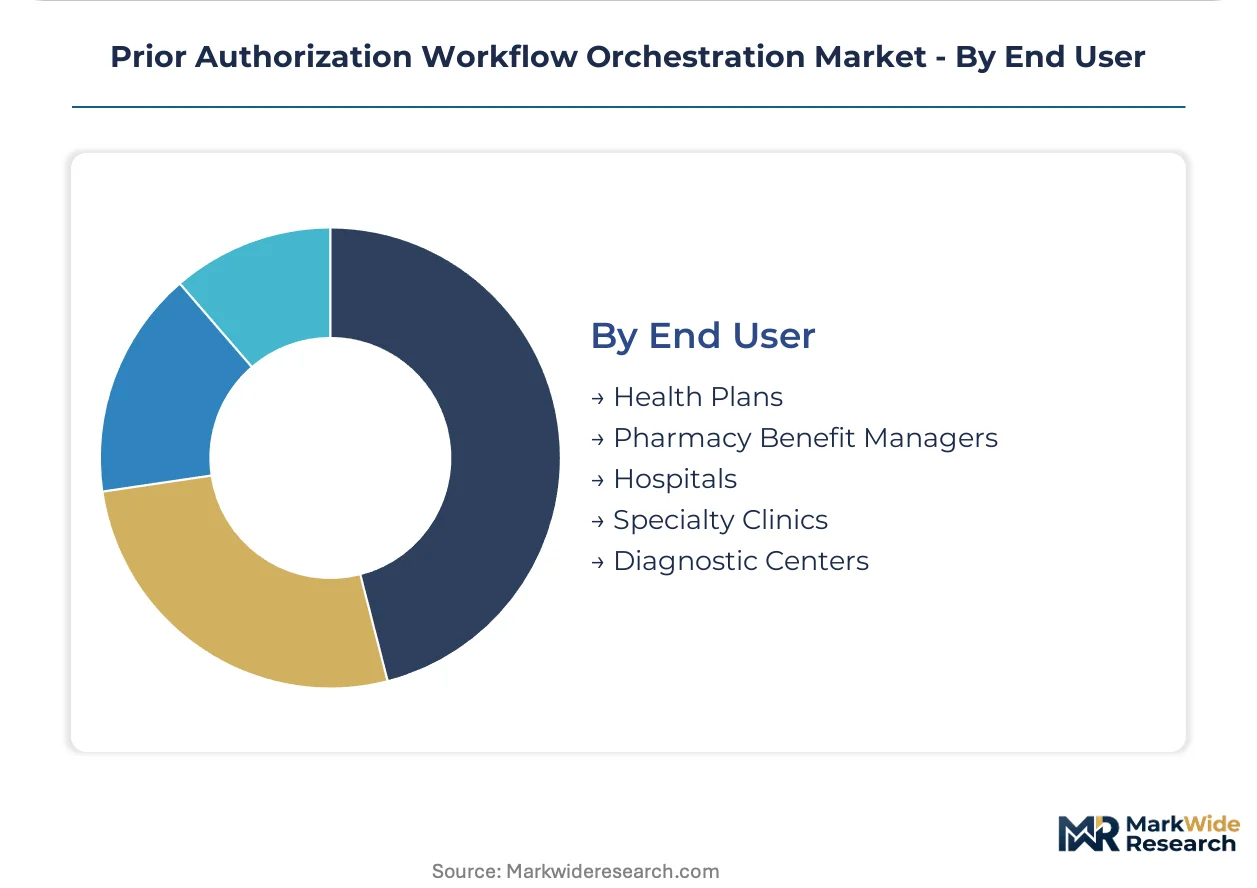
End User:
Customer type dictates pricing sensitivity, implementation complexity, and required payer connectivity depth.
- Hospitals:Acute care facilities require comprehensive integration with existing EHR infrastructure and multi-payer connectivity portfolios. Systems in Michigan and Georgia face legacy technical debt that delays cloud migration despite federal interoperability mandates.
- Specialty Clinics:Focused outpatient centers prioritize rapid implementation and specialty-specific workflow templates. Infusion centers and dialysis clinics in Colorado and Washington adopt cloud-native platforms fastest due to high daily authorization volumes.
- Health Plans:Payer organizations invest in internal decision engines and provider-facing portals to meet CMS automated prior auth deadlines.
- Pharmacy Benefit Managers:PBMs require specialized connectivity for pharmaceutical prior authorization distinct from medical services.
- Diagnostic Centers:Imaging and laboratory facilities need embedded authorization workflows within PACS and LIS systems.
Hospitals represent the largest addressable spend. Specialty Clinics are climbing the fastest in new deployment velocity.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Pricing power concentrates in United States health systems where CMS mandates drive procurement urgency, while Canadian providers operate under provincial budget constraints that compress implementation timelines and favor lighter deployment models.
United States
Integrated delivery networks in Texas and Florida are replacing legacy fax workflows with cloud-native platforms to meet CMS prior authorization deadlines. The FDA's interoperability mandates and HIPAA transaction set requirements enforce real-time API connectivity between EHRs and payer systems. Specialty oncology clinics in Arizona and North Carolina drive fastest adoption of medical necessity review modules.
Germany
Hospital IT departments prioritize HL7 FHIR-compliant systems to satisfy the Digital Healthcare Act's interoperability provisions for electronic health records. The EMA's guidance on real-world evidence integration influences how German payers structure prior authorization criteria for innovative therapies. Medical centers in Bavaria and North Rhine-Westphalia are piloting automated authorization workflows for high-cost specialty pharmaceuticals.
United Kingdom
NHS Trusts in England are consolidating prior authorization processes through the Federated Data Platform to reduce administrative duplication across integrated care systems. NHS England's prior approval frameworks for specialized treatments mandate digital submission pathways that favor API-first vendor architectures. London and Greater Manchester health systems lead procurement of unified eligibility verification platforms.
Canada
Provincial health authorities in Ontario and British Columbia are modernizing prior authorization infrastructure to reduce specialist wait times and administrative burden on primary care physicians. Health Canada's guidance on digital health interoperability shapes procurement specifications for payer-provider connectivity. Toronto and Vancouver hospital networks are deploying hybrid cloud solutions to maintain data residency compliance.
Japan
University hospitals in Tokyo and Osaka are adopting workflow orchestration platforms to streamline reimbursement authorization for advanced medical devices under the national health insurance system. METI's promotion of healthcare data standardization accelerates vendor certification requirements for FHIR-based connectivity. Regional medical associations in Kansai are piloting automated prior auth for proton therapy and regenerative medicine.
Prior Authorization Workflow Orchestration Market Competitive Landscape
Platform integrators command the system tier; component specialists sit upstream in the connectivity layer. The vendor base separates into consolidated EHR-anchored platforms and fragmented point-solution providers. Three archetypes dominate: health plan-owned verticals, EHR-embedded modules, and independent cloud-native orchestrators. Competitive moves concentrate on API gateway consolidation and specialty-specific workflow template expansion.
Within the independent cloud-native tier, Cohere Health exemplifies architecture built for payer-provider collaboration from inception. Epic Systems anchors the EHR-embedded archetype through deep clinical system integration. Optum occupies a position representing health plan vertical integration over both claims data and authorization decision engines.
| Leading Market Players |
|---|
| Availity |
| Cohere Health |
| Waystar |
| Surescripts |
| CoverMyMeds |
| Oracle Health |
| Epic Systems |
| Optum |
| Experian Health |
| Others |
Pricing and Supply Chain Analysis
Texas and Florida health system clusters anchor North American platform capacity, with cloud-native vendor concentration in Austin and Miami directly shaping pricing power for integrated delivery networks negotiating multi-year SaaS contracts. Their scale advantages compress implementation timelines and create regional pricing benchmarks that smaller markets reference.
Pricing Analysis
Configuration-to-order pricing for Epic-embedded deployments commands a 40-60% premium over standard cloud-native SaaS tiers due to deep EHR integration requirements. Subscription-based SaaS models dominate, with price differentiation driven by FHIR API volume tiers and after-sales clinical informaticist support. Pricing pressure stems from mid-tier health systems demanding usage-based pricing tied to authorization throughput. Critical access hospitals exhibit highest price sensitivity; large integrated delivery networks prioritize total cost of ownership over per-transaction rates.
Supply Chain Analysis
Upstream cloud infrastructure feeds from hyperscaler data centers concentrated in Virginia, Oregon, and Ohio, with API gateway middleware sourced from California and Massachusetts development clusters. Raw material dependencies include HL7 FHIR certification libraries, payer rule-engine configurations, and clinical ontology databases. Single-source vulnerability concentrates in proprietary payer decision engine connections that resist standardization. Distribution runs through health system IT procurement committees and GPO technology contracts, with direct vendor relationships gaining share among specialty clinic segments.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Prior authorization workflow orchestration sits in early-cycle expansion, with CMS mandate deadlines creating a procurement tailwind that will sustain vendor growth through compliance-driven replacement cycles across Medicare Advantage plans.
For Market Incumbents: Harden API gateway consolidation through acquisition of specialty-specific rule-engine providers to defend against cloud-native entrants targeting oncology and cardiology workflows. Deepen clinical informaticist capacity in-house to accelerate implementation velocity and reduce customer churn from delayed go-live dates. Vertical control over payer connectivity portfolios remains the critical defensive lever. For New Entrants and Emerging Players: Rural health networks in the Mountain West and Deep South present the most penetrable white-space, with critical access hospitals operating legacy fax workflows and lacking dedicated IT procurement staff. Target diagnostic imaging centers facing elevated prior auth denial rates for radiation therapy and advanced imaging. A lightweight, mobile-first platform with pre-configured Medicaid state templates offers the clearest go-to-market angle. For Investors and Strategic Acquirers: Long-term, this sits as a healthcare IT infrastructure play because prior authorization automation will become embedded plumbing rather than discretionary software spend. Acquisition targets should display dense payer API connectivity and specialty-specific clinical workflow templates. The signal to watch is state Medicaid agency consolidation of prior auth requirements, which would compress certification burden and accelerate platform consolidation.| Strategic Initiative | Industry Significance |
|---|---|
| FHIR API Gateway Consolidation | Epic Systems and Oracle Health are acquiring niche connectivity vendors to deepen payer reach. |
| Specialty Workflow Template Expansion | Cohere Health and Waystar are building oncology-specific rule engines to capture high-value service lines. |
| AI-Assisted Medical Necessity Review | NLP engines trained on CMS Medicare data reduce clinical documentation burden and accelerate approvals. |
| Geographic Expansion to Rural Networks | Cloud-native vendors are piloting lightweight platforms in Montana and Mississippi critical access hospitals. |
| Strategic Partnership with PBMs | CoverMyMeds and Surescripts are embedding pharmaceutical prior auth into medical workflow orchestration layers. |
Research Methodology
Desk research of FDA interoperability guidance documents, CMS prior authorization rulemaking dockets, and HL7 FHIR implementation guides preceded structured interviews with health system CIOs, payer prior auth operations directors, clinical informaticists, and EHR integration specialists. Secondary validation drew from hospital procurement databases, GPO technology contracts, and state Medicaid agency procurement records. Bottom-up authorization volume estimates triangulated against top-down health IT spending forecasts.
Assumptions held fixed include CMS compliance deadline adherence and continued HL7 FHIR API standardization momentum, while variables included state Medicaid agency consolidation timelines and specialty clinic digitization velocity. Segmentation modeling spanned deployment architecture, solution packaging, clinical application, and end-user category across the projection horizon. CAGRs derived from authorization transaction volume growth curves weighted by EHR penetration rates and payer API enablement progress.
Practitioners should monitor state-level prior auth reform legislation and federal interoperability mandate enforcement for early signals of replacement cycle acceleration. Forecasts reflect assumptions about regulatory compliance adherence and vendor certification capacity expansion. Cross-checking against CMS Medicare Advantage plan procurement disclosures and state Medicaid technology modernization budgets is advised before commitment-grade decisions.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.