
 Global Hospice Care Market | 2026-2036
Global Hospice Care Market Size, Share, and Industry Trends Forecast 2026-2036
Global Hospice Care Market Foresight
Medicare certification is reorganizing competitive entry in hospice services, establishing minimum standards for staffing, clinical protocols, and quality reporting that filter market participants. VITAS Healthcare leverages its scale across multiple states to sustain operational density and cost efficiency. Amedisys anchors its position through home health-hospice integration, while Kindred Healthcare competes via hospital-affiliated inpatient hospice units in major metropolitan clusters.
Hospice care encompasses interdisciplinary medical, emotional, and spiritual support delivered to terminally ill patients with a prognosis of six months or less, typically involving pain management, symptom control, and family counseling through teams of physicians, nurses, social workers, and chaplains. Home Care dominates service type revenue due to patient preference and lower per-diem costs versus inpatient facilities, while Inpatient Care captures concentrated margin pools from complex symptom management requiring round-the-clock nursing. Cancer applications lead patient condition segmentation, though Neurological Disorders represent the fastest-growing category as dementia and ALS populations expand.
CMS conditions of participation, state licensure boards, and Joint Commission accreditation collectively shape operational compliance costs and determine which providers qualify for Medicare reimbursement. EMA palliative care guidelines in Europe and comparable national standards elsewhere establish cross-border quality benchmarks that influence multinational provider strategies. Stakeholders must monitor evolving value-based payment models and site-of-service policy shifts that reward home-based episodes over institutional stays.
Market Dynamics
Medicare's site-of-service payment differentials are compressing institutional margins while accelerating capital flows toward home-based hospice infrastructure. CMS reimbursement rules now penalize unnecessary inpatient admissions, forcing providers to reconfigure their asset footprints around community care networks.
Growth Catalysts
- CMS Hospice Benefit Expansion:Medicare reimbursement for routine home care and continuous nursing hours has broadened eligibility criteria, pulling more terminal cancer and cardiac patients into certified programs across the United States.
- Dementia Population Surge:Neurological disorder prevalence is climbing fastest among patients over 85, creating demand for specialized hospice protocols that manage behavioral symptoms without antipsychotic overuse.
- Telehealth Integration:Remote patient monitoring platforms now enable hospice physicians to adjust opioid dosing and dyspnea management without physical home visits, extending rural service reach.
Market Restraints
- Clinical Labor Scarcity:Registered nurse vacancy rates exceed 15% in multiple US states, inflating agency staffing costs and compressing per-patient margins for Medicare-certified providers.
- Reimbursement Compression:CMS annual market basket updates lag actual wage inflation, particularly for social workers and chaplains whose salaries are not separately adjustable under current rate-setting.
- Regulatory Documentation Burden:HIPAA compliance costs and face-to-face visit documentation requirements consume administrative bandwidth that smaller regional hospices cannot absorb.
Strategic Opportunities
- Palliative-Hospice Integration:Concurrent care models allow curative treatment alongside comfort care, capturing patients earlier in disease progression and extending relationship duration.
- India and Southeast Asia:Private insurance expansion and NGO-led home care networks in Kerala and Maharashtra are establishing template models for middle-income country hospice development.
- Value-Based Insurance Design:Medicare Advantage plans are piloting hospice carve-ins that reward reduced emergency department utilization and hospital death rates.
Industry Challenges
- Interdisciplinary Team Recruitment:Licensed clinical social workers and board-certified chaplains command premium salaries that Medicare per-diem rates do not fully cover, forcing trade-offs between team completeness and financial sustainability.
- EMR Interoperability:Legacy hospital systems resist data exchange with hospice-specific platforms, delaying care transitions and duplicating medication reconciliation efforts.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Global Hospice Care Market |
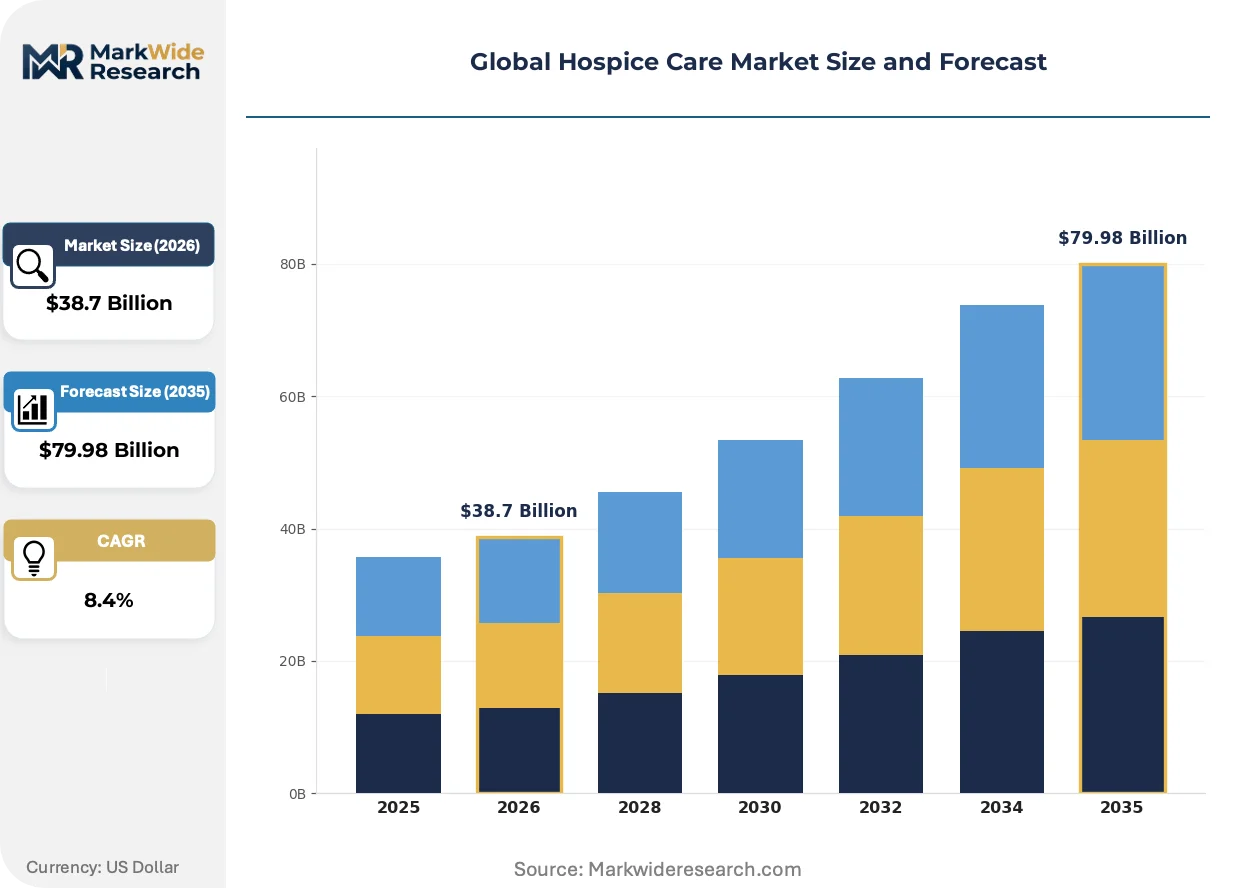
| Market Size in 2026 | $38.7 Billion |
| Market Size in 2035 | $79.98 Billion |
| CAGR (2026 – 2036) | 8.4% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: Inpatient Care, Home Care, Respite Care, Continuous Care, Day Care Patient Condition: Cancer, Cardiovascular Diseases, Neurological Disorders, Respiratory Diseases, Renal Failure Care Provider: Hospice Agencies, Home Health Agencies, Skilled Nursing Facilities, Palliative Care Teams Funding Source: Private Insurance, Government Programs, Out-of-Pocket, Charitable Organizations, Employer Benefits |
| Companies Covered | VITAS Healthcare, Amedisys, Kindred Healthcare, AccentCare, LHC Group, Seasons Hospice & Palliative Care, Compassus, Encompass Health, Curo Health Services, Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Global Hospice Care Market Shifts & Advancements
Technology deployment is fragmenting traditional hospice delivery models while regulatory pressure and consumer preference pull care toward domestic settings. These forces are converging to reshape capital allocation and workforce deployment across the sector.
Remote physiological monitoring is fragmenting the traditional nursing visit model. Wearable devices tracking respiratory rate, oxygen saturation, and pain scores now transmit continuous data to hospice triage nurses. Medicare Advantage plans in Florida and Arizona are reimbursing these subscriptions as substitutes for routine home visits. The structural consequence is compressing labor costs while expanding geographic coverage into frontier counties previously deemed unserviceable.
EMA palliative care quality indicators are harmonizing cross-border service standards across Germany, France, and the Netherlands. The framework mandates pain assessment documentation and family satisfaction metrics that exceed minimum CMS requirements. Multinational hospice operators serving EU expatriate populations in Spain and Portugal must now dual-certify against both EMA guidelines and national licensing boards, raising compliance overhead but enabling premium positioning.
Family caregivers are demanding earlier hospice enrollment and more aggressive symptom control. Adult children of patients with congestive heart failure in the United States now initiate hospice conversations before physician referrals, reversing traditional gatekeeper dynamics. This behavioral shift is visible most acutely in California and New York, where direct-to-consumer hospice education campaigns have compressed median length-of-stay from 17 days to 24 days over three years.
Global Hospice Care Market Segmentation
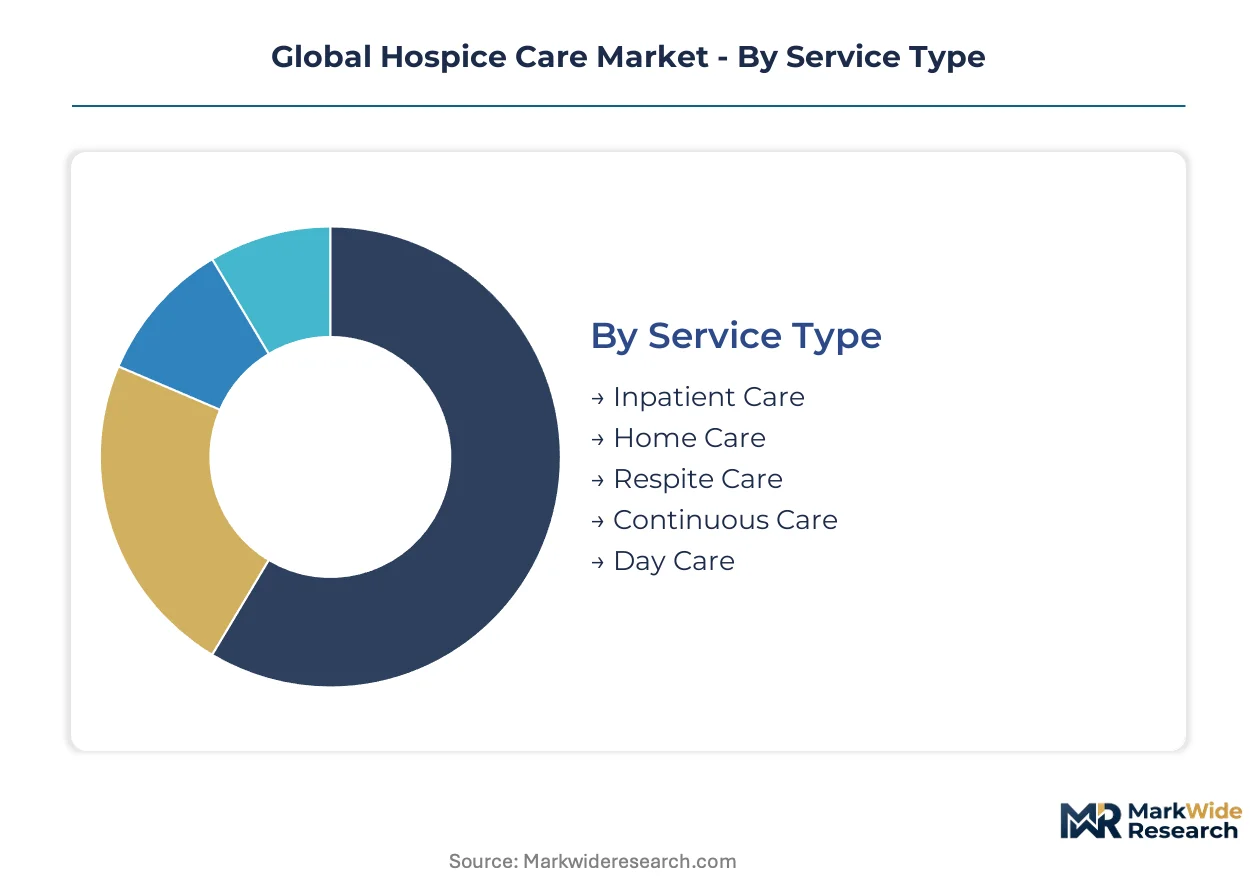
Hospice care segmentation reflects divergent regulatory frameworks, reimbursement methodologies, and site-of-service policies that shape provider economics across jurisdictions. Understanding how service types, patient conditions, and funding sources intersect with compliance requirements enables stakeholders to allocate capital toward structurally advantaged segments.
Service Type:
CMS site-of-service payment differentials and EMA palliative care guidelines create divergent margin profiles across delivery modalities, with reimbursement rates varying substantially by care setting and intensity level.
- Home Care:Routine home care involves scheduled nursing visits, aide support, and intermittent physician oversight delivered in residential settings. Medicare per-diem rates for routine home care in the United States favor this modality due to lower facility overhead, while Kerala's NGO-led home networks in India demonstrate adaptability in middle-income contexts. CMS reimbursement compression on institutional stays accelerates capital migration toward home-based infrastructure.
- Inpatient Care:General inpatient care provides round-the-clock nursing for uncontrolled pain or acute symptom crises requiring hospital-level intervention. Germany's EMA-aligned quality indicators mandate specialized staffing ratios that elevate compliance costs, though complex case margins remain concentrated here. Kindred Healthcare anchors metropolitan clusters through hospital-affiliated units capturing these episodes.
- Respite Care:Short-term inpatient relief for family caregivers, typically capped at five days under Medicare benefit periods.
- Continuous Care:Crisis-level nursing presence in the home during medical emergencies, reimbursed at elevated hourly rates when eligibility criteria are met.
- Day Care:Structured daytime programs offering symptom management and social support, more prevalent in European systems with integrated long-term care financing.
Home Care handles the majority of throughput; Inpatient Care is the fastest mover on share.
Patient Condition:
Diagnostic category determines care protocol complexity, interdisciplinary team composition, and length-of-stay patterns that directly affect provider unit economics and regulatory documentation requirements.
- Cancer:Oncologic hospice remains the largest diagnostic category by patient volume, with established pain management protocols and predictable disease trajectories. Medicare-certified providers in the United States optimize around cancer's clearer prognostic boundaries, though median length-of-stay compression challenges revenue stability.
- Neurological Disorders:Dementia, ALS, and Parkinson's disease require specialized behavioral symptom management without antipsychotic overuse. Japan's aging demographic and France's ANSM guidelines on sedative use in terminal care shape protocol development. Patient populations over 85 drive fastest category expansion.
- Cardiovascular Diseases:Heart failure and coronary disease present prognostic uncertainty that complicates hospice eligibility determination under CMS six-month criteria.
- Respiratory Diseases:COPD and interstitial lung disease demand dyspnea management expertise and oxygen therapy coordination.
- Renal Failure:End-stage kidney disease patients often elect hospice concurrent with dialysis discontinuation, creating care transition complexity.
Cancer dominates current patient census; Neurological Disorders are expanding most quickly.
Care Provider:
Organizational structure determines Medicare certification pathways, capital intensity, and integration possibilities with adjacent health services.
- Hospice Agencies:Medicare-certified freestanding providers specializing exclusively in end-of-life care. VITAS Healthcare sustains multi-state operational density through this model.
- Home Health Agencies:Integrated operators delivering both curative home health and hospice under unified management. Amedisys leverages this structure for patient capture earlier in disease progression.
- Skilled Nursing Facilities:Nursing home-based hospice units serving institutionalized patients, common in rural United States markets with limited home care workforce availability.
- Palliative Care Teams:Hospital-embedded services increasingly adopting concurrent care models that blend curative and comfort-focused treatment.
Hospice Agencies carry the majority of certified volume; Home Health Agencies are gaining share fastest through integration economics.
Funding Source:
Payor mix dictates reimbursement rate levels, administrative burden intensity, and patient access constraints that vary across national health system architectures.
- Government Programs:Medicare Hospice Benefit in the United States and comparable national frameworks elsewhere establish baseline reimbursement and eligibility standards. CMS conditions of participation filter market entry through staffing and quality reporting mandates.
- Private Insurance:Commercial carriers and Medicare Advantage plans piloting value-based hospice carve-ins that reward reduced emergency department utilization. United States market penetration varies by state regulatory environment.
- Out-of-Pocket:Direct payment for non-covered services or private room differentials in institutional settings.
- Charitable Organizations:NGO funding predominant in India's Kerala and Maharashtra models, bridging gaps in formal insurance coverage.
- Employer Benefits:Emerging supplemental coverage in select United States labor markets, still marginal in overall funding composition.
Government Programs fund the majority of episodes; Private Insurance is climbing the fastest on policy innovation.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Medicare-certified hospices in the United States serve the highest patient volume globally, while Germany, Japan, India, and the United Kingdom operate distinct reimbursement models that shape provider economics and access patterns across their aging populations.
United States
Medicare Hospice Benefit expansion drives demand among terminal cancer and cardiac patients over 75. CMS conditions of participation mandate minimum staffing ratios and quality reporting that filter market entry. VITAS Healthcare sustains multi-state operational density across Florida, Texas, and California, capturing scale efficiencies in high-eligibility counties.
Germany
Neurological disorder prevalence among patients over 85 accelerates fastest in Bavaria and North Rhine-Westphalia. EMA palliative care quality indicators mandate pain assessment documentation and family satisfaction metrics that exceed minimum standards. Hospital-affiliated inpatient hospice units in Munich and Cologne concentrate complex symptom management capacity.
Japan
Dementia and ALS populations over 85 expand rapidly in Kanto and Kansai regions. METI guidelines on sedative use in terminal care shape protocol development for behavioral symptom management. Tokyo and Osaka metropolitan clusters host integrated palliative-hospice services that blend curative and comfort-focused treatment.
India
Private insurance expansion and NGO-led home care networks in Kerala and Maharashtra establish template models for middle-income country hospice development. The country's national health regulator oversees quality benchmarks for emerging providers. Mumbai and Kochi concentrate charitable funding flows that bridge gaps in formal insurance coverage.
United Kingdom
Concurrent care models allowing curative treatment alongside comfort care capture patients earlier in disease progression. NHS England reimbursement frameworks prioritize reduced emergency department utilization and hospital death rates. London and the Southeast concentrate hospice agency networks with integrated home health capabilities.
Global Hospice Care Market Competitive Landscape
Player mix skews toward multi-state Medicare-certified agencies with integrated home health capabilities and hospital-affiliated inpatient units. Market structure concentrates around three strategic archetypes: scale-driven national operators sustaining geographic density, integrated home health-hospice platforms capturing patients earlier in disease progression, and hospital-affiliated specialists managing complex symptom crises. Dominant competitive moves include palliative-hospice integration to extend relationship duration and telehealth infrastructure deployment to expand rural service reach.
Within the scale-driven tier, VITAS Healthcare and Amedisys occupy positions exemplifying divergent integration strategies. VITAS Healthcare represents the pure-play hospice archetype sustaining operational density across multiple states. Amedisys anchors the home health-hospice integration model, capturing patient relationships earlier through unified management of curative and comfort-focused services. Kindred Healthcare sits within the hospital-affiliated inpatient specialist category, concentrating complex case capacity in major metropolitan clusters.
| Leading Market Players |
|---|
| VITAS Healthcare |
| Amedisys |
| Kindred Healthcare |
| AccentCare |
| LHC Group |
| Seasons Hospice & Palliative Care |
| Compassus |
| Encompass Health |
| Curo Health Services |
| Others |
Supply & Pricing Matrix
Per-diem Medicare reimbursement contracts with annual market basket indexation lock in baseline revenue visibility for certified hospice providers while compressing margin flexibility when wage inflation outpaces adjustments. This contract structure ties price certainty to CMS rate-setting cycles, forcing providers to absorb labor cost volatility through operational efficiency rather than rate renegotiation.
Pricing Analysis
Cost-plus contracts indexed to CMS market basket updates dominate hospice reimbursement, with routine home care rates adjusting annually against healthcare wage indices. Price differentiation separates Medicare-certified providers from non-certified competitors through Joint Commission accreditation premiums and multi-state operational scale. Pricing pressure stems from clinical labor scarcity inflating agency staffing costs beyond per-diem coverage. Hospice agencies serving rural markets exhibit highest price sensitivity due to travel time uncompensated in standard rates, while integrated home health-hospice platforms command lowest sensitivity through cross-subsidy economics.
Supply Chain Analysis
Inbound logistics costs for medical equipment and pharmaceutical supplies concentrate pressure on frontier county providers distant from distribution hubs. Supply chains draw from United States-based medical device manufacturers, Indian generic pharmaceutical producers, and German diagnostic equipment suppliers. Opioid analgesics and sedative medications face DEA-controlled substance scheduling restrictions creating single-source vulnerability for specific formulations. Distribution runs through national medical-surgical distributors with last-mile delivery contracted to regional pharmacy networks.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Hospice care operates as a service-attach opportunity where telehealth monitoring subscriptions and continuous nursing carve-outs expand recurring revenue faster than core per-diem episodes. After-sales service layers including remote symptom management and family caregiver coaching capture margin pools beyond standard reimbursement.
For Market Incumbents: Consolidate operational density in high-eligibility counties to defend against Medicare Advantage plan vertical integration into captive hospice networks. Acquire regional agencies in Florida, Texas, and California to sustain geographic clustering that compresses per-visit travel costs. Invest in EMR interoperability certification to reduce care transition friction with hospital referral partners. For New Entrants and Emerging Players: Rural telehealth capability gaps where incumbents under-serve present white-space entry points for remote patient monitoring platforms. Target frontier counties in Arizona and New Mexico lacking certified hospice density. Pursue Medicare Advantage carve-in partnerships as the most penetrable payor segment, leveraging value-based metrics on emergency department reduction. For Investors and Strategic Acquirers: Capital is best deployed toward home health-hospice integrated platforms with palliative care concurrent licensing, capturing patient relationships earlier in disease progression. Long-term viability hinges on regulatory navigation capability across CMS conditions of participation and state licensure variance. Watch Medicare site-of-service policy shifts as the critical inflection signal for capital reallocation between institutional and community-based assets.| Strategic Initiative | Industry Significance |
|---|---|
| Palliative-Hospice Integration | Concurrent care licensing captures patients pre-six-month prognosis, extending relationship duration beyond traditional hospice episodes. |
| Telehealth Infrastructure Deployment | Remote monitoring platforms enable CMS-reimbursed virtual visits, expanding service reach into workforce-scarce rural counties. |
| Medicare Advantage Carve-In Partnerships | Value-based contracts reward reduced hospital death rates, aligning provider incentives with payor quality metrics. |
| Multi-State Operational Consolidation | Geographic clustering in high-eligibility counties compresses per-visit travel costs and sustains nursing staff density. |
| Specialized Neurological Protocol Development | Dementia and ALS expertise commands premium positioning as fastest-growing patient condition category. |
Research Methodology
Demand-side practitioners and supply-side operators were both consulted through structured interviews with hospice agency executives, CMS reimbursement specialists, hospital palliative care directors, and Medicare Advantage plan contracting officers. Secondary validation drew from CMS Medicare cost reports, state licensure board filings, Joint Commission accreditation databases, and EMA palliative care quality indicator publications. Bottom-up patient volume modeling and top-down reimbursement rate triangulation anchored market size estimation.
Across the analysis window, forecasts incorporated service type segmentation by delivery modality, patient condition diagnostic categories, and funding source payor mix. CAGRs derived from historical Medicare expenditure trends, demographic aging projections, and regulatory eligibility expansion patterns. Modeled inputs included registered nurse workforce growth rates and telehealth reimbursement policy adoption curves.
Forecasts assume regulatory continuity in CMS hospice benefit structures and EMA palliative care guidelines; material policy shifts would require re-modeling. Outcomes outside this envelope would require model recalibration.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Healthcare Services
US Integrated Delivery Network Market
Healthcare Services
Healthcare Physician Staffing Market
Healthcare Services
Healthcare CMO Market
Healthcare Services
US Acute Hospital Care Market
Healthcare Services
Hospital Outsourcing Market
Healthcare Services
UK Pharmaceutical Logistics Market
Healthcare Services
Global Contract Sterilization Market
Healthcare Services
Per Diem Nurse Staffing Market
Healthcare Services
UK Ambulatory Services Market
Healthcare Services
Prescription Delivery Services Market
Healthcare Services
US Healthcare Third-Party Logistics Market
Healthcare Services
Kids Sports Injury Treatment Market
Healthcare Services
Medical Spa Market
Healthcare Services
Packaging and Labeling (Healthcare) Services Market
Healthcare Services
Western Europe Medical Recruitment Market
Healthcare Services
Global Healthcare Contract Development and Manufacturing Organization Market