
 US Skilled Nursing Facility Market | 2026-2036
US Skilled Nursing Facility Market Size, Share, and Industry Trends Forecast 2026-2036
US Skilled Nursing Facility Market Intelligence
CMS Five-Star Quality Rating System certification is unwinding the competitive landscape by elevating minimum staffing thresholds and clinical outcome benchmarks. Genesis HealthCare leverages its scale across multiple states to absorb compliance costs. The Ensign Group sustains operational margins through decentralized facility management. Life Care Centers of America anchors its position with faith-based community integration.
A skilled nursing facility delivers 24-hour licensed nursing care, rehabilitation therapy, and medical supervision to patients requiring post-hospitalization recovery or chronic disease management, typically operating beds licensed for stays exceeding 30 days with Medicare Part A as the primary reimbursement mechanism. Long-term care occupies the largest revenue share due to extended Medicaid-funded stays among geriatric patients with multiple comorbidities. Short-term rehabilitation generates superior per-diem rates through Medicare reimbursement tied to case-mix adjusted payment groups. Memory care segments command pricing premiums as specialized dementia units require higher staffing ratios and secure environment infrastructure.
CMS, state Medicaid agencies, and OSHA collectively govern facility licensing, reimbursement rates, and workplace safety standards, with CMS Patient-Driven Payment Model revisions directly altering per-diem revenue calculations. State Certificate of Need programs constrain new bed supply in concentrated markets, preserving incumbent pricing power. Stakeholders must monitor CMS proposed rulemaking on minimum nurse staffing ratios to assess capital deployment timing for labor automation and retention infrastructure.
Market Dynamics
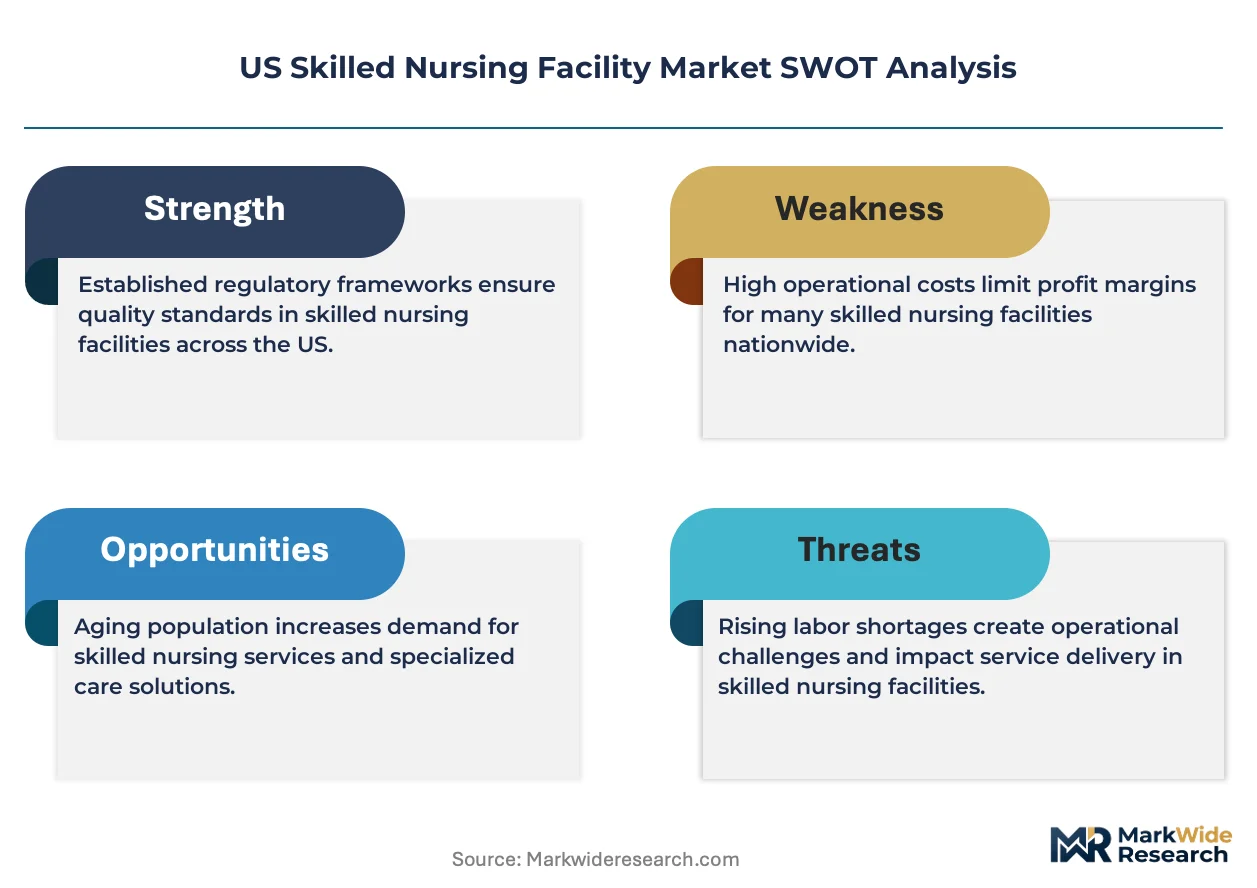
The CMS Five-Star Quality Rating System is compressing reimbursement eligibility for underperforming operators while concentrating volume toward facilities that absorb elevated staffing mandates. This regulatory lever is reshaping capital deployment timelines and facility-level economics across state Medicaid programs.
Growth Catalysts
- Post-Acute Surgical Volume:Joint replacement recoveries and cardiac rehabilitation cases are expanding Medicare Part A admissions. Texas, Florida, and Ohio bed development concentrates near hospital discharge corridors.
- Medicaid Expansion:State-level program extensions are lengthening average length-of-stay for dual-eligible populations with multiple comorbidities. This stabilizes occupancy rates in non-urban markets.
- Remote Patient Monitoring:RPM integration into skilled nursing workflows is reducing preventable hospital readmissions. CMS quality metrics reward facilities deploying continuous glucose and cardiac monitoring.
Market Restraints
- Labor Cost Escalation:Registered nurse and certified nursing assistant wage inflation is compressing per-diem margins. Facilities in competitive labor markets face 15-25% annual staff turnover.
- Certificate of Need Constraints:State CON programs in New York, Illinois, and Kentucky limit new bed supply. Incumbent operators in these markets maintain pricing power without competitive entry pressure.
- Home-Based Care Substitution:Medicare Advantage plans are steering lower-acuity patients toward home health and outpatient rehabilitation. This diverts revenue from traditional facility-based post-acute channels.
Strategic Opportunities
- Memory Care Specialization:Dementia-specific units command staffing-adjusted rate premiums. Secure-environment infrastructure investments attract private-pay families seeking specialized behavioral management.
- Value-Based Care Alignment:Medicare ACO and bundled payment participation creates shared savings upside. Facilities integrating with hospital systems capture preferred provider status.
- Rural Bed Conversion:Underutilized acute care hospitals in Appalachian and Great Plains regions present conversion candidates. State rural health incentives offset capital requirements for skilled nursing repurposing.
Industry Challenges
- Workforce Pipeline Collapse:Nursing school capacity constraints and immigration visa processing delays limit licensed staff availability. Facilities compete with hospitals for same-day hiring.
- Technology Integration Debt:Electronic health record interoperability with hospital systems requires multi-year capital commitments. Legacy platforms impede real-time care coordination.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | US Skilled Nursing Facility Market |
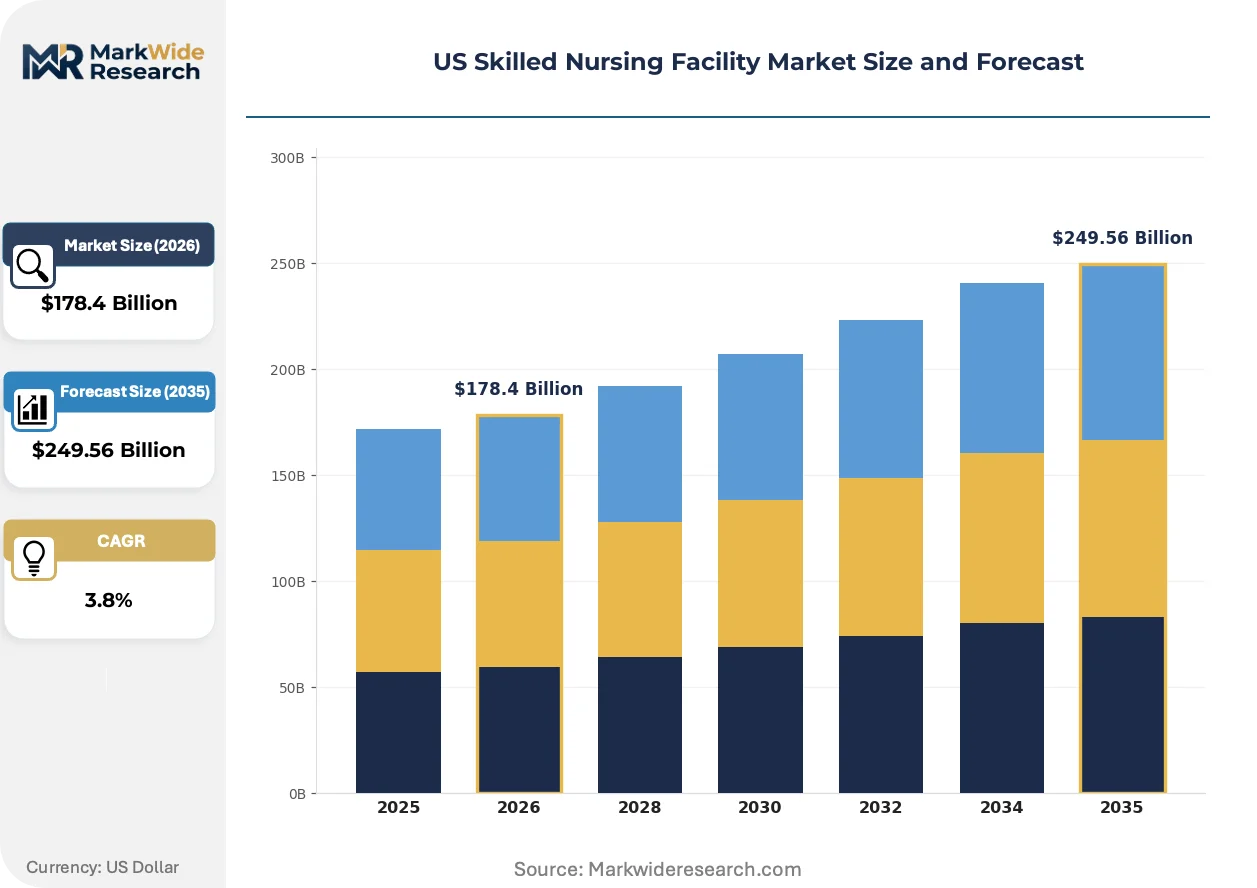
| Market Size in 2026 | $178.4 Billion |
| Market Size in 2035 | $249.56 Billion |
| CAGR (2026 – 2036) | 3.8% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: Long-Term Care, Short-Term Rehabilitation, Palliative Care, Memory Care Facility Type: For-Profit, Non-Profit, Government-Owned, Hybrid Patient Demographics: Geriatric Patients, Disabled Individuals, Post-Acute Care Patients, Chronic Illness Patients Payment Model: Medicare, Medicaid, Private Pay, Managed Care |
| Companies Covered | Genesis HealthCare, The Ensign Group, Life Care Centers of America, ProMedica Senior Care, The Evangelical Lutheran Good Samaritan Society, Saber Healthcare Group, Sava Senior Care, Signature HealthCARE, Brookdale Senior Living, Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
US Skilled Nursing Facility Market Strategic Shifts & Innovations
Technology deployment and reimbursement model redesign are fragmenting the traditional skilled nursing value proposition. Operators must now simultaneously manage acute-complexity patients and long-stay Medicaid populations under diverging staffing protocols.
Telehealth-enabled physician coverage is bifurcating facility capabilities. Specialist consultations via synchronous video reduce emergency department transfers for wound care and infectious disease management. Large multi-state operators deploy 24/7 telehospitalist coverage across rural properties. Smaller independent facilities lack capital for comparable infrastructure, widening the clinical outcomes gap.
OSHA workplace violence prevention mandates are altering facility design standards. The agency's updated enforcement priorities require physical environment modifications including panic buttons and restricted access corridors. Memory care and behavioral health units face the most intensive compliance timelines. Operators in California and Massachusetts are accelerating renovation schedules ahead of state-level adoption.
Hospital-at-home programs are diverting post-acute volume from traditional skilled nursing channels. Medicare waiver expansions allow acute-level care delivery in residential settings for COPD, heart failure, and pneumonia patients. Health systems in Arizona and Wisconsin are piloting bundled arrangements that bypass facility placement entirely. Skilled nursing operators are responding by developing transitional care management contracts that capture patients post-hospital-at-home discharge.
US Skilled Nursing Facility Market Segmentation
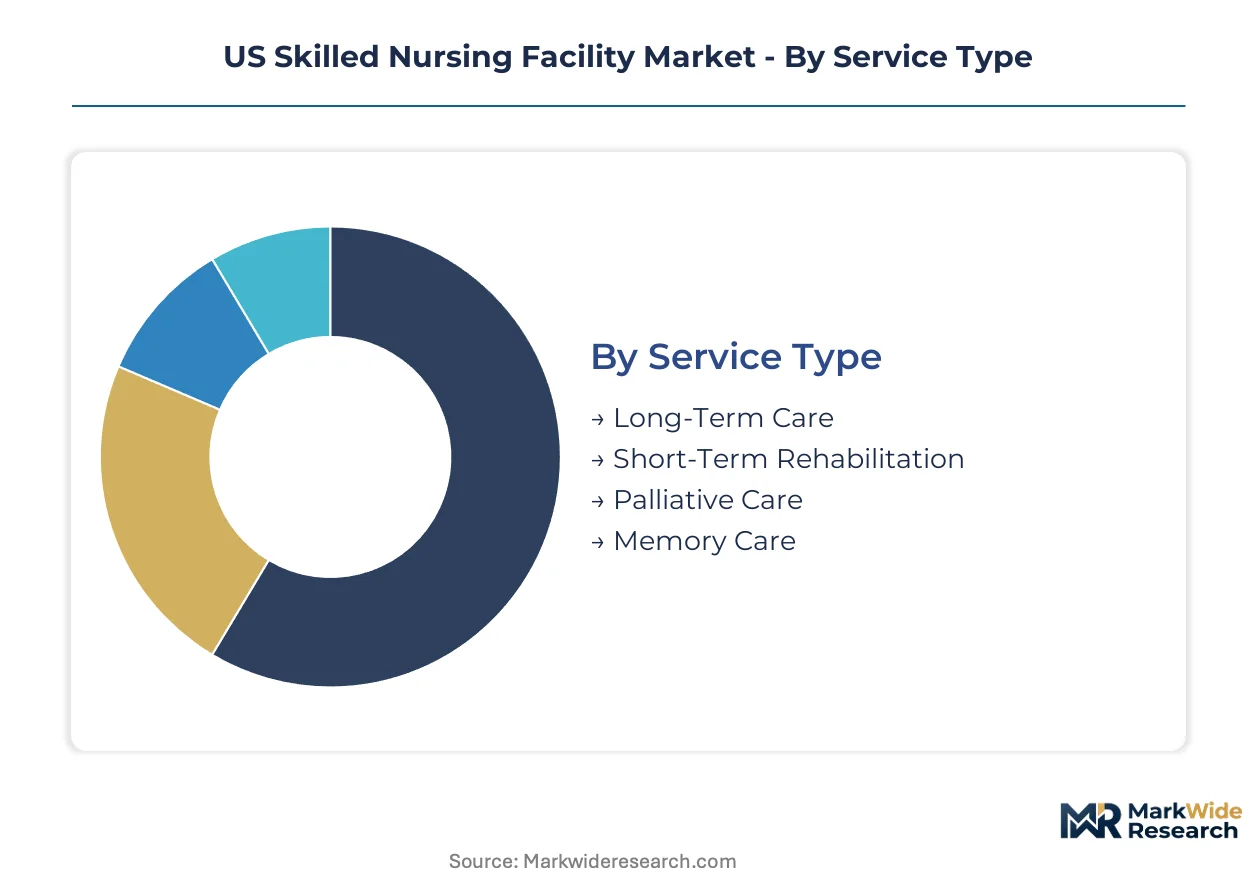
Segmentation in the US skilled nursing facility market reveals divergent operational economics across service lines and ownership structures. Reimbursement mechanisms and patient acuity levels create distinct margin profiles that shape capital allocation and facility design decisions.
Service Type:
Long-term care dominates bed utilization across rural Texas, Florida, and Ohio corridors, while short-term rehabilitation concentrates near metropolitan hospital discharge networks. Memory care and palliative services occupy specialized facility wings with distinct staffing protocols.
- Long-Term Care:Extended-stay services for geriatric patients with multiple chronic conditions, typically funded through state Medicaid programs. Demand concentrates in non-urban Ohio and Appalachian regions where home-based alternatives remain limited by workforce shortages.
- Short-Term Rehabilitation:Post-acute recovery services following joint replacement and cardiac procedures, reimbursed through Medicare Part A case-mix adjusted payment groups. Volume clusters along Texas and Florida hospital discharge corridors where surgical throughput drives admission velocity.
- Palliative Care:Symptom management and comfort-focused services for patients with serious illness, often co-located within skilled nursing facilities. Pain management protocols and hospice transition coordination define operational requirements.
- Memory Care:Secure-unit services for dementia patients requiring behavioral management and wandering prevention. Higher staffing ratios and specialized environmental design command rate premiums from private-pay families.
Long-term care holds the largest share; momentum sits with memory care specialization.
Facility Type:
Ownership structure determines capital access and margin pressure tolerance, with for-profit chains absorbing CMS compliance costs through scale while non-profits leverage community integration for referral stability.
- For-Profit:Investor-owned facilities operating across multi-state networks, deploying centralized purchasing and shared clinical services. These operators dominate new bed development in Texas and Florida Certificate-of-Need-exempt markets.
- Non-Profit:Community-anchored facilities often affiliated with religious or charitable organizations, sustaining occupancy through local hospital relationships and mission-driven reputation. Ohio and Massachusetts host concentrated non-profit presence.
- Government-Owned:County or municipal facilities serving as providers of last resort in underserved markets, typically operating with explicit public subsidy and mandated access obligations.
- Hybrid:Mixed ownership structures combining non-profit mission with for-profit management contracts, emerging in rural hospital conversion scenarios where public capital supports facility repurposing.
For-profit operators capture volume leadership; hybrid structures are climbing the fastest as rural hospital conversions accelerate.
Patient Demographics:
Patient mix determines reimbursement composition and clinical staffing intensity, with geriatric populations anchoring Medicaid-funded length-of-stay economics.
- Geriatric Patients:Adults aged 65 and older with functional decline or cognitive impairment, representing the core census of most facilities. Dual-eligible status complicates reimbursement coordination between Medicare and Medicaid.
- Disabled Individuals:Non-elderly adults with physical or developmental disabilities requiring 24-hour nursing supervision, often funded through Medicaid waiver programs with state-specific eligibility criteria.
- Post-Acute Care Patients:Hospital discharge patients requiring skilled nursing or rehabilitation services before returning home, driving Medicare Part A revenue concentration in short-stay units.
- Chronic Illness Patients:Individuals with diabetes, heart failure, or COPD requiring ongoing medical management, increasingly targeted by remote patient monitoring integration to reduce readmission penalties.
Geriatric patients constitute the dominant demographic; post-acute care patients are gaining share fastest through surgical volume expansion.
Payment Model:
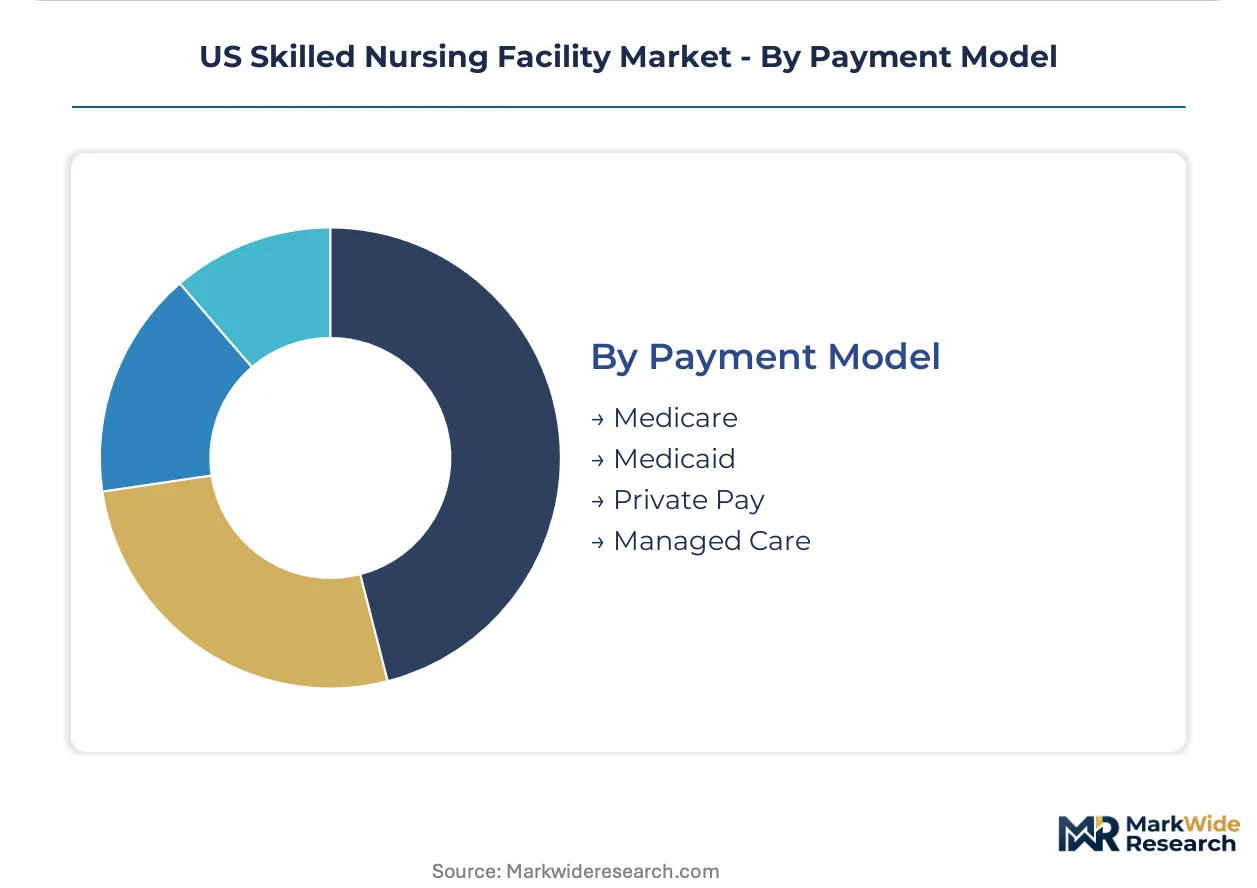
Reimbursement source dictates per-diem rates and administrative burden, with Medicare Advantage growth redirecting traditional Medicare fee-for-service volume.
- Medicare:Federal fee-for-service reimbursement for post-acute stays up to 100 days, with case-mix adjusted payment groups determining daily rates. CMS Five-Star Quality Rating System performance directly impacts eligibility and rate adjustments.
- Medicaid:State-administered programs funding long-term care for low-income patients, with rates varying dramatically across Texas, Florida, and Ohio based on state budget priorities and provider lobbying.
- Private Pay:Out-of-pocket payment from patients or families, concentrated in memory care and premium facility wings where amenities and private rooms justify rate premiums above government benchmarks.
- Managed Care:Medicare Advantage and Medicaid managed care plans negotiating bundled rates and utilization controls, increasingly steering patients toward narrow networks and home-based alternatives.
Medicaid occupies the largest revenue share; managed care is expanding most quickly as Medicare Advantage penetration deepens.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Dual-eligible Medicare-Medicaid beneficiaries and post-acute surgical discharges concentrate demand across distinct state corridors. Certificate-of-Need regulations and Medicaid reimbursement generosity fragment competitive intensity.
Texas
Joint replacement recovery volumes and rapid population aging drive bed demand in Dallas-Fort Worth and Houston corridors. The state maintains CON-exempt status for skilled nursing development, enabling rapid facility expansion. Major operators concentrate new construction along Interstate 35 and Highway 59 hospital discharge networks.
Florida
Snowbird migration patterns and retiree concentration sustain above-national-average occupancy in Tampa Bay and Orlando markets. State Medicaid program generosity ranks below national medians, pressuring long-stay reimbursement rates. The Villages and Sarasota metro areas host specialized memory care development clusters.
Ohio
Rust Belt industrial legacy populations and Appalachian health disparities anchor Medicaid-dependent long-term care demand. The state CON program constrains new bed supply in Cleveland and Columbus markets. Non-profit operators maintain dominant market share through community hospital integration.
California
OSHA workplace violence prevention mandates and aggressive minimum staffing legislation elevate compliance costs above national benchmarks. Los Angeles and San Francisco Bay Area facilities face acute licensed nurse shortages. Medi-Cal reimbursement rates lag operational cost inflation, squeezing rural operator margins.
New York
Downstate Medicaid redetermination turbulence and upstate population decline create divergent regional economics. The state CON apparatus preserves incumbent pricing power in New York City metro corridors. Buffalo and Rochester markets see accelerated hospital-at-home pilot programs diverting traditional skilled nursing volume.
US Skilled Nursing Facility Market Key Industry Players
Player mix skews toward multi-state for-profit chains with scale advantages in compliance absorption and centralized purchasing. Market structure concentrates volume among ten major operators controlling approximately one-third of licensed beds. Strategic archetypes separate into scale-driven consolidators, faith-based community anchors, and regional specialists with hospital system integration. Dominant competitive moves include portfolio divestitures of underperforming assets and Medicare ACO partnership formations.
Within the scale-driven consolidator tier, Genesis HealthCare and The Ensign Group occupy positions reflecting divergent operational philosophies. Genesis HealthCare exemplifies geographic diversification across dozens of states with centralized clinical support infrastructure. The Ensign Group represents decentralized facility autonomy with local market entrepreneurship. Life Care Centers of America anchors the faith-based archetype, sustaining referral relationships through denominational community networks rather than scale economics.
| Leading Market Players |
|---|
| Genesis HealthCare |
| The Ensign Group |
| Life Care Centers of America |
| ProMedica Senior Care |
| The Evangelical Lutheran Good Samaritan Society |
| Saber Healthcare Group |
| Sava Senior Care |
| Signature HealthCARE |
| Brookdale Senior Living |
| Others |
Cost & Logistics Intelligence
Home health substitution is displacing traditional skilled nursing volume in lower-acuity segments, compressing Medicare Advantage reimbursement rates while redirecting capital toward remote patient monitoring infrastructure and transitional care management capabilities.
Pricing Analysis
Cost-plus contracts with CMS wage index adjustments dominate reimbursement structures, tying per-diem rates to local labor market conditions. Price differentiation stems from Five-Star quality ratings and memory care specialization, with private-pay dementia units commanding premiums above Medicaid benchmarks. Pricing pressure intensifies in competitive Certificate-of-Need-exempt markets where new bed supply expands rapidly. Medicaid-dependent long-term care segments exhibit highest price sensitivity, while post-acute rehabilitation units with hospital system integration maintain rate resilience.
Supply Chain Analysis
Inventory lead times for licensed nursing staff stretch 90-180 days in competitive labor markets, forcing reliance on agency staffing at 40-60% cost premiums. Labor supply concentrates domestically with limited immigration visa throughput, while medical equipment and pharmaceutical inputs draw from domestic distributors and regional GPO contracts. Single-source vulnerability sits with specialized wound care and bariatric equipment suppliers. Distribution runs through national group purchasing organizations and direct manufacturer agreements to facility-level receiving.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Market fragmentation creates acquisition opportunities as reimbursement compression and compliance cost escalation force distressed asset sales, particularly among independent operators lacking hospital system integration.
For Market Incumbents: Fortify margin position through backward integration into telehealth physician coverage and remote patient monitoring infrastructure. Absorb CMS staffing mandate costs via multi-state scale while divesting underperforming assets in Certificate-of-Need-constrained markets where competitive entry pressure remains muted. For New Entrants and Emerging Players: Rural hospital conversion gaps present white-space entry points, particularly in Appalachian and Great Plains regions where state rural health incentives offset capital requirements. Target Medicare ACO partnership formation as the primary go-to-market channel, positioning transitional care management services for hospital-at-home discharge patients. For Investors and Strategic Acquirers: The market sits at a consolidation phase that favors regional specialists with hospital system integration over pure-scale consolidators. Long-term viability hinges on value-based care alignment and bundled payment participation. Monitor CMS proposed rulemaking on minimum nurse staffing ratios as the critical inflection signal for labor automation investment timing.| Strategic Initiative | Industry Significance |
|---|---|
| Medicare ACO Partnership Formation | Captures shared savings upside and secures preferred provider status with hospital discharge networks. |
| Memory Care Unit Specialization | Commands staffing-adjusted rate premiums from private-pay families seeking secure-environment dementia services. |
| Rural Hospital Conversion | Repurposes underutilized acute care infrastructure with state rural health incentive offsetting capital requirements. |
| Telehealth Infrastructure Deployment | Reduces emergency department transfers via 24/7 specialist consultation coverage across geographically dispersed properties. |
| Remote Patient Monitoring Integration | CMS quality metrics reward continuous glucose and cardiac monitoring with reduced readmission penalties. |
Research Approach
Initial hypotheses were tested against primary input from skilled nursing facility administrators, hospital discharge planners, state Medicaid agency officials, and CMS policy specialists and refined through secondary validation against CMS Medicare cost reports, state Certificate-of-Need filings, and American Health Care Association operational benchmarks. Bottom-up facility-level capacity and utilization data triangulated with top-down reimbursement flow analysis.
Variance decomposition across service type, facility ownership structure, patient demographic, and payment model segmentation dimensions anchored the analytical framework. CAGRs derived from historical bed supply expansion, surgical volume growth, and Medicaid enrollment trends. Forecast inputs incorporated CMS Five-Star Quality Rating System reform timelines and Medicare Advantage penetration trajectories.
Forecasts assume regulatory continuity in CMS reimbursement methodologies and state Medicaid program structures; material policy shifts would require re-modeling. Outputs are directional rather than point-estimates.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Healthcare Facilities
Trauma Care Centers Market
Healthcare Facilities
US Hospital Facilities Market
Healthcare Facilities
Confinement Center Market
Healthcare Facilities
Mobile Hospitals Market
Healthcare Facilities
Micro-Hospitals Market
Healthcare Facilities
US and Europe Ambulatory Surgery Centers Market
Healthcare Facilities
Bedless Hospitals Market
Healthcare Facilities
US Assisted Living Facility Market
Healthcare Facilities
Asia-Pacific Smart Hospital Market
Healthcare Facilities
US Ambulatory Surgery Centers Market
Healthcare Facilities
Private Office-Based Clinics Market
Healthcare Facilities
Global Healthcare Architecture Market
Healthcare Facilities
Global Healthcare Facilities Management Market
Healthcare Facilities
Ambulatory Surgical Centers Market
Healthcare Facilities
Longevity Clinic Chain Infrastructure Market
Healthcare Facilities
US Skilled Nursing Facility and Rehabilitation Market