
 US Post-Acute Care (PAC) Market | 2026-2036
US Post-Acute Care (PAC) Market Size, Share, and Industry Trends Forecast 2026-2036
US Post-Acute Care (PAC) Market Analytics
Skilled nursing labor shortages are reorganizing how operators staff facilities and manage length-of-stay targets. Amedisys leverages home-based clinical networks to extend care beyond institutional walls. Kindred Healthcare anchors long-term acute care capacity in urban hospital corridors. Encompass Health differentiates through inpatient rehabilitation facility specialization and joint-venture structures with acute-care systems.
Post-acute care encompasses coordinated medical and rehabilitative services delivered after acute hospitalization, encompassing skilled nursing, home health, inpatient rehabilitation, and long-term acute care designed to restore functional independence or manage chronic conditions. Service type segmentation reveals skilled nursing facilities retaining the largest revenue footprint while home health care captures the fastest enrollment growth as Medicare Advantage plans steer patients toward lower-cost settings. Payment model dynamics show fee-for-service still dominating transaction volume though value-based care and bundled payments are concentrating margin pools around outcomes accountability.
CMS, the Department of Health and Human Services, and state Medicaid agencies shape market access through reimbursement rates, quality star ratings, and certificate-of-need regulations that limit facility expansion in certain jurisdictions. Medicare Advantage plan growth alters referral patterns and prior authorization requirements, forcing providers to reconfigure intake workflows and data reporting capabilities. Stakeholders must monitor how CMS innovation center demonstrations recalibrate risk-sharing obligations between hospitals and post-acute partners.
Market Dynamics
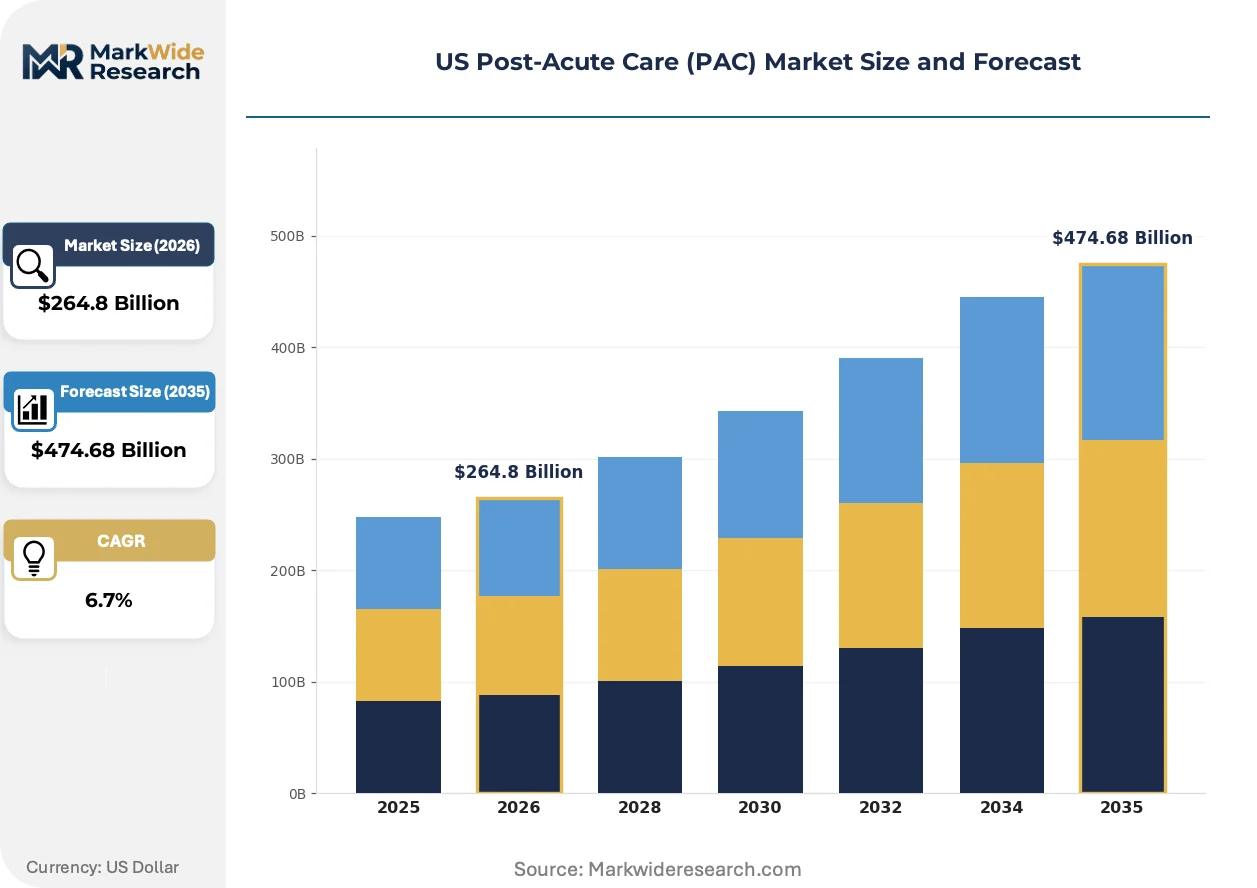
CMS reimbursement compression is forcing post-acute operators to reengineer cost structures around shorter length-of-stay targets and lower-acuity site migration. Medicare Advantage penetration above 50% in Florida and Texas is redirecting patient flows away from institutional skilled nursing toward home-based alternatives.
Growth Catalysts
- Medicare Advantage expansion:Plan enrollment growth in Sun Belt states is creating volume guarantees for home health agencies willing to accept capitated risk contracts.
- Hospital-at-home waivers:CMS Acute Hospital Care at Home program is extending reimbursement to home-based skilled nursing equivalents, enabling infrastructure investment in remote monitoring.
- SNF value-based purchasing:The CMS Skilled Nursing Facility Value-Based Purchasing Program ties Medicare reimbursement to hospital readmission rates, rewarding operators with integrated care coordination.
Market Restraints
- Certificate-of-need statutes:Thirty-five states and the District of Columbia maintain CON laws that block new skilled nursing facility construction in saturated markets, entrenching incumbents.
- Licensed practical nurse scarcity:Workforce pipeline constraints in rural Texas and Florida counties are capping bed expansion regardless of capital availability.
- Medicaid rate stagnation:State fiscal pressures in Illinois and New York have frozen reimbursement rates below operating costs for dual-eligible populations.
Strategic Opportunities
- Rural hospital partnerships:Critical access hospitals in the Upper Midwest lack post-acute capacity, creating joint-venture openings for rehabilitation specialists.
- Remote patient monitoring convergence:Integration of FDA-cleared biometric wearables with EHR systems is enabling 24-hour oversight without bedside staffing.
- SNFist model expansion:Physician groups employing dedicated post-acute hospitalists are capturing Medicare Advantage attribution in California and Arizona markets.
Industry Challenges
- Interoperability fragmentation:HL7 FHIR implementation gaps between acute EHRs and post-acute point-of-care systems are blocking real-time care transition data exchange.
- Prior authorization complexity:Medicare Advantage plans' disparate documentation requirements are extending admission delays and compressing effective length-of-stay.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | US Post-Acute Care (PAC) Market |
| Market Size in 2026 | $264.8 Billion |
| Market Size in 2035 | $474.68 Billion |
| CAGR (2026 – 2036) | 6.7% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: Skilled Nursing Facility, Home Health Care, Rehabilitation Center, Long-Term Acute Care Hospital Payment Model: Fee-for-Service, Capitation, Bundled Payments, Value-Based Care Care Setting: Inpatient, Outpatient, Home-Based, Transitional Patient Type: Elderly, Post-Surgical, Chronic Illness, Palliative Care |
| Companies Covered | Kindred Healthcare, Amedisys, Ensign Group, Select Medical, Encompass Health, Brookdale Senior Living, LHC Group, HCR ManorCare, Genesis HealthCare, Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
US Post-Acute Care (PAC) Market Evolving Landscape
Telehealth-enabled remote therapeutic monitoring is compressing the physical footprint required for skilled intervention. Regulatory pressure on hospital readmissions is accelerating investment in predictive analytics for discharge planning.
Remote patient monitoring platforms with FDA-cleared pulse oximetry and blood pressure telemetry are displacing routine in-person nursing assessments for stable post-surgical patients. Medicare Advantage plans in Florida are embedding these devices in standard home health benefit packages. The technology is displacing traditional 60-day episode visit schedules with as-needed response protocols.
CMS mandatory skilled nursing facility staffing minimums are compressing operating margins for facilities below 100 beds. The rule requires 3.48 nursing hours per resident day and 0.55 registered nurse hours per resident day starting in fiscal year 2026. Rural operators in Mississippi and Alabama are consolidating through management contracts to achieve scale compliance.
Patient preference for aging-in-place is redirecting elective joint replacement recovery toward home health settings. Hospital outpatient departments in Texas are embedding home health referrals into pre-surgical counseling workflows. California Medicare Advantage beneficiaries now select home recovery at rates exceeding institutional rehabilitation for uncomplicated hip and knee procedures.
US Post-Acute Care (PAC) Market Segmentation
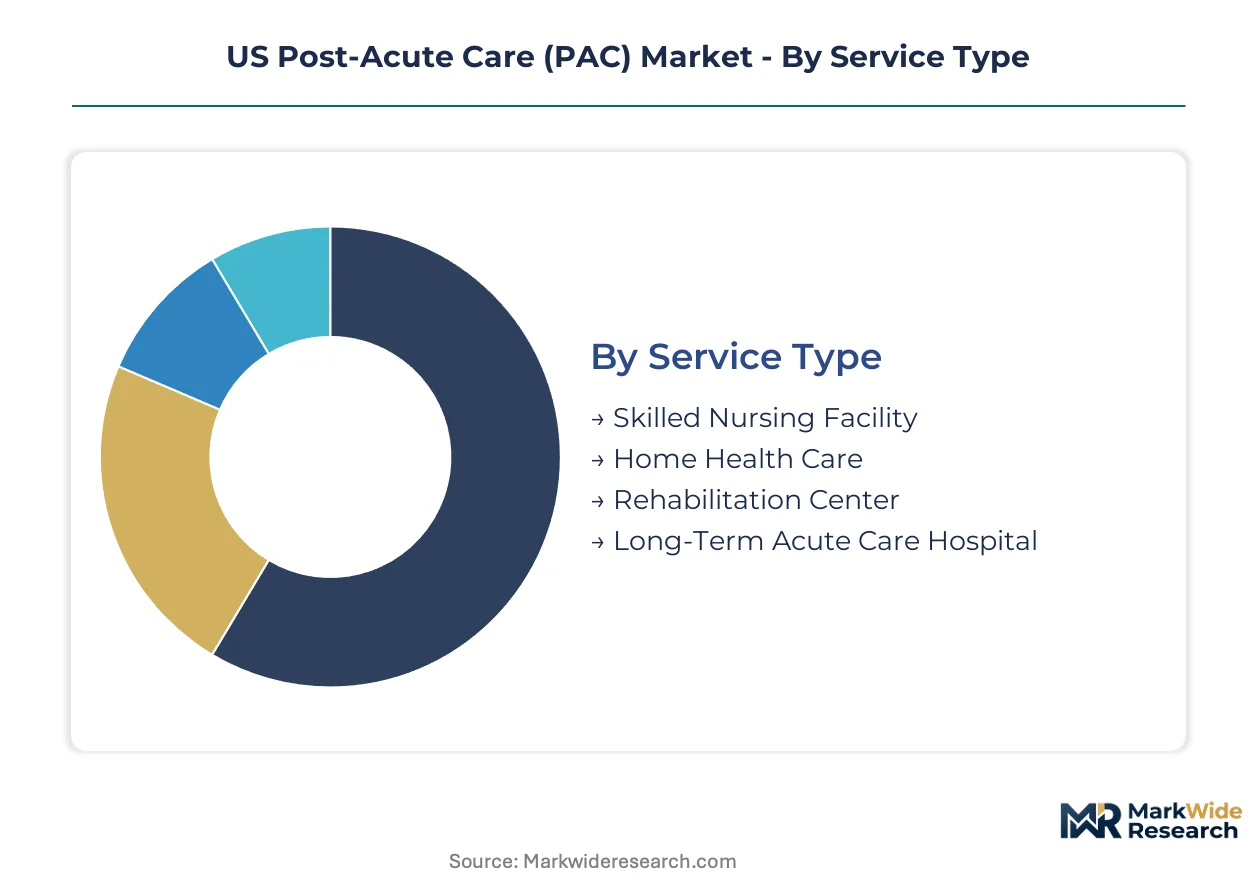
Post-acute care segmentation reveals how capital allocation, regulatory pressure, and patient preference are redistributing volume across institutional and community-based settings. Understanding these divides exposes where Medicare Advantage plans are steering attribution and where fee-for-service legacy structures still dominate reimbursement.
Service Type:
Geographic demand patterns split sharply between facility-based services concentrated in Medicare-dense Sun Belt metros and home-based alternatives penetrating rural counties previously dependent on institutional discharge.
- Skilled Nursing Facility:Institutional settings deliver 24-hour nursing supervision, rehabilitation therapy, and medical management for complex post-hospital recovery. Demand clusters in Florida retirement corridors and Texas urban hospital referral zones where dual-eligible populations require extended custodial support. CMS staffing minimums are compressing margins for sub-scale operators in Mississippi and Alabama, accelerating consolidation.
- Home Health Care:Clinical services delivered in patient residences encompass skilled nursing, physical therapy, and medication management through episodic or ongoing models. California and Arizona Medicare Advantage markets are driving fastest enrollment growth as capitated plans substitute home visits for institutional days. Remote patient monitoring integration is displacing routine in-person assessments for stable post-surgical cohorts.
- Rehabilitation Center:Inpatient rehabilitation facilities specialize in intensive therapy protocols for stroke, trauma, and orthopedic recovery.
- Long-Term Acute Care Hospital:Extended-stay hospitals manage ventilator-dependent and complex wound patients requiring sub-acute medical oversight.
Skilled nursing facilities command the established base. The steepest expansion runs through home health care.
Payment Model:
Reimbursement architecture determines margin stability, with legacy fee-for-service yielding predictable per-diem revenue while risk-bearing models demand capital reserves and predictive analytics infrastructure.
- Fee-for-Service:Traditional Medicare reimbursement pays per procedure, day, or visit without outcome accountability. Rural Texas and Florida operators still rely on this structure for census stability, though volume is eroding as Medicare Advantage penetration crosses 50% in key counties.
- Value-Based Care:Outcome-linked reimbursement ties payment to readmission rates, functional improvement, and patient experience scores. The CMS Skilled Nursing Facility Value-Based Purchasing Program rewards integrated care coordination, favoring operators with hospital joint ventures and robust discharge planning protocols.
- Capitation:Fixed per-member-per-month payments transfer utilization risk to providers.
- Bundled Payments:Single prospective payments for acute-plus-post-acute episodes concentrate accountability on hospital-PAC partnerships.
Fee-for-service retains transactional volume dominance. Value-based contracting is gaining share fastest among multi-site operators with data infrastructure.
Care Setting:
Site-of-service migration reflects both regulatory waiver expansion and patient preference for reduced institutional exposure during recovery.
- Home-Based:Care delivery in private residences leverages telehealth, remote monitoring, and intermittent clinical visits. The CMS Acute Hospital Care at Home program is extending reimbursement to skilled nursing equivalents in patient homes, enabling infrastructure investment in biometric telemetry and 24-hour virtual oversight.
- Inpatient:Facility-based recovery remains essential for high-acuity patients requiring continuous nursing and therapy intensity.
- Outpatient:Day rehabilitation and clinic-based therapy serve ambulatory patients with transportation access.
- Transitional:Short-stay bridge programs coordinate handoffs between acute discharge and definitive post-acute placement.
Inpatient settings anchor high-acuity revenue. Home-based delivery is climbing the fastest as waiver programs and Medicare Advantage steer lower-complexity volume communityward.
Patient Type:
Clinical acuity and demographic profile determine site selection, reimbursement tier, and length-of-service intensity across the post-acute continuum.
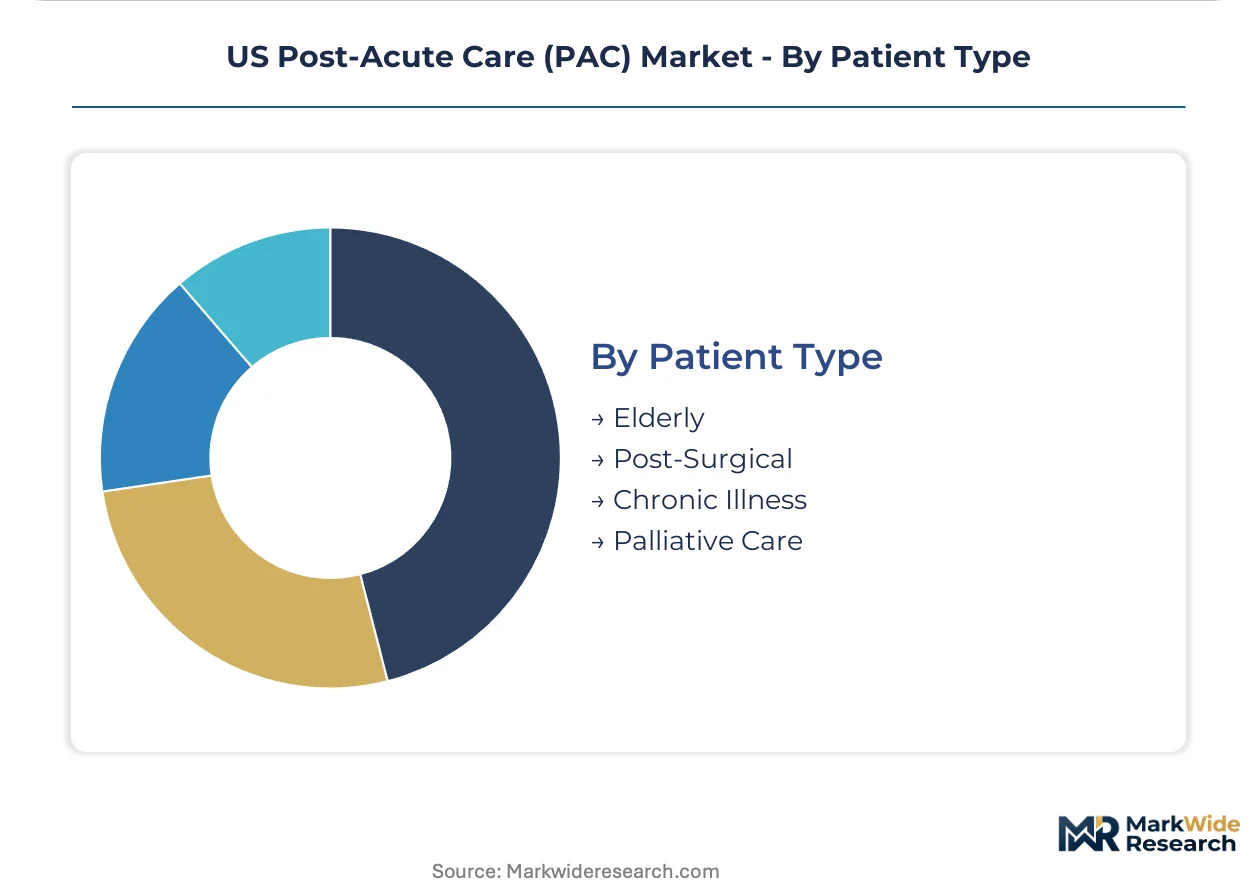
- Elderly:Medicare beneficiaries over 65 constitute the core post-acute census, with age-related functional decline driving demand for both restorative rehabilitation and chronic disease management. Florida and Arizona retirement in-migration concentrates volume in markets with established Medicare Advantage networks.
- Post-Surgical:Joint replacement and cardiac procedure recovery is migrating rapidly to home health in California and Texas as ambulatory surgery expansion reduces institutional length-of-stay.
- Chronic Illness:Congestive heart failure, COPD, and diabetes management requires ongoing skilled intervention.
- Palliative Care:Symptom-focused support for serious illness addresses quality-of-life goals alongside curative treatment.
Elderly populations command the established base. Post-surgical segments are expanding most quickly through home-based recovery protocols.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Florida commands premium pricing power through Medicare Advantage density while rural Mississippi operators absorb CMS staffing rule compression. Texas and California split volume leadership between institutional and home-based channels.
Florida
Medicare Advantage penetration exceeding 50% in Miami-Dade and Broward counties concentrates attributed lives under capitated contracts. CMS Hospital-at-Home waivers enable home health agencies to substitute for skilled nursing days. The Tampa-St. Petersburg corridor anchors joint-venture partnerships between hospital systems and rehabilitation specialists.
Texas
Dual-eligible expansion in Harris and Dallas counties drives skilled nursing demand for extended custodial support. State Medicaid managed care contracts impose prior authorization layers that delay post-acute placement. San Antonio and Austin metro clusters concentrate home health agency investment in remote patient monitoring infrastructure.
California
Medicare Advantage attribution wars between Kaiser Permanente and Blue Shield of California reshape referral network loyalty. Department of Health Care Services Medi-Cal rate adjustments lag operating cost inflation for dual-eligible populations. The Los Angeles-Orange County basin hosts the densest concentration of SNFist physician groups capturing post-acute attribution.
Illinois
Medicaid rate stagnation under state fiscal pressure compresses margins for Chicago-area skilled nursing operators serving dual-eligibles. Certificate-of-need restrictions block new facility construction in Cook County saturated markets. Peoria and Rockford rural hospital partnerships create joint-venture openings for rehabilitation capacity expansion.
Arizona
Retirement in-migration to Maricopa and Pima counties expands Medicare Advantage enrollment faster than national benchmarks. Arizona Health Care Cost Containment System managed care procurement favors home-based alternatives over institutional placement. The Phoenix-Mesa corridor concentrates investment in telehealth-enabled remote therapeutic monitoring platforms.
US Post-Acute Care (PAC) Market Competitive Landscape
Technology leadership and cost leadership are held by different player archetypes across the post-acute continuum. National multi-site operators with hospital joint ventures capture value-based contract share while regional chains defend fee-for-service volume in rural markets. Three archetypes dominate: integrated health system partners, scale-driven national platforms, and sub-scale rural consolidators. Competitive moves concentrate on Medicare Advantage network exclusivity negotiations and remote monitoring infrastructure deployment.
Within the integrated health system tier, Encompass Health and Select Medical exemplify joint-venture structures with acute-care hospitals. Amedisys occupies a position representing home-based clinical network expansion beyond institutional walls. These three names anchor the competitive map without exhausting its structure.
| Leading Market Players |
|---|
| Kindred Healthcare |
| Amedisys |
| Ensign Group |
| Select Medical |
| Encompass Health |
| Brookdale Senior Living |
| LHC Group |
| HCR ManorCare |
| Genesis HealthCare |
| Others |
Value Network & Pricing Analysis
Bed-scale economics above 100 licensed beds anchor both cost absorption capacity and rate negotiation leverage against Medicare Advantage plans. CMS staffing minimums effective fiscal year 2026 compress margin floors for sub-scale operators, concentrating supply-side viability among multi-site platforms with centralized clinical staffing pools.
Pricing Analysis
Configured-to-order pricing for bundled episodes commands premium spreads against standard per-diem fee-for-service rates. Three-tier pricing structure across premium joint-venture facilities, standard community-based skilled nursing, and economy rural Medicaid-dependent operators reflects quality star ratings and hospital affiliation density. Pricing pressure stems from Medicare Advantage capitation rates falling below traditional Medicare fee schedules, squeezing operators lacking scale economies. Medicaid-dependent rural facilities exhibit highest price sensitivity; hospital-affiliated rehabilitation joint ventures demonstrate lowest sensitivity due to guaranteed referral flows.
Supply Chain Analysis
Licensed practical nurse pipeline constraints in rural Texas and Florida counties choke capacity expansion regardless of capital availability. Clinical labor supply draws from community college programs in Mississippi, Alabama, and Georgia, while remote patient monitoring hardware sources from domestic FDA-cleared device manufacturers. Single-source vulnerability concentrates in specialized therapy staffing agencies serving multiple competing operators. Distribution runs through regional GPO contracts aggregating medical supplies and pharmaceutical purchasing for multi-site operators.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
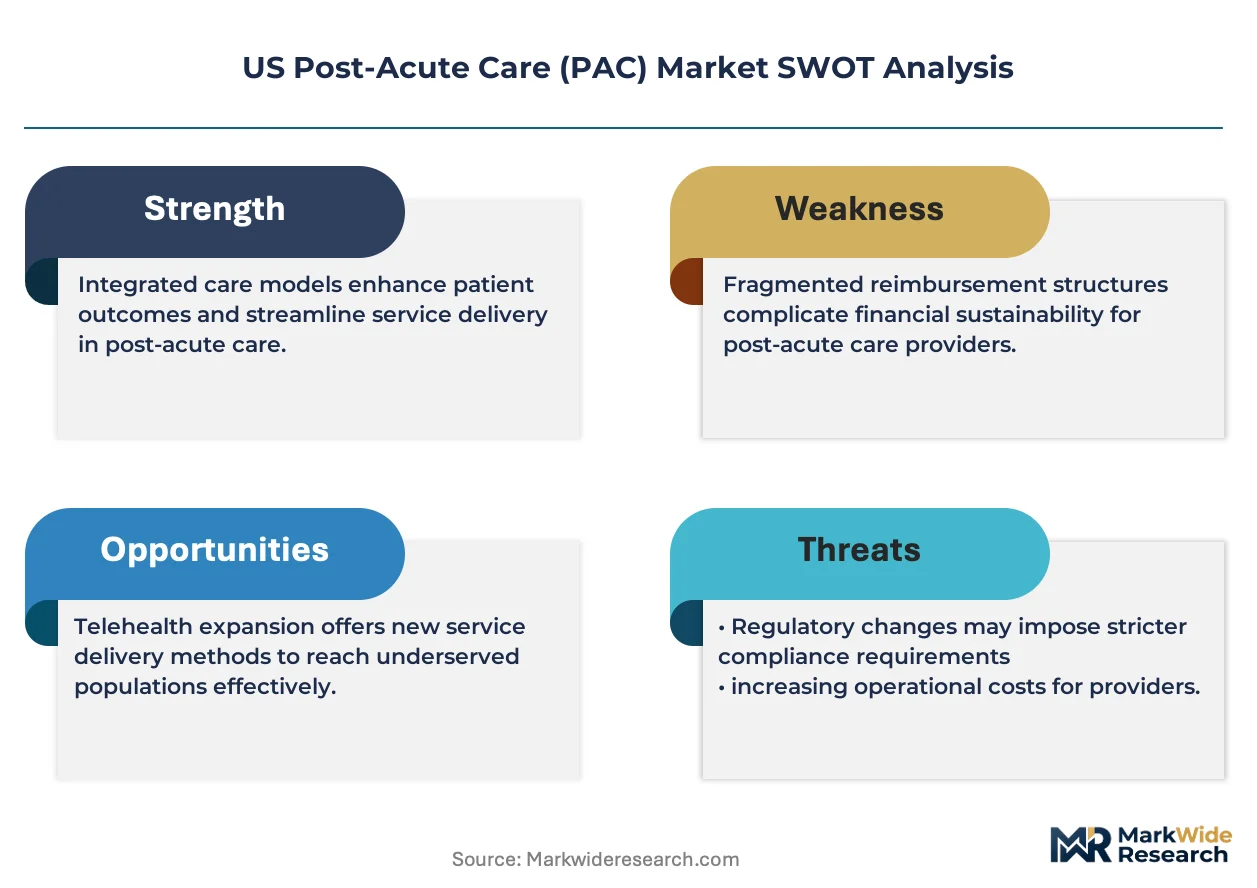
Fragmentation across state-level Medicaid managed care procurement and Medicare Advantage network exclusivity creates niche entry points for specialized operators. Site-of-service migration toward home-based recovery splinters volume across non-traditional competitors lacking legacy facility overhead.
For Market Incumbents: Compound scale advantages through management contract consolidation of sub-100-bed rural facilities facing CMS staffing rule compliance costs. Acquire remote patient monitoring platforms to substitute technology for bedside nursing hours. Defend against hospital-at-home waiver expansion by embedding virtual oversight capabilities into existing home health infrastructure. For New Entrants and Emerging Players: Differentiate on SNFist physician group attribution models capturing Medicare Advantage primary care relationships in California and Arizona markets. Target rural hospital partnership gaps in Upper Midwest critical access corridors lacking post-acute capacity. Penetrate through joint-venture structures offering rehabilitation expertise without competing for CON-restricted facility licenses. For Investors and Strategic Acquirers: Mid-cycle technology positioning favors platforms with deployed remote monitoring infrastructure and hospital system joint-venture density over pure-play facility owners. Long-term viability rests on capitated contract share and data integration capabilities bridging acute-to-post-acute transitions. Watch Medicare Advantage penetration rates in Sun Belt retirement corridors as inflection indicators for volume guarantee negotiations.| Strategic Initiative | Industry Significance |
|---|---|
| Remote Patient Monitoring Deployment | FDA-cleared biometric telemetry enables 24-hour virtual oversight without bedside staffing escalation. |
| Hospital Joint Venture Formation | Integrated care coordination secures value-based purchasing bonuses under CMS SNF VBP programs. |
| SNFist Physician Group Acquisition | Dedicated post-acute hospitalists capture Medicare Advantage attribution in California attribution wars. |
| Rural Facility Consolidation | Management contracts achieve CMS staffing minimum compliance through centralized clinical staffing pools. |
| Home Health Infrastructure Buildout | Hospital-at-Home waiver reimbursement extends skilled nursing equivalents into patient residences. |
Research Methodology
Findings reconcile primary fieldwork against secondary review of CMS Medicare cost reports, state Medicaid rate filings, and Medicare Advantage plan landscape files. Interviews with skilled nursing facility operators, home health agency executives, hospital system post-acute directors, and Medicare Advantage network contracting managers informed demand-side dynamics. Secondary validation drew from CMS Nursing Home Compare star ratings, state certificate-of-need databases, and Medicare Advantage penetration trackers. Bottom-up facility census modeling triangulated against top-down payment flow analysis across fee-for-service and capitated channels.
Segmentation dimensions modeled span service type, payment model, care setting, and patient acuity tier across the projection horizon. CAGRs derive from trend extrapolation of Medicare Advantage enrollment shifts, CMS innovation center demonstration expansions, and site-of-service migration patterns. Forecast inputs incorporate state-level CON restriction indices and remote patient monitoring adoption curves by metropolitan statistical area.
Material uncertainties — CMS staffing rule implementation delays, Medicare Advantage rate reset negotiations, and state Medicaid fiscal stress — sit outside the modeled envelope. Forecasts reflect assumptions on capitated contract penetration and technology substitution timelines. Practitioners should keep alternative scenarios live as Medicare Advantage network exclusivity terms and hospital-at-home waiver permanence evolve.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Healthcare Services
Global Funeral Homes and Funeral Services Market
Healthcare Services
Global Sperm Bank Market
Healthcare Services
Healthcare CMO Market
Healthcare Services
Canada Senior Living Market
Healthcare Services
US Registered Nurses Market
Healthcare Services
Global Umbilical Cord Blood Banking Market
Healthcare Services
Healthcare CRO Services Market
Healthcare Services
Europe Medical Affairs Outsourcing Market
Healthcare Services
Hospital Outsourcing Market
Healthcare Services
US Care Services Market
Healthcare Services
Healthcare Patent Filing Outsourcing Market
Healthcare Services
India Senior Living Market
Healthcare Services
Global Medical Affairs Outsourcing Market
Healthcare Services
UK Pharmaceutical Logistics Market
Healthcare Services
Inhaled and Intranasal Products Contract Service Providers Market
Healthcare Services
Surgical Fluid Disposal Market