
 US Mental Health and Addiction Treatment Centers Market | 2026-2036
US Mental Health and Addiction Treatment Centers Market Size, Share, and Industry Trends Forecast 2026-2036
US Mental Health and Addiction Treatment Centers Market Insights
Telehealth platform integration is reshaping how mental health and addiction treatment centers deliver continuous care beyond facility walls. Bridges to Recovery leverages its residential specialization to sustain premium inpatient positioning in high-acuity cases. Lindner Center of HOPE anchors a regional hub model that competes on integrated psychiatric and addiction services. Elevate Addiction Services differentiates through destination residential programs that control geographic isolation as a therapeutic variable.
US mental health and addiction treatment centers constitute licensed medical and therapeutic facilities providing structured interventions for psychiatric disorders and substance use conditions, typically operating under Joint Commission accreditation standards with clinical staffing ratios governed by state health departments. These centers function primarily to reduce acute crisis episodes, stabilize medication regimens, and transition patients toward community-based maintenance. Outpatient services now lead volume flows as teletherapy infrastructure matures, while partial hospitalization captures margin pools from patients requiring intensive monitoring without overnight admission. Inpatient capacity remains concentrated in private and non-profit facility types where length-of-stay economics favor severe diagnostic categories.
FDA oversight of digital therapeutics and HIPAA privacy frameworks shape how treatment centers adopt remote monitoring tools and patient data architectures. CMS reimbursement rules and state-level Medicaid agency waivers directly determine teletherapy eligibility and facility payment rates. State health departments enforce licensure standards that gate market entry for new operators. Stakeholders must track evolving FDA digital health guidance and CMS telehealth reimbursement permanence decisions to calibrate capital allocation between virtual and brick-and-mortar capacity.
Market Dynamics
Telehealth parity rules and CMS reimbursement permanence decisions are compressing the boundary between facility-based and virtual care delivery, forcing capital reallocation toward hybrid infrastructure.
Growth Catalysts
- Medicaid Expansion Pressure:California, Texas, and Florida face dual demand surges from uninsured populations and newly eligible beneficiaries, expanding addressable patient pools for licensed operators.
- 21st Century Cures Act:Federal interoperability mandates accelerate electronic health record integration across psychiatric and addiction treatment workflows.
- Employer Behavioral Health Mandates:Large self-insured employers now require comprehensive mental health parity in network contracts, pulling volume toward accredited residential programs.
Market Restraints
- Workforce Supply Bottleneck:Psychiatrist and licensed clinical social worker shortages concentrate in rural Texas and Florida counties, capping bed expansion regardless of capital availability.
- Brick-and-Mortar Capex Intensity:Joint Commission accreditation requires physical facility standards that telehealth infrastructure cannot satisfy, trapping capital in depreciating real estate.
- State Licensure Fragmentation:No reciprocity across California, Texas, and Florida state health departments forces redundant compliance spend for multi-state operators.
Strategic Opportunities
- Partial Hospitalization Penetration:Medicare Advantage plans in Florida and Texas now reimburse intensive outpatient programs at rates approaching inpatient levels, opening margin pools without overnight staffing costs.
- Digital Therapeutics Integration:FDA-cleared prescription digital therapeutics for substance use disorder can extend reach beyond facility walls into employer and payer direct contracts.
- Destination Residential Positioning:Geographic isolation as a therapeutic variable attracts self-pay patients from coastal urban markets to lower-cost Mountain West and Southwest facilities.
Industry Challenges
- Credentialing Timeline Compression:Joint Commission and state health department survey cycles now lag technology deployment, creating compliance gaps for hybrid care models.
- EHR Interoperability Debt:Legacy psychiatric record systems lack FHIR-compliant APIs, forcing manual data bridges that violate HIPAA technical safeguards.
- Clinical Workforce Burnout:High-acuity residential programs in California face annual staff turnover exceeding 40%, destabilizing continuity of care metrics.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | US Mental Health and Addiction Treatment Centers Market |
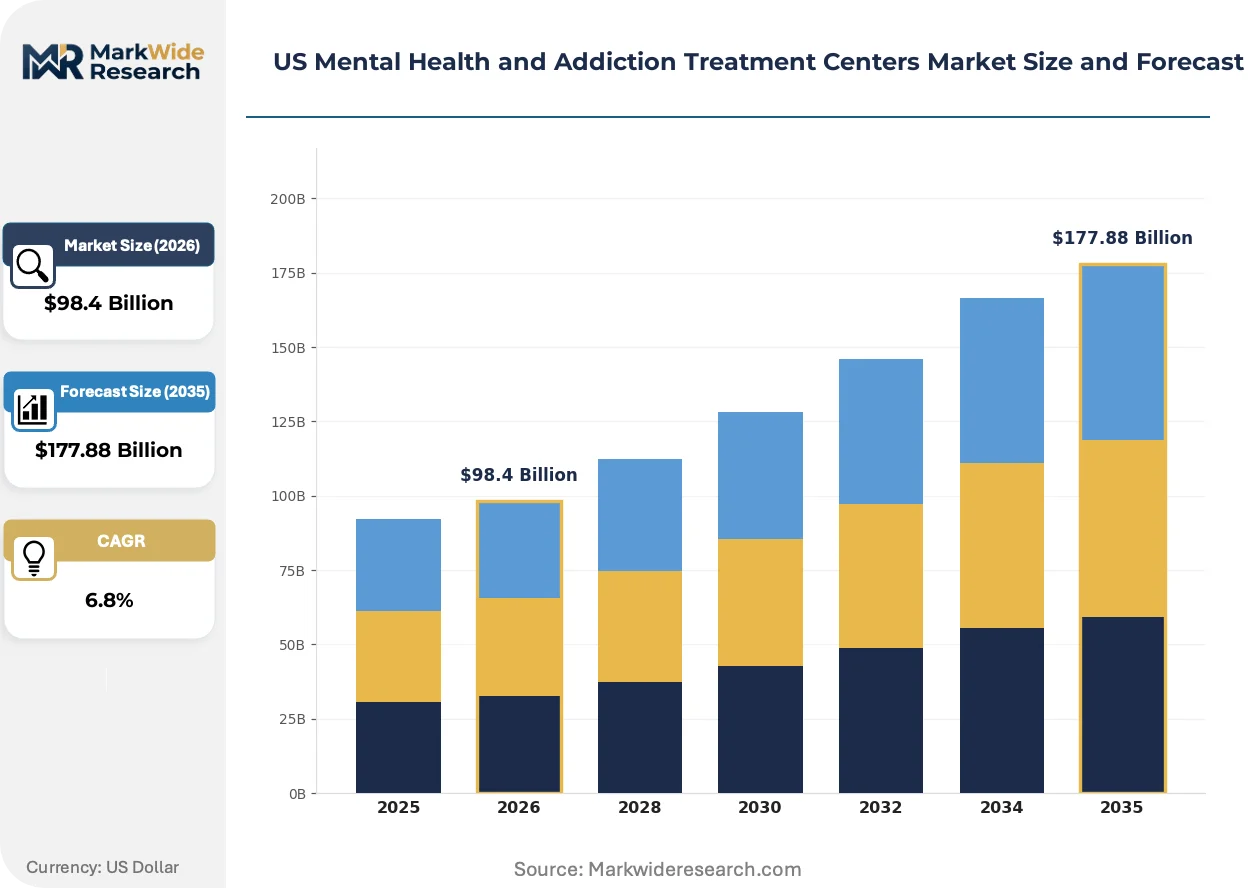
| Market Size in 2026 | $98.4 Billion |
| Market Size in 2035 | $177.88 Billion |
| CAGR (2026 – 2036) | 6.8% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Treatment Type: Inpatient, Outpatient, Teletherapy, Partial Hospitalization Service Offering: Counseling, Medication Management, Detoxification, Group Therapy Target Population: Adults, Adolescents, Veterans, Substance Users Facility Type: Private, Non-Profit, Public, Specialty Clinics |
| Companies Covered | Bridges to Recovery, Lindner Center of HOPE, Amend Treatment, Elevate Addiction Services, Ashley Addiction Treatment, The Menninger Clinic, Austen Riggs Center, UF Health Florida Recovery Center, Skyland Trail, Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
US Mental Health and Addiction Treatment Centers Market Trends and Innovations
Virtual care infrastructure is collapsing the traditional separation between acute stabilization and longitudinal maintenance, forcing treatment centers to rearchitect staffing and facility footprints around continuous rather than episodic engagement.
Remote patient monitoring platforms with biometric feedback loops are collapsing the distinction between inpatient observation and home-based recovery. Medicare Advantage plans in Florida and Texas now contract directly with residential operators for post-discharge monitoring bundles. This compression enables shorter length-of-stay economics while capturing per-member-per-month revenue streams previously lost to community providers.
CMS telehealth reimbursement permanence rules are solidifying virtual psychiatric evaluation as a standard of care. State Medicaid agencies in California and Texas must now align prior authorization requirements with federal parity standards. Rural counties without psychiatrist density are responding by licensing telehealth-only providers that bypass traditional facility accreditation entirely.
Self-insured employers are unbundling behavioral health from general medical networks and contracting directly with residential treatment centers for carve-out programs. This disintermediation bypasses health plan administrative layers and redirects volume toward facilities with proven outcomes data. The shift is most visible in Texas energy sector employers and California technology firms with concentrated employee populations.
US Mental Health and Addiction Treatment Centers Market Segmentation
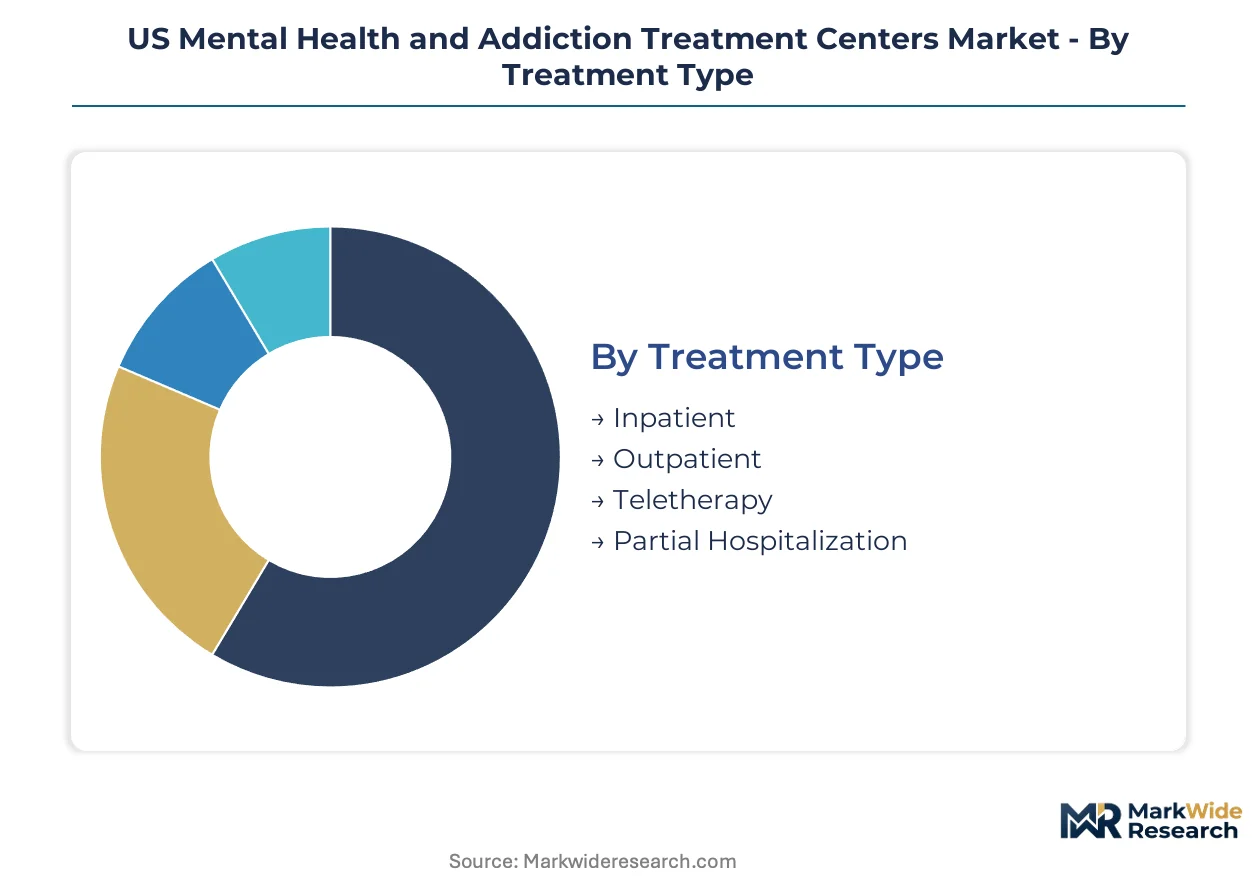
Segmentation in the US mental health and addiction treatment centers market reveals how reimbursement rules, clinical acuity, and facility economics partition patient flows across distinct operational models. Each dimension captures a different axis of competitive positioning—from care intensity to payer mix to licensure requirements.
Treatment Type:
The use-case spectrum spans crisis stabilization through longitudinal maintenance, with each modality carrying distinct capital intensity and margin profiles.
- Inpatient:Residential facilities provide 24-hour medical supervision and structured therapeutic programming for severe psychiatric episodes or acute withdrawal. California and Texas operators concentrate bed capacity here to capture commercial insurance reimbursement for high-acuity diagnoses requiring Joint Commission-accredited physical infrastructure.
- Outpatient:Clinic-based services deliver scheduled therapy sessions and medication management without overnight stays. Florida Medicaid expansion has concentrated volume growth in this segment as newly eligible beneficiaries access community-based care that avoids prior authorization barriers common to residential admission.
- Teletherapy:HIPAA-compliant video platforms connect licensed clinicians to patients in their homes. CMS telehealth parity rules have normalized reimbursement parity with in-person visits for psychiatric evaluation.
- Partial Hospitalization:Day programs provide intensive clinical programming—typically 4-6 hours daily—without residential overhead. Medicare Advantage plans in Texas now reimburse these programs at rates approaching inpatient levels.
Established volume favors Inpatient; emerging adoption favors Teletherapy.
Service Offering:
Margin concentration follows the clinical labor intensity and regulatory oversight burden attached to each intervention type.
- Counseling:Individual and family psychotherapy sessions delivered by licensed clinical social workers and psychologists. California's Kaiser Permanente and other integrated systems have concentrated demand for brief evidence-based protocols.
- Medication Management:Psychiatric evaluation and prescription monitoring for mood disorders, psychosis, and addiction pharmacotherapy. Psychiatrist shortages in rural Texas and Florida counties constrain capacity expansion regardless of patient demand.
- Detoxification:Medically supervised withdrawal management for alcohol, opioids, and benzodiazepines with 24-hour nursing coverage. Florida's large uninsured population and Medicaid expansion create dual pressure on publicly funded detox capacity.
- Group Therapy:Facilitated peer sessions addressing substance use, trauma, and co-occurring disorders. Lower labor costs per patient-hour enable margin capture in high-volume community mental health settings.
Reimbursement stability favors Medication Management; volume expansion favors Group Therapy.
Target Population:
Payer mix and clinical complexity vary sharply across demographic segments, shaping facility specialization and marketing investment.
- Adults:The core patient base for most licensed operators, spanning working-age individuals with commercial insurance, Medicaid, or Medicare coverage. Employer behavioral health mandates have concentrated commercial volume in accredited residential programs.
- Adolescents:Minors requiring specialized licensing, family involvement protocols, and educational coordination. California's state health department enforces stricter staffing ratios for adolescent beds than adult units.
- Veterans:Eligible patients accessing care through VA contracts or TRICARE networks. Texas hosts concentrated veteran populations that attract specialized PTSD and substance use programming.
- Substance Users:Patients with primary opioid, alcohol, or stimulant use disorders, often with co-occurring psychiatric conditions. SAMHSA block grants and state Medicaid waivers determine access intensity in Florida and California.
Commercial margin favors Adults; unmet need concentration favors Veterans.
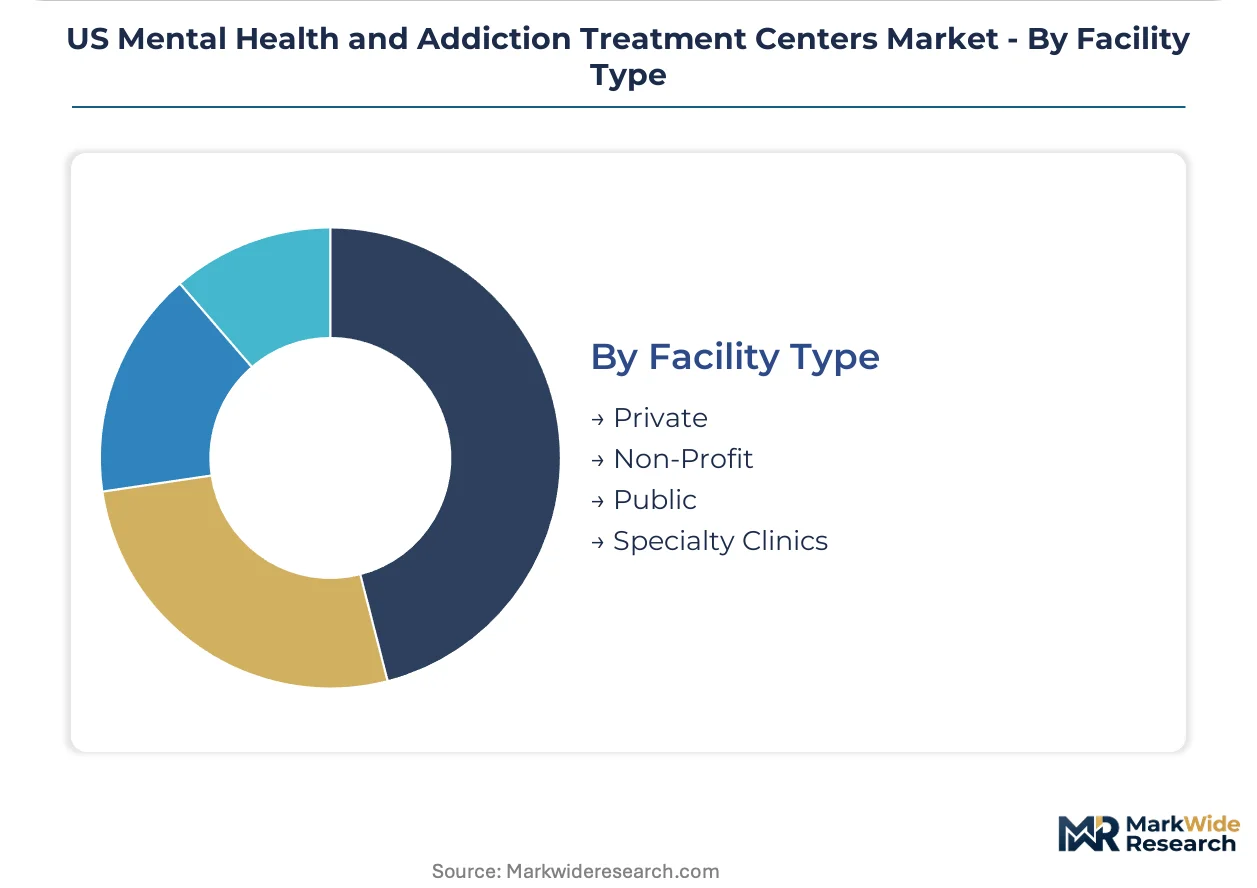
Facility Type:
Ownership structure determines capital access, mission constraints, and payer contract flexibility in ways that reshape competitive dynamics.
- Private:Investor-owned centers operating on margin targets with flexibility to decline Medicaid patients. Destination residential operators in the Mountain West and Southwest target self-pay patients from coastal urban markets.
- Non-Profit:Mission-driven organizations accepting charitable contributions and community benefit obligations. These facilities anchor safety-net capacity in California counties with large uninsured populations.
- Public:State and county-operated facilities serving involuntary commitment and indigent patient populations. Texas state hospitals face chronic bed shortages that overflow to private contractors.
- Specialty Clinics:Narrow-focus operations—eating disorders, trauma, LGBTQ+ affirmative care—that differentiate through clinical reputation rather than scale. Florida's retiree concentration supports geriatric psychiatry specialty models.
Scale economics favor Private; community integration favors Non-Profit.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
California treatment centers export residential expertise to self-pay patients from Texas and Florida, while Medicaid expansion in those states creates reciprocal demand for outpatient capacity.
California
Silicon Valley employers and Kaiser Permanente drive commercial behavioral health volume. State health department staffing ratio mandates for adolescent beds exceed national norms. Los Angeles and San Francisco Bay Area clusters concentrate high-acuity residential capacity serving interstate self-pay migration.
Texas
Energy sector employers unbundle behavioral health from medical networks for direct residential contracts. State hospital bed shortages overflow to private operators through emergency procurement. Houston and Dallas-Fort Worth anchor the state's psychiatric and addiction treatment infrastructure.
Florida
Medicare Advantage retiree concentration and Medicaid expansion create dual payer pressure on capacity. SAMHSA block grants and state Medicaid waivers govern substance use program access. Miami and Tampa metropolitan areas concentrate both geriatric psychiatry and publicly funded detox capacity.
New York Metro
Integrated delivery systems and commercial insurance density support outpatient network scale. State parity enforcement exceeds federal minimums for behavioral health coverage. Manhattan and Westchester County clusters compete on academic medical center affiliation.
Pacific Northwest
Employer-sponsored wellness mandates and Medicaid managed care penetration shape demand. State health departments license telehealth-only providers bypassing facility accreditation. Seattle and Portland metropolitan areas pioneer remote patient monitoring integration with residential discharge planning.
US Mental Health and Addiction Treatment Centers Market Competitive Landscape
Channel-controlling players compete with product-specialist players across three structural tiers. Large integrated health systems and employer carve-out managers concentrate commercial volume through direct contracting. Mid-scale regional operators defend position through Joint Commission accreditation and geographic clustering. Boutique residential specialists capture self-pay margin through destination positioning and clinical reputation. Dominant competitive moves include strategic partnerships with Medicare Advantage plans and portfolio diversification into partial hospitalization programs.
Within the destination residential tier, Bridges to Recovery and Elevate Addiction Services exemplify geographic isolation as a therapeutic variable, anchoring premium self-pay positioning in lower-cost markets. Lindner Center of HOPE occupies a regional hub archetype competing on integrated psychiatric and addiction services. These three operators represent contrasting capital allocation strategies between facility-based intensity and virtual care extension.
| Leading Market Players |
|---|
| Bridges to Recovery |
| Lindner Center of HOPE |
| Amend Treatment |
| Elevate Addiction Services |
| Ashley Addiction Treatment |
| The Menninger Clinic |
| Austen Riggs Center |
| UF Health Florida Recovery Center |
| Skyland Trail |
| Others |
Pricing and Supply Chain Analysis
I-10 corridor freight costs from California distribution hubs to Texas and Florida treatment centers compress margin pools for residential operators while amplifying price differentiation between destination programs and metro-proximate facilities. Supply concentration among Joint Commission-accredited bed providers in California and Texas reinforces premium pricing power for high-acuity residential capacity, whereas Medicaid-dependent outpatient networks in Florida face procurement pressure from state reimbursement ceilings.
Pricing Analysis
Legacy telehealth platform pricing lags behind next-generation remote patient monitoring bundles that integrate biometric feedback loops, creating a technology-generation pricing gap that stratifies reimbursement rates across the analysis window. Three-tier pricing structure across premium destination residential, standard accredited inpatient, and economy outpatient levels reflects Joint Commission certification status and geographic isolation value. Pricing pressure stems from Medicare Advantage plan rate compression in Florida and Texas partial hospitalization segments. Self-pay patients in coastal California markets exhibit lowest price sensitivity, while Medicaid expansion beneficiaries in Florida drive volume at reimbursement-constrained tiers.
Supply Chain Analysis
Workforce supply bottlenecks between California, Texas, and Florida dominate operational risk as psychiatrist and licensed clinical social worker shortages concentrate in rural counties, constraining bed expansion regardless of capital deployment. Clinical labor sourcing draws from state-licensed training pipelines, interstate recruitment networks, and telehealth credentialing platforms that bypass geographic constraints. Single-source vulnerability in EHR interoperability debt forces manual data bridges that violate HIPAA technical safeguards. Distribution runs through direct employer carve-out contracts, Medicare Advantage plan networks, and state Medicaid managed care organizations that gate patient volume.
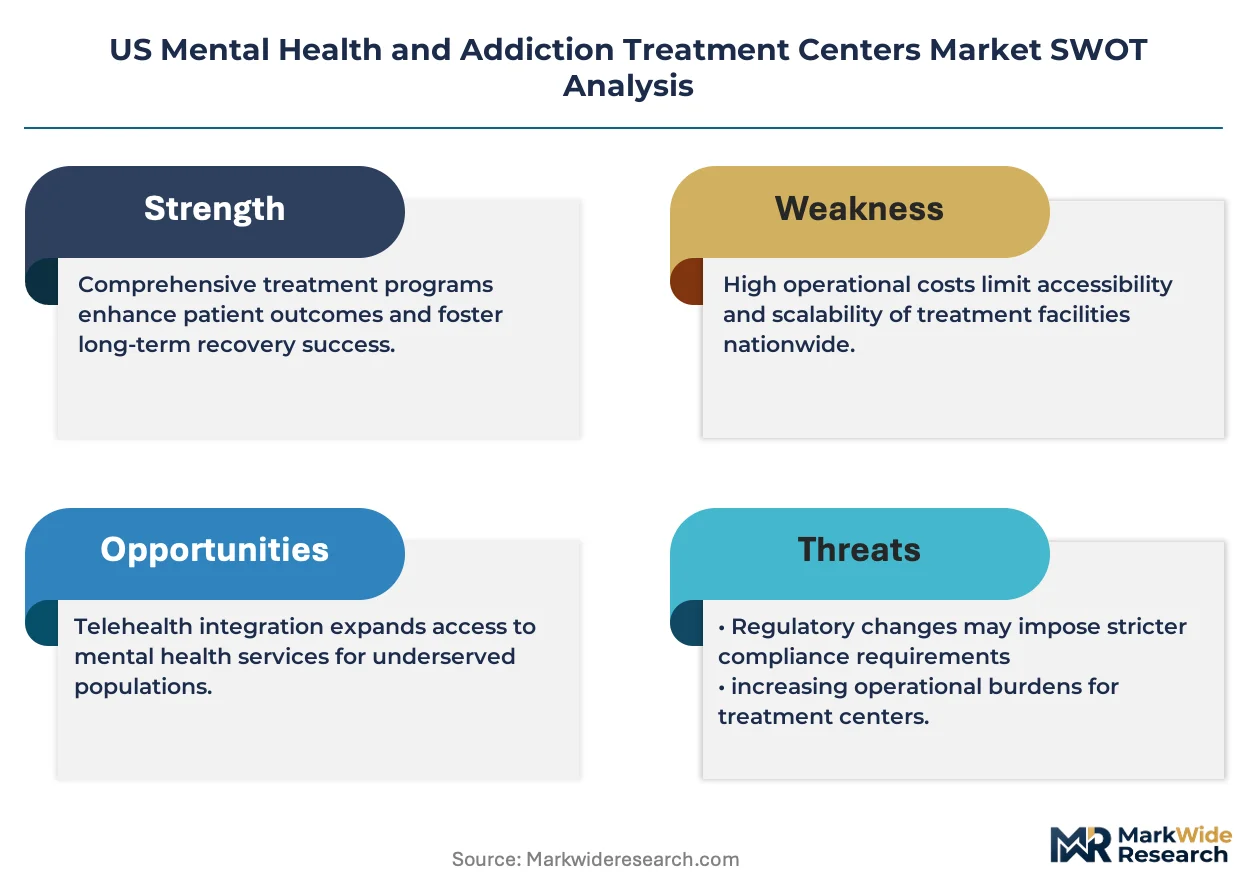
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Buyer power is concentrating among large self-insured employers and Medicare Advantage plans that unbundle behavioral health from general medical networks, consolidating procurement leverage around outcomes data requirements and direct residential contracting.
For Market Incumbents: Pre-empt workforce supply bottlenecks through captive training pipeline investments in California and Texas psychiatric residency partnerships. Anchor defensive positioning by acquiring telehealth credentialing platforms that bypass Joint Commission facility accreditation requirements, neutralizing brick-and-mortar capex intensity threats from virtual-only entrants. For New Entrants and Emerging Players: Rural Texas counties without psychiatrist density represent the most penetrable white-space geography for telehealth-only licensing models that bypass traditional facility accreditation. Target partial hospitalization program contracts with Medicare Advantage plans in Florida where reimbursement rates approach inpatient levels. Pursue direct employer carve-out positioning with energy sector and technology firms seeking outcomes-based behavioral health partnerships. For Investors and Strategic Acquirers: Telehealth-enabled partial hospitalization operators with Medicare Advantage plan contracts present the priority acquisition archetype for capturing margin pools without overnight staffing costs. Long-term viability hinges on CMS telehealth reimbursement permanence decisions and state Medicaid agency alignment with federal parity standards. Monitor FDA digital therapeutics clearance timelines for substance use disorder interventions as inflection signals for platform valuation multiples.| Strategic Initiative | Industry Significance |
|---|---|
| Telehealth Infrastructure Integration | CMS telehealth parity rules normalize virtual psychiatric evaluation reimbursement across state Medicaid programs. |
| Partial Hospitalization Program Expansion | Medicare Advantage plans in Florida and Texas reimburse intensive outpatient programs at inpatient-approaching rates. |
| Destination Residential Positioning | Geographic isolation as therapeutic variable attracts self-pay patients from coastal California urban markets. |
| Employer Direct Contracting | Self-insured employers unbundle behavioral health from general medical networks for carve-out volume. |
| Digital Therapeutics Integration | FDA-cleared prescription digital therapeutics extend reach beyond facility walls into payer direct contracts. |
Research Methodology
Cross-validation between primary interviews with treatment center executives, clinical operations directors, and employer benefits managers and secondary sources including CMS reimbursement filings, state health department licensure databases, and Joint Commission accreditation records anchors the qualitative findings. Hospital procurement committees and Medicare Advantage plan contracting officers provided payer-side perspective. Bottom-up facility capacity counts triangulate against top-down expenditure estimates from Medicaid and commercial claims data.
Calibration against historical bed expansion patterns and telehealth adoption curves across the projection horizon ensures analytical robustness. Segmentation dimensions modeled include treatment type, service offering, target population, and facility ownership structure with geographic payer mix as an industry-specific overlay. CAGRs derive from regression analysis of reimbursement rate trajectories and workforce supply elasticity. Forecast inputs incorporate FDA digital health guidance evolution and CMS telehealth permanence rulemaking.
Macroeconomic conditions sit as an overlay; deviation in Medicaid federal matching fund levels, commercial insurance premium trends, or clinical labor wage inflation would shift the trajectory. Forecasts reflect documented assumptions regarding regulatory stability and technology adoption curves. Continuous validation against operating reality is the recommended discipline.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Addiction Treatment
Cocaine Intoxication Treatment Market
Addiction Treatment
Global Addiction Treatment Market
Addiction Treatment
Nicotine De-Addiction Products Market
Addiction Treatment
Smokeless Tobacco Treatment Market
Addiction Treatment
US Ketamine Clinics Market
Addiction Treatment
Opioid Use Disorder (OUD) Market
Addiction Treatment
Opioid Induced Constipation Treatment Market
Addiction Treatment
Drug Free Depression Treatment Market
Addiction Treatment
Opioid Use Disorder Treatment Market
Addiction Treatment
Substance Abuse Treatment Market
Addiction Treatment
Alcohol Use Disorder Treatment Market
Addiction Treatment
Methadone Market
Addiction Treatment
Global Substance Use Disorder Treatment Market
Addiction Treatment
Opioid Withdrawal Treatment Market