
 US House Calls Market | 2026-2036
US House Calls Market Size, Share, and Industry Trends Forecast 2026-2036
US House Calls Market Intelligence
Concierge-grade service tiers is unwinding traditional fee-for-service constraints across the US House Calls Market. DispatchHealth leverages hospital system partnerships to sustain geographic density in major metros. Heal differentiates through full-stack primary care delivery that integrates remote monitoring with in-home visits. Concierge MD anchors the premium segment with membership-based models serving high-net-worth households in coastal markets.
US house calls encompass licensed medical professionals delivering diagnostic, therapeutic, and preventive services directly to patients in residential settings, typically utilizing portable diagnostic equipment and electronic health record systems synchronized with payer networks. Primary care visits constitute the volume backbone, while chronic care management captures expanding reimbursement under CMS value-based programs. Telehealth platforms extend reach into rural geographies where mobile medical units face deployment cost barriers.
CMS, state medical boards, and HIPAA compliance frameworks collectively shape operational requirements for credentialing, documentation, and data security across house call providers. FDA oversight of remote monitoring devices and DEA regulations for controlled substance prescribing in home settings impose additional compliance layers. Stakeholders must track state-level scope-of-practice expansions for nurse practitioners and physician assistants as workforce constraints intensify.
Market Dynamics
CMS value-based reimbursement models are restructuring provider economics across the US House Calls Market, compressing fee-for-service margins while rewarding longitudinal patient relationships and outcome metrics tied to chronic care management.
Growth Catalysts
- IRA prescription drug pricing provisions:Reduced out-of-pocket costs for Medicare beneficiaries expand medication adherence programs delivered through house call channels.
- Aging-in-place preferences:Florida, Texas, and California seniors increasingly reject facility-based transitions, creating concentrated demand corridors for in-home primary care.
- Remote patient monitoring integration:Bluetooth-enabled diagnostic devices synchronize vitals directly into EHR systems, enabling real-time clinical decision-making during residential visits.
Market Restraints
- Physician supply concentration:Rural counties across the Great Plains and Mountain West face specialist deserts exceeding 100 miles, limiting service radius viability.
- Reimbursement lag structure:Medicare claims processing cycles stretch 30-45 days, straining working capital for independent house call practices.
- DEA controlled substance barriers:In-home prescribing of Schedule II medications requires complex documentation protocols that deter pain management expansion.
Strategic Opportunities
- Medicaid waiver expansion:State-level 1115 waivers in Texas and Florida now cover house calls for dual-eligible populations previously excluded from fee schedules.
- Hospital-at-home bundling:CMS Acute Hospital Care at Home program creates new reimbursement codes for post-acute transitions previously confined to skilled nursing facilities.
- Nurse practitioner scope liberalization:Arizona, Colorado, and Oregon independent practice laws enable non-physician providers to anchor rural service territories.
Industry Challenges
- Interoperability fragmentation:House call platforms struggle with EHR integration across heterogeneous hospital system architectures, delaying care coordination.
- Mobile diagnostic calibration:Portable imaging and lab equipment requires daily quality assurance protocols that extend visit duration and compress daily caseload capacity.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | US House Calls Market |
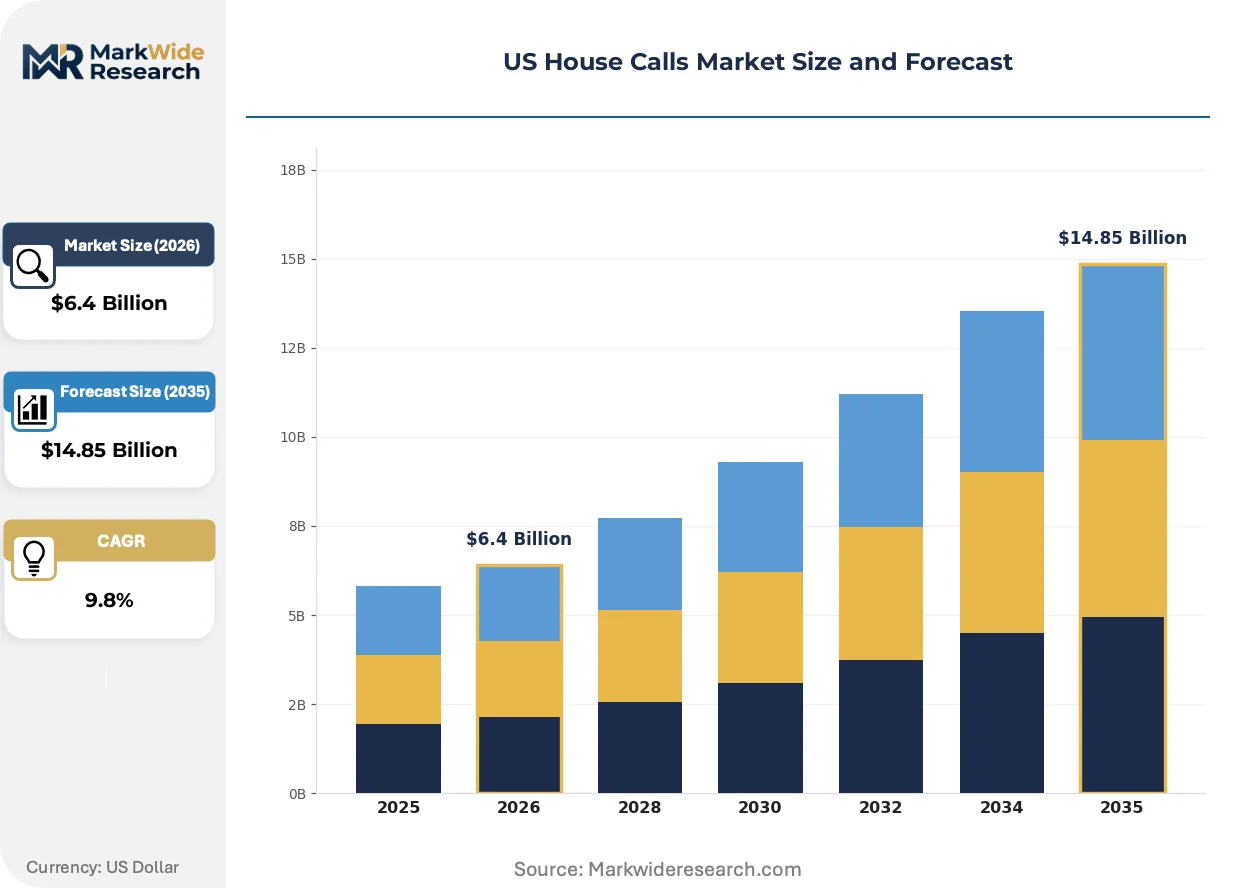
| Market Size in 2026 | $6.4 Billion |
| Market Size in 2035 | $14.85 Billion |
| CAGR (2026 – 2036) | 9.8% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: Primary Care, Specialist Consultations, Chronic Care Management, Palliative Care End User: Seniors, Homebound Patients, Busy Families, Disabled Individuals Technology: Telehealth Platforms, Mobile Medical Units, Remote Monitoring Devices, Patient Portals Care Setting: Private Residences, Assisted Living Facilities, Nursing Homes, Community Centers |
| Companies Covered | Doctor on Demand, Urgent Med House Calls, Heal, Ennoble Care, House Call Doctors Medical Group, DispatchHealth, SOS Doctor House Call, Concierge MD, MDLIVE, Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
US House Calls Market Strategic Shifts & Innovations
Technology convergence and regulatory flexibility are dissolving traditional site-of-care boundaries across the US House Calls Market, enabling clinical service delivery models that were structurally impossible under legacy reimbursement frameworks.
Portable point-of-care ultrasound is decomposing the diagnostic monopoly of fixed imaging centers. Cardiologists and internists now deploy handheld devices for cardiac, pulmonary, and abdominal assessments during residential visits. Medicare Advantage plans in Miami-Dade and Orange County have expanded prior authorization for these modalities, compressing specialist referral cycles from weeks to same-day resolution.
HIPAA-compliant mobile documentation platforms are reshaping compliance architecture for roaming clinical workforces. Cloud-native EHR systems with offline synchronization capabilities enable real-time charting without residential broadband dependency. House call providers in rural Arizona and New Mexico leverage these tools to maintain documentation integrity across cellular dead zones.
Subscription-based primary care memberships are displacing traditional insurance billing for affluent households in coastal California and Northeast corridor markets. Patients pay monthly retainers for unlimited access to house call services, bypassing prior authorization friction. This model concentrates in metropolitan statistical areas where household density supports route optimization and where concierge medicine infrastructure already exists.
US House Calls Market Segmentation
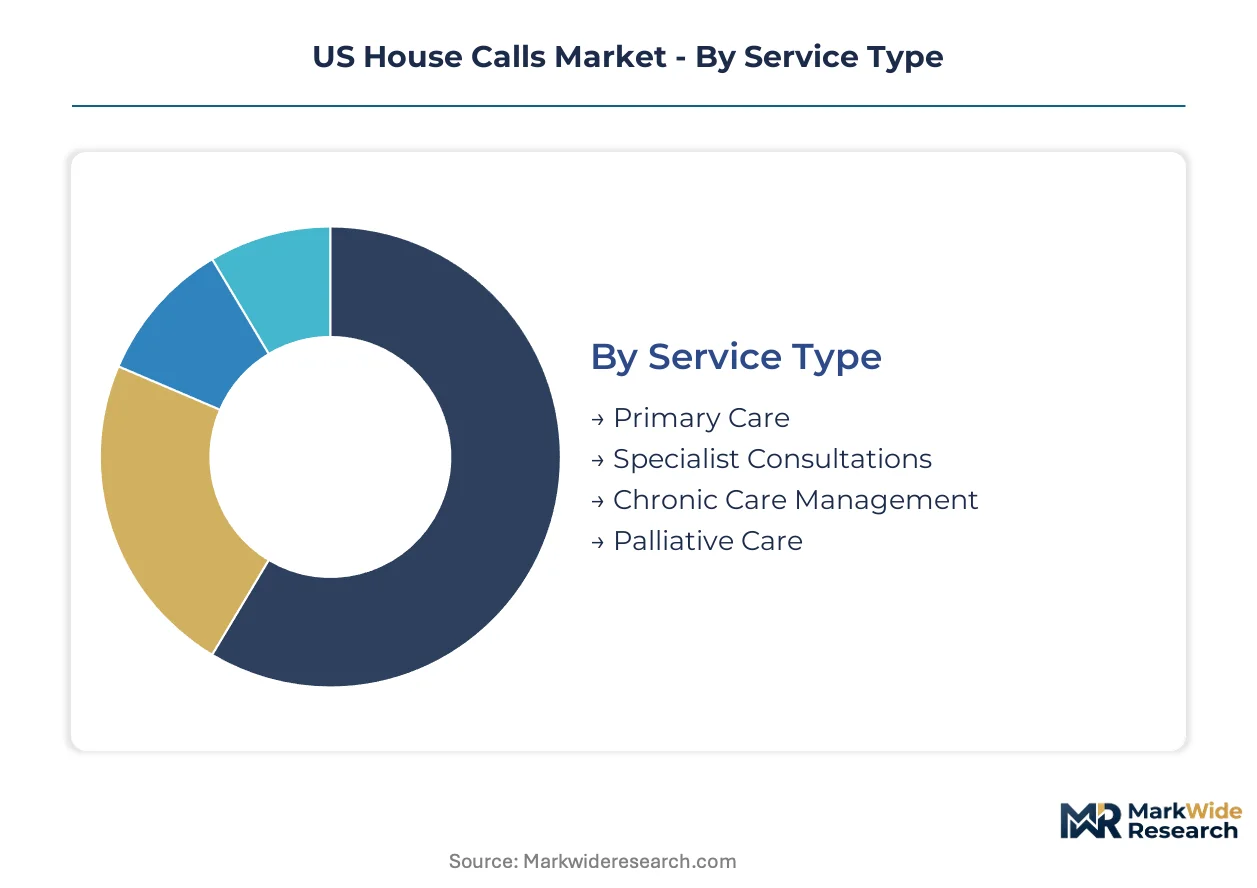
Service configuration determines reimbursement pathways and regulatory compliance burdens across the US House Calls Market. Patient acuity, technology deployment, and site-of-care classification collectively shape provider economics and operational scale.
Service Type:
CMS reimbursement codes differentiate house call services through visit complexity, care coordination requirements, and outcome accountability metrics.
- Primary Care:Routine diagnostic and preventive services delivered by physicians or nurse practitioners using portable examination equipment. Medicare Advantage plans in Florida and Texas now bundle these visits with remote monitoring for dual-eligible populations.
- Specialist Consultations:Cardiology, pulmonology, and geriatric assessments performed by board-certified specialists deploying handheld ultrasound and EKG devices. Demand concentrates in Miami-Dade and Orange County where prior authorization barriers for portable imaging have relaxed.
- Chronic Care Management:Monthly care coordination for patients with two or more chronic conditions, reimbursed under CMS value-based codes requiring 24/7 access and care plan documentation.
- Palliative Care:Symptom-focused interventions for serious illness, typically delivered by interdisciplinary teams including social workers and chaplains alongside clinicians.
Primary Care handles the majority of throughput; Chronic Care Management is expanding most quickly on share.
End User:
Patient mobility constraints and caregiver support structures determine service frequency, visit duration, and clinical staffing ratios.
- Seniors:Medicare beneficiaries aged 65+ requiring medication reconciliation, fall risk assessments, and advance care planning. Florida's aging-in-place initiatives have expanded house call eligibility for this cohort.
- Homebound Patients:Individuals meeting CMS homebound criteria due to illness or injury, qualifying for higher reimbursement rates under traditional Medicare fee schedules.
- Busy Families:Working parents seeking pediatric acute care or wellness visits outside standard clinic hours, concentrated in metropolitan statistical areas with concierge infrastructure.
- Disabled Individuals:Patients with physical or cognitive impairments requiring accessible examination techniques and specialized transportation coordination for mobile medical units.
Seniors generate the dominant visit volume; Busy Families show the steepest expansion trajectory as subscription models penetrate coastal California markets.
Technology:
Hardware and platform investments determine geographic reach, clinical capability, and integration complexity with hospital system EHR architectures.
- Telehealth Platforms:HIPAA-compliant video consultation systems enabling synchronous virtual visits. Rural Arizona and New Mexico providers leverage these tools to extend coverage into cellular dead zones through offline synchronization.
- Mobile Medical Units:Retrofitted vans or RVs delivering point-of-care laboratory testing and imaging. Deployment costs concentrate service density in major metros while limiting rural viability.
- Remote Monitoring Devices:Bluetooth-enabled blood pressure cuffs, pulse oximeters, and weight scales transmitting vitals directly into EHR systems. Medicare Advantage plans now cover device provisioning for chronic care enrollees.
- Patient Portals:Secure messaging and appointment scheduling interfaces reducing administrative overhead for house call practices managing dispersed patient panels.
Telehealth Platforms anchor the technology stack on volume; Remote Monitoring Devices are climbing the fastest as CMS expands reimbursement for continuous biometric surveillance.
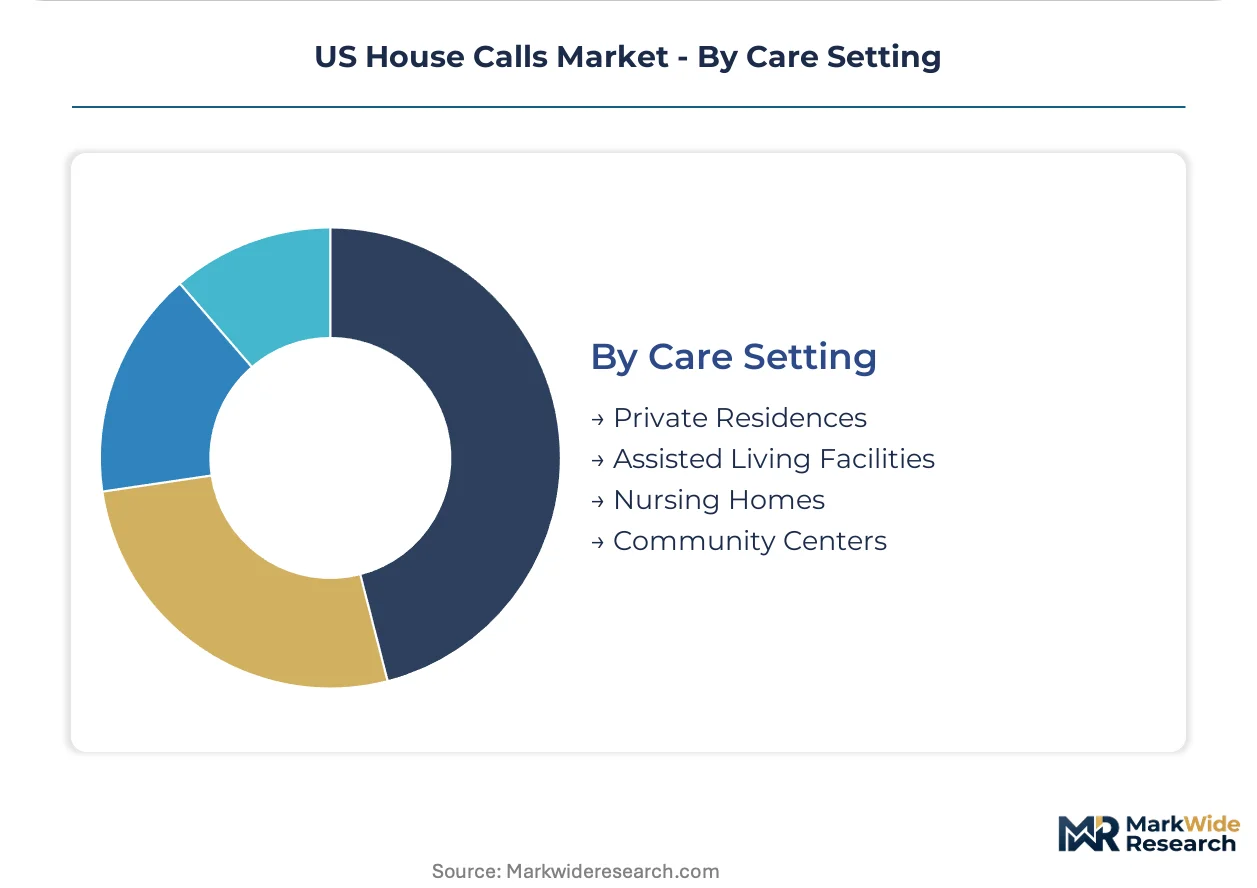
Care Setting:
Facility type dictates infection control protocols, liability frameworks, and care coordination relationships with institutional staff.
- Private Residences:Single-family homes and apartments where patients maintain autonomous living arrangements. HIPAA-compliant mobile documentation platforms enable real-time charting without residential broadband dependency.
- Assisted Living Facilities:Residential communities providing personal care services but not skilled nursing, requiring house call providers to coordinate with facility nursing directors and maintain separate medical records.
- Nursing Homes:Skilled nursing facilities where house call physicians supplement or replace attending medical directors, navigating complex state survey requirements and quality metrics.
- Community Centers:Shared spaces hosting group wellness visits or vaccination clinics, requiring temporary medical station setup and crowd management protocols.
Private Residences absorb the dominant share of clinical hours; Assisted Living Facilities are gaining share fastest as operators outsource medical directorship to house call networks.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Price sensitivity for house call services varies sharply across US sub-regions, with Medicare-dependent rural markets demanding lean operational models while affluent coastal metros absorb premium subscription tiers without volume constraints.
Florida
Miami-Dade and Orange County seniors drive dense demand corridors where aging-in-place preferences collide with specialist physician shortages. CMS Hospital-at-Home waivers and state Medicaid 1115 expansions for dual-eligibles widen reimbursement pathways. West Palm Beach and Tampa Bay house call networks concentrate on Medicare Advantage bundling with remote monitoring for chronic care enrollees.
Texas
Houston and Dallas-Fort Worth metropolitan statistical areas absorb expanding house call volume from homebound populations and busy family segments seeking pediatric acute care outside clinic hours. State-level scope-of-practice liberalization for nurse practitioners enables non-physician providers to anchor rural service territories in the Permian Basin and Rio Grande Valley. Austin-based platforms leverage technology infrastructure to synchronize mobile medical unit deployment across sprawling metro geographies.
California
Los Angeles County and Bay Area markets sustain subscription-based primary care memberships among affluent households bypassing prior authorization friction. HIPAA-compliant mobile documentation platforms with offline synchronization enable service extension into rural Sierra Nevada and Central Valley zones with cellular dead zones. San Diego operators integrate with hospital system EHR architectures to manage post-acute transitions under CMS value-based codes.
Arizona
Maricopa County and Tucson metro areas exploit independent practice laws for nurse practitioners to serve dispersed retirement communities with limited physician density. Rural Apache and Navajo counties rely on telehealth platforms extending reach where mobile medical unit deployment costs prove prohibitive. Flagstaff and Prescott providers coordinate with regional health systems to manage chronic care for geographically isolated Medicare beneficiaries.
New York
New York City metropolitan area concentrates concierge-grade service tiers among high-net-worth households in Manhattan and Brooklyn brownstone districts. Upstate regions including Buffalo and Rochester face physician supply constraints that telehealth platforms partially offset through synchronous virtual visits. State regulations on controlled substance prescribing in home settings create compliance complexity that deters pain management expansion across Hudson Valley and Capital District service territories.
US House Calls Market Key Industry Players
Technology leadership and cost leadership are held by different player archetypes across the US House Calls Market. Full-stack platform operators with integrated EHR and remote monitoring capabilities command premium positioning, while lean dispatch networks compete on visit density and geographic coverage. Three archetypes dominate: technology-integrated primary care platforms, hospital system partnership models, and concierge membership operators. Consolidation pressure is accelerating through strategic partnerships with payers and vertical integration into remote patient monitoring device provisioning.
Within the technology-integrated tier, Heal and DispatchHealth exemplify divergent scale strategies. Heal anchors full-stack primary care delivery with remote monitoring integration, while DispatchHealth sustains geographic density through hospital system partnerships in major metros. Concierge MD occupies the premium membership segment serving high-net-worth coastal markets. Doctor on Demand and MDLIVE represent telehealth-first architectures extending into house call channels through hybrid virtual-physical models.
| Leading Market Players |
|---|
| Doctor on Demand |
| Urgent Med House Calls |
| Heal |
| Ennoble Care |
| House Call Doctors Medical Group |
| DispatchHealth |
| SOS Doctor House Call |
| Concierge MD |
| MDLIVE |
| Others |
Cost & Logistics Intelligence
Thirty-to-forty-five-day Medicare claims processing cycles compress working capital availability for independent house call practices, concentrating pricing power among hospital-affiliated networks with balance-sheet depth to absorb reimbursement lag. This liquidity asymmetry reinforces tiered service stratification across the US House Calls Market.
Pricing Analysis
Chronic care management subscriptions drive lifetime value capture across patient relationships. Three-tier pricing structure across premium concierge, standard Medicare Advantage, and economy Medicaid waiver levels segments buyers by coverage sophistication. Cost compression in standard tiers intensifies because CMS value-based codes reward outcome metrics over visit volume. Medicaid-dependent rural counties exhibit acute price sensitivity; Manhattan and coastal California households absorb premium retainers without volume constraints.
Supply Chain Analysis
Inventory cycles for portable diagnostic equipment run 15-30 days with daily calibration protocols compressing provider caseload capacity. Hardware supply concentrates in China, South Korea, and Germany for Bluetooth-enabled biometric sensors and handheld ultrasound devices. Component dependencies span lithium-ion batteries, medical-grade semiconductors, and FDA-cleared telemetry modules. Single-source vulnerability for EHR-integrated telemetry chips threatens continuity. Distribution runs through hospital system procurement committees and direct-to-practice medical device channels.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
The US House Calls Market operates as a defensive-moat story where CMS reimbursement entrenchment creates switching costs that lock in patient panels and deter competitive poaching.
For Market Incumbents: Consolidate geographic density through hospital system partnerships in Miami-Dade and Orange County corridors where prior authorization relationships already exist. Acquire remote monitoring device provisioning capabilities to capture upstream revenue from chronic care enrollees. Nurse practitioner scope liberalization in Arizona and Colorado threatens physician-centric models; anchor rural territories with independent-practice non-physician providers before competitors establish presence.
For New Entrants and Emerging Players: Rural telehealth platform gaps in Apache and Navajo counties offer white-space entry points where mobile medical unit deployment costs exclude incumbent scale players. Target Medicaid 1115 waiver expansion corridors in Texas and Florida where dual-eligible populations remain underserved. Pursue hospital-at-home bundling relationships with regional health systems seeking CMS Acute Hospital Care at Home program participation.
For Investors and Strategic Acquirers: Long-term, this sits as a regulatory-capture play because CMS value-based reimbursement restructuring favors incumbents with existing patient longitudinal data and outcome documentation infrastructure. Acquisition targets should display integrated EHR-remote monitoring stacks with proven Medicare Advantage contracting relationships. Watch for state-level scope-of-practice liberalization as inflection signal for nurse practitioner-anchored rural rollouts.
| Strategic Initiative | Industry Significance |
|---|---|
| Hospital System Partnership | Secures prior authorization pathways and EHR integration in dense metro corridors. |
| Remote Monitoring Device Provisioning | Captures upstream hardware revenue from Medicare Advantage chronic care enrollees. |
| CMS Reimbursement Strategy | Positions providers for Hospital-at-Home waivers and value-based code expansion. |
| Software Companion Development | Enables HIPAA-compliant mobile documentation with offline synchronization for rural zones. |
| Nurse Practitioner Scope Expansion | Unlocks rural service territories under Arizona, Colorado, and Oregon independent practice laws. |
Research Approach
Initial hypotheses were tested against primary input from house call practice operators, Medicare Advantage plan contracting officers, hospital system integration specialists, and CMS policy analysts and refined through secondary validation against CMS Medicare data, state Medicaid waiver filings, hospital procurement databases, and FDA 510(k) clearances for remote monitoring devices. Bottom-up patient panel sizing and top-down reimbursement code valuation were triangulated to converge volume and value estimates.
Variance decomposition across service type, technology deployment, care setting, and geographic regulatory cluster shaped the analytical framework over the projection horizon. CAGRs were derived from patient demographic trajectories, Medicare Advantage penetration curves, and state-level scope-of-practice legislative tracking. Forecast inputs incorporated CMS value-based reimbursement shift assumptions and telehealth platform adoption elasticity in rural cellular dead zones.
Underlying assumptions cover sustained CMS Hospital-at-Home program expansion and state Medicaid 1115 waiver continuity, with deviation risk concentrated in DEA controlled substance prescribing rule changes and Medicare claims processing cycle extensions. Outputs are directional rather than point-estimates.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Home Healthcare
Global Home Health Care Services Market
Home Healthcare
Senior in-Home Care Services Market
Home Healthcare
Portable Toilet for Elderly Market
Home Healthcare
Home Healthcare Market
Home Healthcare
US Home Healthcare Market
Home Healthcare
Adult Day Care Market
Home Healthcare
Outpatient Home Therapy Market
Home Healthcare
Home Care Service Market
Home Healthcare
Chemotherapy at Home Services Market
Home Healthcare
US Home Infusion Therapy Market
Home Healthcare
US Home Healthcare Services Market
Home Healthcare
Canada Home Healthcare Market
Home Healthcare
Global Home Healthcare Software Market
Home Healthcare
Elder Care Subscription Market
Home Healthcare
Global Elderly Care Market
Home Healthcare
Elderly Care Apps Market