
 US Hospital Emergency Department Market | 2026-2036
US Hospital Emergency Department Market Size, Share, and Industry Trends Forecast 2026-2036
US Hospital Emergency Department Market Intelligence
Freestanding emergency center networks are reshaping how patients access acute care across suburban and exurban markets. HCA Healthcare leverages its scale to dominate high-volume metropolitan corridors with integrated ED-hospital campuses. Tenet Healthcare Corporation anchors its position through specialized cardiac and trauma capabilities in underserved regions. Community Health Systems competes by extending its footprint into mid-size cities where ED closures have created access gaps.
A hospital emergency department constitutes a twenty-four-hour clinical facility designed for immediate assessment, stabilization, and treatment of acute medical conditions, typically operating under Level I through V trauma designations with mandated response-time thresholds. Its core function centers on preventing mortality and disability through rapid intervention for time-sensitive pathologies. Trauma care and cardiac care segments command the deepest reimbursement pools due to high resource intensity and specialist staffing requirements. Telemedicine within the technology segment is expanding fastest as CMS reimbursement parity rules and workforce shortages push health systems toward remote physician consultation models. Pediatric care remains structurally underrepresented relative to disease burden, creating margin pressure on children's hospitals that must maintain dedicated ED capacity.
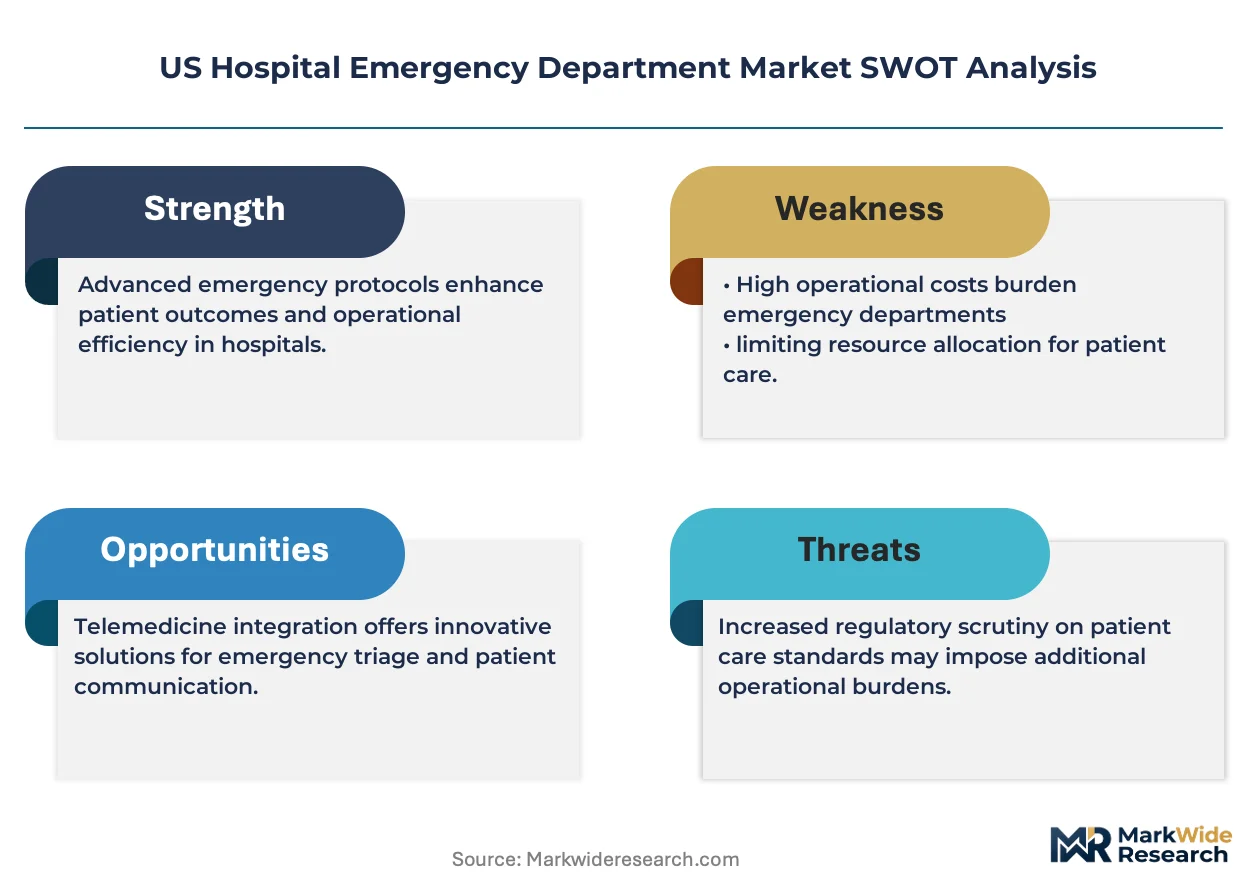
FDA oversight of emergency-use medical devices, CMS conditions of participation governing ED staffing and equipment, and EMTALA mandates requiring screening and stabilization regardless of insurance status collectively define operational compliance burdens. These frameworks shape capital allocation toward regulatory-ready infrastructure and influence payer contracting strategies for emergency services. Stakeholders must monitor state-level certificate-of-need reforms and CMS site-neutral payment proposals that threaten freestanding ED economics while rewarding integrated delivery networks.
Market Dynamics
Medicaid expansion under the ACA is redrawing payer mix across rural and exurban ED networks, forcing operators to recalibrate staffing models and capital deployment toward higher-Medicaid census zones.
Growth Catalysts
- Telemedicine reimbursement parity:CMS rules mandating equivalent payment for remote physician consultations are accelerating adoption of virtual triage platforms across health systems.
- Freestanding emergency center proliferation:Texas and Florida regulatory frameworks permit off-campus acute care facilities, capturing suburban demand outside traditional hospital footprints.
- EHR interoperability mandates:CMS conditions of participation require seamless data exchange between EDs and downstream providers, driving technology infrastructure investment.
Market Restraints
- Specialist physician scarcity:Emergency medicine residency bottlenecks and rural maldistribution constrain ED staffing capacity regardless of capital availability.
- EMTALA unfunded mandate:Federal requirements for screening and stabilization regardless of insurance status impose structural cost burdens on safety-net facilities.
- Site-neutral payment threats:CMS proposals to equalize reimbursement between hospital-based and freestanding EDs threaten the economic model of off-campus facilities.
Strategic Opportunities
- Pediatric emergency capacity gaps:Structural underrepresentation of dedicated pediatric EDs relative to disease burden creates expansion opportunity for children's hospital networks.
- Micro-hospital integration:CMS flexibility for co-located emergency and inpatient services under 10 beds enables lower-cost market entry in underserved exurban corridors.
- AI-assisted clinical decision support:FDA 510(k) pathways for emergency diagnostic algorithms are opening reimbursement channels for machine-learning triage tools.
Industry Challenges
- Nurse staffing volatility:Travel nurse dependency and burnout-driven turnover destabilize ED operations and inflate labor costs beyond fixed reimbursement rates.
- Behavioral health boarding:Psychiatric patient retention in EDs awaiting inpatient placement consumes physical capacity and degrades throughput metrics.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | US Hospital Emergency Department Market |
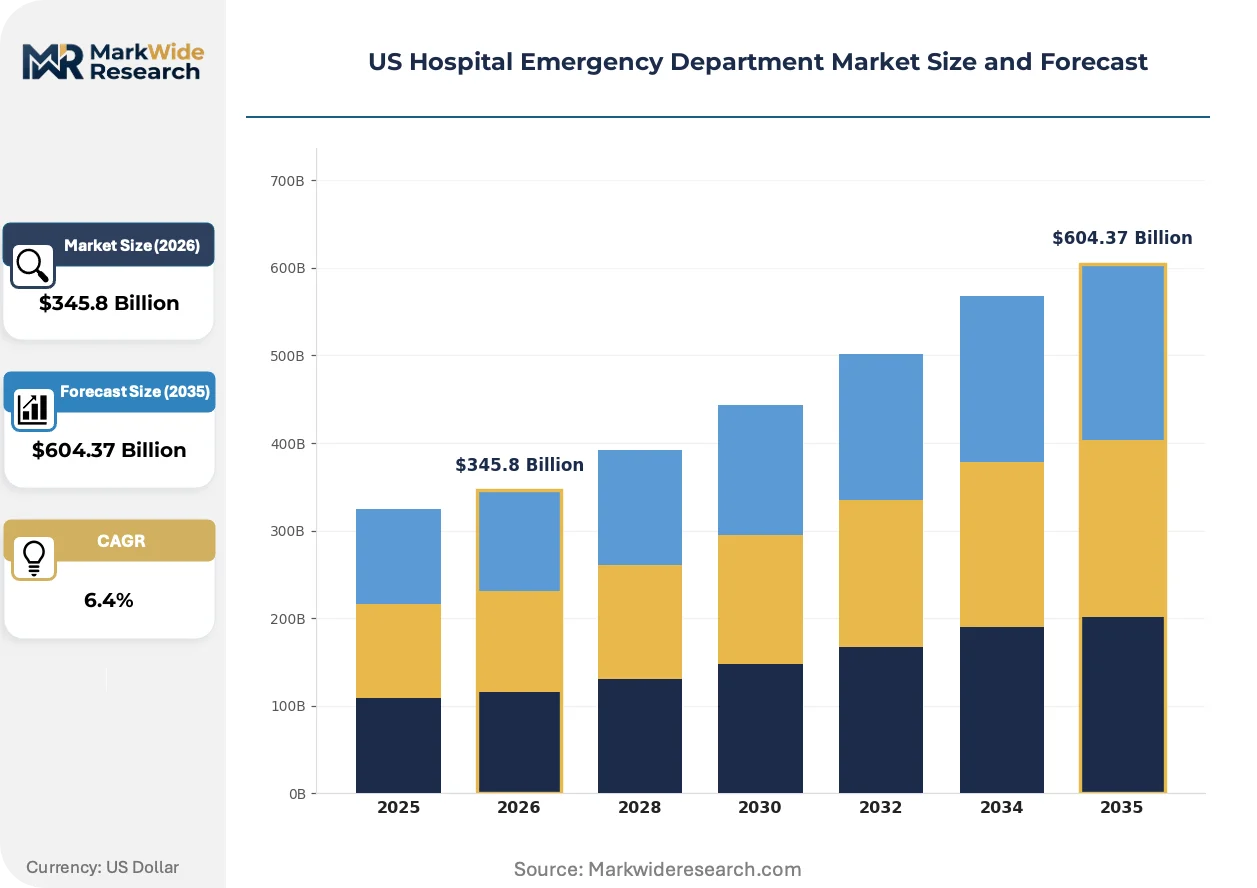
| Market Size in 2026 | $345.8 Billion |
| Market Size in 2035 | $604.37 Billion |
| CAGR (2026 – 2036) | 6.4% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: Trauma Care, Cardiac Care, Stroke Care, Pediatric Care Delivery Mode: Triage, Admission, Observation, Transfer Technology: Telemedicine, Imaging Systems, Patient Monitoring, EHR End User: Patients, Caregivers, Insurers, Healthcare Providers |
| Companies Covered | Ascension Health, Lifepoint Health, HCA Healthcare, Parkland Health, Ardent Health Services, Tenet Healthcare Corporation, Community Health Systems, CHRISTUS Health, Universal Health Services, Inc., Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
US Hospital Emergency Department Market Strategic Shifts & Innovations
Acute care delivery is fragmenting across physical and virtual channels, with technology substituting for proximity and policy redefining where emergency services can legally and economically operate.
Telemedicine platforms are virtualizing the initial patient encounter, replacing physical triage with video-based physician assessment. Urban academic medical centers and large integrated systems are deploying these tools fastest, compressing time-to-provider metrics and reducing low-acuity ED volumes that strain capacity.
CMS site-neutral payment proposals are recalibrating capital allocation toward hospital-attached emergency capacity rather than freestanding alternatives. The regulatory uncertainty is freezing greenfield investment in off-campus facilities while operators await final rulemaking on reimbursement parity.
Patients are bypassing traditional ED entry points through direct-to-consumer urgent care and retail clinic channels, then escalating to emergency departments only when acuity demands. This behavioral shift concentrates ED census toward higher-complexity cases, reshaping staffing ratios and equipment requirements in suburban markets where alternatives proliferate.
US Hospital Emergency Department Market Segmentation
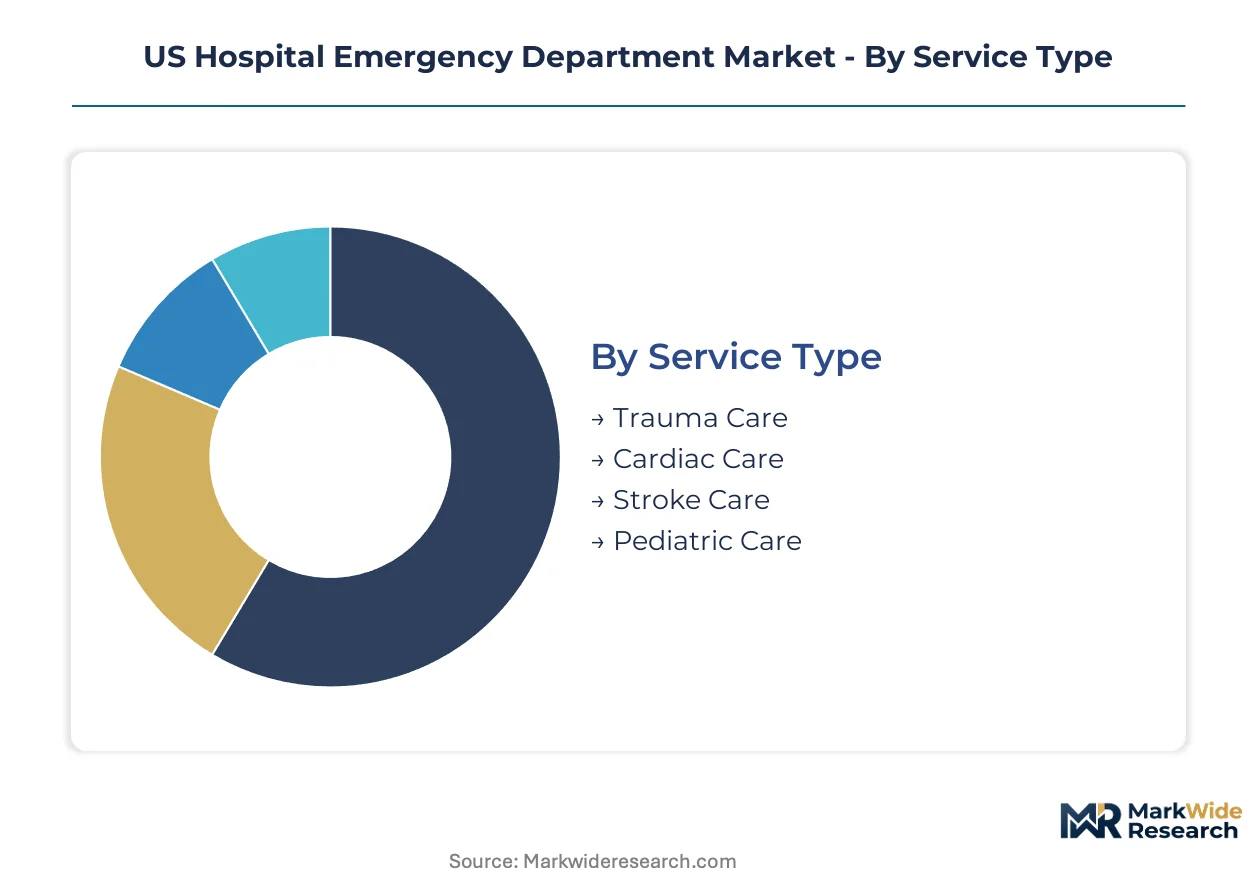
Segmentation reveals how capital flows diverge across clinical service lines, patient pathways, and technology platforms. Understanding these divisions helps operators align staffing models with reimbursement intensity and regulatory requirements.
Service Type:
Mature trauma and cardiac segments anchor revenue stability, while pediatric and stroke capabilities represent emerging expansion frontiers.
- Trauma Care:Level I through V designated facilities deliver surgical stabilization for penetrating injuries and multisystem trauma. Urban academic medical centers in Texas and Florida concentrate demand where Medicaid expansion has broadened payer coverage for uninsured trauma patients.
- Cardiac Care:STEMI and NSTEMI protocols require catheterization lab proximity and interventional cardiology coverage. Suburban hospital networks in Georgia and North Carolina are expanding cardiac ED capacity to capture transfers from rural facilities lacking percutaneous coronary intervention capability.
- Stroke Care:Comprehensive stroke centers with thrombectomy capability serve as regional hubs.
- Pediatric Care:Dedicated pediatric EDs with subspecialty coverage remain structurally scarce relative to disease burden.
Trauma Care handles the majority of throughput; Pediatric Care is the fastest mover on share.
Delivery Mode:
Cost tier stratification separates high-intensity admission pathways from lower-acuity observation and transfer alternatives.
- Triage:Rapid assessment protocols sort patients into acuity categories using ESI scoring. Freestanding emergency centers in Texas deploy advanced triage to bypass traditional hospital queues and capture commercially insured suburban demand.
- Admission:Inpatient boarding from ED holds consumes capacity and degrades throughput metrics. Safety-net hospitals in California face acute pressure from psychiatric admission delays and medical-surgical bed scarcity.
- Observation:CMS two-midnight rule compliance drives short-stay utilization.
- Transfer:EMTALA-mandated stabilization precedes interfacility movement for definitive care.
Triage commands the highest technology investment intensity; Observation is expanding most quickly as payers scrutinize admission appropriateness.
Technology:
Application focus distinguishes diagnostic infrastructure from connectivity and remote care platforms.
- Telemedicine:Video-based physician consultation platforms enable virtual triage and specialist backup for rural facilities. CMS reimbursement parity rules are accelerating deployment across integrated delivery networks in Mississippi and Arkansas where neurologist and psychiatrist scarcity limits on-site coverage.
- Imaging Systems:CT, MRI, and point-of-care ultrasound support rapid diagnostic confirmation. Trauma centers in Pennsylvania and Ohio prioritize 24/7 radiology coverage to meet ACS verification standards.
- Patient Monitoring:Continuous telemetry and early warning scoring systems detect deterioration.
- EHR:CMS interoperability mandates require seamless data exchange with downstream providers.
Imaging Systems absorbs the largest capital allocation; Telemedicine is gaining share fastest as workforce gaps widen.
End User:
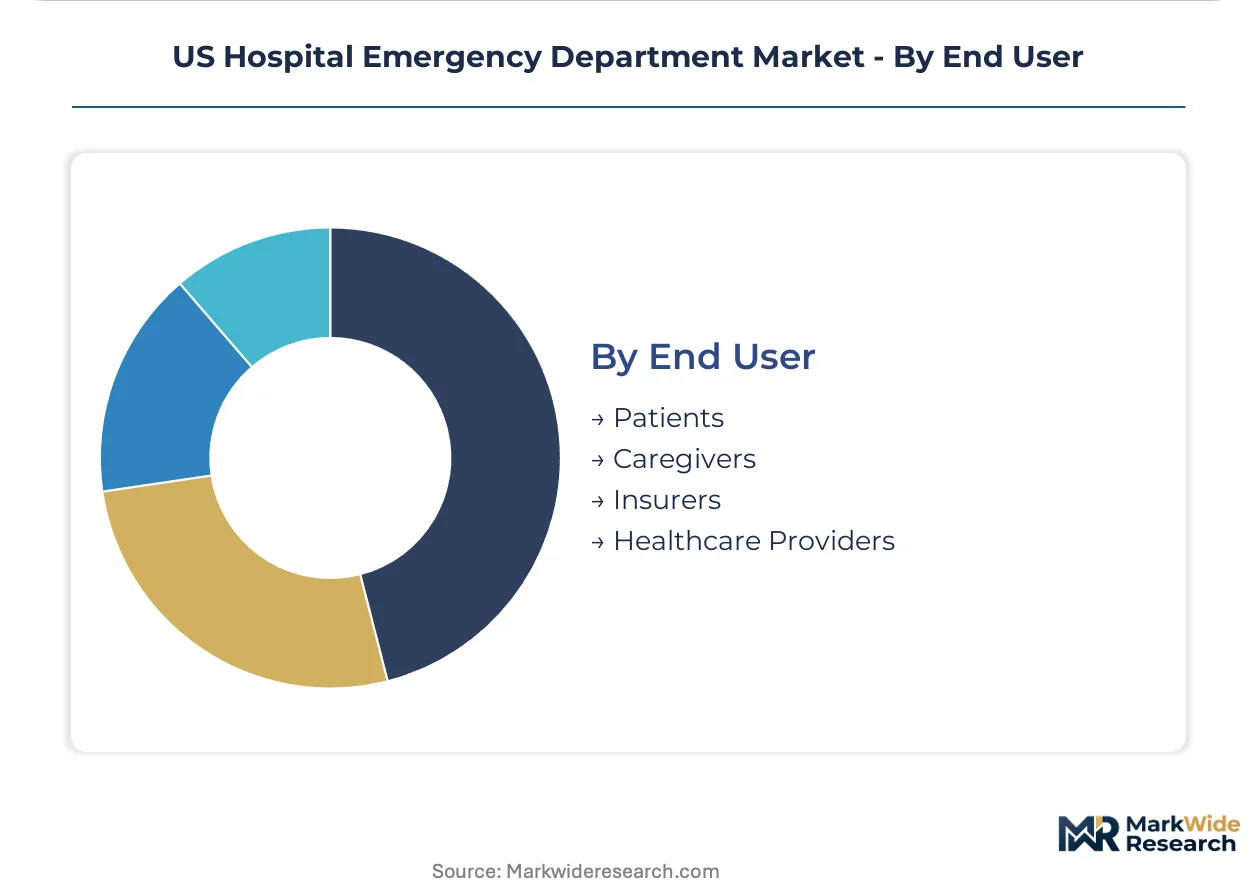
Customer type segmentation separates direct clinical consumers from financial intermediaries and institutional purchasers.
- Patients:Consumer choice drives site selection between hospital-based EDs, freestanding centers, and urgent care alternatives. High-deductible plan growth in Texas and Florida pushes commercially insured patients toward transparently priced freestanding facilities.
- Healthcare Providers:Physician groups and hospital systems procure ED services as network components. Accountable care organizations in Massachusetts and California increasingly steer members toward lower-cost emergency settings.
- Insurers:Prior authorization and narrow network design reshape site-of-service economics.
- Caregivers:Family decision-making influences transport mode and facility selection.
Healthcare Providers drive the largest contract value; Patients are shifting fastest toward retail-accessible alternatives.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Texas and Florida command premium reimbursement rates for freestanding emergency centers, while rural Mississippi and Arkansas operate under severe specialist scarcity that compresses margins and limits service intensity.
Texas
Freestanding emergency center proliferation drives suburban capacity expansion outside traditional hospital footprints. State certificate-of-need exemptions permit off-campus acute care facilities to capture commercially insured demand. Dallas-Fort Worth and Houston metro corridors concentrate HCA Healthcare and Tenet Healthcare Corporation integrated ED-hospital campuses competing for high-volume trauma designation.
Florida
Retirement migration and seasonal population surges create cyclical ED demand spikes unmatched by permanent staffing. State Medicaid managed care expansion under CMS waivers broadens payer coverage for previously uninsured emergency visits. Tampa Bay and Orlando metropolitan clusters anchor Community Health Systems and AdventHealth networks expanding cardiac and stroke-capable emergency capacity.
California
Psychiatric boarding crises and medical-surgical bed scarcity degrade ED throughput metrics across safety-net facilities. CalAIM Medicaid transformation and CMS behavioral health integration mandates reshape reimbursement for emergency psychiatric stabilization. Los Angeles County and San Francisco Bay Area academic medical centers deploy telemedicine triage platforms to address neurologist and psychiatrist workforce gaps.
North Carolina
Suburban hospital networks expand cardiac ED capacity to capture rural STEMI transfers lacking percutaneous coronary intervention capability. State Medicaid expansion implementation in 2024 redraws payer mix across previously high-uncompensated-care zones. Research Triangle and Charlotte metropolitan corridors concentrate Duke Health and Atrium Health integrated emergency networks competing for comprehensive stroke center designation.
Pennsylvania
Trauma center designation competition drives 24/7 radiology and surgical specialist coverage investments to meet ACS verification standards. CMS conditions of participation for EHR interoperability mandate seamless data exchange with downstream rehabilitation and long-term acute care providers. Philadelphia and Pittsburgh urban academic medical centers anchor Level I trauma hubs receiving multisystem trauma transfers from rural Pennsylvania and neighboring West Virginia.
US Hospital Emergency Department Market Key Industry Players
Platform integrators command the system tier; component specialists sit upstream supplying discrete service capabilities. The vendor base concentrates around three distinct scale tiers: national integrated delivery networks operating across multiple states, regional hospital systems dominating single-state or adjacent-state corridors, and specialized operators focusing on discrete clinical capabilities such as trauma or pediatric emergency services. Dominant competitive moves include horizontal consolidation through hospital acquisitions and vertical integration into physician staffing and post-acute services.
Among national-scale integrated networks, HCA Healthcare anchors the high-volume metropolitan corridor tier, Tenet Healthcare Corporation occupies the specialized cardiac-trauma capability position, and Community Health Systems represents the mid-size city access-gap expansion archetype. These three entities collectively exemplify how scale, clinical specialization, and geographic fill-in strategies segment competitive positioning across the US emergency department landscape.
| Leading Market Players |
|---|
| Ascension Health |
| Lifepoint Health |
| HCA Healthcare |
| Parkland Health |
| Ardent Health Services |
| Tenet Healthcare Corporation |
| Community Health Systems |
| CHRISTUS Health |
| Universal Health Services, Inc. |
| Others |
Cost & Logistics Intelligence
Dallas-Fort Worth anchors freestanding emergency center capacity expansion, where certificate-of-need exemptions concentrate supply and amplify pricing power for commercially insured suburban corridors. This geographic supply concentration shapes downstream reimbursement negotiations and capital allocation patterns across Texas and Florida markets.
Pricing Analysis
Configured-to-order pricing for specialized trauma and cardiac capabilities commands substantial premiums over standard emergency service tiers. Three-tier pricing structure across premium trauma designation, standard community ED, and economy urgent care levels stratifies patient access by acuity and payer mix. Price differentiation hinges on Level I trauma certification and 24/7 specialist coverage availability. Pricing pressure stems from CMS site-neutral payment proposals threatening freestanding ED economics. Safety-net hospitals exhibit highest price sensitivity due to Medicaid and uninsured census concentration.
Supply Chain Analysis
Upstream feedstock for emergency department infrastructure draws from domestic medical device manufacturing clusters in Minnesota and Massachusetts, alongside imported imaging equipment from Germany and Japan. Critical inputs include CT and MRI systems, point-of-care ultrasound devices, and telemetry monitoring platforms. Single-source vulnerability concentrates in advanced imaging componentry from select German and Japanese suppliers. Distribution runs through integrated delivery network procurement consortia and group purchasing organizations serving hospital systems.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
US hospital emergency departments represent a compelling service-attach opportunity as telemedicine subscription layers and physician staffing contracts expand faster than physical infrastructure investments.
For Market Incumbents: Insulate core metropolitan positions through backward integration into emergency medicine physician staffing, reducing dependency on third-party groups. Pursue trauma center designation upgrades in high-growth exurban corridors to capture Medicaid expansion volume. Defensive consolidation should prioritize cardiac and stroke-capable facilities threatened by specialist scarcity and site-neutral payment compression.
For New Entrants and Emerging Players: Rural Mississippi and Arkansas present geographic underpenetration where neurologist and psychiatrist workforce gaps create telemedicine partnership opportunities. Target pediatric emergency capacity in midsize cities lacking dedicated children's hospital access. Deploy micro-hospital formats under 10 beds to exploit CMS flexibility for co-located emergency and inpatient services with lower capital thresholds.
For Investors and Strategic Acquirers: Carve-out targets emerge from nonprofit health systems divesting non-core emergency assets to focus on academic missions. Long-term viability favors operators with integrated payer relationships and technology-enabled workforce substitution capabilities. Monitor FDA 510(k) clearance velocity for AI-assisted triage tools as inflection indicator for reimbursement expansion.
| Strategic Initiative | Industry Significance |
|---|---|
| Telemedicine Platform Integration | CMS reimbursement parity rules accelerate virtual triage deployment across rural Mississippi and Arkansas networks. |
| Trauma Center Designation Upgrade | Level I certification captures Medicaid expansion volume and multisystem trauma transfers from regional facilities. |
| Physician Staffing Backward Integration | In-house emergency medicine groups reduce third-party dependency and stabilize labor cost volatility. |
| Micro-Hospital Format Deployment | Sub-10-bed co-located emergency and inpatient services exploit CMS site flexibility for exurban market entry. |
| AI-Assisted Triage Development | FDA 510(k) pathways for emergency diagnostic algorithms open new reimbursement channels for machine-learning tools. |
Research Approach
A standing panel of emergency medicine physicians, hospital purchasing committee chairs, GPO contracts managers, and CMS policy specialists provided ongoing calibration across the study period. Primary interviews with health system executives and freestanding ED operators combined with secondary validation against CMS Medicare cost reports, hospital procurement databases, state certificate-of-need filings, and trauma center verification records. Bottom-up facility-level capacity data triangulated against top-down payer claims analysis to establish market sizing.
Scenario-bracketing framed projections across the analysis window, modeling service type segmentation by trauma, cardiac, stroke, and pediatric capability tiers alongside delivery mode and technology platform dimensions. CAGRs derived from facility expansion pipelines, Medicaid enrollment trajectories, and telemedicine reimbursement rule implementation schedules. Forecast inputs incorporated EMTALA compliance cost structures and workforce shortage projections from emergency medicine residency match data.
Macroeconomic conditions sit as an overlay; deviation in Medicare reimbursement rates, state Medicaid expansion velocity, or specialist physician supply would shift the trajectory. Forecasts reflect documented assumptions regarding CMS site-neutral payment finalization and FDA AI diagnostic clearance timelines. Cross-checking against American College of Surgeons trauma center verification trends is advised before commitment-grade decisions.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Emergency Medical Services
Global Fixed Wing Air Ambulance Service Market
Emergency Medical Services
Urgent Care Market
Emergency Medical Services
North America Ambulance Services Market
Emergency Medical Services
Global Ambulance Market
Emergency Medical Services
Air Ambulance Market
Emergency Medical Services
US Urgent Care Centers Market
Emergency Medical Services
China First Aid Market
Emergency Medical Services
Adrenal Crisis Management Market
Emergency Medical Services
First Aid Market
Emergency Medical Services
US Emergency Medical Transportation Market
Emergency Medical Services
Global Emergency Medical Apps Market
Emergency Medical Services
US EMS Billing Services Market
Emergency Medical Services
US Freestanding Emergency Department Market
Emergency Medical Services
Europe Ambulance Services Market
Emergency Medical Services
South East Asia Ambulance Services Market
Emergency Medical Services
Global Ambulance Services Market