
 US Hospice Care Market | 2026-2036
US Hospice Care Market Size, Share, and Industry Trends Forecast 2026-2036
US Hospice Care Market Analytics
Continuous home nursing oversight is restructuring how hospice providers package and bill for end-of-life services. Amedisys leverages its home health infrastructure to cross-sell hospice admissions at the point of patient decline. Chemed Corporation anchors its VITAS Healthcare unit around urban hospital partnerships that feed high-acuity referrals. LHC Group competes through joint-venture models with nonprofit health systems, embedding hospice within accountable care networks.
Hospice care constitutes physician-directed palliative services delivered to terminally ill patients with a prognosis of six months or less, encompassing pain management, symptom control, psychosocial support, and bereavement counseling through interdisciplinary teams of nurses, social workers, chaplains, and aides. Its primary purpose is to substitute curative interventions with comfort-focused care that preserves patient autonomy and reduces unnecessary hospitalization. Home care commands the largest service-type volume due to Medicare's per-diem reimbursement bias toward routine home care days, while palliative care represents the fastest-expanding segment as health systems integrate it upstream of hospice eligibility. Residential facilities capture concentrated margin pools where room-and-board charges supplement Medicare's limited hospice housing benefit.
CMS governs hospice reimbursement through the Medicare Hospice Benefit, conditioning payment on physician certification of terminal illness and six-month prognosis, while state Medicaid agencies layer supplemental coverage for non-Medicare-eligible populations. The Office of Inspector General enforces fraud controls against inappropriate enrollment and inadequate care plans, raising compliance costs for operators. State licensure boards and the Joint Commission accreditation standards further shape staffing ratios and quality metrics that determine market access. Stakeholders must weigh the trade-off between Medicare Advantage capitation growth and fee-for-service hospice margins when designing network contracts and referral strategies.
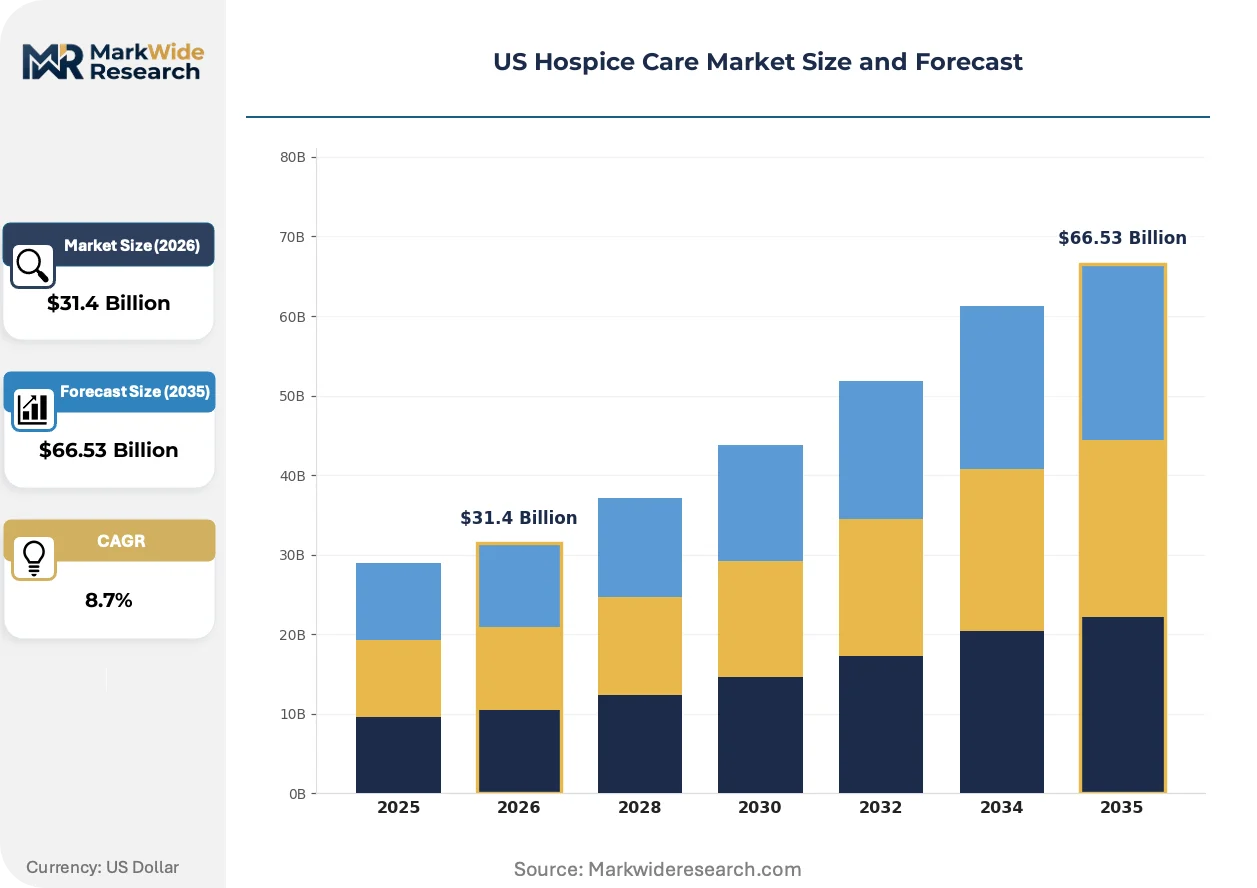
Market Dynamics
Medicare's per-diem reimbursement architecture is restructuring hospice provider economics toward routine home care density and away from institutional settings. This payment compression forces operators to optimize visit frequency, staff mix, and referral velocity to preserve margins under fixed-rate pressure.
Growth Catalysts
- Medicare Advantage expansion:MA plans now cover hospice-eligible populations through capitated arrangements, creating integrated care incentives that funnel declining patients into hospice earlier.
- Aging-in-place infrastructure:Sun Belt states have invested in home modification programs and community-based services that extend independent living, expanding the addressable hospice pool.
- Telehealth parity:CMS permanent telehealth flexibilities allow hospice physicians to conduct face-to-face recertification visits remotely, removing geographic barriers to enrollment.
Market Restraints
- Registered nurse scarcity:Hospice agencies compete with acute care hospitals for limited RN labor, inflating wage costs in competitive metropolitan markets.
- Medicare wage index compression:The CMS hospice wage index methodology underfunds providers in high-cost urban counties relative to actual staffing expenses.
- Family caregiver dependency:Routine home care requires 24/7 informal caregiver presence, excluding patients without residential support networks from community-based eligibility.
Strategic Opportunities
- Palliative care integration:Health systems are embedding palliative consults upstream of hospice eligibility, creating referral pipelines for pre-hospice revenue capture.
- Residential facility partnerships:Assisted living operators seek hospice embedment to reduce hospital transfer costs, opening margin-rich room-and-board arrangements.
- Value-based insurance design:Medicare Advantage plans experiment with hospice carve-ins that reward length-of-stay optimization and hospitalization avoidance.
Industry Challenges
- Interdisciplinary team coordination:Hospice agencies struggle to synchronize nurse, social work, chaplain, and aide schedules across dispersed home territories without sacrificing visit compliance.
- Compliance documentation burden:CMS Conditions of Participation require detailed care plan updates and physician recertification narratives that consume substantial administrative FTE capacity.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | US Hospice Care Market |
| Market Size in 2026 | $31.4 Billion |
| Market Size in 2035 | $66.53 Billion |
| CAGR (2026 – 2036) | 8.7% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: Inpatient Care, Home Care, Respite Care, Palliative Care Care Setting: Residential Facilities, Hospitals, Home, Long-Term Care Patient Type: Senior Citizens, Cancer Patients, Neurological Disorder Patients, Cardiac Patients Funding Source: Medicare, Medicaid, Private Insurance, Out-of-Pocket |
| Companies Covered | Chemed Corporation (VITAS Healthcare), Amedisys, LHC Group, Inc., Gentiva, Compassus, Chapters Health System, Brookdale Senior Living, Inc., AccentCare, Inc., Seasons Hospice & Palliative Care, Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
US Hospice Care Market Evolving Landscape
Remote patient monitoring and predictive analytics are reconfiguring how hospice agencies anticipate symptom crises and deploy clinical resources. These tools compress the gap between patient need and provider response.
Continuous remote monitoring systems is overtaking scheduled intermittent visits as the primary oversight modality for high-acuity hospice patients. Large multi-site hospice operators deploy wearable biosensors and algorithmic risk scoring to identify impending symptom escalations before emergency calls. This technology is overtaking traditional telephone triage by enabling proactive nurse dispatch and reducing after-hours crisis volume.
CMS hospice quality reporting requirements now mandate CAHPS survey participation and hospice item set submission under penalty of payment reduction. This regulatory architecture compels agencies to invest in patient experience infrastructure and data analytics capabilities. Smaller regional hospices face disproportionate compliance costs, accelerating consolidation toward scaled operators with dedicated quality departments.
Family caregiver burden is shifting hospice purchasing criteria toward respite and support service bundling. Adult children of terminally ill patients increasingly select providers based on caregiver relief offerings rather than clinical reputation alone. This preference rotation is most pronounced in suburban Sun Belt markets where multigenerational proximity is lower and formal support networks are essential.
US Hospice Care Market Segmentation
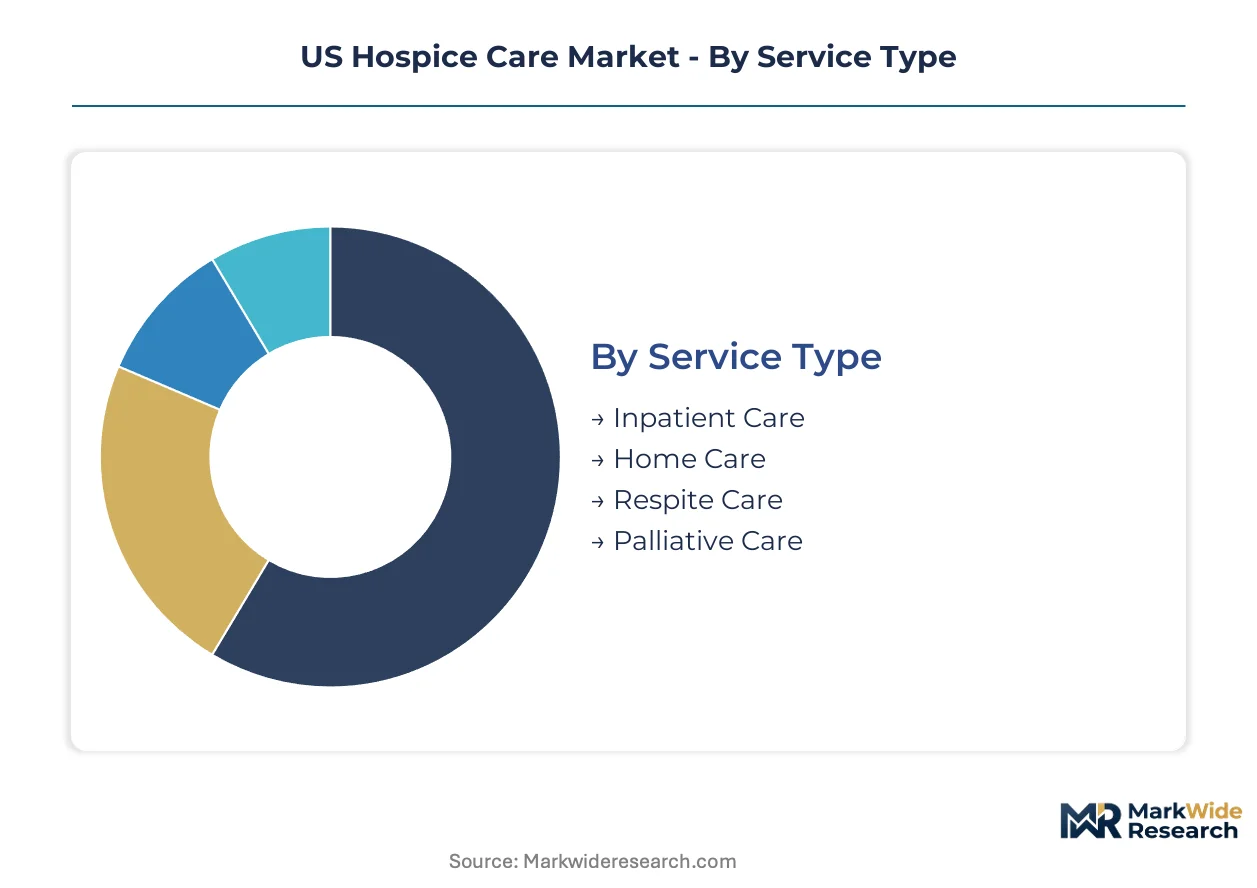
Hospice market segmentation reveals how reimbursement architecture and patient acuity reshape provider economics. Distinct service configurations, care settings, patient populations, and funding mechanisms create divergent margin profiles and operational requirements across the US hospice landscape.
Service Type:
Service type differentiation tracks Medicare reimbursement intensity and clinical labor deployment requirements across the care continuum.
- Home Care:Routine home care delivers intermittent nursing, aide, and social work visits to patients in private residences under Medicare's per-diem structure. Demand concentrates across Florida, Arizona, and Texas Sun Belt metros where aging-in-place infrastructure and Medicare Advantage penetration intersect most densely, though family caregiver dependency excludes patients lacking 24/7 residential support.
- Palliative Care:Upstream symptom management and care coordination serves patients before hospice eligibility, typically delivered through hospital consult services or outpatient clinics. Health systems in California and New York embed palliative teams to capture pre-hospice revenue and reduce emergency utilization, with CMS quality reporting mandates accelerating infrastructure investment.
- Inpatient Care:General inpatient level provides crisis symptom management requiring 24-hour nursing oversight in skilled nursing or hospice unit settings.
- Respite Care:Short-term institutional relief for family caregivers, capped at five consecutive days under Medicare benefit limits.
Home Care leads volumes today; Palliative Care is gaining share fastest.
Care Setting:
Setting selection reflects housing stability, informal caregiver availability, and proximity to institutional backup for symptom crises.
- Home:Private residences serve as the dominant care setting, enabled by Medicare's reimbursement bias toward routine home care days and telehealth flexibilities for physician recertification. Patient preference for autonomy and lower cost structures relative to institutional alternatives sustain this concentration, though geographic nursing scarcity in urban markets strains visit compliance.
- Residential Facilities:Assisted living and skilled nursing facilities embed hospice services to reduce hospital transfer costs and capture room-and-board margin pools. Partnerships between hospice agencies and facility operators concentrate in suburban Sun Belt markets where operator consolidation creates preferred vendor relationships.
- Hospitals:Acute care settings provide general inpatient and crisis respite levels, with urban hospital partnerships feeding high-acuity referrals to specialized hospice units.
- Long-Term Care:Nursing facilities serve dual-eligible populations with complex symptom management needs beyond family caregiver capacity.
Home dominates admission counts; Residential Facilities show the steepest expansion trajectory among institutional alternatives.
Patient Type:
Patient type segmentation aligns hospice enrollment with disease trajectory predictability and interdisciplinary team specialization requirements.
- Senior Citizens:Adults aged 65 and above constitute the core hospice population, with multiple comorbidities and functional decline driving six-month prognosis certifications. Medicare eligibility and aging demographics across US retirement corridors sustain volume concentration, though cognitive impairment complicates pain assessment and symptom reporting.
- Cancer Patients:Oncologic diagnoses with predictable decline curves historically anchored hospice enrollment, with physician familiarity facilitating timely referrals. Community-based oncology practices in metropolitan markets increasingly embed hospice liaisons to manage care transitions.
- Neurological Disorder Patients:ALS, Parkinson's disease, and advanced dementia require specialized symptom protocols and extended length-of-stay management.
- Cardiac Patients:Congestive heart failure and terminal cardiovascular disease present fluctuating trajectories that challenge prognosis accuracy and enrollment timing.
Senior Citizens anchor admission volumes; Neurological Disorder Patients are expanding most quickly as dementia prevalence rises.
Funding Source:
Funding source segmentation determines reimbursement mechanics, prior authorization burden, and patient cost-sharing exposure.
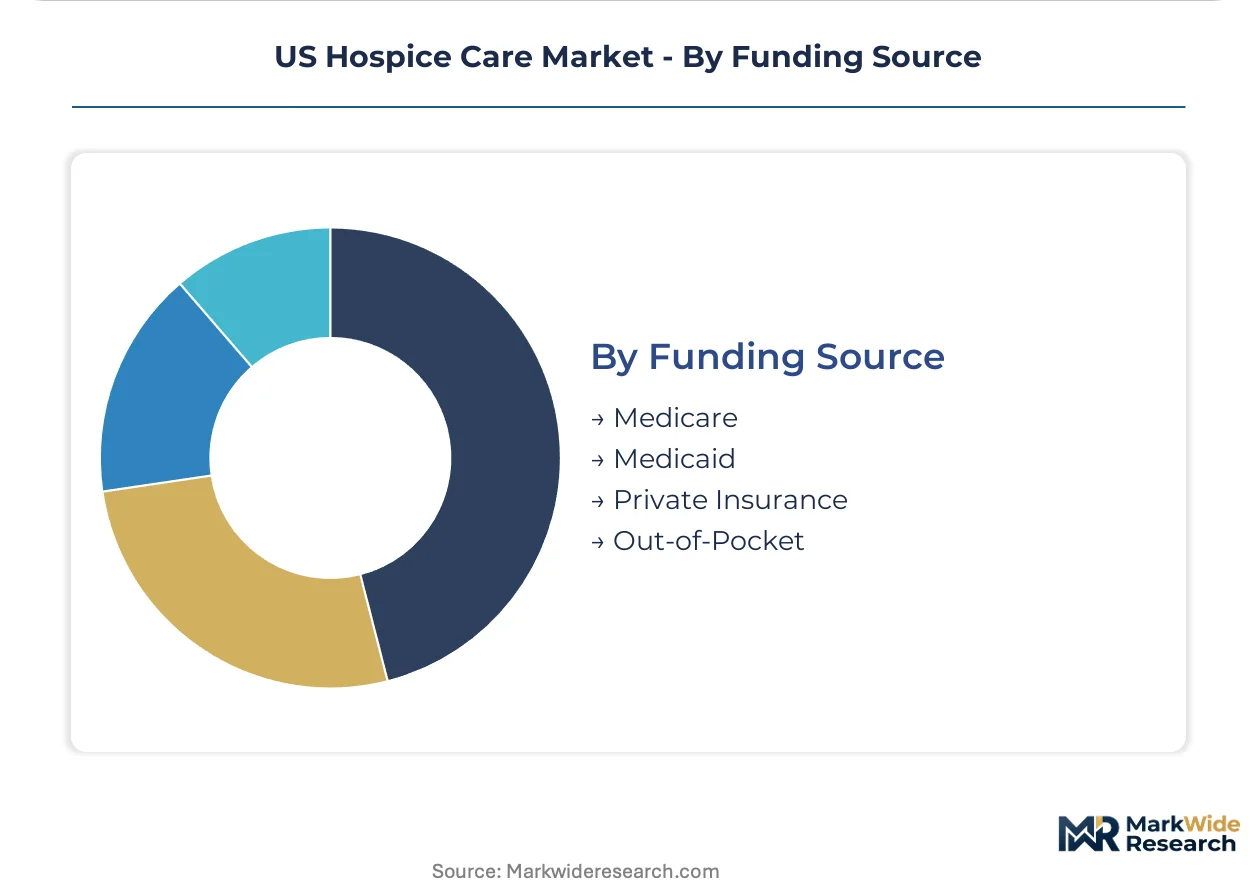
- Medicare:The Medicare Hospice Benefit covers 85% of US hospice days through per-diem payments conditioned on physician terminal prognosis certification. CMS Conditions of Participation govern staffing ratios and quality reporting, with Medicare Advantage capitation experiments in California and Florida reshaping network contracting incentives.
- Medicaid:State-administered supplemental coverage extends eligibility to non-Medicare populations including younger disabled adults and dual-eligible seniors. State variation in hospice benefit design creates administrative complexity for multi-state operators.
- Private Insurance:Employer-sponsored and individual market plans replicate Medicare benefit structures with variable prior authorization requirements.
- Out-of-Pocket:Direct payment for non-covered services including room-and-board in residential settings and extended respite beyond Medicare limits.
Medicare dominates funding flows; Medicare Advantage carve-ins are climbing the fastest among payment mechanisms.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Florida's Medicare Advantage penetration outpaces California's hospice density, yet both Sun Belt states confront identical RN scarcity constraints that compress visit compliance margins.
Florida
Aging-in-place infrastructure and snowbird retirement migration concentrate hospice demand across Tampa Bay and Orlando metros. State Medicaid agencies administer supplemental hospice benefits for dual-eligible populations under federal CMS partnership frameworks. Miami-Dade and Broward counties host assisted living consolidation that creates preferred vendor relationships with embedded hospice operators.
California
Health systems in Los Angeles and San Francisco embed palliative consult services upstream of hospice eligibility to capture pre-hospice revenue streams. CMS Conditions of Participation govern staffing ratios and quality reporting mandates that shape operator compliance costs. The Bay Area's technology sector drives telehealth adoption for remote physician recertification visits.
Texas
Houston and Dallas-Fort Worth hospital partnerships feed high-acuity referrals to specialized hospice units serving cancer and cardiac patient populations. Medicare's per-diem reimbursement architecture biases provider economics toward routine home care density. Austin's medical corridor attracts joint-venture models between for-profit agencies and nonprofit health systems.
Arizona
Phoenix and Tucson retirement communities generate concentrated demand for residential facility partnerships that reduce hospital transfer costs. State licensure boards enforce staffing ratio requirements that determine market access for new entrants. Maricopa County's assisted living operator consolidation accelerates preferred hospice embedment arrangements.
US Hospice Care Market Competitive Landscape
Top-tier vendors anchor multi-state home health infrastructure, while regional specialists compete through hospital partnership density and joint-venture models with nonprofit systems. The vendor base stratifies across three archetypes: integrated home health-hospice platforms, pure-play hospice operators, and senior living embedment specialists. Consolidation accelerates through Medicare Advantage network contracting and palliative care upstream integration.
Within the integrated platform tier, Amedisys and LHC Group exemplify cross-selling architectures that leverage home health footprints for hospice conversion at patient decline points. Chemed Corporation's VITAS Healthcare unit occupies a distinct position anchored around urban hospital referral relationships. These three entities represent divergent strategic bets on channel control versus institutional partnership density.
| Leading Market Players |
|---|
| Chemed Corporation (VITAS Healthcare) |
| Amedisys |
| LHC Group, Inc. |
| Gentiva |
| Compassus |
| Chapters Health System |
| Brookdale Senior Living, Inc. |
| AccentCare, Inc. |
| Seasons Hospice & Palliative Care |
| Others |
Value Network & Pricing Analysis
Medicare Advantage plans concentrate purchasing power across Sun Belt states, anchoring hospice reimbursement to CMS per-diem schedules that compress margins toward routine home care density. This buyer archetype consolidation forces providers to optimize visit frequency and staff mix under fixed-rate pressure.
Pricing Analysis
Capacity additions in Florida and Texas are reshaping price floors as new entrants compete for Medicare Advantage network contracts. Pricing stratifies across nonprofit health system joint ventures, for-profit multi-site operators, and regional specialists, with differentiation driven by telehealth integration depth and interdisciplinary team certification levels. Cost compression in high-wage urban counties intensifies because CMS wage index methodology underfunds actual staffing expenses. Medicare Advantage plans exhibit highest price sensitivity, while self-funded employer plans show lowest.
Supply Chain Analysis
Freight costs for medical equipment and pharmaceutical supplies exert limited pressure on hospice economics given the service-intensive nature of care delivery. Clinical labor draws from US-based registered nurse pools concentrated in Sun Belt retirement corridors, with registered nurse scarcity in Arizona and Nevada creating single-source vulnerability for visit compliance. Medical supply distribution runs through group purchasing organizations serving hospital-affiliated hospice units. Supply chain risk centers on registered nurse wage inflation in competitive metropolitan markets.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Geographic arbitrage between high-Medicare-Advantage-penetration Florida and underserved rural Midwest markets exploits reimbursement rate differentials and labor cost spreads. State Medicaid supplemental benefit variations create additional regulatory-driven margin opportunities.
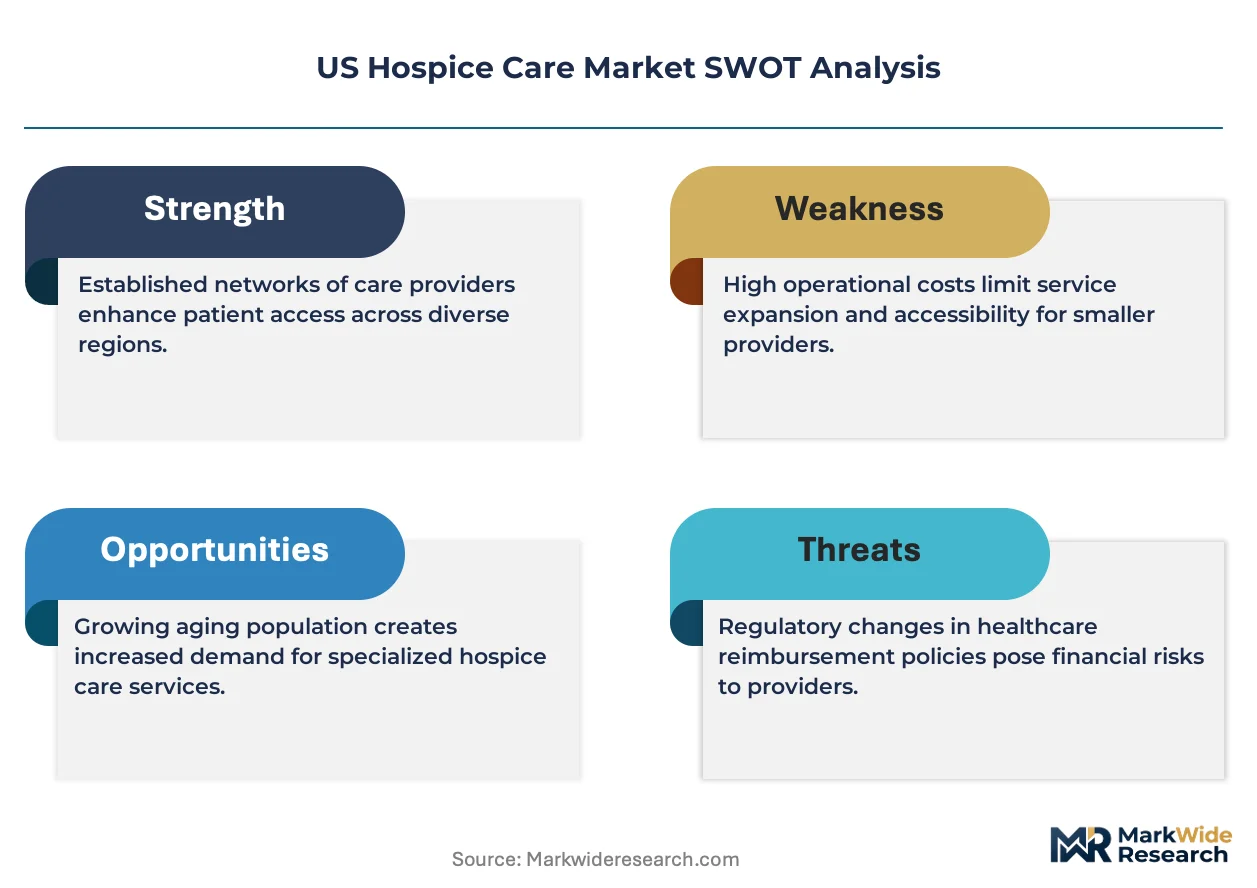
For Market Incumbents: Acquire home health infrastructure to cross-sell hospice admissions at patient decline points. Consolidate registered nurse labor pools through geographic clustering in Sun Belt metros to defend against wage inflation. Secure preferred vendor status with assisted living operators undergoing consolidation. For New Entrants and Emerging Players: Rural Medicare fee-for-service counties present the most penetrable geography, where family caregiver dependency excludes patients from community-based eligibility and institutional alternatives command premium pricing. Target cardiac and neurological disorder patient populations with extended length-of-stay profiles. Pursue hospital partnership embedment as primary go-to-market channel. For Investors and Strategic Acquirers: Private equity platforms with home health holdings are the most active acquirer in this space, seeking hospice assets for care continuum integration. Five-to-ten-year viability hinges on Medicare Advantage carve-in adoption velocity. Watch for CMS telehealth flexibility permanence rulings as inflection signal for remote care model scalability.| Strategic Initiative | Industry Significance |
|---|---|
| Palliative Care Integration | Health systems embed upstream consult services to capture pre-hospice revenue and reduce emergency utilization. |
| Residential Facility Partnership | Assisted living operators seek hospice embedment to reduce hospital transfer costs and capture room-and-board margins. |
| Telehealth Infrastructure Investment | CMS permanent flexibilities enable remote physician recertification, removing geographic barriers to enrollment. |
| Joint Venture with Nonprofit Systems | LHC Group model embeds hospice within accountable care networks for referral pipeline security. |
| Quality Reporting Capability Buildout | CAHPS survey participation and hospice item set submission become mandatory under CMS penalty structures. |
Research Methodology
Bottom-up patient volume modeling reconciled against top-down Medicare claims tracking forms the analytical core of this study. Primary interviews with hospice agency executives, Medicare Advantage contracting officers, registered nurse staffing directors, and assisted living operator procurement leads combine with secondary validation from CMS Medicare cost reports, state Medicaid hospice benefit filings, hospital procurement databases, and OIG fraud enforcement records.
Historical trendline analysis across routine home care days, general inpatient levels, and continuous care episodes establishes baseline growth patterns. Segmentation dimensions modeled include service type, care setting, patient diagnosis category, and funding mechanism across the projection horizon. CAGRs derive from patient demographic projections, Medicare Advantage penetration trajectories, and registered nurse supply elasticity estimates.
Underlying measurement precision varies by segment; Medicare-certified agency data carries tighter precision than non-certified community-based programs. Forecasts reflect assumptions regarding CMS reimbursement stability and Medicare Advantage network expansion velocity. Stakeholders should weight assumptions against their own operating context.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Healthcare Services
In-Home Senior Care Franchises Market
Healthcare Services
US Hospice Market
Healthcare Services
Global Hospice Care Market
Healthcare Services
US Care Services Market
Healthcare Services
Primary Care Physicians Market
Healthcare Services
Eastern Europe Online Pharmacy Market
Healthcare Services
United States Senior Living Market
Healthcare Services
Biopharmaceutical Third Party Logistics (3PL) Market
Healthcare Services
Asia-Pacific Healthcare Staffing Market
Healthcare Services
Canada Corporate Wellness Market
Healthcare Services
Healthcare Cold Chain Logistics Market
Healthcare Services
North America Healthcare Cold Chain Logistics Market
Healthcare Services
Global Healthcare Contract Development and Manufacturing Organization Market
Healthcare Services
Medical Devices and Equipment Logistics Market
Healthcare Services
Chronic Disease Management Service Market
Healthcare Services
Healthcare Revenue Cycle Management (RCM) Outsourcing Market