
 US Freestanding Emergency Department Market | 2026-2036
US Freestanding Emergency Department Market Size, Share, and Industry Trends Forecast 2026-2036
US Freestanding Emergency Department Market Intelligence
Emergency medicine physician staffing is rotating toward a hybrid model combining on-site intensivists with remote telemedicine coverage, easing recruitment bottlenecks in secondary markets. HCA Healthcare leverages its scale to sustain 24/7 specialist rosters across multiple freestanding sites in overlapping catchment areas. Envision Healthcare competes through its national emergency physician staffing contracts, while Emerus Hospital Partners, LLC. anchors joint-venture development with regional health systems seeking capital-light expansion.
A freestanding emergency department operates as a licensed emergency care facility physically detached from a hospital campus, typically equipped with CT scanners, ultrasound, and laboratory services capable of stabilizing patients before transfer. These facilities accept all emergency patients regardless of ability to pay and must meet state-level emergency department licensing standards equivalent to hospital-based units. Urgent care within the service type segment leads volume throughput due to lower acuity presentations and faster door-to-discharge times. Diagnostic imaging commands disproportionate margin contribution given the capital intensity of on-site CT and MRI suites relative to reimbursement rates.
CMS, state departments of health, and The Joint Commission govern facility licensing, reimbursement eligibility, and accreditation standards for freestanding emergency departments operating outside hospital campuses. CMS site-neutral payment policies directly constrain revenue per visit for facilities opened after 2015, while state certificate-of-need laws in roughly two-thirds of US states block or channel greenfield development. Stakeholders must monitor evolving state Medicaid expansion decisions and CMS 340B drug pricing litigation, as both will alter the economic viability of freestanding emergency services in underserved counties.
Market Dynamics
CMS site-neutral payment policies are compressing reimbursement differentials between hospital-based and off-campus emergency departments, forcing capital deployment toward lower-acuity service lines and telemedicine integration.
Growth Catalysts
- Rural hospital closures:Medicare and Medicaid patients in underserved counties seek accessible emergency stabilization without inpatient transfer capacity.
- Telemedicine credentialing frameworks:State medical boards are standardizing interstate physician licensing, enabling remote specialist coverage across multiple freestanding sites.
- Texas certificate-of-need exemptions:The state permits greenfield emergency facility development without capacity demonstration, accelerating permit issuance relative to restricted markets.
Market Restraints
- CMS site-neutral payment cuts:Facilities opened after 2015 face Medicare reimbursement rates capped at 40% below hospital-based equivalents.
- Imaging equipment supply concentration:CT and MRI suite procurement depends on concentrated OEM channels with extended lead times.
- Specialist recruitment bottlenecks:Emergency medicine board-certified physicians cluster in urban academic centers, leaving secondary markets understaffed.
Strategic Opportunities
- Medicaid expansion tailwinds:States adopting expansion increase eligible patient volumes for emergency services in rural counties.
- Micro-hospital convergence:Hybrid models combining freestanding emergency departments with 8-10 inpatient beds capture transfer-avoidance revenue.
- Value-based emergency care contracts:Medicare Advantage plans are piloting episode-based reimbursement for emergency stabilization and appropriate diversion.
Industry Challenges
- Physician scheduling complexity:24/7 intensivist coverage across geographically dispersed sites requires sophisticated labor optimization platforms.
- EHR interoperability gaps:Freestanding sites struggle with bidirectional data exchange to receiving hospitals during patient transfer.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | US Freestanding Emergency Department Market |
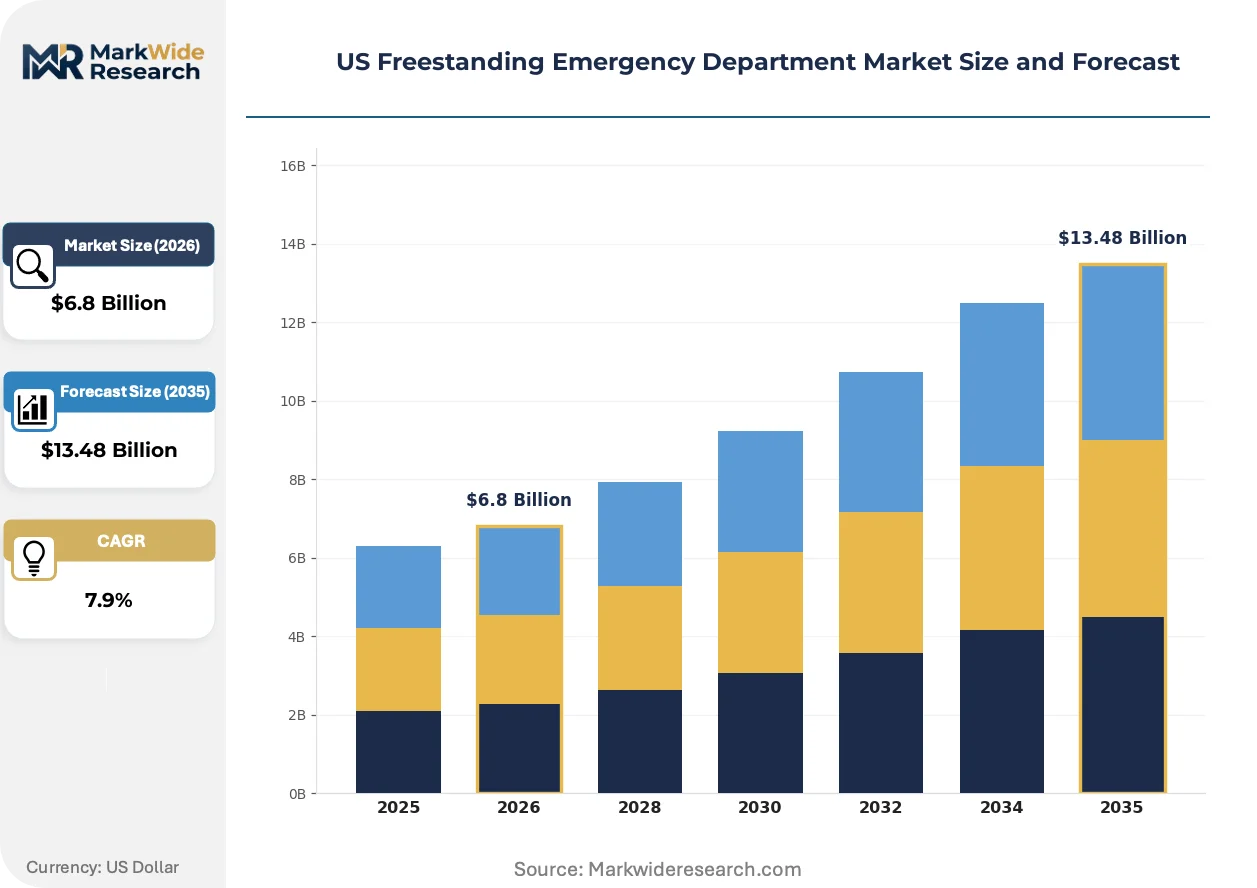
| Market Size in 2026 | $6.8 Billion |
| Market Size in 2035 | $13.48 Billion |
| CAGR (2026 – 2036) | 7.9% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: Urgent Care, Surgical Services, Pediatric Care, Diagnostic Imaging End User: Insurance Companies, Patients, Healthcare Providers, Government Agencies Technology: Telemedicine Solutions, Electronic Health Records, AI Diagnostics, Wearable Devices Application: Trauma Care, Cardiac Emergencies, Respiratory Issues, Behavioral Health |
| Companies Covered | Universal Health Services, Inc., Emerus Hospital Partners, LLC., HCA Healthcare, Envision Healthcare, Community Health Systems, Ascension, CHRISTUS Health, AdventHealth, Tenet Healthcare, Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
US Freestanding Emergency Department Market Strategic Shifts & Innovations
Point-of-care diagnostics and remote patient monitoring are compressing the traditional emergency department footprint, enabling decentralized care delivery in smaller physical formats.
Portable ultrasound systems with AI-assisted image interpretation are miniaturizing diagnostic capabilities previously requiring fixed radiology suites. Freestanding emergency departments in Texas and Florida are deploying handheld devices for FAST exams and cardiac imaging. This technology is miniaturizing capital requirements, allowing facilities under 10,000 square feet to achieve diagnostic parity with hospital-based units.
CMS Conditions of Participation updates are mandating real-time electronic patient event reporting to receiving hospitals. The rule compels freestanding operators to invest in health information exchange infrastructure or risk Medicare decertification. Facilities in certificate-of-need states face additional state health department reporting layers, creating compliance cost divergence across jurisdictions.
Patients with commercial insurance are bypassing freestanding emergency departments for urgent care chains advertising transparent pricing. Employer-sponsored health plans in Ohio are steering members toward preferred urgent care networks through differential copay structures. This channel migration is most pronounced in suburban markets where urgent care density exceeds freestanding emergency department penetration.
US Freestanding Emergency Department Market Segmentation
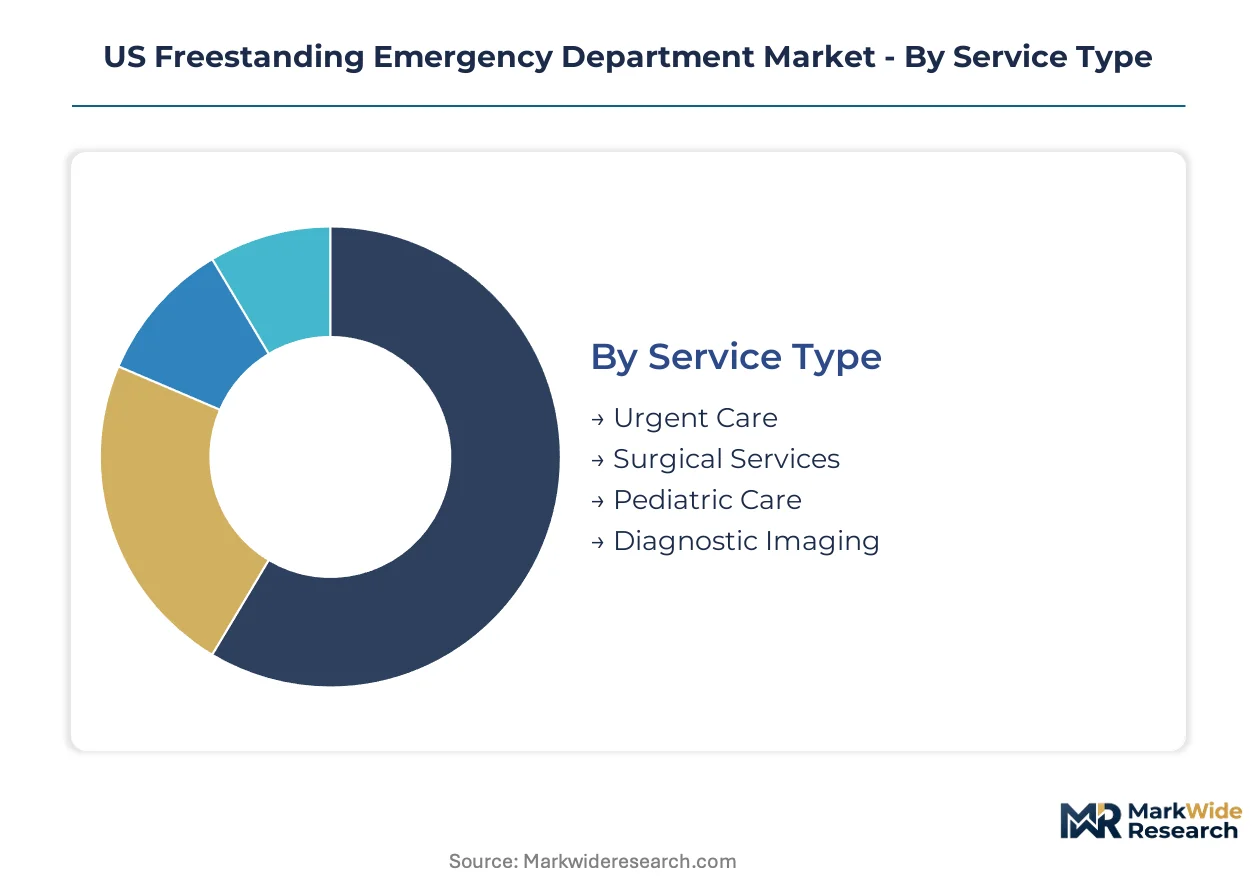
Segmentation reveals how freestanding emergency departments allocate capital across service intensity levels and patient acuity tiers. Each category exposes distinct reimbursement dynamics and operational constraints that shape facility design and staffing models.
Service Type:
Geographic deployment varies sharply by service intensity, with high-acuity offerings concentrating in hospital-affiliated networks while lower-acuity lines penetrate exurban markets independently.
- Urgent Care:Delivers non-life-threatening treatment for fractures, infections, and minor lacerations with door-to-discharge targets under 60 minutes. Volume concentrates in Texas and Florida suburban corridors where certificate-of-need exemptions permit rapid site proliferation; CMS site-neutral cuts bite less severely here due to lower baseline reimbursement.
- Diagnostic Imaging:Houses fixed CT, MRI, and ultrasound suites generating disproportionate margin contribution relative to square footage. Ohio and secondary Texas markets favor this segment for transfer-avoidance revenue when rural hospital closures eliminate local radiology access.
- Surgical Services:Limited operative capabilities for appendectomy, abscess drainage, and wound repair requiring 23-hour observation capacity.
- Pediatric Care:Dedicated pediatric emergency physicians and weight-based equipment protocols for patients under 18.
Urgent Care holds the largest share; momentum sits with Diagnostic Imaging.
End User:
Cost tier stratification drives divergent facility positioning, with premium reimbursement from commercial payers enabling advanced imaging while Medicaid-dependent sites minimize capital intensity.
- Healthcare Providers:Hospital systems and physician groups operating joint-venture facilities capture downstream admission revenue and specialist referral volume. HCA Healthcare and Emerus Hospital Partners dominate this channel in Texas through overlapping catchment area strategies.
- Patients:Direct-pay and high-deductible commercial patients select facilities based on transparent pricing and proximity; steering by employer-sponsored plans in Ohio channels this segment toward urgent care alternatives.
- Insurance Companies:Medicare Advantage plans pilot episode-based emergency reimbursement, demanding real-time utilization data from contracted facilities.
- Government Agencies:Medicaid expansion states generate eligible volume in rural counties; CMS Conditions of Participation mandate electronic reporting infrastructure.
Healthcare Providers anchor volume; Patients represent the steepest expansion trajectory as deductible burdens rise.
Technology:
Application maturity separates proven platforms with immediate ROI from emerging tools requiring regulatory clearance and workflow redesign.
- Electronic Health Records:Core infrastructure for CMS compliance and bidirectional data exchange with receiving hospitals during patient transfer. EHR interoperability gaps persist in certificate-of-need states with additional state reporting layers.
- Telemedicine Solutions:Remote specialist coverage enables 24/7 intensivist availability across geographically dispersed sites; state medical board standardization of interstate licensing accelerates deployment in Florida and Texas.
- AI Diagnostics:Algorithm-assisted image interpretation for portable ultrasound and chest X-ray triage.
- Wearable Devices:Remote patient monitoring for post-discharge surveillance and chronic condition flare detection.
Electronic Health Records dominate installed base; Telemedicine Solutions climb the fastest as labor costs escalate.
Application:
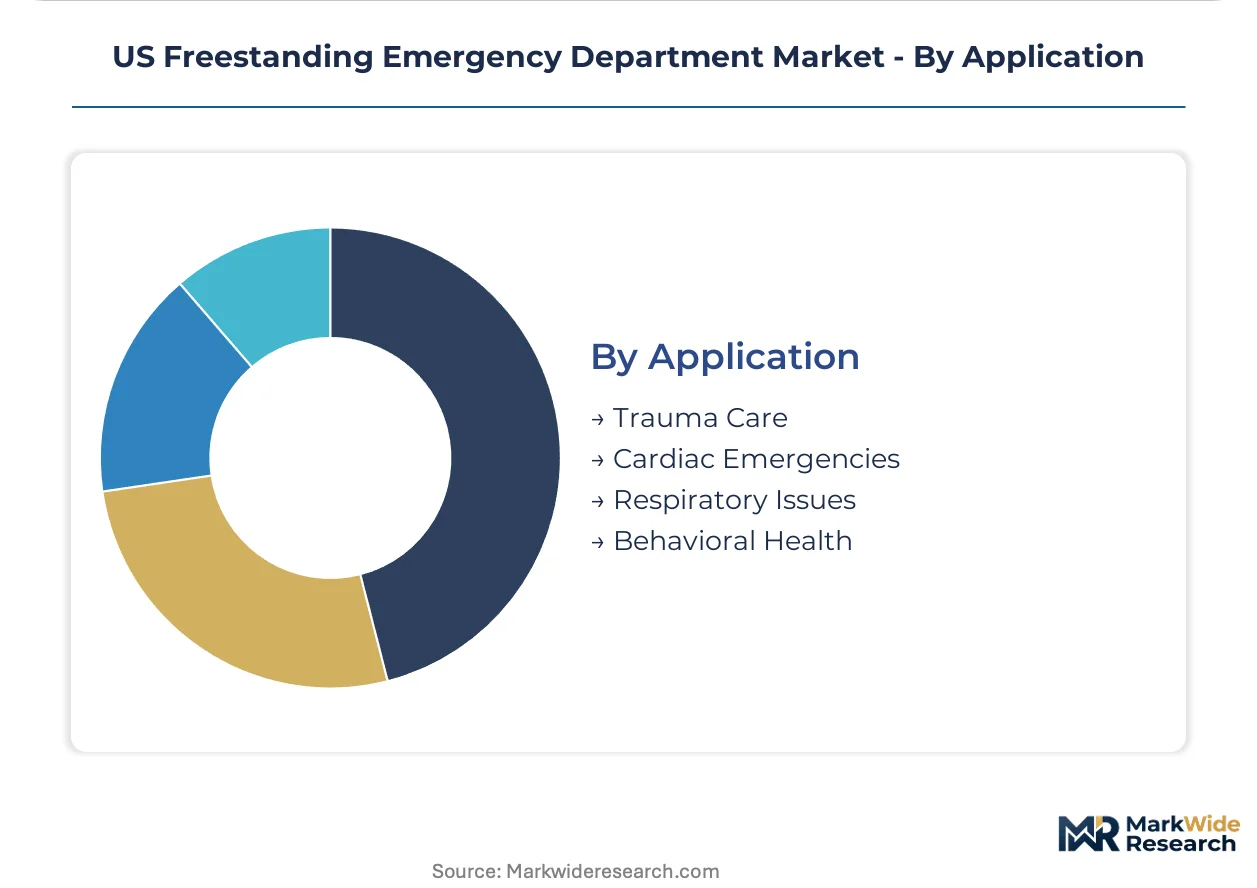
Volume concentration aligns with epidemiological patterns and regional disease burden, with cardiac and trauma presentations commanding higher reimbursement per encounter.
- Trauma Care:Stabilization of severe injuries requiring immediate hemorrhage control and rapid transfer to Level I trauma centers. Demand clusters along Texas highway corridors and Florida retirement communities where fall risk and motor vehicle incidents concentrate.
- Cardiac Emergencies:Chest pain protocols, ECG interpretation, and thrombolytic administration within door-to-needle windows. Rural Ohio counties with hospital closures depend on freestanding sites for acute myocardial infarction stabilization.
- Respiratory Issues:Asthma exacerbation, COPD decompensation, and pneumonia management with point-of-care testing.
- Behavioral Health:Psychiatric crisis evaluation and chemical dependency assessment with 24-hour hold capability.
Trauma Care captures the highest per-visit revenue; Behavioral Health gains share fastest as inpatient psychiatric bed scarcity worsens.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
CMS site-neutral payment policies anchor facility economics across the United States, with state-level certificate-of-need laws creating stark geographic variation in development velocity. Texas, Florida, and Ohio concentrate construction permits and operational licenses.
Texas
Rural hospital closures in the Panhandle and West Texas drive Medicare patient migration toward off-campus emergency stabilization. The state health department exempts freestanding emergency departments from certificate-of-need requirements, accelerating permit issuance relative to restricted markets. Dallas-Fort Worth and Houston suburban corridors host overlapping catchment area strategies by hospital-affiliated networks.
Florida
Retirement community density and fall-risk trauma presentations concentrate demand along the Gulf and Atlantic coasts. State medical board standardization of interstate physician licensing enables remote specialist coverage across geographically dispersed sites. The Tampa-Orlando corridor leads portable ultrasound deployment with AI-assisted image interpretation for cardiac and FAST exams.
Ohio
Employer-sponsored health plans steer commercial patients toward urgent care alternatives through differential copay structures, compressing freestanding emergency volume in suburban Columbus and Cleveland markets. Rural counties with hospital closures depend on these facilities for acute myocardial infarction stabilization. The state maintains certificate-of-need restrictions that channel development toward medically underserved areas.
California
Medicaid expansion generates eligible patient volumes in Central Valley and Inland Empire counties with limited inpatient capacity. Office of Statewide Health Planning and Development licensing requirements exceed federal CMS Conditions of Participation, elevating compliance costs. Los Angeles and San Diego metro areas concentrate pediatric-dedicated freestanding emergency capacity.
North Carolina
Mountain region hospital closures create access gaps filled by stabilization-focused facilities in Asheville and Boone corridors. State certificate-of-need laws block greenfield development without capacity demonstration, limiting permit velocity relative to Texas. Research Triangle health systems deploy joint-venture models with national staffing firms to secure 24/7 intensivist coverage.
US Freestanding Emergency Department Market Key Industry Players
Technology leadership and cost leadership are held by different player archetypes across the US freestanding emergency department market. Hospital-affiliated networks leverage downstream admission revenue to subsidize 24/7 specialist rosters, while physician staffing firms compete through national credentialing platforms and labor optimization. Three archetypes dominate: integrated health systems with overlapping catchment strategies, joint-venture developers seeking capital-light expansion, and national staffing contractors supplying remote coverage. Competitive moves concentrate on strategic partnerships for geographic density and telemedicine infrastructure deployment to ease recruitment bottlenecks.
Within the integrated health system tier, HCA Healthcare exemplifies scale-driven multi-site coordination across Texas markets. Emerus Hospital Partners, LLC. occupies a position as the dominant joint-venture developer anchoring regional health system expansion. Envision Healthcare represents the national staffing contractor archetype, supplying emergency physician coverage through interstate licensing frameworks.
| Leading Market Players |
|---|
| Universal Health Services, Inc. |
| Emerus Hospital Partners, LLC. |
| HCA Healthcare |
| Envision Healthcare |
| Community Health Systems |
| Ascension |
| CHRISTUS Health |
| AdventHealth |
| Tenet Healthcare |
| Others |
Cost & Logistics Intelligence
Take-or-pay staffing contracts with national physician groups lock in labor cost visibility for multi-site operators while insulating against spot-market rate volatility in secondary Texas and Florida markets. These arrangements tether reimbursement stability to CMS site-neutral policy exposure, forcing capital-light entrants toward urgent care adjacencies where pricing compression is less severe.
Pricing Analysis
Price spreads between suburban Dallas-Fort Worth and rural Panhandle facilities exceed 35% for equivalent cardiac stabilization encounters due to commercial payer density differentials. Three-tier pricing structure across hospital-affiliated premium sites, independent standard facilities, and micro-hospital economy models stratifies patient access by insurance status. Pricing pressure stems from employer-sponsored plans in Ohio steering members toward urgent care networks through tiered copay differentials. Medicaid-dependent rural counties exhibit highest price sensitivity, while commercially insured suburban corridors tolerate premium imaging surcharges.
Supply Chain Analysis
Extended lead times for CT and MRI suites from concentrated German and Japanese OEM channels stretch 14-18 months, constraining rapid deployment in certificate-of-need exempt markets. Imaging equipment procurement draws from single-source dependencies for helium-cooled magnets and rare-earth detector components. Tariff exposure on Chinese-sourced radiology accessories creates margin vulnerability for capital-constrained independents. Distribution runs through regional medical equipment lessors who bundle installation, maintenance, and compliance certification into per-scan revenue share arrangements.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Incumbents must defend against urgent care chain substitution as employer-sponsored benefit designs increasingly divert low-acuity volume away from freestanding emergency facilities.
For Market Incumbents: Secure overlapping catchment area density in Texas certificate-of-need exempt corridors to preempt competitor site acquisition and sustain specialist roster economies. Anchor joint-venture partnerships with regional health systems seeking capital-light expansion, using downstream admission revenue to offset CMS site-neutral reimbursement compression. Vertical integration into telemedicine credentialing platforms mitigates intensivist recruitment bottlenecks threatening 24/7 coverage mandates. For New Entrants and Emerging Players: Joint Commission accreditation fast-track programs enable rapid licensure in Florida retirement corridors where fall-risk trauma demand outpaces supply. White-space concentration sits with pediatric-dedicated micro-hospital formats in California Central Valley counties lacking inpatient pediatric capacity. Medicaid expansion states generate eligible volume in rural Ohio counties with recent hospital closures, accessible through GPO contracting relationships rather than direct payer negotiation. For Investors and Strategic Acquirers: Capital is best deployed toward hospital-affiliated network archetypes with proven transfer-avoidance revenue capture and existing CMS Conditions of Participation infrastructure. Long-term viability hinges on positioning for Medicare Advantage episode-based reimbursement pilots expanding across the analysis window. Monitor state Medicaid expansion decisions as the critical inflection signal for rural county volume trajectory.| Strategic Initiative | Industry Significance |
|---|---|
| Telemedicine Infrastructure Deployment | Remote intensivist coverage enables 24/7 specialist availability across geographically dispersed Texas and Florida sites. |
| Micro-Hospital Format Development | Hybrid 8-10 bed models capture transfer-avoidance revenue in rural Ohio counties with hospital closures. |
| Joint Venture Partnership Structuring | Capital-light expansion with Emerus Hospital Partners, LLC. accelerates market entry in certificate-of-need restricted states. |
| Point-of-Care Diagnostic Miniaturization | Portable ultrasound with AI-assisted interpretation reduces capital intensity for facilities under 10,000 square feet. |
| Health Information Exchange Investment | CMS-mandated real-time reporting infrastructure prevents Medicare decertification risk in bidirectional patient transfer protocols. |
Research Approach
Initial hypotheses were tested against primary input from emergency medicine physician group executives, hospital system strategy officers, state health department licensing directors, and GPO contracts managers and refined through secondary validation. CMS Medicare cost reports, state certificate-of-need filing databases, The Joint Commission accreditation records, and hospital procurement databases anchored quantitative triangulation. Bottom-up site-level capacity modeling and top-down reimbursement flow analysis converged on volume and value estimates.
Variance decomposition across service type, end user cost tier, technology maturity, and application acuity segments structured the analytical framework. CAGRs were derived from modeled encounter volume growth and reimbursement rate trajectories across the projection horizon. Site-neutral payment policy phase-in schedules, rural hospital closure velocity by county, and telemedicine licensure standardization progress served as industry-specific forecast inputs.
Underlying assumptions cover CMS reimbursement stability, state Medicaid expansion continuity, and OEM equipment delivery schedules, with deviation risk concentrated in 340B drug pricing litigation outcomes and interstate physician licensing harmonization setbacks. Outputs are directional rather than point-estimates.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Emergency Medical Services
Global Fixed Wing Air Ambulance Service Market
Emergency Medical Services
Air Ambulance Services Market
Emergency Medical Services
Resuscitation Trolley Market
Emergency Medical Services
Emergency Medical Services Market
Emergency Medical Services
South East Asia Ambulance Services Market
Emergency Medical Services
First Aid Market
Emergency Medical Services
Patient Transport Services Market
Emergency Medical Services
Europe Ambulance Services Market
Emergency Medical Services
Global Ambulance Market
Emergency Medical Services
Global Emergency Medical Apps Market
Emergency Medical Services
US EMS Billing Services Market
Emergency Medical Services
Adrenal Crisis Management Market
Emergency Medical Services
Global Ambulance Stretchers Market
Emergency Medical Services
Emergency Medical Supplies Market
Emergency Medical Services
Global Ambulance Services Market
Emergency Medical Services
Chest Compressors Market