
 US Birth Centers Market | 2026-2036
US Birth Centers Market Size, Share, and Industry Trends Forecast 2026-2036
US Birth Centers Market Insights
Certified nurse-midwife availability is redrawing competitive boundaries across the US birth center landscape. Cedars-Sinai Medical Center leverages its Los Angeles footprint to anchor premium hospital-affiliated center capacity. The Mother Baby Center competes through Minneapolis-St. Paul geographic dominance. TriStar Centennial Women's and Children's Hospital specializes in integrated perinatal pathways spanning prenatal through neonatal handoff.
Birth centers constitute licensed healthcare facilities providing low-risk maternity care outside conventional acute hospital settings, typically featuring homelike environments with hydrotherapy tubs, telemetry-capable recovery suites, and immediate operating room access protocols. These centers serve the dual commercial purpose of reducing cesarean delivery rates while capturing bundled reimbursement from commercial payers and Medicaid managed care organizations. Hospital-affiliated centers command the largest revenue pool by combining payer contracting scale with freestanding center aesthetics. Freestanding centers represent the fastest-growing care setting as state certificate-of-need relaxations enable independent midwifery practice expansion. Midwifery services generate the steadiest margin profile through recurring prenatal visit cadences and lower malpractice exposure relative to surgical birth interventions.
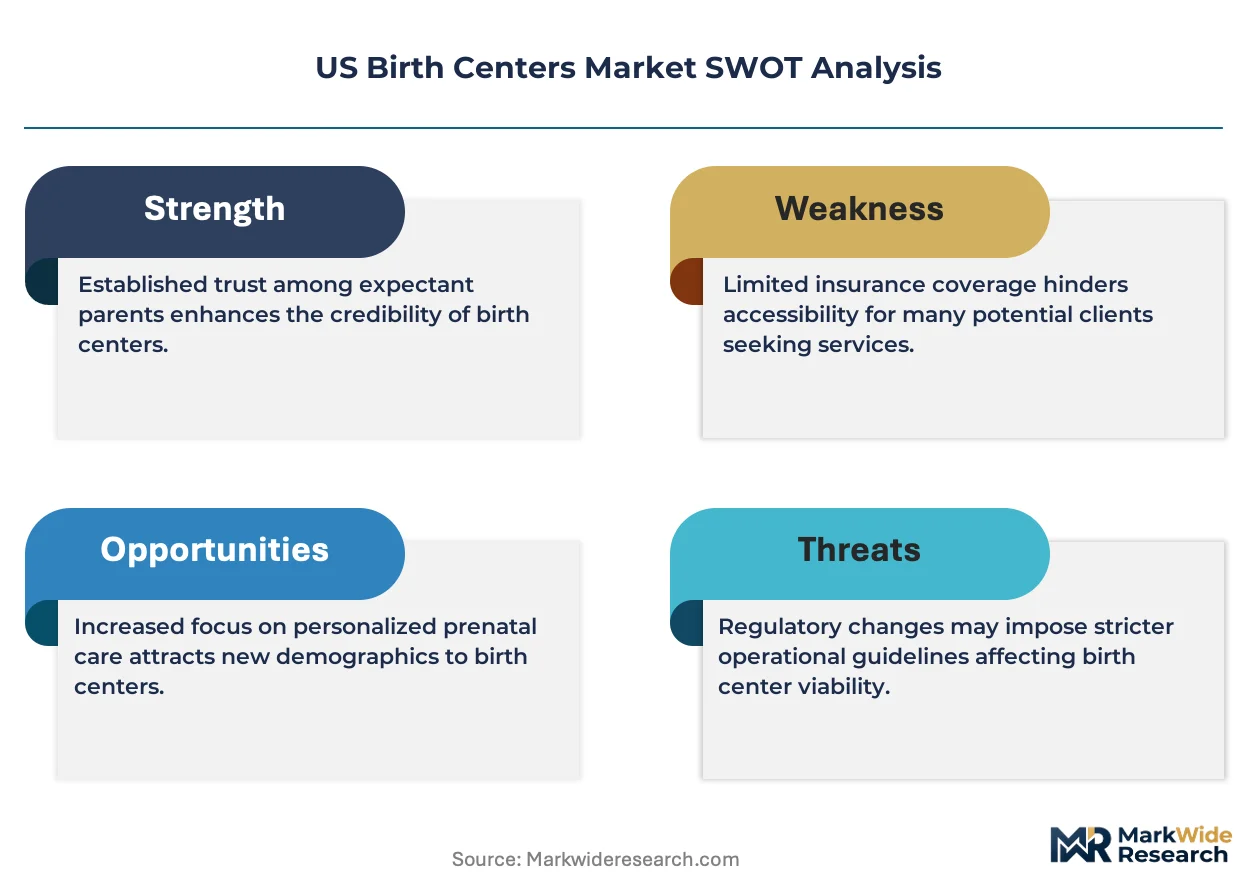
CMS conditions of participation, state department of health licensing standards, and CABC accreditation requirements collectively determine birth center operational scope and reimbursement eligibility across US jurisdictions. FDA oversight of medical devices used in intrapartum monitoring shapes capital equipment procurement decisions. OSHA workplace safety mandates influence staffing ratios and ergonomic design specifications. Stakeholders must monitor evolving state Medicaid birth center benefit expansions and commercial payer bundled payment pilots to align facility development timelines with reimbursement unlocks.
Market Dynamics
State Medicaid expansion under CMS guidance is redrawing reimbursement eligibility for out-of-hospital births, accelerating capital flows toward hospital-affiliated and freestanding birth center development across metropolitan corridors.
Growth Catalysts
- Medicaid Managed Care Expansion:CMS guidance enabling state-level birth center benefit inclusion unlocks payer contracting scale for facilities serving low-income expectant mothers.
- Telemetric Intrapartum Monitoring:FDA-cleared wireless fetal surveillance systems extend low-risk birth eligibility by enabling real-time obstetric consultation without physical hospital presence.
- Certificate-of-Need Relaxation:State-level CON moratoriums in Texas and California permit independent midwifery practice expansion without hospital capital partnership requirements.
Market Restraints
- Certified Nurse-Midwife Supply Concentration:ACME-accredited training program capacity limits constrain workforce scaling in Mountain West and Great Plains sub-regions.
- Malpractice Premium Volatility:Commercial liability coverage for out-of-hospital birth settings carries pricing uncertainty that compresses freestanding center margin profiles.
- Immediate Operating Room Access Mandates:State department of health licensing standards requiring 15-minute OR proximity restrict rural site feasibility and inflate real estate costs.
Strategic Opportunities
- Medicaid Managed Care Bundled Pilots:State innovation waivers testing episode-based payment for maternity care create margin expansion potential for integrated perinatal pathways.
- Hospital-Affiliated Freestanding Hybrids:Health systems in New York and Illinois are piloting off-campus licensed facilities combining payer scale with home-like environments.
- Telehealth Prenatal Integration:Remote patient monitoring platforms converging with midwifery services reduce visit burden while maintaining CABC accreditation visit-count requirements.
Industry Challenges
- ACNM Certification Pipeline Lag:Two-year graduate program throughput fails to match birth center opening velocity, forcing wage inflation for experienced certified nurse-midwives.
- CABC Accreditation Timeline Compression:Twelve-to-eighteen-month facility review cycles delay operational revenue commencement after lease execution and buildout completion.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | US Birth Centers Market |
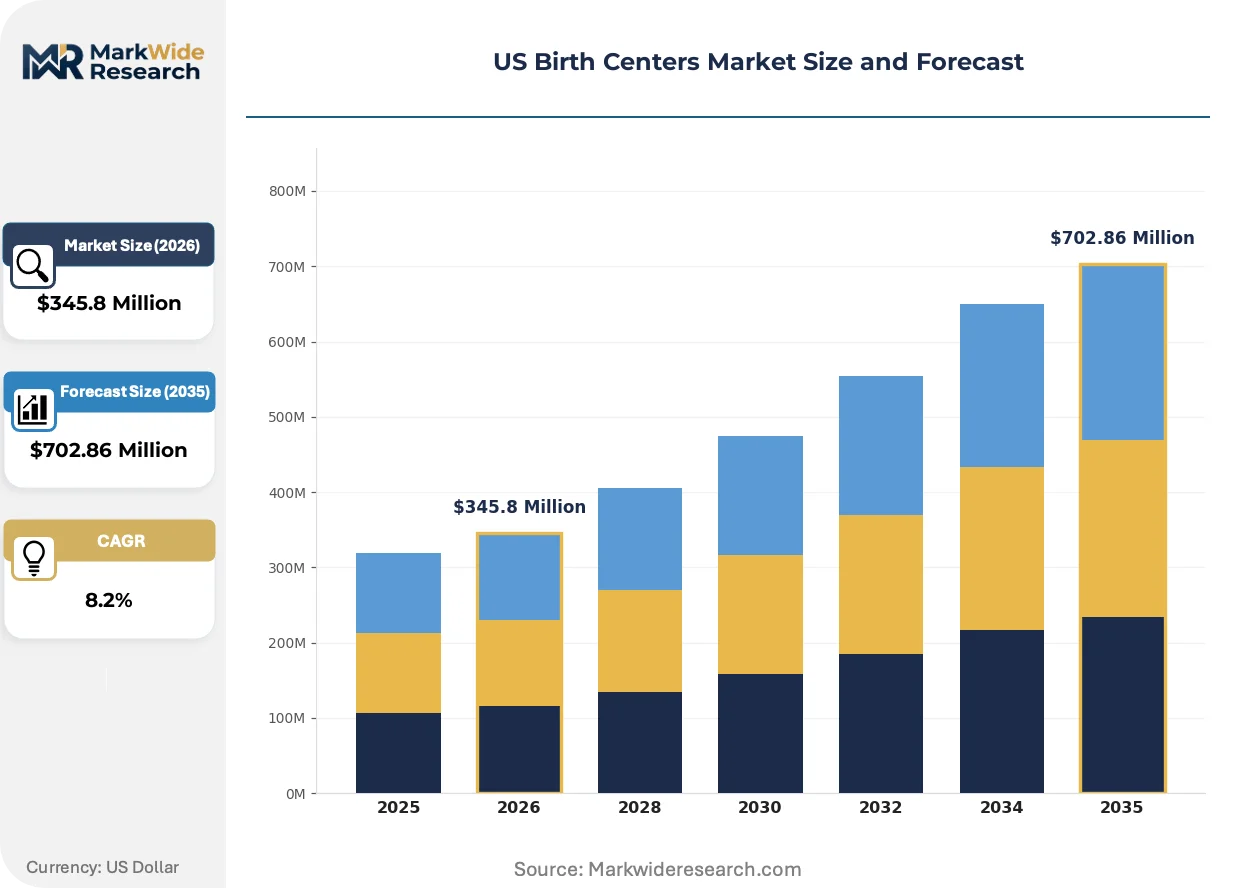
| Market Size in 2026 | $345.8 Million |
| Market Size in 2035 | $702.86 Million |
| CAGR (2026 – 2036) | 8.2% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: Midwifery Services, Prenatal Care, Birthing Services, Postpartum Care Care Setting: Home Birth, Freestanding Centers, Hospital-affiliated Centers, Mobile Clinics Clientele Type: Expectant Mothers, Families, Health Insurance Providers, Community Organizations Facility Size: Small Centers, Medium Centers, Large Centers, Specialty Care Centers |
| Companies Covered | Ronald Reagan UCLA Medical Center (UCLA Health), Barnes-Jewish Hospital, Rose Medical Center, Cedars-Sinai Medical Center (Cedars-Sinai), Cleveland Clinic, Prisma Health Baptist Parkridge Hospital, The Mount Sinai Hospital, TriStar Centennial Women's and Children’s Hospital, The Mother Baby Center, Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
US Birth Centers Market Trends and Innovations
Clinical workflow digitization and payer contracting innovation are restructuring how birth centers capture patient volume and manage perinatal risk across licensed facility categories.
Wireless telemetry systems for intrapartum fetal heart rate monitoring are bifurcating the technology stack across hospital-affiliated and freestanding settings. Hospital-affiliated centers deploy enterprise-grade platforms with direct EMR integration, while independent centers adopt lightweight, cloud-connected devices. This technology divergence is compressing equipment procurement decisions into binary capital allocation paths based on payer mix and obstetric backup depth.
CMS conditions of participation updates for Medicaid birth center reimbursement are tightening documentation requirements for low-risk eligibility screening. Industrial consequence includes mandatory investment in structured prenatal assessment protocols and electronic risk-stratification tools. Freestanding centers in Medicaid expansion states face the steepest compliance curve as they scale beyond initial certificate-of-need exemptions.
Expectant mother preference for integrated perinatal experiences is displacing fragmented hospital-based care navigation. Hospital systems respond by unbundling maternity service lines into distinct licensed birth center entities with separate brand identities. This channel disintermediation is most visible in California and Texas, where health systems operate parallel freestanding facilities under distinct consumer-facing brands while retaining back-office integration.
US Birth Centers Market Segmentation
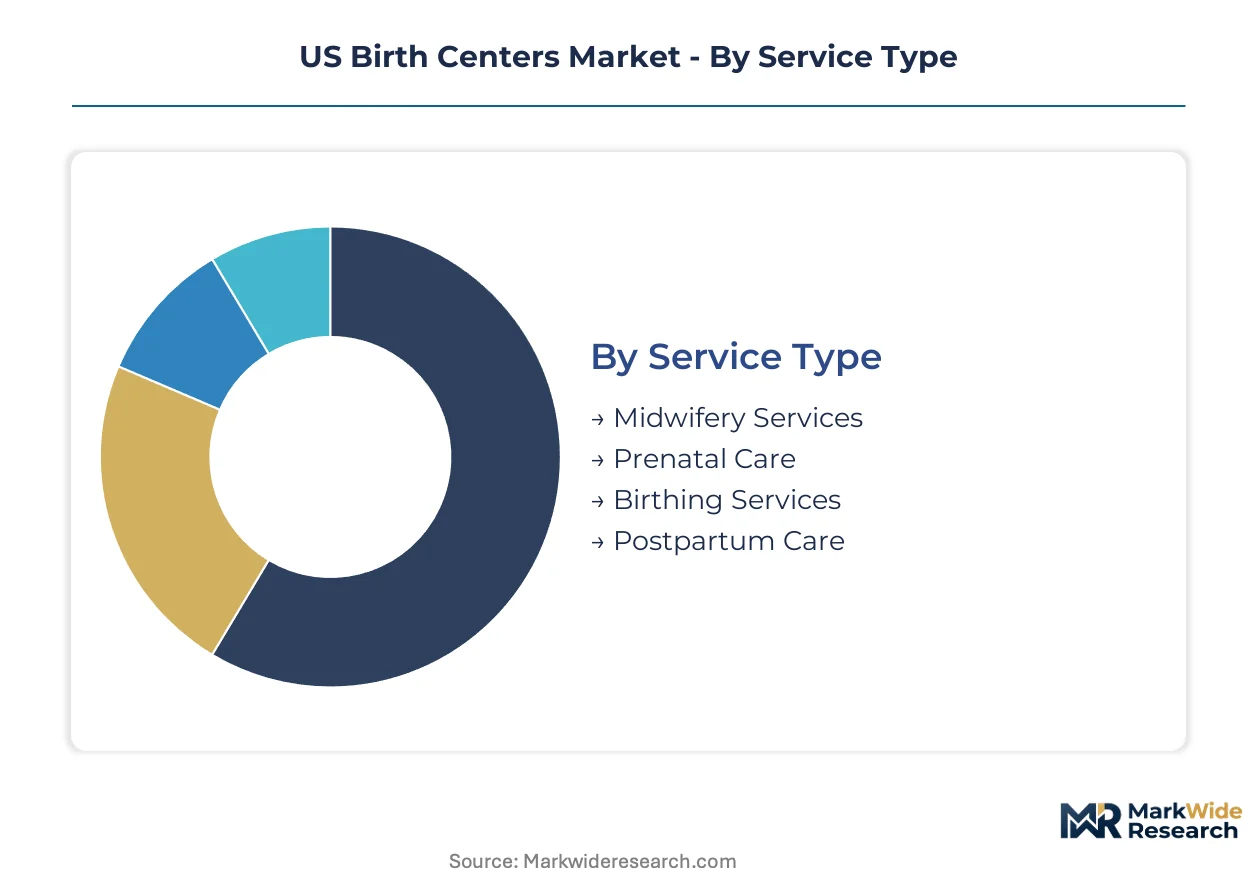
Birth center operators segment service delivery across four structural dimensions to align capital deployment with reimbursement pathways and workforce availability. Each segmentation layer reveals distinct margin profiles and regulatory exposure that shape facility development decisions across Texas, California, and New York metropolitan corridors.
Service Type:
Midwifery-led care models face intensifying substitution pressure from telehealth-integrated obstetric practices that fragment traditional prenatal visit revenue streams.
- Midwifery Services:Certified nurse-midwife provision of intrapartum and postpartum care operates on lower malpractice exposure than physician-led delivery. Demand concentrates in Medicaid expansion states where CMS guidance enables independent practice billing, though ACNM certification pipeline constraints limit workforce scaling.
- Prenatal Care:Structured risk-stratification protocols and visit-count requirements mandated by CABC accreditation standards govern service intensity. Texas and California health systems bundle these visits into episode-based payment pilots, compressing standalone reimbursement for independent centers.
- Birthing Services:Intrapartum care delivery with hydrotherapy and telemetry monitoring.
- Postpartum Care:Neonatal transition support and lactation consultation extending 72 hours post-delivery.
Midwifery Services retains volume leadership; Freestanding center-compatible Birthing Services holds the steepest expansion curve.
Care Setting:
Capital requirements stratify sharply across settings, with hospital-affiliated models commanding payer contracting scale that freestanding competitors cannot replicate without certificate-of-need exemptions.
- Hospital-affiliated Centers:Licensed facilities operating under hospital CMS certification number with immediate OR access protocols. New York and Illinois health systems pilot off-campus models combining Medicaid managed care scale with freestanding aesthetics, though 15-minute OR proximity mandates inflate real estate costs.
- Freestanding Centers:Independent licensed facilities without hospital capital partnership. Texas and California CON relaxations accelerate openings, yet commercial liability premium volatility compresses margins and FDA-cleared wireless fetal surveillance procurement demands binary capital allocation decisions.
- Home Birth:Community-based midwifery attendance without fixed facility overhead.
- Mobile Clinics:Deployable prenatal screening units serving rural access gaps.
Hospital-affiliated Centers dominate revenue concentration; Freestanding Centers are expanding most quickly as state CON moratoriums unlock independent practice.
Clientele Type:
Reimbursement reliability varies by payer category, with Medicaid managed care expansion creating volume concentration among low-income expectant mothers that commercial payers selectively avoid.
- Expectant Mothers:Low-risk pregnancy patients seeking alternatives to conventional hospital delivery. Demand clusters in metropolitan corridors where hospital-affiliated centers combine payer scale with home-like environments, though preference for integrated perinatal experiences displaces fragmented care navigation.
- Health Insurance Providers:Commercial payers and Medicaid managed care organizations negotiating bundled episode rates. CMS conditions of participation updates tighten documentation requirements for low-risk eligibility screening, forcing investment in structured assessment protocols.
- Families:Spousal and extended family participation in birth planning.
- Community Organizations:Nonprofit referral networks serving underserved populations.
Expectant Mothers represent the addressable volume base; Health Insurance Providers determine margin feasibility through contracting leverage.
Facility Size:
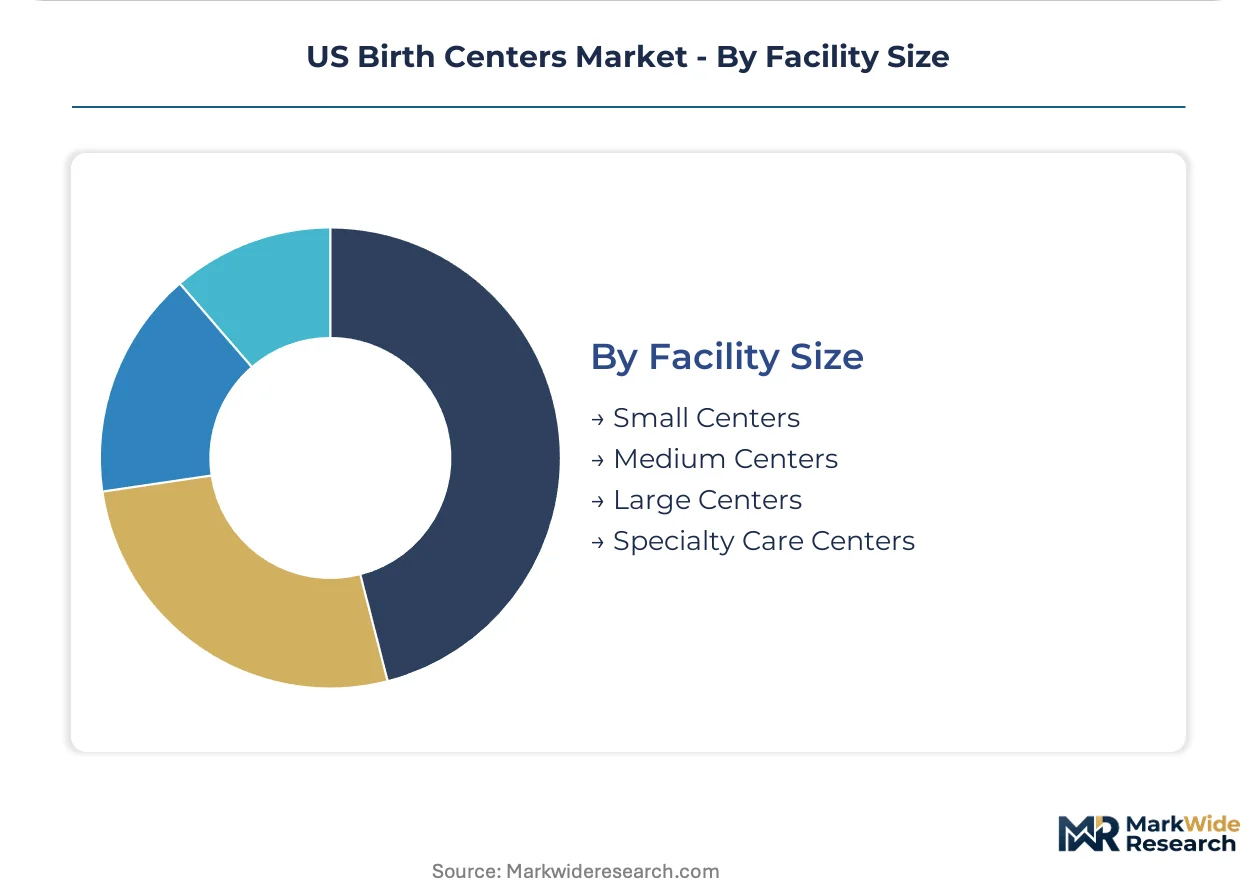
Operational scope and staffing ratios scale non-linearly with facility size, as OSHA workplace safety mandates and state licensing standards impose fixed compliance costs that burden smaller centers disproportionately.
- Large Centers:Multi-suite facilities with 24-hour CNM coverage and telemetry-capable recovery suites. California health systems operate parallel freestanding facilities under distinct consumer-facing brands while retaining back-office integration, capturing bundled reimbursement scale.
- Specialty Care Centers:Facilities integrating perinatal pathways from prenatal through neonatal handoff. Minneapolis-St. Paul geographic concentration demonstrates this model's dependence on hospital system affiliation for obstetric backup depth.
- Small Centers:Single-suite operations with limited birth volume capacity.
- Medium Centers:Two-to-four suite facilities serving moderate catchment areas.
Large Centers anchor revenue concentration; Specialty Care Centers gain share fastest through integrated pathway differentiation.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Texas hospital-affiliated centers command premium payer contracting leverage that freestanding competitors in Mountain West sub-regions cannot replicate without certificate-of-need exemptions. California health systems capture bundled reimbursement scale through parallel freestanding brands. New York metropolitan corridors concentrate Medicaid managed care volume.
Texas
Certificate-of-need moratoriums unlock independent midwifery practice expansion across Dallas-Fort Worth and Houston metropolitan corridors. State Medicaid birth center benefit inclusion under CMS guidance accelerates capital flows toward hospital-affiliated development. Texas Health Resources operates multiple licensed facilities combining payer scale with freestanding aesthetics in suburban catchment zones.
California
Integrated perinatal pathway demand clusters in Los Angeles and San Francisco Bay Area metropolitan corridors. FDA-cleared wireless fetal surveillance procurement shapes binary capital allocation decisions between enterprise-grade and cloud-connected platforms. Cedars-Sinai Medical Center anchors premium hospital-affiliated center capacity through its Los Angeles footprint.
New York
Medicaid managed care expansion concentrates expectant mother volume in New York City and Long Island sub-regions. State department of health licensing standards enforce 15-minute operating room proximity mandates that inflate real estate costs. Health systems pilot off-campus licensed facilities combining payer scale with home-like environments in Westchester and Nassau counties.
Illinois
Hospital-affiliated freestanding hybrid models emerge in Chicago metropolitan and collar county corridors. OSHA workplace safety mandates influence staffing ratios and ergonomic design specifications across multi-suite facilities. Northwestern Medicine and Advocate Aurora systems test distinct consumer-facing brands while retaining back-office integration.
Minnesota
Geographic concentration of specialty care centers demonstrates dependence on hospital system affiliation for obstetric backup depth. ACNM certification pipeline constraints limit certified nurse-midwife workforce scaling in Twin Cities and Rochester sub-regions. The Mother Baby Center competes through Minneapolis-St. Paul metropolitan dominance.
US Birth Centers Market Competitive Landscape
Technology leadership and cost leadership are held by different player archetypes across the US birth center landscape. Hospital-affiliated centers deploy enterprise-grade telemetry platforms with direct EMR integration, while freestanding competitors adopt lightweight cloud-connected devices to compress capital requirements. The market structures around three archetypes: health system-integrated facilities, independent midwifery practices, and specialty perinatal pathway providers. Dominant competitive moves include hospital system brand unbundling into distinct licensed entities and strategic partnerships for telemetric intrapartum monitoring coverage.
Among health system-integrated operators, Cedars-Sinai Medical Center, Cleveland Clinic, and The Mount Sinai Hospital occupy positions representing the premium-tier hospital-affiliated archetype. These entities exemplify payer contracting scale combined with freestanding center aesthetics. TriStar Centennial Women's and Children's Hospital anchors integrated perinatal pathway specialization spanning prenatal through neonatal handoff. The Mother Baby Center sits within the geographic dominance archetype through its Minneapolis-St. Paul concentration.
| Leading Market Players |
|---|
| Ronald Reagan UCLA Medical Center (UCLA Health) |
| Barnes-Jewish Hospital |
| Rose Medical Center |
| Cedars-Sinai Medical Center (Cedars-Sinai) |
| Cleveland Clinic |
| Prisma Health Baptist Parkridge Hospital |
| The Mount Sinai Hospital |
| TriStar Centennial Women's and Children's Hospital |
| The Mother Baby Center |
| Others |
Pricing and Supply Chain Analysis
Wireless fetal surveillance system substitution for wired telemetry infrastructure is redrawing capital allocation geography and compressing equipment procurement economics across hospital-affiliated and freestanding birth center categories. This technology displacement simultaneously enables cloud-connected platform adoption in independent facilities while locking enterprise-grade EMR-integrated systems into health system-affiliated centers with bundled payer contracting scale.
Pricing Analysis
Metropolitan corridor price spreads between Texas hospital-affiliated centers and Mountain West freestanding facilities reflect divergent malpractice premium structures and real estate cost baselines. Three-tier pricing structure across premium hospital-integrated, standard freestanding, and economy home-birth levels stratifies by CMS certification depth and immediate OR access protocol investment. Pricing pressure stems from ACNM certification pipeline constraints forcing wage inflation for experienced certified nurse-midwives. Medicaid managed care organizations exhibit highest price sensitivity; commercial payers with bundled episode pilots demonstrate lowest.
Supply Chain Analysis
United States and Germany anchor FDA-cleared wireless fetal monitoring device manufacturing with ISO 13485-certified production facilities. Equipment procurement draws from semiconductor components for telemetry chipsets, medical-grade polymers for disposable sensors, and cloud infrastructure services for data transmission. Single-source vulnerability concentrates in ACME-accredited training program capacity limiting certified nurse-midwife workforce scaling. Distribution runs through health system group purchasing organizations for hospital-affiliated centers and direct manufacturer relationships for independent freestanding facilities.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Birth center market power is shifting toward Medicaid managed care organizations as state-level payer consolidation accelerates volume concentration among low-income expectant mothers across Texas, California, and New York metropolitan corridors.
For Market Incumbents: Shield margin position through backward integration into certified nurse-midwife training pipeline partnerships addressing ACNM certification lag. Fortify hospital-affiliated center payer contracting scale against freestanding competitor certificate-of-need exemptions by accelerating off-campus licensed facility deployment with distinct consumer-facing brands. Regulatory threat from CMS documentation requirement tightening demands preemptive investment in structured prenatal assessment protocol digitization.
For New Entrants and Emerging Players: Differentiate on telehealth-integrated prenatal care models reducing visit burden while maintaining CABC accreditation visit-count requirements. White-space opportunity concentrates in Illinois and Minnesota collar county corridors where hospital-affiliated freestanding hybrid models remain underpenetrated. Go-to-market angle should emphasize Medicaid managed care bundled pilot participation capturing episode-based payment margin expansion.
For Investors and Strategic Acquirers: Secondary-cycle assets sit with private equity-backed freestanding center rollups in Texas and California CON-relaxation corridors. Long-term viability hinges on state Medicaid birth center benefit inclusion durability and commercial liability premium stabilization. Acquisition target archetype: specialty care centers with integrated perinatal pathway differentiation and hospital system affiliation for obstetric backup depth. Signal to watch: FDA clearance velocity for next-generation wireless intrapartum monitoring platforms enabling rural site feasibility.
| Strategic Initiative | Industry Significance |
|---|---|
| CABC Accreditation Investment | Twelve-to-eighteen-month facility review cycles govern operational revenue commencement timing across state licensing jurisdictions. |
| Telemetric Monitoring Platform Deployment | FDA-cleared wireless fetal surveillance systems extend low-risk birth eligibility through real-time obstetric consultation capability. |
| Medicaid Managed Care Contracting | CMS guidance enabling state-level birth center benefit inclusion unlocks payer contracting scale for low-income expectant mother volume. |
| Hospital-Affiliated Freestanding Hybrid Development | Off-campus licensed facilities combine payer scale with home-like environments in New York and Illinois pilot corridors. |
| Certified Nurse-Midwife Workforce Pipeline Investment | ACME-accredited training program capacity constraints limit workforce scaling in Mountain West and Great Plains sub-regions. |
Research Methodology
Initial hypotheses were tested against primary input from certified nurse-midwives, birth center administrators, Medicaid managed care contracting officers, and hospital system maternity service line executives and refined through secondary validation. Primary stakeholder interviews combined with CMS Medicare data, state department of health licensing records, CABC accreditation databases, and FDA medical device clearance filings. Bottom-up facility-level capacity modeling triangulated against top-down payer expenditure analysis.
Variance-decomposition across the projection horizon isolates volume, pricing, and mix effects by care setting, facility size, and clientele type segmentation dimensions. CAGRs derive from facility opening velocity projections, workforce supply elasticity estimates, and reimbursement pathway expansion scenarios. Industry-specific forecast inputs incorporate certificate-of-need relaxation timelines and ACNM certification program throughput assumptions.
Material uncertainties — state Medicaid birth center benefit exclusion reversals, commercial liability premium volatility spikes, and ACME accreditation pipeline collapses — sit outside the modeled envelope. Forecasts reflect assumptions about regulatory stability and workforce supply continuity. Recalibration cycles align with material shifts in CMS conditions of participation updates and state-level CON policy changes.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Reproductive Health
Surrogacy Market
Reproductive Health
Global Genital Herpes Treatment Market
Reproductive Health
Pregnancy Care Products Market
Reproductive Health
Donor Egg IVF (in-Vitro Fertilization) Market
Reproductive Health
US Sexual and Reproductive Health Clinics Market
Reproductive Health
Global Gynecology Drugs Market
Reproductive Health
Egg Donation Market
Reproductive Health
UK in Vitro Fertilization (IVF) Market
Reproductive Health
IVF Services Market
Reproductive Health
Europe in Vitro Fertilization (IVF) Market
Reproductive Health
Fertility Treatments Market
Reproductive Health
US Long-Acting Contraception Market
Reproductive Health
Germany in Vitro Fertilization (IVF) Market
Reproductive Health
Cervical Dysplasia Treatment Market
Reproductive Health
Donor Egg IVF Services Market
Reproductive Health
Ovum Egg Banking Market