
 US Ambulatory Surgical Centers Market | 2026-2036
US Ambulatory Surgical Centers Market Size, Share, and Industry Trends Forecast 2026-2036
US Ambulatory Surgical Centers Market Analysis
Polymer-based antimicrobial surfaces is hardening infection-control economics in ASC construction and renovation. Tenet Healthcare leverages its multi-state footprint to sustain same-day surgical throughput across high-volume markets. AMSURG anchors physician partnership models that compete with hospital-owned outpatient departments on cost and scheduling flexibility. United Surgical Partners International specializes in joint-venture structures with health systems, dominating selective metropolitan corridors.
Ambulatory surgical centers are freestanding facilities licensed to perform scheduled surgical procedures with admission and discharge on the same calendar day, typically incorporating Class A operating suites with HEPA filtration, positive-pressure environments, and minimum corridor widths of eight feet for gurney transport and emergency egress. Their primary commercial purpose centers on delivering lower-cost alternatives to inpatient hospital surgery for appropriately selected patients across payer categories. Orthopedic surgery and ophthalmology command the largest service-type revenue pools, with ophthalmology's cataract volume sustaining mature margin profiles while orthopedic ASCs absorb migrating joint replacement cases. Single-specialty centers concentrate capital efficiency and staffing predictability, whereas multi-specialty configurations spread fixed costs across procedure mix but demand more complex supply chain orchestration.
FDA oversight of 510(k)-cleared surgical devices and CMS conditions for coverage directly determine which procedures ASCs may bill and at what reimbursement tier, while state-level CON programs govern facility entry in roughly two-thirds of US jurisdictions. OSHA bloodborne pathogen standards and Medicare accreditation requirements from AAAHC or The Joint Commission shape operational compliance burdens and capital renewal cycles. Stakeholders must monitor CMS procedure-code additions to the ASC-payable list and state Medicaid expansion decisions as the principal levers for volume migration from hospital outpatient departments.
Market Dynamics
CMS reimbursement reforms are accelerating the migration of orthopedic joint replacements from hospital outpatient departments into Medicare-certified ASCs, compressing facility economics and forcing capital redeployment toward robotic surgical platforms.
Growth Catalysts
- CMS ASC-Payable List Expansion:Federal procedure-code additions now cover total knee arthroplasty and cervical spine fusion, unlocking high-revenue surgical volumes previously restricted to inpatient settings.
- Texas-Florida-California Corridor:Weak certificate-of-need statutes in these states enable rapid facility licensing and physician-owned center proliferation without competitor blocking.
- Polymer-Based Antimicrobial Surfaces:Infection-control material advances reduce renovation cycle costs and satisfy Joint Commission accreditation standards for HEPA-positive pressure environments.
Market Restraints
- Certificate-of-Need Jurisdictions:Roughly two-thirds of US states maintain CON programs that artificially constrain new entry and protect incumbent hospital outpatient departments from price competition.
- Robotic Platform Capital Intensity:da Vinci and competing surgical systems require seven-figure equipment commitments plus specialized maintenance contracts that strain single-specialty center balance sheets.
- Anesthesiologist Supply Bottleneck:CRNA supervision requirements and regional anesthesia fellowship scarcity limit same-day surgical throughput expansion in rural and secondary metropolitan markets.
Strategic Opportunities
- Medicaid Expansion States:Arkansas, Missouri, and Oklahoma recently expanded eligibility, creating new payer mix for ASCs willing to accept state-federal reimbursement rates below Medicare benchmarks.
- Ophthalmology-Ophthalmology Convergence:Cataract centers adding refractive laser suites capture premium self-pay volumes while leveraging existing sterile processing infrastructure.
- Health System Joint Ventures:United Surgical Partners International's metropolitan corridor model demonstrates how ASCs gain referral network access through equity partnerships with nonprofit hospital systems.
Industry Challenges
- Perioperative Nurse Staffing:ASCs compete with acute-care hospitals for preoperative and PACU registered nurses, with travel nursing rate volatility compressing labor cost predictability.
- Medicare Accreditation Cycles:AAAHC and Joint Commission surveys require 36-month renewal documentation that consumes administrative bandwidth without generating incremental revenue.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | US Ambulatory Surgical Centers Market |
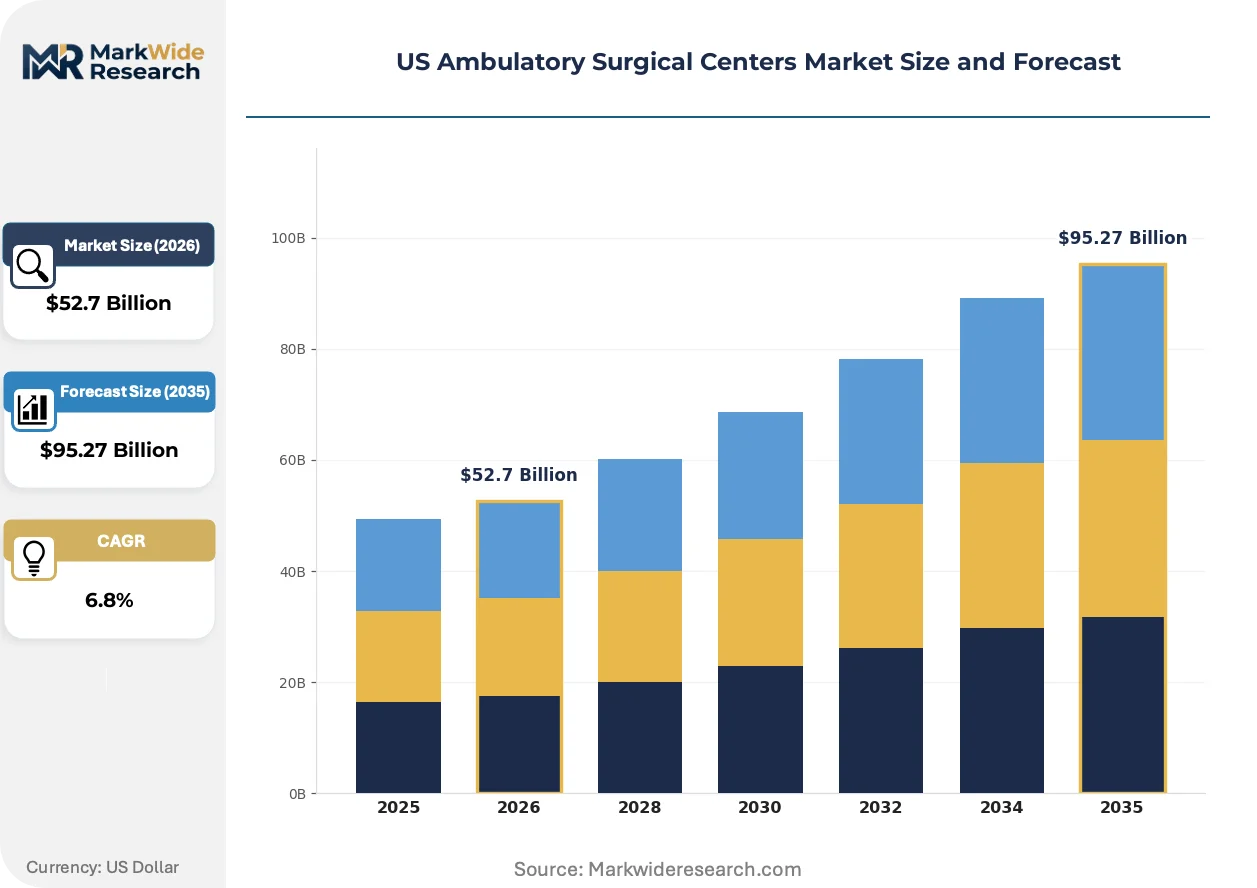
| Market Size in 2026 | $52.7 Billion |
| Market Size in 2035 | $95.27 Billion |
| CAGR (2026 – 2036) | 6.8% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: General Surgery, Orthopedic Surgery, Pain Management, Ophthalmology Technology: Endoscopic Systems, Anesthesia Equipment, Imaging Devices, Surgical Robots End User: Patients, Surgeons, Healthcare Providers, Insurers Capacity: Single-Specialty Centers, Multi-Specialty Centers, High-Capacity Facilities, Low-Capacity Facilities |
| Companies Covered | Virtua Health, Tenet Healthcare, United Surgical Partners International, MUSC Health, Sarasota Memorial Health Care System, AMSURG, ORA Orthopedics, BayCare, HCA Surgery Ventures, Others |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
US Ambulatory Surgical Centers Market Emerging Trajectories
Digital surgical workflows and same-day discharge protocols are compressing length-of-stay metrics while elevating patient throughput as the primary operational KPI for facility investment decisions.
Robotic-assisted surgical platforms are integrating computer-navigated implant positioning into orthopedic ASCs, with high-volume joint replacement centers in Arizona and Nevada adopting these systems to reduce revision surgery rates and justify premium facility fees to commercial payers. The technology is integrating preoperative planning software with intraoperative real-time feedback, enabling less experienced surgeons to match academic medical center outcomes and expanding the addressable physician pool for ASC recruitment.
CMS conditions for coverage now mandate specific staffing ratios and emergency transfer agreements with Level I trauma centers, tightening operational compliance burdens while grandfathered facilities face accelerated capital renewal cycles to meet revised fire safety and corridor width standards. Texas and Florida ASCs report the steepest adaptation costs due to rapid facility aging and hurricane-code structural requirements.
Commercial payer steerage programs are redirecting elective surgical volume toward in-network ASCs through differential copay structures, with self-insured employers in the Midwest and Southeast now requiring preauthorization counseling that presents hospital outpatient departments and freestanding centers as explicit cost alternatives. This channel shift concentrates purchasing power among third-party administrators and reduces direct physician-to-patient facility selection.
US Ambulatory Surgical Centers Market Segmentation
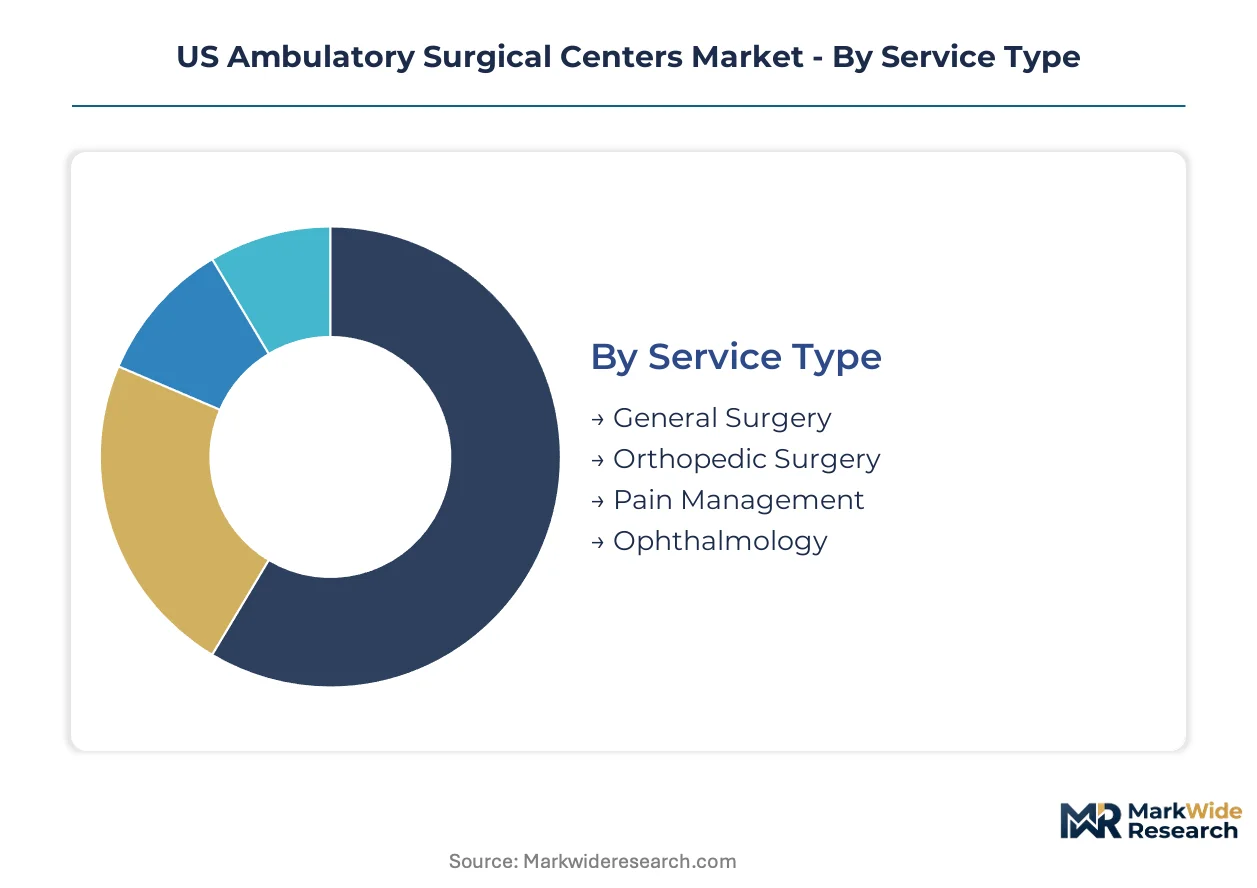
Ambulatory surgical center economics diverge sharply across service lines and capital configurations. Procedure reimbursement tiers and equipment depreciation schedules determine which segments absorb investment and which generate sustainable margin.
Service Type:
Orthopedic and ophthalmology services command divergent capital requirements and payer mix profiles that reshape facility development priorities.
- Orthopedic Surgery:Joint replacement and spine procedures now qualify for ASC reimbursement under CMS payable-list expansion. Texas and Florida centers absorb migrating hospital outpatient department volume as CON restrictions weaken in these states.
- Ophthalmology:Cataract extraction sustains mature margin structures with shorter procedure times and lower anesthesia complexity. Premium refractive add-ons in California and Arizona capture self-pay revenue above standard Medicare rates.
- General Surgery:Hernia repair and cholecystectomy remain volume staples with predictable staffing models.
- Pain Management:Epidural injections and spinal cord stimulation trials require lighter capital equipment than surgical suites.
Volume sits with ophthalmology; growth tilts toward orthopedic surgery.
Technology:
Capital deployment intensity separates centers capable of premium commercial payer contracting from commodity competitors.
- Surgical Robots:da Vinci and competing platforms demand seven-figure equipment commitments plus specialized maintenance contracts. Arizona and Nevada high-volume joint centers adopt these systems to reduce revision rates and justify facility fees.
- Endoscopic Systems:Flexible and rigid scopes constitute baseline infrastructure across all service lines. Antimicrobial polymer surface integration in newer suites satisfies Joint Commission HEPA-positive pressure standards.
- Anesthesia Equipment:Total intravenous anesthesia delivery systems support same-day discharge protocols.
- Imaging Devices:C-arm fluoroscopy and portable MRI reduce transfer dependency for complex cases.
Capital concentrates in surgical robots; deployment pace accelerates fastest in endoscopic system refresh cycles.
End User:
Revenue capture mechanics differ fundamentally between clinical decision-makers and financial risk-bearers.
- Healthcare Providers:Physician-owners and health system joint-venture partners drive facility selection through equity stakes and scheduling control. United Surgical Partners International structures dominate metropolitan corridor development.
- Insurers:Commercial payer steerage programs redirect elective volume through differential copay designs. Self-insured employers in the Midwest now mandate preauthorization counseling presenting ASC and hospital outpatient department alternatives.
- Surgeons:Credentialing privileges and block-time allocation determine individual procedure throughput.
- Patients:Out-of-pocket cost exposure influences facility choice in high-deductible plan structures.
Provider control anchors current volume; insurer channel management is gaining share fastest in employer-sponsored coverage.
Capacity:
Fixed cost spreading versus operational complexity trade-offs define competitive positioning across facility scale.
- Multi-Specialty Centers:Orthopedic, ophthalmology, and general surgery suites share sterile processing infrastructure and PACU recovery bays. Supply chain orchestration demands sophisticated inventory management across divergent procedure kits.
- Single-Specialty Centers:Concentrated capital efficiency and predictable staffing ratios protect margin in reimbursement-compressed environments. AMSURG partnership models exploit this structure for cost and scheduling advantages against hospital-owned competitors.
- High-Capacity Facilities:Six-plus operating rooms justify dedicated anesthesia teams and robotic platform amortization.
- Low-Capacity Facilities:Two-to-three room configurations serve rural and secondary metropolitan markets with limited case volume.
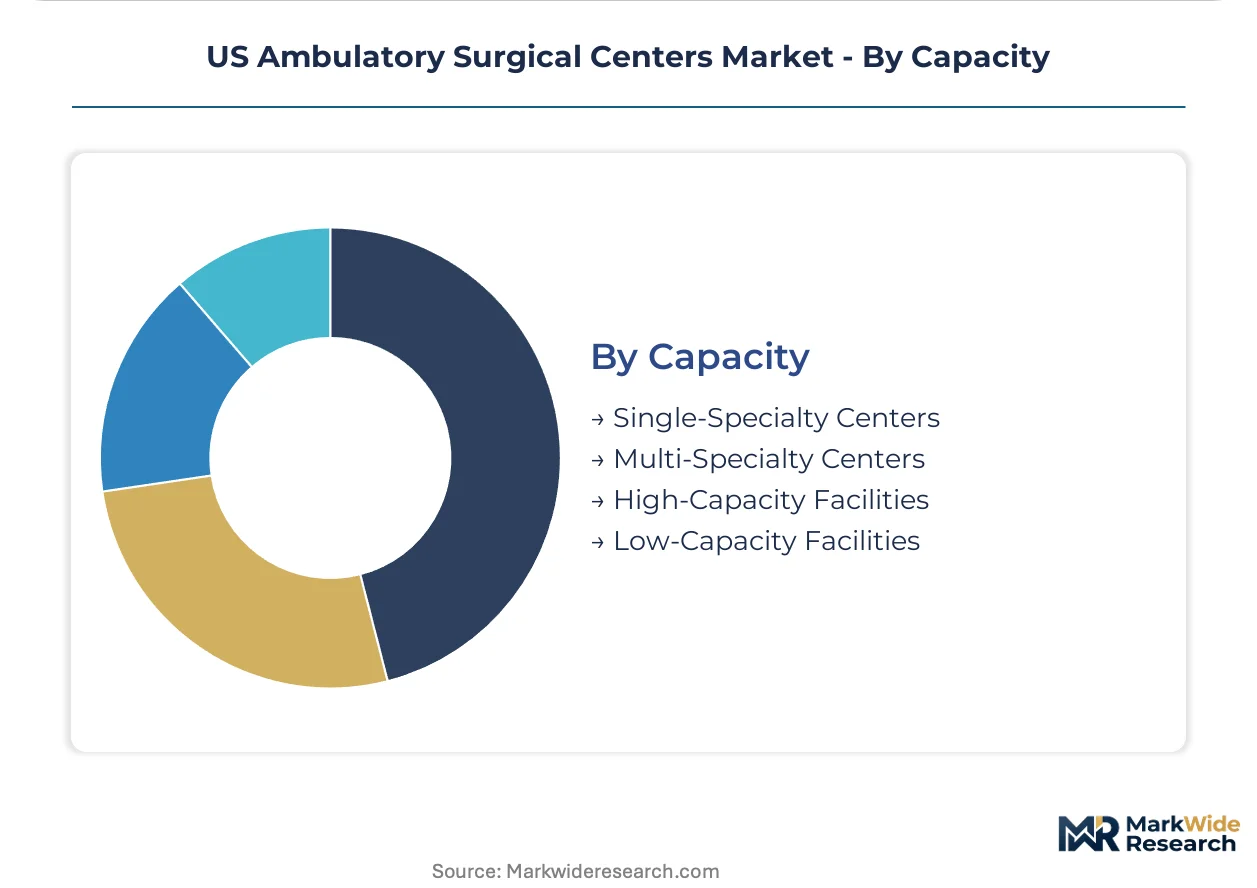
Multi-specialty configurations dominate metropolitan markets; single-specialty centers are expanding most quickly in Texas and Florida corridor development.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Texas Enterprise Zones and Florida Rural Areas of Critical Economic Concern channel capital deployment toward ambulatory surgical center development through property tax abatements and sales tax refunds on construction materials.
Texas
Joint replacement migration from hospital outpatient departments accelerates ASC licensing in Dallas-Fort Worth and Houston corridors. CMS payable-list expansion for total knee arthroplasty unlocks Medicare reimbursement previously restricted to inpatient settings. San Antonio and Austin metropolitan clusters absorb retiring orthopedic surgeon practices into physician-owned center joint ventures.
Florida
Cataract volume concentration in Tampa Bay and Orlando sustains ophthalmology-dominant facility economics. Weak certificate-of-need statutes enable rapid licensing without competitor blocking from incumbent hospital systems. Miami-Dade and Broward counties attract multi-specialty configurations spreading fixed costs across orthopedic and general surgery procedure mix.
California
Premium refractive laser add-ons in Los Angeles and Orange County capture self-pay revenue above standard Medicare cataract reimbursement rates. Seismic retrofit mandates and OSHPD facility standards elevate construction costs for aging ASC renovation cycles. Sacramento and Central Valley markets concentrate pain management and lower-acuity general surgery in lower-capital configurations.
Arizona
Robotic-assisted platform adoption in Phoenix and Scottsdale orthopedic centers reduces revision surgery rates to justify premium facility fees. Retiree demographic density concentrates demand for same-day joint replacement in Sun Corridor metropolitan planning areas. Rural facility development stalls on anesthesiologist supply constraints and CRNA supervision requirement bottlenecks.
Nevada
Las Vegas and Reno corridors leverage proximity to California patient outflow for cash-pay cosmetic and refractive procedures. State Medicaid expansion under the Nevada Care Plan creates new payer mix for ASCs accepting below-Medicare reimbursement benchmarks. Clark County certificate-of-need repeal in 2015 enables rapid facility proliferation without volume forecasting requirements.
US Ambulatory Surgical Centers Market Vendor Landscape
Branded specialists and contract manufacturers split share differently across segments, with health system joint ventures commanding metropolitan corridor access while physician-owned partnerships dominate exurban and secondary market penetration. Market structure tilts toward consolidation among multi-state operators with capital reserves for robotic platform deployment and accreditation renewal cycles. Three archetypes anchor competitive positioning: health system-integrated joint ventures, physician partnership platforms, and private equity-backed roll-up consolidators. Dominant competitive moves center on strategic partnerships with nonprofit hospital systems for referral network access and geographic expansion through de novo development in certificate-of-need-repealed states.
Within the health system-integrated tier, Tenet Healthcare and United Surgical Partners International exemplify multi-state footprint strategies that sustain same-day surgical throughput across high-volume markets. AMSURG anchors physician partnership models that compete with hospital-owned outpatient departments on cost and scheduling flexibility. These three operators represent divergent capital deployment philosophies toward robotic platform acquisition and metropolitan corridor concentration.
| Leading Market Players |
|---|
| Virtua Health |
| Tenet Healthcare |
| United Surgical Partners International |
| MUSC Health |
| Sarasota Memorial Health Care System |
| AMSURG |
| ORA Orthopedics |
| BayCare |
| HCA Surgery Ventures |
| Others |
Supply Flow & Price Mechanics
Commercial payer steerage programs mandating preauthorization counseling for elective procedures force ASCs to compete explicitly on out-of-pocket cost exposure, compelling supply chain managers to consolidate procurement volumes across multi-facility networks and squeezing pricing power for standalone centers without GPO leverage.
Pricing Analysis
Short lead-time premiums for robotic platform spare parts and specialized maintenance contracts dominate ASC procurement economics, with da Vinci system components commanding expedited pricing tiers against standard replenishment schedules. Price differentiation hinges on AAAHC accreditation status and Medicare certification tier, with accredited facilities securing favorable commercial payer rates while uncredentialed competitors face reimbursement compression. Pricing pressure stems from CRNA supervision requirements elevating per-case anesthesia costs. Self-insured employers exhibit highest price sensitivity; hospital joint-venture partners demonstrate lowest.
Supply Chain Analysis
Domestic-content mandates under the Buy American Act reshape surgical device sourcing for federally funded ASC construction projects, privileging FDA-registered domestic manufacturers over offshore alternatives. Supply concentrates in the United States, Germany, and Japan for precision orthopedic implants and endoscopic systems. Raw material dependencies include medical-grade polymers, titanium alloys, and HEPA filtration media. Single-source vulnerability runs through da Vinci platform maintenance contracts. Distribution runs through group purchasing organizations consolidating volume across health system networks.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
CMS conditions for coverage function as a cost-of-compliance moat, with Medicare accreditation requirements from AAAHC or The Joint Commission creating barrier-to-entry protection for incumbent operators with established documentation infrastructure.
For Market Incumbents: Lock in physician partnership equity structures to secure case volume commitment against hospital-owned outpatient department expansion. Consolidate sterile processing infrastructure across metropolitan corridor facilities to spread fixed costs. Prioritize robotic platform deployment in Texas and Florida certificate-of-need-repealed markets to preempt competitor positioning. For New Entrants and Emerging Players: Digital surgical workflow integration offers a technology-first wedge into underserved rural markets lacking same-day discharge protocol sophistication. Target Arizona and Nevada secondary metropolitan corridors with anesthesiologist supply constraints. Pursue Medicaid expansion state entry through below-Medicare rate acceptance. For Investors and Strategic Acquirers: The window for entry favors physician-owned single-specialty platforms with established Medicare certification in CON-repealed jurisdictions. Long-term viability rests on consolidation plays capturing robotic platform amortization efficiency. Monitor CMS procedure-code additions to the ASC-payable list as the principal inflection signal for volume migration acceleration.| Strategic Initiative | Industry Significance |
|---|---|
| Medicare Certification Investment | AAAHC or Joint Commission accreditation unlocks CMS reimbursement tiers and commercial payer network inclusion. |
| Robotic Platform Deployment | da Vinci system acquisition reduces revision surgery rates to justify premium facility fees in orthopedic ASCs. |
| Health System Joint Venture | Equity partnerships with nonprofit hospital systems secure referral network access in metropolitan corridors. |
| Physician Partnership Model | AMSURG-style equity structures compete with hospital-owned outpatient departments on scheduling flexibility. |
| Medicaid Expansion Positioning | Arkansas, Missouri, and Oklahoma eligibility expansion creates new payer mix for rate-flexible operators. |
Methodological Framework
Multi-period observation of CMS procedure-code additions, state-level certificate-of-need statute changes, and robotic platform adoption rates anchored the trend analysis, supplemented by interviews with ASC administrators, orthopedic surgeons, GPO contracts managers, and commercial payer network directors. Secondary validation drew from CMS Medicare cost reports, FDA 510(k) device clearance databases, state health department licensing records, and AAAHC accreditation survey schedules. Bottom-up facility count modeling and top-down reimbursement flow analysis provided cross-verification.
Input-output matrices mapped procedure volume by service line against capital equipment depreciation schedules and staffing ratio requirements across the projection horizon. Segmentation dimensions included service type, technology tier, ownership structure, and metropolitan statistical area regulatory environment. CAGRs were derived from compound growth trajectory fitting against historical Medicare reimbursement trend lines. Forecast inputs incorporated anesthesiologist supply elasticity and commercial payer steerage program penetration assumptions.
Several conditions sit outside the modeled scope, including federal Medicaid expansion reversals, state-level CON statute reinstatements, and disruptive surgical technology obsolescence cycles. Forecasts reflect documented assumptions subject to revision from regulatory, demographic, or competitive dynamics. Within these boundaries, the analytical envelope holds.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Healthcare Facilities
Confinement Center Market
Healthcare Facilities
Micro-Hospitals Market
Healthcare Facilities
Global Ambulatory Surgery Centers (Ascs) Market
Healthcare Facilities
US Office-Based Labs Market
Healthcare Facilities
Ambulatory Surgical Centers Market
Healthcare Facilities
US and Europe Ambulatory Surgery Centers Market
Healthcare Facilities
Hospital Lighting Market
Healthcare Facilities
Sauna and Spa Market
Healthcare Facilities
Global Healthcare Architecture Market
Healthcare Facilities
Longevity Clinic Chain Infrastructure Market
Healthcare Facilities
Bedless Hospitals Market
Healthcare Facilities
Global Healthcare Facilities Management Market
Healthcare Facilities
Mobile Hospitals Market
Healthcare Facilities
US Hospital Facilities Market
Healthcare Facilities
US Assisted Living Facility Market
Healthcare Facilities
Private Office-Based Clinics Market