
 Private Office-Based Clinics Market | 2026-2036
Private Office-Based Clinics Market Size, Share, and Industry Trends Forecast 2026-2036
Private Office-Based Clinics Market Analytics
Modular service bundling is repositioning how employers and insurers purchase clinic capacity, shifting from episodic fee-for-service toward packaged primary-preventive offerings. HCA International leverages its hospital-affiliated ambulatory network to sustain referral density across southeastern US markets. MedLife anchors its growth in Eastern European capitals through specialist-heavy clinic formats that compete directly with public hospital outpatient departments. Bupa Care Homes Plc differentiates by integrating office-based clinics into its residential care footprint, controlling patient flow across the post-acute continuum.
Private office-based clinics constitute physician-owned or corporate-operated outpatient facilities delivering diagnosis, treatment, and preventive care outside hospital campuses, typically requiring medical office space of 1,500–8,000 square feet with procedure rooms, laboratory connectivity, and digital health infrastructure. Their commercial purpose centers on lower-cost site-of-service substitution for ambulatory-sensitive conditions and elective procedures. Primary Care and Preventive Services represent the mature volume base where margin compression from capitated contracts has intensified, while Specialist Consultations and Diagnostic Testing concentrate higher per-visit yields and faster growth as patients seek expedited access outside congested hospital systems. The Pricing Model dimension reveals Bundled Payments and Retainer models capturing disproportionate margin pools by aligning clinic incentives with episode outcomes and direct employer contracts.
US CMS site-neutral payment rules and HIPAA interoperability mandates reshape clinic investment priorities toward certified electronic health record systems and price transparency infrastructure. The EU Medical Device Regulation and GDPR compliance requirements raise capital barriers for clinics deploying connected diagnostic equipment and cross-border telemedicine services. India's Clinical Establishments Act and CDSCO medical device oversight create heterogeneous state-level licensing conditions that fragment multi-clinic expansion. Stakeholders must monitor how regulator-driven site-of-service payment differentials and data governance standards determine viable clinic scale and partnership structures.
Market Dynamics
Employer-sponsored clinic networks are consolidating purchasing power around bundled primary-preventive service packages, compressing traditional fee-for-service margins while rewarding scale-efficient operators with direct contracting relationships.
Growth Catalysts
- Site-neutral payment differentials:US CMS reimbursement frameworks now reduce payment gaps between hospital outpatient departments and freestanding clinics, redirecting procedural volume toward lower-cost office-based settings.
- Capitated employer contracts:Large self-insured employers in the United States are procuring clinic capacity through per-member-per-month arrangements that prioritize preventive care access over episodic treatment.
- Telemedicine infrastructure:HIPAA-certified video consultation platforms are extending clinic reach into suburban and rural catchments without proportional physical expansion costs.
Market Restraints
- EMR capital intensity:Certified electronic health record systems require substantial upfront investment, particularly for independent physician practices lacking hospital system subsidies.
- Laboratory connectivity costs:CLIA-waived and moderate-complexity lab certification creates fixed cost barriers for clinics seeking in-house diagnostic capability.
- Specialist recruitment friction:Concentrated demand for procedure-capable specialists in metropolitan India, Brazil, and the United States drives compensation inflation that erodes clinic-level margins.
Strategic Opportunities
- Metropolitan corridor densification:Secondary cities across India and Brazil present whitespace for capital-light clinic formats targeting physician entrepreneurs with turnkey operational support.
- Post-acute integration:Residential care operators in the United Kingdom and United States are embedding office-based clinics within senior living campuses to capture longitudinal patient relationships.
- GDPR-compliant telemedicine:EU Medical Device Regulation clarity on software-as-a-medical-device classification enables cross-border diagnostic service delivery from centralized clinical hubs.
Industry Challenges
- Interoperability workforce gaps:Clinics struggle to recruit health information technology specialists capable of implementing certified EHR systems and price transparency infrastructure mandated by US regulations.
- State-level licensing fragmentation:India's Clinical Establishments Act creates heterogeneous compliance conditions across Maharashtra, Karnataka, and Tamil Nadu that complicate multi-clinic expansion playbooks.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Private Office-Based Clinics Market |
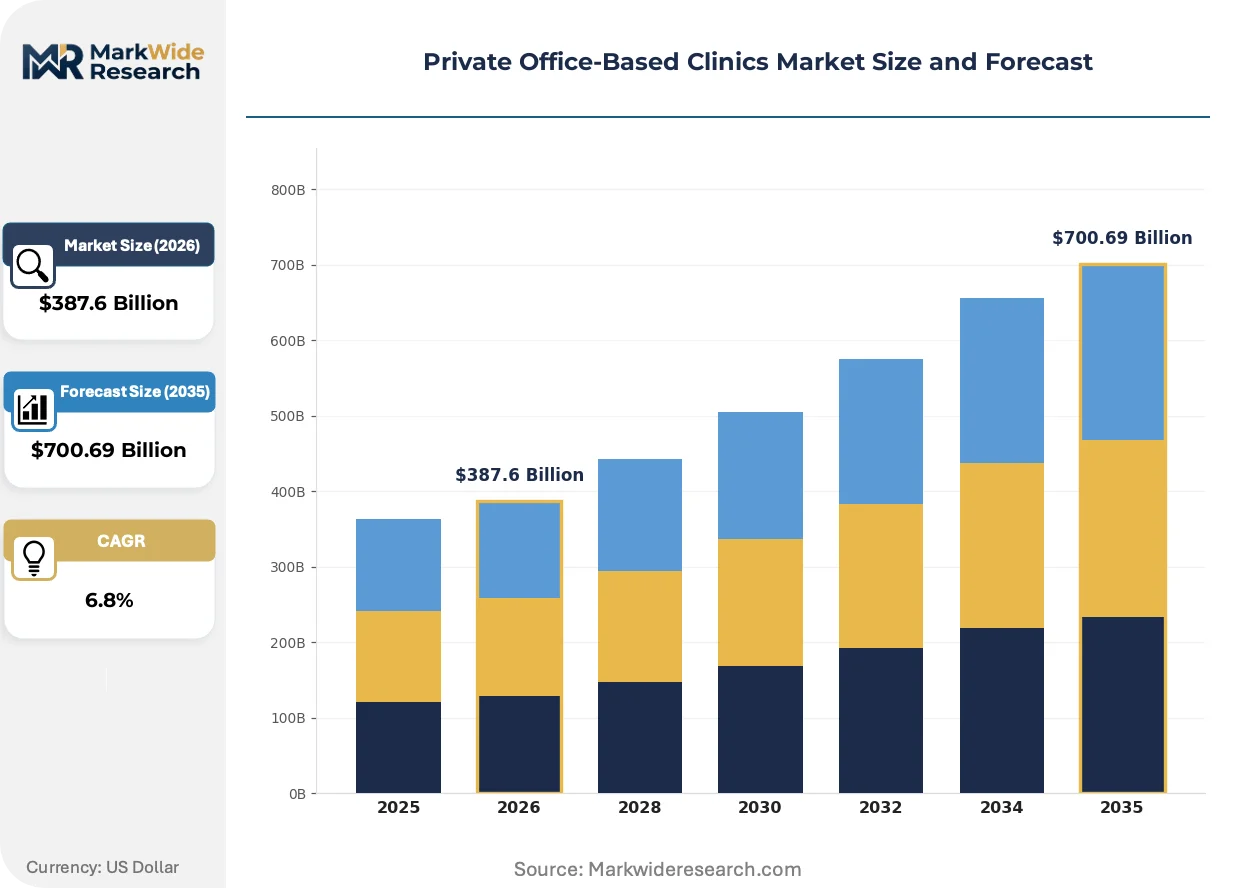
| Market Size in 2026 | $387.6 Billion |
| Market Size in 2035 | $700.69 Billion |
| CAGR (2026 – 2036) | 6.8% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: Primary Care, Specialist Consultations, Preventive Services, Diagnostic Testing End User: Patients, Insurance Companies, Employers, Healthcare Providers Technology: Telemedicine, Electronic Health Records, Practice Management Software, Patient Portals Pricing Model: Capitation, Fee-for-Service, Retainer, Bundled Payments |
| Companies Covered | Capita Health and Wellbeing Ltd, MedLife, Bupa Care Homes Plc, Jackson Healthcare, HCA International, Four Seasons Healthcare Ltd, Colombia Asia, Pathstone Partners, Bupa Insurance Ltd, Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Private Office-Based Clinics Market Evolving Landscape
Digital health infrastructure is redrawing the boundary between centralized hospital systems and distributed outpatient capacity, enabling new organizational models that compete on access velocity rather than procedural breadth.
Remote patient monitoring platforms are decentralizing chronic disease management from hospital-based specialty centers to office-based primary care settings. Medicare Advantage plans in the United States are deploying these tools to reduce emergency department utilization among high-risk populations. The technology is decentralizing revenue capture toward clinics capable of continuous biometric oversight rather than episodic intervention.
EU Medical Device Regulation software classification guidance is clarifying which diagnostic algorithms require notified body certification before clinical deployment. This regulatory precision is accelerating investment in validated clinical decision support tools while freezing marginal applications in regulatory limbo. Connected diagnostic equipment manufacturers serving German and French clinic networks are prioritizing MDR-compliant development roadmaps over faster-to-market alternatives.
Direct-to-employer contracting is compressing traditional payer intermediation from clinic revenue cycles. Self-insured employers in the United States are negotiating capitated arrangements that bypass commercial insurance administrative layers entirely. This channel shift concentrates volume with clinic operators possessing sufficient scale to assume utilization risk across employee populations.
Private Office-Based Clinics Market Segmentation
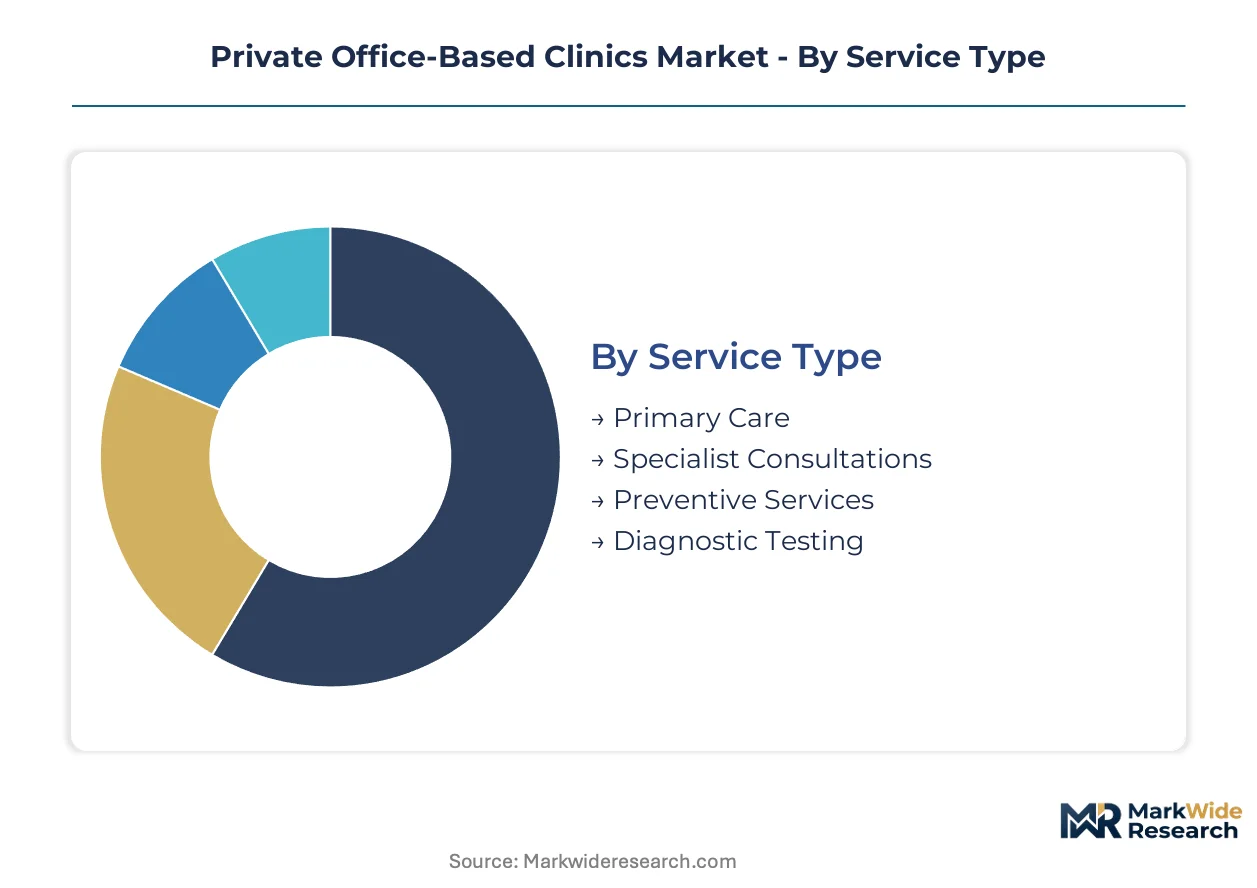
Segmentation in private office-based clinics reveals how capital deployment, reimbursement structures, and technology integration create divergent margin profiles across service configurations. Understanding these partitions helps operators align facility investment with payer contract economics.
Service Type:
Capital requirements vary sharply across service categories, with procedure-capable specialties demanding substantially higher equipment and staffing investment than preventive care formats.
- Primary Care:Standardized examination infrastructure with basic diagnostic equipment supports high visit volumes at compressed per-encounter yields. Demand concentrates in United States metropolitan corridors where capitated Medicare Advantage contracts reward access density over acuity.
- Specialist Consultations:Procedure rooms with specialized instrumentation drive per-visit revenue premiums of 3-4x primary care levels. Cardiology and orthopedics clusters in São Paulo and Bangalore attract physician entrepreneurs seeking independent practice autonomy outside hospital employment.
- Preventive Services:Wellness screening and immunization protocols require minimal capital equipment but depend on population-scale contract relationships.
- Diagnostic Testing:CLIA-waived and moderate-complexity laboratory certification creates fixed cost barriers that favor multi-site operators with centralized quality management.
Primary Care absorbs the bulk of installed capacity; Specialist Consultations is expanding most quickly.
End User:
Customer type determines contract structure complexity, with institutional purchasers demanding outcome guarantees that reshape clinic operational priorities.
- Patients:Direct-pay and high-deductible plan beneficiaries prioritize appointment availability and transparent pricing over continuity relationships.
- Insurance Companies:Commercial payers impose utilization management protocols and narrow network restrictions that constrain referral autonomy.
- Employers:Self-insured corporations in the United States negotiate per-member-per-month arrangements that transfer utilization risk to clinic operators. Boeing and Walmart direct-contracting models concentrate volume with scaled multi-site providers capable of population health management.
- Healthcare Providers:Hospital systems purchase clinic capacity to extend referral catchments and manage post-acute transitions. HCA International affiliates office-based cardiology and gastroenterology practices to feed procedural volume into adjacent ambulatory surgery centers.
Insurance Companies currently dominate contract volume; Employers are gaining share fastest as direct contracting bypasses traditional payer intermediation.
Technology:
Digital infrastructure investment separates scalable multi-clinic platforms from single-site practices locked into fragmented vendor relationships.
- Telemedicine:HIPAA-certified video platforms extend metropolitan clinic brands into suburban and rural catchments without proportional physical footprint expansion. Medicare reimbursement parity for virtual visits during the public health emergency established permanent demand channels.
- Electronic Health Records:Certified systems require substantial upfront capital and ongoing interoperability maintenance that independent practices struggle to absorb. United States CMS Promoting Interoperability program penalties and HIPAA Security Rule compliance create ongoing cost pressure.
- Practice Management Software:Scheduling, billing, and revenue cycle automation reduces administrative overhead for high-volume primary care formats.
- Patient Portals:Secure messaging and appointment scheduling tools satisfy HIPAA individual access requirements while reducing front-desk labor intensity.
Electronic Health Records captures the largest technology expenditure; Telemedicine demonstrates the steepest expansion trajectory.
Pricing Model:
Revenue structure alignment with purchaser risk tolerance creates divergent margin stability across contract types.
- Capitation:Per-member-per-month payments reward preventive care investment and population health management capabilities. United States Medicare Advantage and large self-insured employer contracts concentrate with operators possessing actuarial infrastructure to assume utilization risk.
- Fee-for-Service:Episodic reimbursement dominates legacy commercial insurance relationships but faces margin compression from prior authorization requirements and out-of-network billing restrictions. Independent physician practices in India and Brazil rely on this structure due to limited HMO penetration.
- Retainer:Direct primary care membership fees eliminate payer intermediation entirely, capturing patient loyalty through guaranteed access and transparent pricing.
- Bundled Payments:Episode-based reimbursement for defined procedures aligns clinic incentives with outcome efficiency across the care continuum.
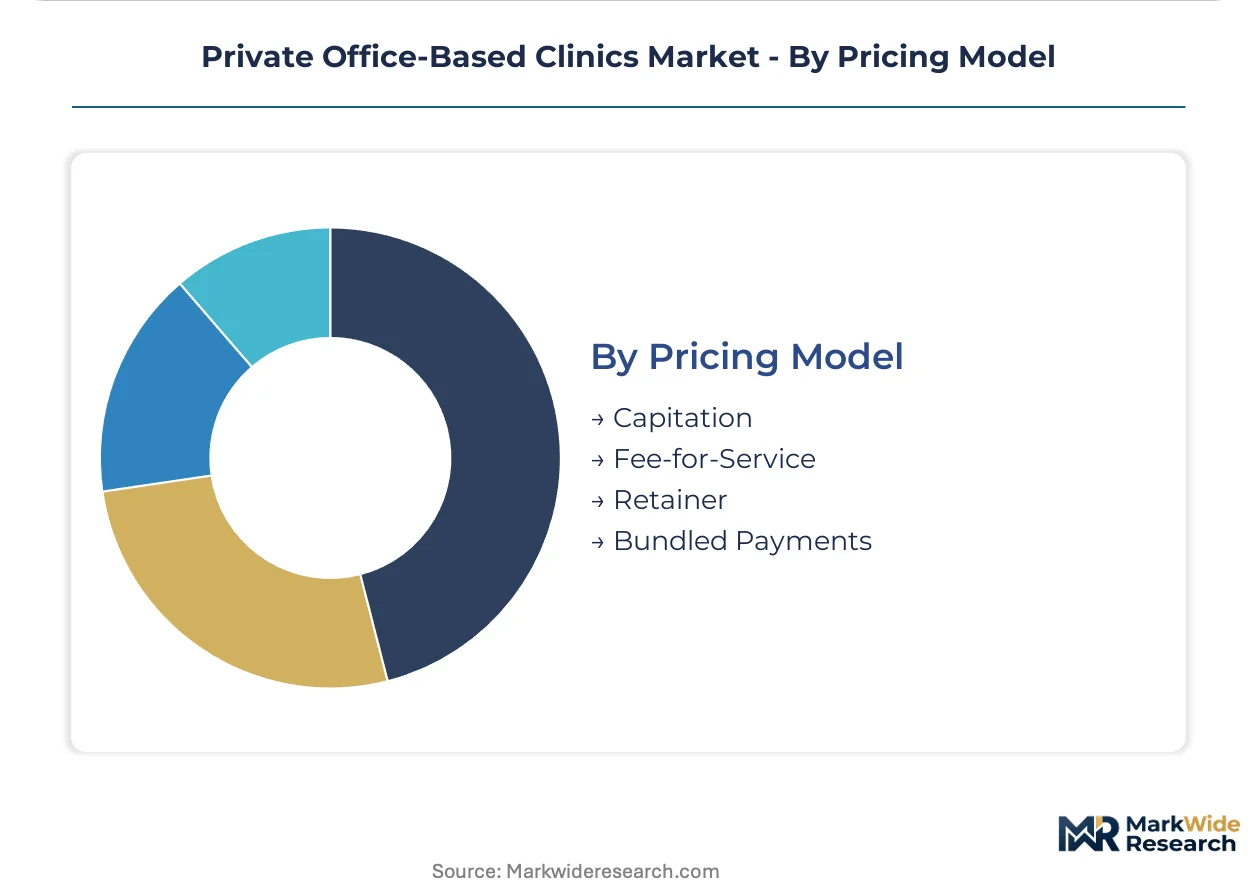
Fee-for-Service retains the largest revenue share; Bundled Payments are climbing the fastest as CMS site-neutral policies expand eligible procedure categories.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Clinic production capacity concentrates in physician entrepreneurship corridors while consumption demand clusters around metropolitan employer populations and aging residential communities. Capital deployment favors lower-cost site-of-service substitution over hospital campus expansion.
United States
Self-insured employers in Boeing and Walmart direct-contracting models concentrate volume with scaled multi-site providers. CMS site-neutral payment rules reduce reimbursement gaps between hospital outpatient departments and freestanding clinics. Southeast metropolitan corridors sustain referral density through hospital-affiliated ambulatory networks.
Germany
EU Medical Device Regulation software classification clarifies diagnostic algorithm certification requirements for clinic networks. GDPR compliance raises capital barriers for cross-border telemedicine service deployment. Connected diagnostic equipment manufacturers serving German clinic networks prioritize MDR-compliant development roadmaps.
India
Physician entrepreneurship drives capital-light clinic formats in Bangalore and São Paulo corridor equivalents. CDSCO medical device oversight and Clinical Establishments Act create heterogeneous state-level licensing across Maharashtra, Karnataka, and Tamil Nadu. Metropolitan corridor densification presents whitespace for turnkey operational support models.
Brazil
Cardiology and orthopedics clusters in São Paulo attract physician entrepreneurs seeking independent practice autonomy. ANVISA pharmaceutical and device regulation shapes diagnostic equipment procurement protocols. Specialist compensation inflation in concentrated metropolitan markets erodes clinic-level margins.
United Kingdom
Residential care operators embed office-based clinics within senior living campuses to capture longitudinal patient relationships. NHS England site-of-service policies influence private clinic reimbursement differentials. London and Southeast England concentrate employer-sponsored clinic network expansion.
Private Office-Based Clinics Market Competitive Landscape
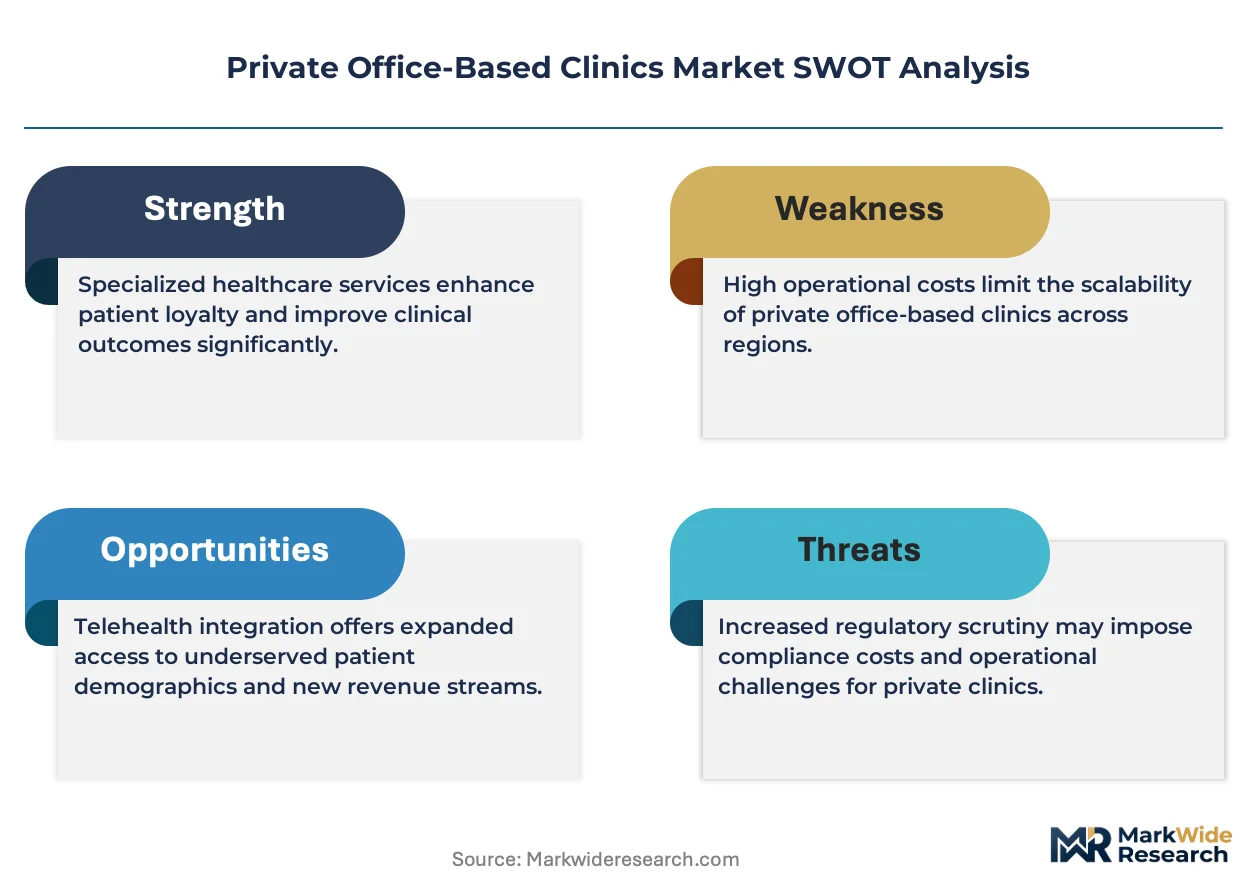
The competitive structure tilts toward hospital-affiliated ambulatory networks and corporate-operated multi-site platforms. Independent physician practices face margin compression from EMR capital intensity and laboratory connectivity costs. Two strategic archetypes dominate: hospital system extenders capturing referral density, and employer-direct contractors assuming population health risk. Consolidation proceeds through ambulatory network acquisitions and capitated contract aggregation.
Within the hospital-affiliated tier, HCA International exemplifies the referral-capture archetype through southeastern US market positioning. MedLife occupies a position representing specialist-heavy clinic formats competing with public hospital outpatient departments in Eastern European capitals. Bupa Care Homes Plc anchors the post-acute integration vector, embedding clinic capacity within residential care footprints to control patient flow across the continuum.
| Leading Market Players |
|---|
| Capita Health and Wellbeing Ltd |
| MedLife |
| Bupa Care Homes Plc |
| Jackson Healthcare |
| HCA International |
| Four Seasons Healthcare Ltd |
| Colombia Asia |
| Pathstone Partners |
| Bupa Insurance Ltd |
| Others |
Value Network & Pricing Analysis
Horizontal integration into multi-site clinic platforms anchors supply position and pricing power for operators serving capitated employer contracts across the United States, Germany, and India. Captive laboratory networks and centralized procurement of CLIA-certified diagnostic equipment compress per-visit cost structures while enabling competitive rate positioning against hospital outpatient departments.
Pricing Analysis
Margin tightening in primary care reflects CMS site-neutral payment compression and employer per-member-per-month contract standardization. Three-tier pricing structure across premium concierge, standard commercial, and economy capitated levels segments buyer price sensitivity, with self-insured employers least sensitive due to total cost of care framing and uninsured direct-pay patients most sensitive to transparent visit fees. Specialist consultation premiums erode in São Paulo and Bangalore as physician entrepreneurship expands supply.
Supply Chain Analysis
Single-source vulnerability sits with Chinese manufacturers of connected diagnostic equipment and Indian API suppliers for in-clinic pharmaceutical dispensing. Equipment procurement draws from Germany, China, and the United States; laboratory reagents and consumables hinge on concentrated chemical processing corridors. Tariff exposure on imaging and monitoring devices elevates total cost of ownership for capital-light clinic formats. Distribution runs through regional medical supply distributors with hospital-affiliated networks securing preferential allocation.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Telemedicine infrastructure is displacing legacy brick-and-mortary expansion models across employer-sponsored and direct-pay clinic segments, compressing capital requirements while extending geographic reach.
For Market Incumbents: Deploy capitated contract aggregation to consolidate employer purchasing relationships against emerging multi-site competitors. HCA International and MedLife demonstrate referral-capture density through southeastern US and Eastern European specialist clustering. EMR interoperability certification investment defends against HIPAA penalty exposure and payer network exclusion. Laboratory connectivity standardization preserves diagnostic margin capture. For New Entrants and Emerging Players: CMS site-neutral payment rules in the United States open a window for freestanding procedural clinics to capture orthopedic and cardiology volume shifting from hospital outpatient departments. Secondary Indian cities present whitespace for turnkey operational support models targeting physician entrepreneurs under heterogeneous Clinical Establishments Act conditions. Direct-to-employer capitated contracting bypasses commercial payer intermediation entirely. For Investors and Strategic Acquirers: Exit pathways concentrate in hospital-affiliated ambulatory network acquisition and employer-direct contracting platform rollup. Long-term viability favors operators with population health management infrastructure and multi-state licensing compliance capabilities. The signal to watch is Medicare Advantage plan telemedicine reimbursement parity permanence.| Strategic Initiative | Industry Significance |
|---|---|
| EMR Interoperability Certification | HIPAA-compliant systems satisfy CMS Promoting Interoperability mandates and payer network entry requirements. |
| Capitated Employer Contracting | Per-member-per-month arrangements with Boeing and Walmart concentrate volume with scaled multi-site providers. |
| Telemedicine Platform Deployment | HIPAA-certified video consultation extends metropolitan clinic brands into suburban and rural catchments. |
| Post-Acute Integration | Bupa Care Homes Plc embeds clinics within residential campuses to capture longitudinal patient relationships. |
| Specialist Cluster Densification | Cardiology and orthopedics concentrations in São Paulo and Bangalore attract physician entrepreneurs. |
Research Methodology
Independent corroboration across clinic operations executives, employer benefits directors, and payer network managers underwrites the qualitative findings. Primary interviews with GPO contracts managers, biomedical engineers, and regulatory affairs leads combined with secondary validation from CMS Medicare data, hospital procurement databases, and FDA 510(k) filings establish segment sizing. Bottom-up clinic capacity modeling and top-down employer spending triangulation reconcile volume estimates.
Rate-of-change decomposition across the analysis window segments growth by service type, pricing model, technology infrastructure, and metropolitan corridor density. CAGRs derive from employer contract expansion trajectories, CMS reimbursement rule implementation timelines, and telemedicine adoption curves modeled against Medicare Advantage penetration. Forecast inputs incorporate CLIA laboratory certification capacity and EU MDR software classification compliance timelines.
The model assumes a particular technology adoption path; alternative pathways for remote patient monitoring integration would alter the outlook. Forecasts reflect assumptions regarding site-neutral payment permanence and state-level licensing harmonization. Deviation in CMS reimbursement differential enforcement or GDPR telemedicine cross-border clarity would shift the outlook materially.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Healthcare Facilities
Trauma Care Centers Market
Healthcare Facilities
US Skilled Nursing Facility Market
Healthcare Facilities
US Hospital Facilities Market
Healthcare Facilities
Global Healthcare Architecture Market
Healthcare Facilities
Asia-Pacific Smart Hospital Market
Healthcare Facilities
Confinement Center Market
Healthcare Facilities
Ambulatory Surgical Centers Market
Healthcare Facilities
Assisted Living Facilities Market
Healthcare Facilities
Micro-Hospitals Market
Healthcare Facilities
Hospital Lighting Market
Healthcare Facilities
US Office-Based Labs Market
Healthcare Facilities
Qatar Senior Living Market
Healthcare Facilities
Sauna and Spa Market
Healthcare Facilities
Global Ambulatory Surgery Centers (Ascs) Market
Healthcare Facilities
Longevity Clinic Chain Infrastructure Market
Healthcare Facilities
US and Europe Ambulatory Surgery Centers Market