
 Private Healthcare Market | 2026-2036
Private Healthcare Market Size, Share, and Industry Trends Forecast 2026-2036
Private Healthcare Market Outlook
Multi-source contracting for specialty pharmaceuticals is pivoting toward consolidated purchasing alliances that reduce administrative burden. UnitedHealth Group leverages its OptumRx platform to anchor pharmacy benefit management across employer networks. CVS Health sustains competitive density through MinuteClinic locations embedded within retail footprints. Kaiser Permanente differentiates via captive hospital-physician-health plan integration that limits external referral leakage.
Private healthcare encompasses fee-for-service and prepaid medical delivery outside government-funded systems, typically involving capital-intensive facilities, licensed clinical labor, and third-party administration of risk pools. Its commercial purpose centers on reducing wait times, expanding consumer choice, and capturing elective procedure revenue streams. Inpatient services retain the largest revenue share due to surgical complexity and facility overhead, while telehealth delivery mode captures the fastest growth trajectory as asynchronous consultations reduce per-encounter costs. Wearable devices within the technology segment concentrate margin pools among continuous glucose monitoring and cardiac rhythm detection applications.
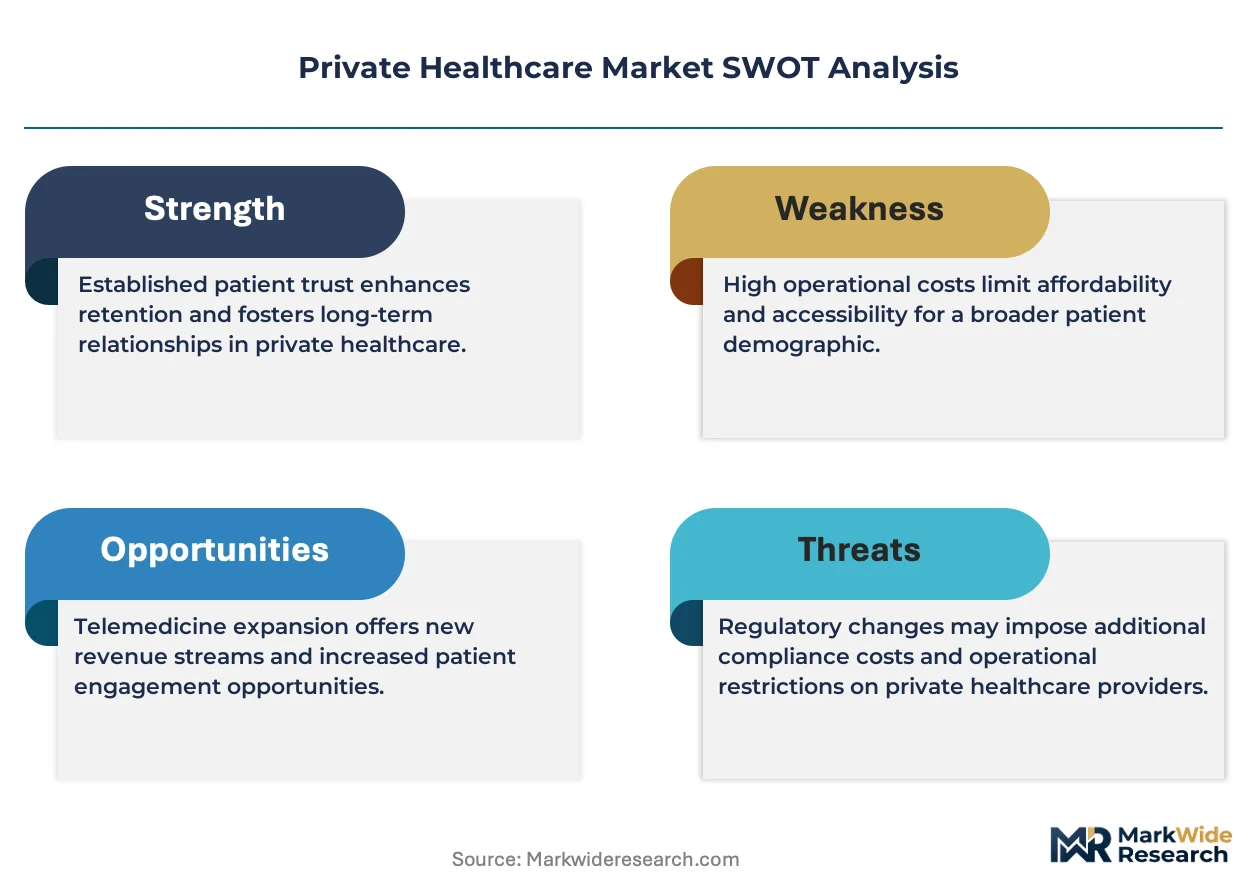
FDA digital health pre-certification and HIPAA interoperability rules shape product development timelines for connected care platforms. CMS value-based reimbursement frameworks redirect capital toward outcomes-accountable delivery models. Stakeholders must monitor how state-level insurance commissioner rate reviews constrain premium growth relative to medical cost inflation.
Market Dynamics
Employer-sponsored insurance networks are consolidating purchasing power through captive pharmacy benefit managers, compressing reimbursement rates for independent physician practices and forcing capital alignment with integrated delivery systems.
Growth Catalysts
- CMS Value-Based Reimbursement:Medicare's accountable care organization models redirect capital toward outcomes-measured delivery, rewarding hospitals that reduce readmission rates through coordinated post-acute care.
- Continuous Glucose Monitoring Adoption:Wearable metabolic sensors expand the addressable patient population beyond insulin-dependent diabetics to pre-diabetic employer wellness programs seeking early intervention.
- United States Employer Network Expansion:Large self-insured corporations are direct-contracting with specialty surgical centers, bypassing traditional payer intermediaries to capture transparent bundled pricing for orthopedic and cardiovascular procedures.
Market Restraints
- Specialty Pharmaceutical Input Concentration:Biologic drug manufacturing relies on single-source plasma fractionators and sterile fill-finish facilities concentrated in Ireland and Puerto Rico, creating supply vulnerability.
- FDA Digital Health Pre-Certification Burden:Software-as-medical-device pathways require continuous post-market performance monitoring that extends product development timelines and elevates compliance costs for connected care platforms.
- Telehealth Substitution Ceiling:Asynchronous virtual consultations cannot replicate physical examination requirements for surgical clearance or complex chronic disease management, limiting addressable procedure categories.
Strategic Opportunities
- India Medical Value Travel:Joint Commission International-accredited hospital networks in Chennai and Hyderabad are capturing elective cardiac and orthopedic flows from Middle East and African patient populations seeking cost arbitrage.
- EU Medical Device Regulation Convergence:MDR harmonized standards create a single conformity pathway for digital therapeutics manufacturers, reducing redundant national notified body submissions across Germany, France, and Netherlands markets.
- Remote Patient Monitoring Integration:Convergence of Bluetooth-enabled pulse oximetry with cloud-based EHR analytics enables hospital-at-home reimbursement models that shift acute bed demand to residential settings.
Industry Challenges
- Interoperability Standardization Delays:HIPAA information-blocking enforcement and TEFCA framework implementation lag behind vendor capability, forcing health systems to maintain redundant interface engines.
- Certified Nurse Anesthetist Pipeline Constraints:CRNA program enrollment caps and clinical preceptor shortages limit operating room throughput expansion for ambulatory surgery centers seeking to capture inpatient migration.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Private Healthcare Market |
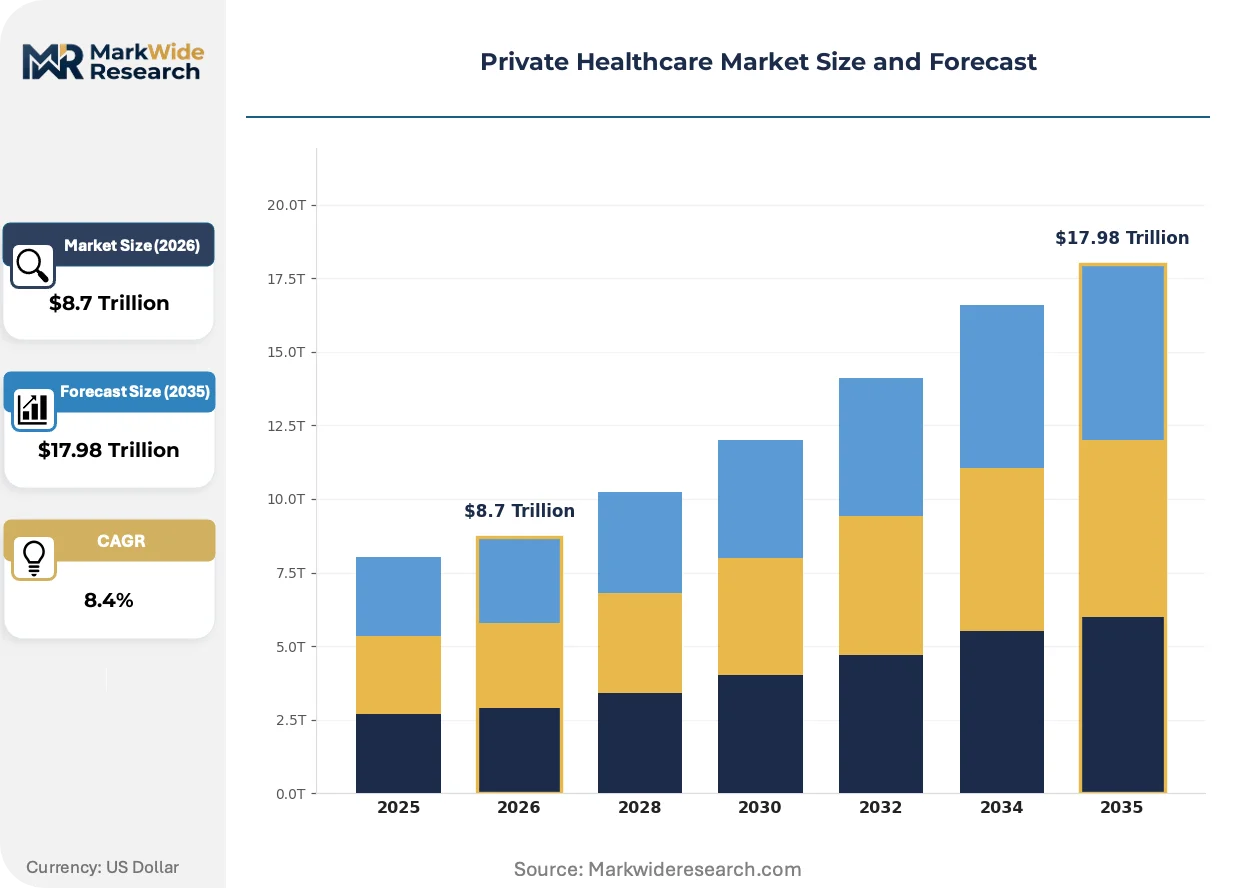
| Market Size in 2026 | $8.7 Trillion |
| Market Size in 2035 | $17.98 Trillion |
| CAGR (2026 – 2036) | 8.4% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: Inpatient, Outpatient, Diagnostic, Rehabilitation Delivery Mode: Telehealth, Personal Visits, Home Care, Emergency Services End User: Individuals, Employers, Insurers, Organizations Technology: Wearable Devices, Health Apps, EHR Systems, Telemedicine Platforms |
| Companies Covered | Centene Corporation, CVS Health, UnitedHealth Group, Molina Healthcare, The Cigna Group, Elevance Health, Humana, Guidewell, Kaiser Permanente, Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Private Healthcare Market Strategic Shifts
Artificial intelligence diagnostic algorithms are securing FDA 510(k) clearances at accelerating velocity, compressing the traditional radiologist-pathologist workflow and reallocating clinical labor toward patient-facing care coordination.
Asynchronous store-and-forward telehealth is overtaking real-time video consultation as the dominant virtual care modality for dermatology and ophthalmology screening, with employer health plans adopting it for routine specialist access. Large self-insured corporations are embedding these platforms into wellness portals to reduce per-encounter costs while maintaining specialist network adequacy ratios. The structural consequence is a compression of synchronous telehealth vendor margins and a pivot toward platform licensing rather than per-visit fees.
EU AI Act risk-classification frameworks for medical decision-support software are forcing manufacturers to re-engineer algorithm transparency and human-in-the-loop documentation. High-risk diagnostic applications now require conformity assessments with notified bodies before CE marking, extending time-to-market for European deployment. German hospital procurement committees are prioritizing vendors with established EU MDR and AI Act dual compliance, disadvantaging earlier-stage developers lacking regulatory affairs infrastructure.
Direct-to-employer contracting is bypassing traditional payer intermediaries for high-volume elective procedures, with self-insured plan sponsors negotiating bundled rates directly with integrated delivery networks. This channel disintermediation is most visible in Texas and Florida markets where large employer concentrations overlap with physician-owned surgical hospital density. The shift forces traditional commercial insurers to defend market share through administrative service-only offerings that cede underwriting risk to plan sponsors while retaining network management fees.
Private Healthcare Market Segmentation
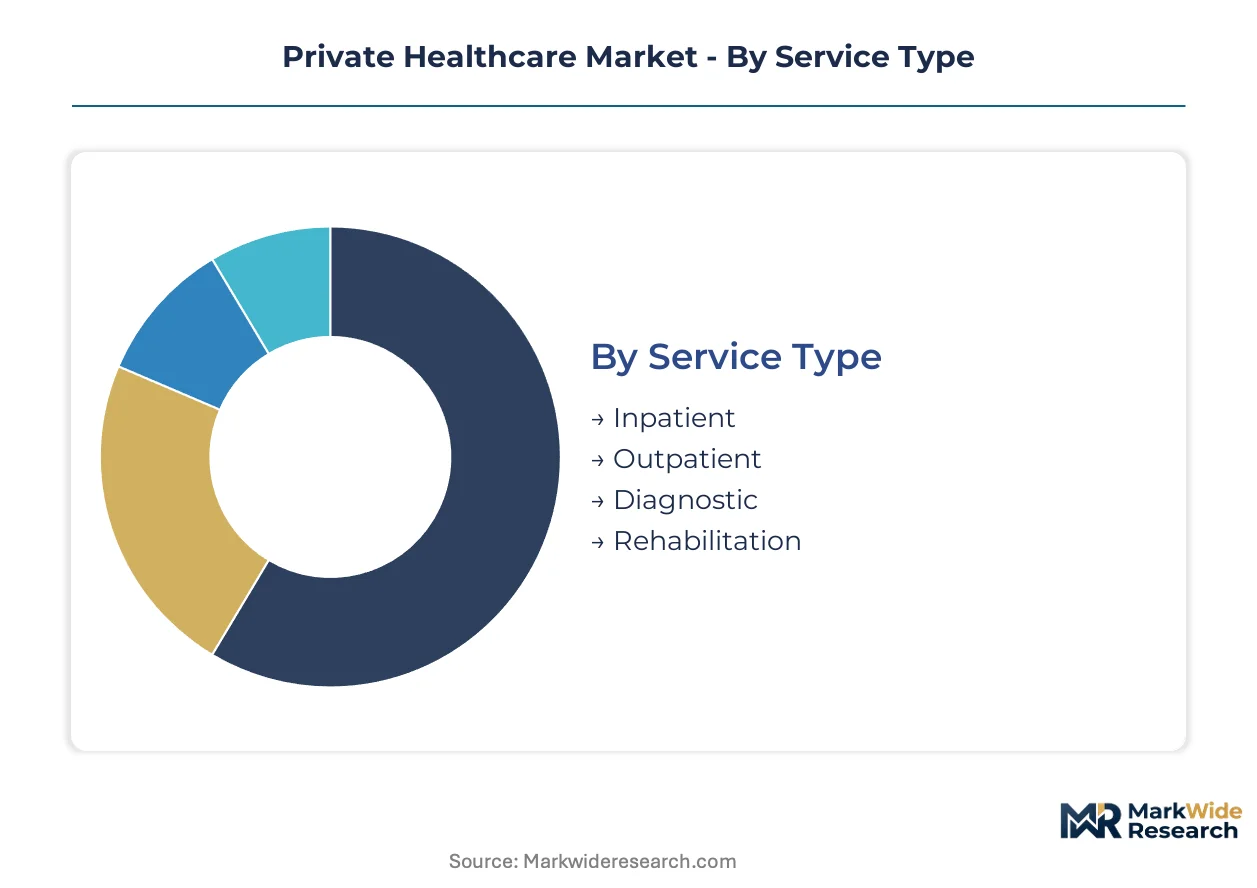
Private healthcare segmentation reveals how regulatory pathways, reimbursement structures, and patient acuity reshape capital allocation across service lines. Distinct approval burdens from FDA, CMS, and state insurance commissioners govern each category's commercial viability and margin profile.
Service Type:
FDA facility certification and CMS Conditions of Participation impose tiered compliance costs across acute and post-acute settings, with inpatient surgical centers facing the most intensive Joint Commission accreditation cycles.
- Inpatient:Capital-intensive facilities delivering surgical procedures and overnight monitoring under licensed physician oversight. Demand concentrates in United States metropolitan corridors where integrated payer-provider systems capture premium cardiac and orthopedic flows through narrow network contracting.
- Outpatient:Ambulatory surgical centers and same-day procedure clinics operating under Medicare ASC coverage determinations. United States employer-sponsored plans increasingly mandate site-of-service steering toward these lower-cost settings for arthroscopy and cataract extraction.
- Diagnostic:Imaging and laboratory services requiring CLIA certification and state radiologic technologist licensure.
- Rehabilitation:Post-acute physical and occupational therapy governed by Medicare IRF prospective payment systems.
Leading the category by volume: Inpatient. Growing fastest: Outpatient.
Delivery Mode:
Cost tier stratification separates high-touch emergency interventions from asynchronous virtual encounters, with reimbursement differentials of 40-60% between equivalent clinical services delivered via telehealth versus in-person settings.
- Telehealth:Synchronous video and asynchronous store-and-forward consultations enabled by HIPAA-compliant platforms. United States employer wellness portals embed dermatology and behavioral health screening to reduce per-encounter spend while maintaining network adequacy ratios.
- Personal Visits:Traditional face-to-face encounters in clinic and hospital settings retaining diagnostic authority for surgical clearance and complex chronic management.
- Home Care:Skilled nursing and personal care services reimbursed under Medicare home health prospective payment.
- Emergency Services:Hospital-based trauma and urgent stabilization governed by EMTALA mandate and state-level certificate-of-need restrictions.
Expanding most quickly: Telehealth. Retaining highest revenue per encounter: Emergency Services.
End User:
Customer type determines pricing power and contract duration, with self-insured employers leveraging direct contracting to bypass traditional payer intermediaries for predictable high-volume procedures.
- Individuals:Direct-pay patients and marketplace exchange enrollees selecting plans based on premium-network tradeoffs. United States silver-tier exchange products concentrate in Florida and Texas markets with limited provider directory breadth.
- Employers:Self-insured corporations and fully insured small groups purchasing population health management. Large manufacturers in automotive and technology sectors negotiate bundled surgical rates directly with integrated delivery networks.
- Insurers:Commercial carriers and managed care organizations administering risk pools and provider networks.
- Organizations:Government contractors, educational institutions, and union trusts purchasing group coverage.
Driving contract value: Employers. Most price-sensitive segment: Individuals.
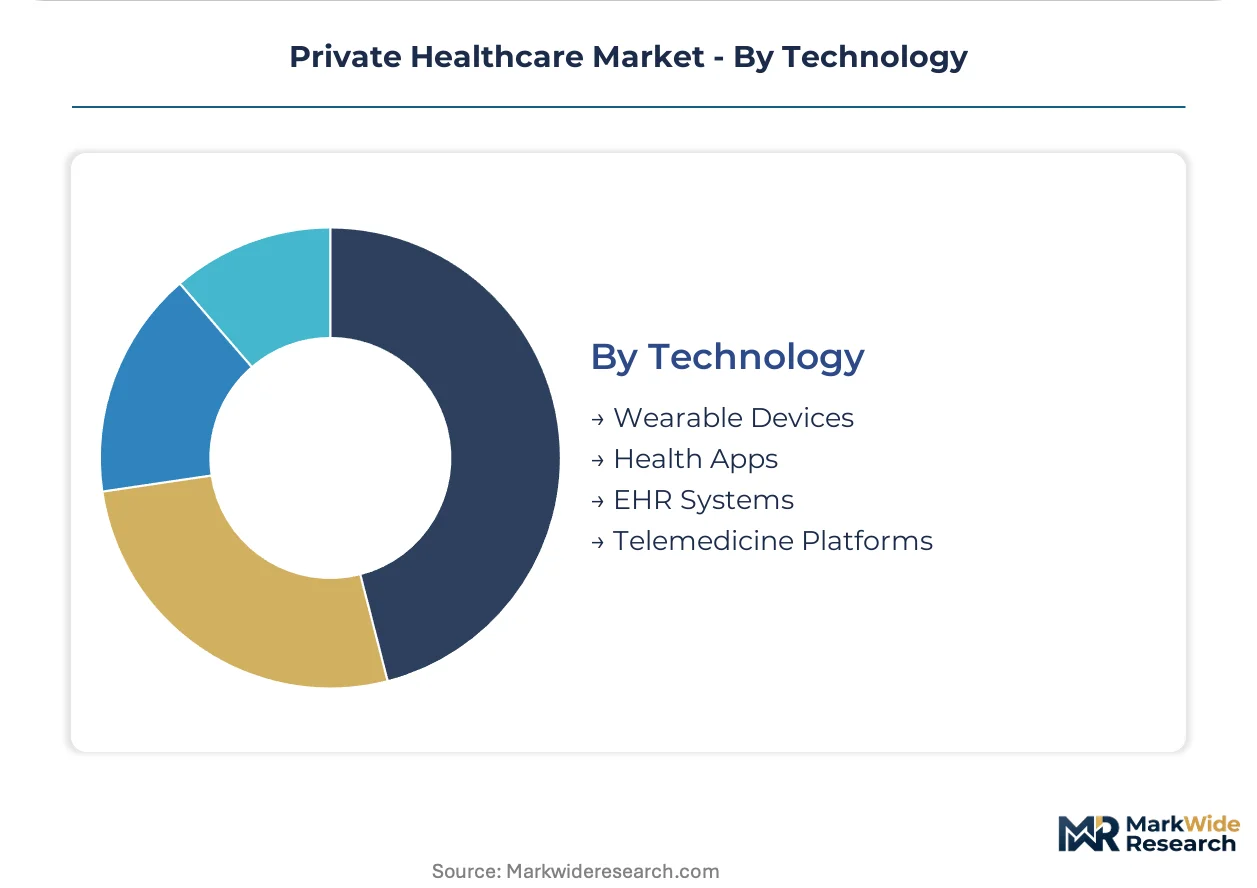
Technology:
Margin concentration follows FDA pre-certification burden and CMS digital health reimbursement decisions, with software-as-medical-device pathways extending time-to-market for algorithm-driven diagnostics.
- Wearable Devices:Continuous glucose monitors, cardiac rhythm detectors, and pulse oximeters requiring FDA 510(k) clearance. United States endocrinology practices prescribe CGM systems to pre-diabetic employer populations for early metabolic intervention.
- Health Apps:Consumer-facing wellness and condition management software facing FTC health claim enforcement and state medical practice act restrictions on unlicensed diagnosis.
- EHR Systems:Certified health information technology governed by ONC interoperability rules and HIPAA information-blocking provisions.
- Telemedicine Platforms:Video consultation infrastructure integrating with payer prior authorization workflows and state medical board cross-border licensure requirements.
Steepest expansion trajectory: Wearable Devices. Highest compliance overhead: Health Apps.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Employer-sponsored insurance networks concentrate purchasing power in the United States, while integrated payer-provider systems in Germany and Japan reshape capital allocation toward outcomes-accountable models. Regulatory divergence across FDA, EMA, and PMDA jurisdictions fragments approval pathways for digital health platforms.
United States
Self-insured corporations and narrow network contracting drive demand concentration in metropolitan corridors. CMS value-based reimbursement frameworks redirect capital toward accountable care organizations that reduce hospital readmissions. The Texas Medical Center in Houston anchors cardiac and orthopedic surgical flows through direct employer contracting arrangements.
Germany
Statutory health insurance funds and private Krankenversicherung schemes sustain dual-track demand for elective procedures. EU MDR and AI Act conformity assessments extend time-to-market for diagnostic algorithms. The Rhine-Ruhr and Bavarian hospital networks concentrate MedTech procurement committees prioritizing vendors with established regulatory affairs infrastructure.
Japan
Aging demographics and long-term care insurance expansion sustain demand for rehabilitation and home care services. PMDA digital health approval pathways and METI reimbursement guidelines shape connected care platform economics. The Kanto region around Tokyo concentrates advanced medical clusters pursuing hospital-at-home reimbursement models.
United Kingdom
Private medical insurance subscriptions and NHS outsourcing contracts sustain dual revenue streams for acute services. MHRA post-Brexit regulatory divergence from EMA creates parallel approval burdens for device manufacturers. London and Southeast England clusters concentrate Harley Street specialty practices and independent hospital groups.
India
Medical value travel from Middle East and African patient populations drives elective cardiac and orthopedic demand. CDSCO medical device rules and state-level clinical establishment acts govern facility licensing. Chennai and Hyderabad anchor Joint Commission International-accredited hospital networks capturing cost-arbitrage flows.
Private Healthcare Market Competitive Environment
Vertical integration dominates the current landscape as payer-owned pharmacy benefit managers and captive provider networks compress margins for independent practices. The structure concentrates around three tiers: integrated payer-provider systems, standalone insurance carriers with outsourced networks, and retail-embedded clinic operators. Strategic archetypes include the fully integrated closed-loop model, the PBM-anchored pharmacy network, and the ambulatory surgery center specialist. M&A activity and direct-to-employer contracting represent the dominant competitive vectors reshaping market share.
Among integrated payer-provider systems, Kaiser Permanente exemplifies the captive hospital-physician-health plan model that limits external referral leakage. UnitedHealth Group anchors the PBM-integrated archetype through its OptumRx platform spanning employer network pharmacy benefit management. CVS Health occupies the retail-embedded position with MinuteClinic locations sustaining competitive density within consumer-facing footprints.
| Leading Market Players |
|---|
| Centene Corporation |
| CVS Health |
| UnitedHealth Group |
| Molina Healthcare |
| The Cigna Group |
| Elevance Health |
| Humana |
| Guidewell |
| Kaiser Permanente |
| Others |
Value Chain & Pricing Dynamics
HIPAA interoperability mandates and FDA digital health pre-certification requirements gate qualified supply access for connected care platforms, while premium-tier pricing accrues to vendors with established regulatory affairs infrastructure that accelerates time-to-market for algorithm-driven diagnostics.
Pricing Analysis
Volume-midpoint concentration in employer-sponsored wellness programs compresses per-encounter margins, while specialty surgical bundles and captive pharmacy benefit management retain superior returns. Three-tier pricing structure across integrated payer-provider systems, standalone insurance carriers, and retail-embedded clinic operators reflects certification burden and network adequacy differentiation. Cost compression in asynchronous telehealth intensifies because employer portals are shifting from per-visit fees toward platform licensing models. Individual marketplace enrollees exhibit highest price sensitivity, whereas self-insured corporations with direct contracting arrangements demonstrate lowest sensitivity due to transparent bundled rate negotiations.
Supply Chain Analysis
Certified nurse anesthetist program enrollment caps in the United States and clinical preceptor shortages in Ireland constrain sterile fill-finish facility throughput expansion. Biologic drug manufacturing draws from single-source plasma fractionators in Ireland, Puerto Rico, and Germany, while continuous glucose monitoring sensors source from semiconductor foundries in Taiwan and South Korea. Single-source vulnerability in sterile fill-finish capacity creates supply interruption exposure for specialty pharmaceutical inputs. Distribution runs through integrated delivery networks, pharmacy benefit managers, and direct-to-employer contracting channels that bypass traditional payer intermediaries.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
FDA software-as-medical-device pathways and EU AI Act risk-classification frameworks impose compliance costs that erect barrier-to-entry moats, advantaging incumbents with established regulatory affairs infrastructure against capital-constrained challengers.
For Market Incumbents:Acquire ambulatory surgery center networks to capture inpatient procedure migration and secure operating room throughput capacity. Consolidate specialty pharmaceutical purchasing alliances to compress administrative burden and defend margin position against independent physician practice alignment. Threat of direct-to-employer contracting bypassing traditional payer intermediaries necessitates captive pharmacy benefit manager expansion and narrow network density reinforcement.
For New Entrants and Emerging Players:Launch via hospital-at-home reimbursement models integrating Bluetooth-enabled pulse oximetry with cloud-based EHR analytics to shift acute bed demand toward residential settings. White-space opportunity concentrates in India medical value travel corridors serving Middle East and African patient populations seeking Joint Commission International-accredited cardiac and orthopedic cost arbitrage. Go-to-market angle should emphasize EU MDR and AI Act dual compliance to access German hospital procurement committees prioritizing established regulatory infrastructure.
For Investors and Strategic Acquirers:FDA 510(k) clearance acceleration for artificial intelligence diagnostic algorithms is the leading indicator that algorithm-driven workflow compression will reallocate clinical labor toward patient-facing care coordination, favoring platforms with radiologist-pathologist substitution capabilities. Long-term viability across the projection horizon rests on outcomes-accountable delivery models with demonstrated readmission rate reduction. Acquisition target archetype: integrated payer-provider systems with captive hospital-physician-health plan structures limiting external referral leakage. Signal to monitor: CMS value-based reimbursement framework expansion redirecting capital toward accountable care organizations with coordinated post-acute care capabilities.
| Strategic Initiative | Industry Significance |
|---|---|
| FDA Digital Health Pre-Certification | Software-as-medical-device pathways require continuous post-market performance monitoring that elevates compliance costs for connected care platforms. |
| Hospital System Partnership | Direct contracting with self-insured corporations bypasses traditional payer intermediaries for transparent bundled surgical pricing. |
| Reimbursement Strategy | CMS value-based frameworks redirect capital toward accountable care organizations reducing hospital readmissions through coordinated post-acute care. |
| Software Companion Development | Asynchronous store-and-forward telehealth overtakes real-time video consultation for dermatology and ophthalmology employer wellness screening. |
| CE Marking Pathway | EU MDR harmonized standards create single conformity pathways reducing redundant national notified body submissions across Germany, France, and Netherlands markets. |
Study Parameters
Trade association data, regulatory filings, and customs records anchored secondary inputs while primary interviews with hospital purchasing committees, GPO contracts managers, biomedical engineers, and clinician administrators validated demand-side assumptions. FDA 510(k) clearance databases, CMS Medicare reimbursement schedules, hospital procurement databases, and employer benefits survey data provided secondary validation. Bottom-up service line modeling and top-down macroeconomic triangulation reconciled volume and value estimates.
Data-stream reconciliation across inpatient, outpatient, diagnostic, and telehealth delivery modes enabled segmentation-level forecasting throughout the projection horizon. Service type, delivery mode, end user category, and technology platform dimensions structured the analytical framework. CAGRs were derived from historical trajectory analysis and regulatory inflection point identification, incorporating FDA digital health pre-certification velocity and CMS value-based reimbursement adoption curves as healthcare-specific forecast inputs.
Regulatory pathway delays, specialty pharmaceutical supply interruptions, and telehealth substitution ceiling constraints are the dominant revision risks to modeled outputs. Forecasts reflect assumptions regarding employer-sponsored insurance network expansion and integrated payer-provider system consolidation trajectories. Material deviation in FDA pre-certification timelines, biologic manufacturing capacity, or synchronous telehealth reimbursement parity warrants pause and re-evaluation.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Healthcare Services
Audiology Services Market
Healthcare Services
Global Corporate Wellness Solutions Market
Healthcare Services
US Hospice Care Market
Healthcare Services
Global Funeral Homes and Funeral Services Market
Healthcare Services
Kids Sports Injury Treatment Market
Healthcare Services
Long Term Care Market
Healthcare Services
Global Sperm Bank Market
Healthcare Services
US Registered Nurses Market
Healthcare Services
Medical Transcription Services Market
Healthcare Services
Patient Throughput and Capacity Management Market
Healthcare Services
Global Offsite Medical Case Management Market
Healthcare Services
Chronic Disease Management Service Market
Healthcare Services
Global Pharmaceutical Contract Sales Outsourcing (CSO) Market
Healthcare Services
Global Infusion Pharmacy Management Market
Healthcare Services
Asia-Pacific Healthcare Cold Chain Logistics Market
Healthcare Services
Hospice and Palliative Care Centers Market