
 Primary Care Physicians Market | 2026-2036
Primary Care Physicians Market Size, Share, and Industry Trends Forecast 2026-2036
Primary Care Physicians Market Analysis
Multi-source physician recruitment is hardening as health systems compete for scarce primary care talent. Mayo Clinic Physicians leverages its academic reputation to sustain physician retention across the Upper Midwest. Southern California Permanente Medical Group anchors capitated contracts through integrated outpatient and telehealth infrastructure. Optum controls a growing share of employed physicians via its acquisition-driven medical group strategy.
Primary care physicians deliver continuous, first-contact medical services encompassing diagnosis, treatment coordination, and preventive health maintenance for undifferentiated patient presentations. These clinicians operate within structured reimbursement frameworks that tie compensation to quality metrics, patient satisfaction scores, and utilization efficiency targets. Chronic disease management commands the deepest margin pools as payers shift risk to provider organizations managing diabetes, hypertension, and heart failure populations. Telehealth services represent the fastest-expanding care setting, though outpatient clinics retain the highest visit volume and revenue density per encounter.
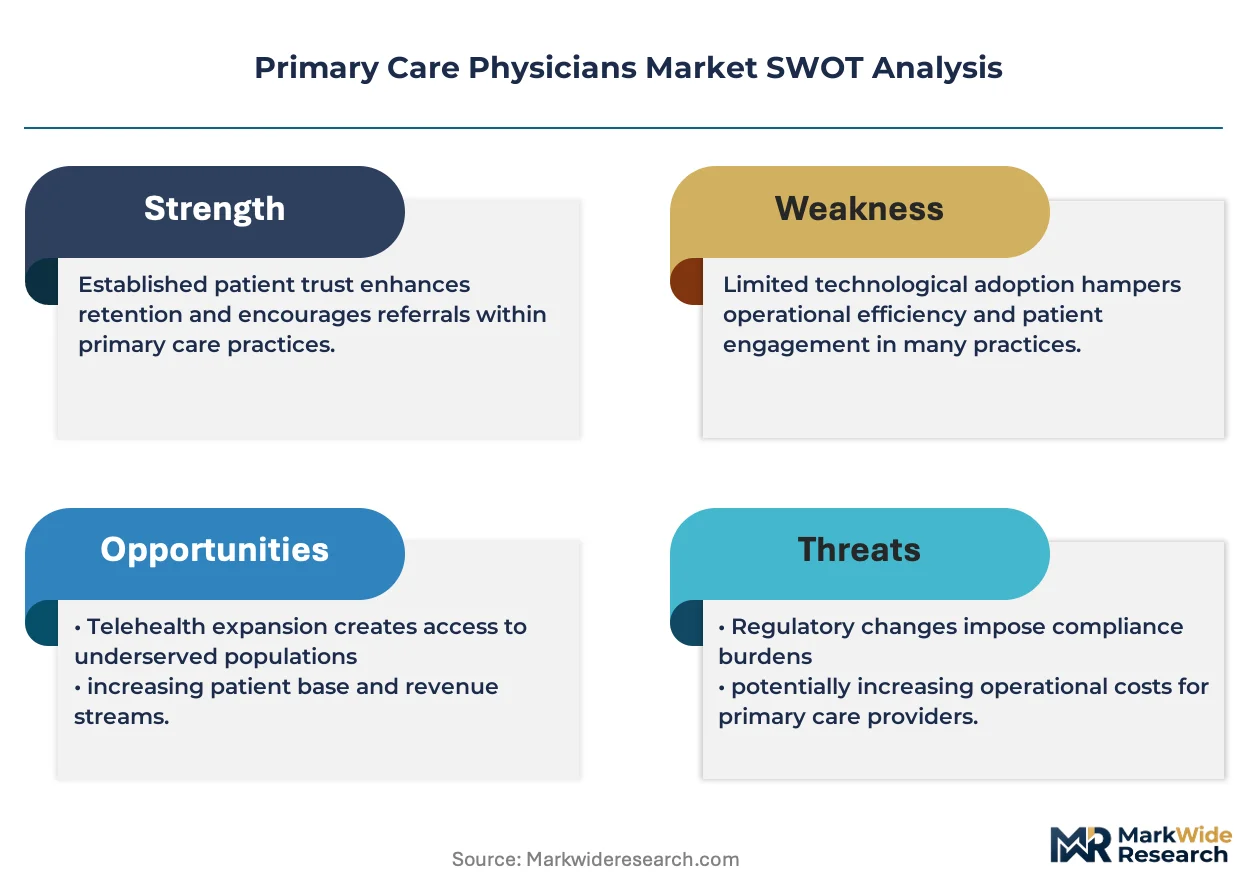
FDA oversight of digital health tools and CMS quality reporting requirements shape how physician practices adopt remote monitoring and electronic documentation systems. HIPAA privacy rules and state-level scope-of-practice regulations constrain telehealth expansion across state lines, creating compliance complexity for multi-state medical groups. Stakeholders must monitor how Medicare Advantage penetration and value-based contract structures alter physician employment preferences between independent practice and health system affiliation.
Market Dynamics
Medicare Advantage penetration is restructuring physician compensation models, pulling primary care physicians into risk-bearing contracts that reward population health outcomes over fee-for-service volume.
Growth Catalysts
- CMS Quality Payment Program:Value-based reimbursement incentives accelerate physician practice consolidation into integrated delivery networks capable of managing attributed patient populations.
- Geriatric enrollment expansion:Medicare Advantage plans enroll aging cohorts requiring chronic disease management, concentrating demand for longitudinal primary care relationships.
- Remote patient monitoring:FDA-cleared digital health devices enable continuous biometric tracking, extending physician reach beyond traditional clinic encounters.
Market Restraints
- HIPAA interstate compliance friction:State-level scope-of-practice variations block telehealth licensing portability, fragmenting multi-state medical group operations.
- Physician supply concentration:Rural and underserved urban areas face persistent recruitment gaps as medical graduates cluster in metropolitan academic centers.
- Administrative burden escalation:Electronic health record documentation requirements consume clinical time, reducing patient-facing capacity without proportional reimbursement adjustment.
Strategic Opportunities
- Direct-to-employer contracting:Self-insured employers bypass traditional payer intermediaries, purchasing primary care access for workforce populations through onsite or near-site clinics.
- Behavioral health integration:Collaborative care models embed psychiatric services within primary care workflows, addressing unmet mental health demand under single reimbursement structures.
- IRA preventive service mandates:Expanded Medicare coverage for vaccines and screenings creates volume anchors for preventive care delivery infrastructure.
Industry Challenges
- Interoperability standards fragmentation:Competing health information exchange protocols force practices to maintain multiple data interfaces, elevating IT integration costs.
- Prior authorization processing delays:Payer utilization management requirements obstruct timely specialist referrals and diagnostic testing, degrading patient experience metrics.
- Workforce pipeline constraints:Graduate medical education funding caps limit residency slot expansion, choking entry-level physician supply growth.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Primary Care Physicians Market |
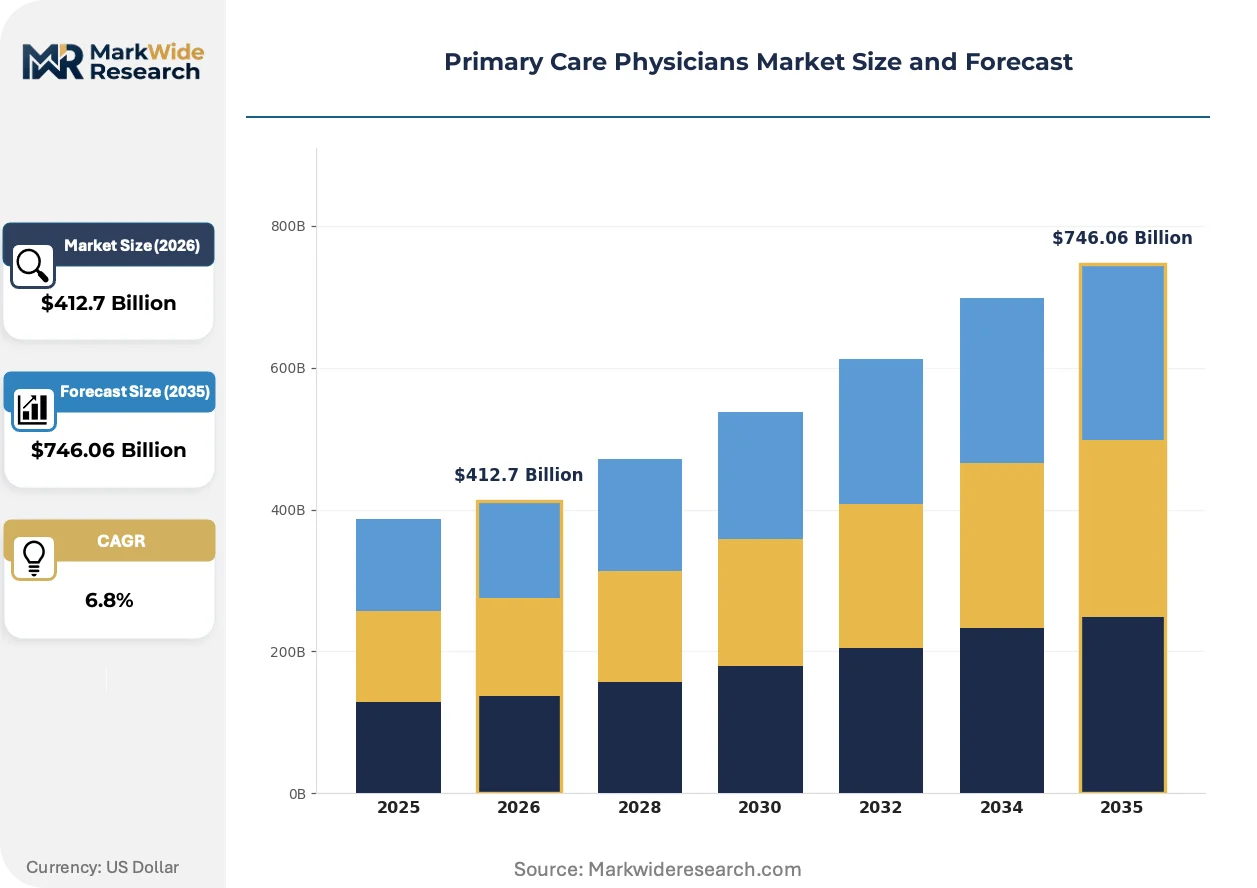
| Market Size in 2026 | $412.7 Billion |
| Market Size in 2035 | $746.06 Billion |
| CAGR (2026 – 2036) | 6.8% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: Routine Check-ups, Preventive Care, Chronic Disease Management, Pediatric Care Patient Type: Adult Patients, Geriatric Patients, Pediatric Patients, Female Patients Care Setting: Outpatient Clinics, Telehealth Services, Community Health Centers, Emergency Rooms Insurance Type: Government Programs, Private Insurance, Self-Pay, Employer-Sponsored Plans |
| Companies Covered | Mayo Clinic Physicians, RWJBarnabas Health Medical Group, Southern California Permanente Medical Group, Northwell Health Physician Partners, Ascension Medical Group, The Permanente Medical Group, University of Pittsburgh Physicians, Hill Physicians Medical Group, Optum, Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Primary Care Physicians Market Emerging Trajectories
Artificial intelligence documentation tools and asynchronous care models are compressing traditional visit structures, enabling physicians to scale panel sizes without proportional staff expansion.
Ambient clinical intelligence is overtaking manual EHR data entry. These voice-activated systems parse patient-physician conversations to auto-populate structured documentation fields. Large medical groups deploy this technology to reduce after-hours administrative work. The compression of documentation burden is overtaking the traditional medical scribe model, reallocating labor costs toward clinical rather than clerical functions.
CMS telehealth parity extensions reshape site-of-service regulations. These policy continuations preserve audio-only visit reimbursement levels established during emergency declarations. Rural health clinics adapt by converting telephone encounters into billable telehealth services. Federally qualified health centers in frontier states deploy this regulatory flexibility to maintain access for broadband-limited populations.
Subscription-based primary care memberships disrupt traditional insurance-dependent access models. Patients pay monthly fees for guaranteed same-day appointments and extended visit durations. Direct primary care practices in Texas and Florida expand rapidly, attracting patients frustrated with deductible exposure and narrow network restrictions. Employer-sponsored health plans in the Southeast increasingly supplement these arrangements as recruitment and retention tools.
Primary Care Physicians Market Segmentation
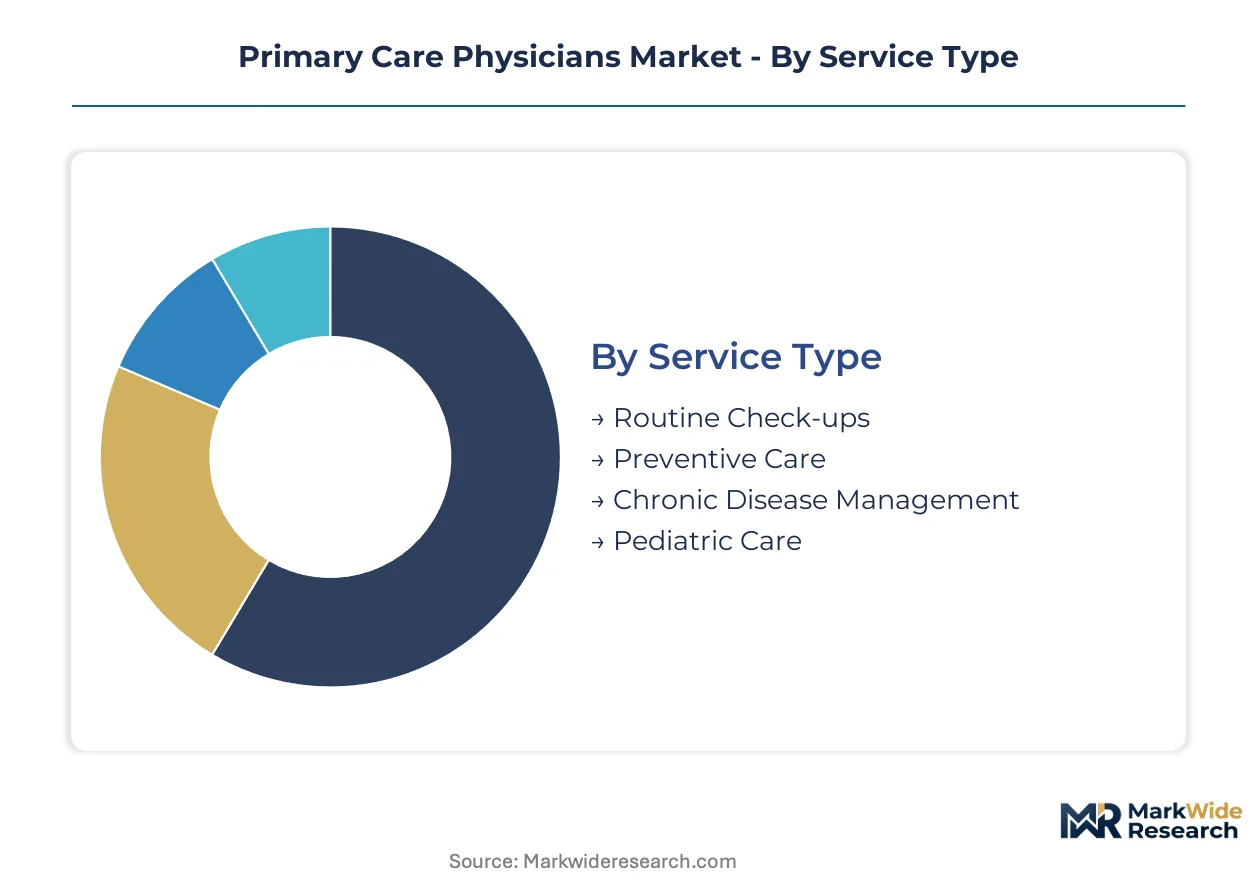
Primary care physicians segment across service intensity, patient risk profiles, care delivery venues, and reimbursement pathways. These divisions determine panel size economics, technology infrastructure requirements, and physician compensation structures within integrated delivery networks.
Service Type:
Standalone preventive encounters generate distinct revenue recognition compared to embedded chronic care workflows within risk-bearing contracts.
- Routine Check-ups:Annual wellness visits and episodic acute assessments constitute the foundational visit type. CMS annual wellness visit billing codes anchor volume in Medicare Advantage contracts across Florida and Arizona retirement corridors.
- Chronic Disease Management:Diabetes, hypertension, and heart failure protocols demand care coordination infrastructure and quality metric reporting. Kaiser Permanente and Geisinger Health deploy these services within global capitation arrangements where outcomes determine margin.
- Preventive Care:Vaccination administration and cancer screening protocols align with IRA-mandated Medicare coverage expansions.
- Pediatric Care:Well-child visits and developmental surveillance anchor family medicine panel retention.
Volume placements concentrate in Routine Check-ups; the faster expansion belongs to Chronic Disease Management.
Patient Type:
Cost tier stratification separates high-utilization geriatric populations from lower-acuity adult panels in physician compensation design.
- Geriatric Patients:Medicare-eligible cohorts with multiple comorbidities drive care coordination complexity. Medicare Advantage penetration in Pennsylvania and Ohio concentrates attributed lives requiring intensive case management.
- Adult Patients:Working-age populations aged 18-64 present undifferentiated complaints and preventive service gaps. Employer-sponsored plans in Texas and North Carolina purchase access through direct-to-employer contracts.
- Pediatric Patients:Medicaid-dependent children in federally qualified health centers require developmental and immunization services.
- Female Patients:Reproductive health and gender-specific screening needs segment within family medicine and OB/GYN integration models.
Panel density peaks with Adult Patients; Geriatric Patients deliver the steepest expansion trajectory as Medicare Advantage enrollment climbs.
Care Setting:
Geographic reach constraints differentiate brick-and-mortar capacity from virtual care scalability in physician practice strategy.
- Outpatient Clinics:Traditional exam room infrastructure retains the highest reimbursement per encounter and procedural revenue capture. Mayo Clinic and Cleveland Clinic anchor market presence through multispecialty campus networks.
- Telehealth Services:Audio-video and audio-only encounters extend panel reach beyond physical catchment areas. Rural health clinics in Montana and Wyoming leverage CMS telehealth parity to maintain access for frontier populations.
- Community Health Centers:Federally qualified health centers serve Medicaid and uninsured populations under cost-based reimbursement.
- Emergency Rooms:Hospital-based emergency departments absorb primary care overflow and after-hours demand.
Encounter volume concentrates in Outpatient Clinics; Telehealth Services are climbing the fastest as audio-only reimbursement persists.
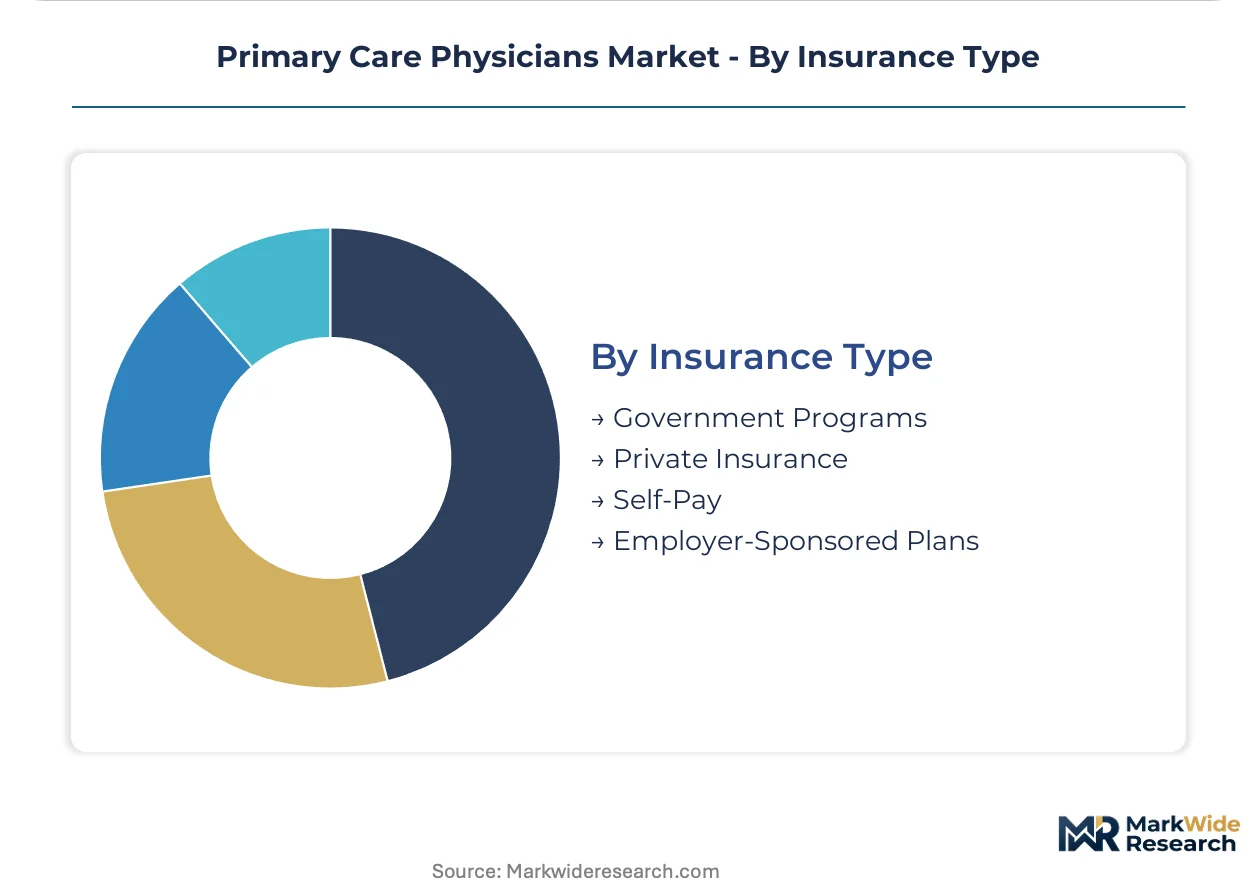
Insurance Type:
Margin stability separates capitated government programs from fee-for-service private arrangements in practice viability calculations.
- Government Programs:Medicare and Medicaid reimbursement schedules set baseline pricing with quality incentive adjustments. CMS physician fee schedule updates and MIPS scoring determine net revenue for practices across Illinois and Michigan.
- Private Insurance:Commercial payer contracts negotiate rates above government benchmarks with prior authorization requirements. Blue Cross Blue Shield plans in Tennessee and Alabama impose utilization management on specialist referrals.
- Self-Pay:Direct primary care memberships bypass insurance intermediaries through monthly subscription models.
- Employer-Sponsored Plans:Self-insured employers purchase primary care access through onsite clinics or direct contracts.
Attributed lives concentrate in Government Programs; Employer-Sponsored Plans are gaining share fastest as direct contracting proliferates.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Human capital pipelines in metropolitan medical centers anchor geographic demand concentration for primary care services. Medicare Advantage enrollment patterns and state-level scope-of-practice regulations reshape where physician labor concentrates.
United States
Medicare Advantage penetration in Florida and Arizona retirement corridors drives geriatric panel expansion. CMS telehealth parity extensions preserve audio-only reimbursement for rural access. Mayo Clinic anchors physician retention across Minnesota, Wisconsin, and Iowa through academic prestige and integrated delivery infrastructure.
Canada
Provincial health authority budgets determine primary care team expansion in Ontario and British Columbia. Health Canada oversight of digital health tools shapes remote monitoring adoption timelines. Toronto and Vancouver medical schools concentrate training capacity, creating urban-rural distribution imbalances.
Germany
Statutory health insurance physician associations negotiate regional care contracts in Bavaria and North Rhine-Westphalia. EMA digital health guidance influences reimbursement for remote patient monitoring devices. Berlin and Munich academic medical centers compete for specialist-trained generalists.
United Kingdom
NHS England primary care networks consolidate general practice contracts across Greater London and the Midlands. GP retention schemes target underserved coastal and rural areas. Manchester and Birmingham integrated care systems test capitated population health models.
Australia
Medicare Benefits Schedule updates determine general practitioner billing rates in New South Wales and Victoria. TGA regulation of software-based medical devices constrains telehealth platform deployment. Sydney and Melbourne private health insurers experiment with direct-to-employer primary care contracts.
Primary Care Physicians Market Vendor Landscape
Physician practice acquisition dominates the current landscape as health systems and payer-affiliated medical groups compete for scarce clinical talent. Market structure tilts toward consolidation, with integrated delivery networks and payer-owned groups absorbing independent practices. Three archetypes define competitive positioning: academic medical center affiliates leveraging research prestige, payer-integrated groups capturing risk-bearing contracts, and independent multi-specialty associations preserving physician governance. M&A activity and direct-to-employer contract pursuit represent the dominant competitive moves reshaping market share.
Within the academic-affiliate tier, Mayo Clinic Physicians and University of Pittsburgh Physicians exemplify retention strategies built on research integration and specialty referral density. Among payer-integrated operators, Optum and Southern California Permanente Medical Group occupy positions where capitated contracts and technology infrastructure create physician employment preference. Hill Physicians Medical Group represents the independent association model, maintaining physician ownership structures while negotiating collective commercial contracts.
| Leading Market Players |
|---|
| Mayo Clinic Physicians |
| RWJBarnabas Health Medical Group |
| Southern California Permanente Medical Group |
| Northwell Health Physician Partners |
| Ascension Medical Group |
| The Permanente Medical Group |
| University of Pittsburgh Physicians |
| Hill Physicians Medical Group |
| Optum |
| Others |
Supply Flow & Price Mechanics
Medicare Advantage plan concentration among geriatric populations anchors risk-adjusted capitation as the dominant pricing model, with CMS quality incentive tiers compressing margins for practices failing HEDIS benchmarks. Fee-for-service reimbursement retains residual share in rural markets where risk-bearing infrastructure remains underdeveloped.
Pricing Analysis
Service bundling separates capitated global budgets from unbundled fee-for-service encounters. Three-tier pricing structure across premium concierge, standard commercial, and Medicaid-safety-net levels reflects panel risk stratification and care coordination intensity. Price differentiation hinges on quality metric attainment and geographic cost-of-labor indices. Pricing pressure stems from CMS physician fee schedule stagnation against inflationary cost growth. Medicaid-dependent practices exhibit highest price sensitivity; direct-to-employer contracted groups demonstrate lowest sensitivity due to captive workforce access premiums.
Supply Chain Analysis
State licensure reciprocity gaps and HIPAA Business Associate Agreement requirements gate multi-state physician group expansion. Clinical labor supply concentrates in the United States, Canada, and the United Kingdom where graduate medical education pipelines feed metropolitan markets. Electronic health record systems, remote patient monitoring devices, and telehealth platforms constitute critical input dependencies. Supply chain risk centers on single-source EHR vendor lock-in and interoperability failure. Distribution runs through integrated delivery networks, federally qualified health centers, and direct-to-employer onsite clinic operators.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Vertical integration into downstream care coordination infrastructure and upstream physician training pipelines defines competitive positioning. Players capturing risk-bearing contracts must control both clinical labor supply and population health management capabilities.
For Market Incumbents: Anchor market position through exclusive Medicare Advantage attribution contracts in Florida and Arizona retirement corridors. Defend against Optum's acquisition-driven scale by deepening academic medical center referral density. Prioritize backward integration into graduate medical education sponsorship to secure pipeline access. Invest in ambient clinical intelligence deployment to compress documentation burden and extend panel capacity without proportional labor expansion. For New Entrants and Emerging Players: Federally qualified health centers in frontier states present the most penetrable channel partner type for risk-bearing contract entry. White-space targets include rural Medicare Advantage markets lacking integrated delivery network presence and employer-sponsored direct contracting in Texas and North Carolina manufacturing corridors. Pursue telehealth-first models exploiting CMS audio-only parity extensions to bypass brick-and-mortar capital requirements. For Investors and Strategic Acquirers: The window for entry favors physician practice management platforms with embedded value-based care infrastructure. Long-term viability rests on attributed lives under global capitation rather than fee-for-service volume aggregation. Target acquisition archetypes include multi-specialty groups with existing Medicare Advantage contracts and proprietary remote patient monitoring technology. Monitor CMS Innovation Center model termination announcements as inflection indicators for risk contract profitability.| Strategic Initiative | Industry Significance |
|---|---|
| Medicare Advantage Risk Contract Acquisition | Captures attributed geriatric lives in Florida and Arizona corridors under capitated reimbursement. |
| Ambient Clinical Intelligence Deployment | Reduces Mayo Clinic physician documentation burden and extends panel capacity without scribe labor. |
| Direct-to-Employer Contracting Expansion | Bypasses traditional payer intermediaries through Texas and North Carolina workforce clinic arrangements. |
| Telehealth Platform Integration | Leverages CMS audio-only parity to serve Montana and Wyoming frontier populations beyond physical catchment. |
| Graduate Medical Education Pipeline Investment | Secures resident placement priority through University of Pittsburgh and Mayo Clinic training affiliations. |
Methodological Framework
Multi-period observation of Medicare Advantage enrollment trajectories, CMS quality metric benchmarks, and physician practice acquisition velocities anchored the trend analysis, supplemented by interviews with health system strategy officers, Medicare Advantage plan actuaries, primary care clinic operators, and GPO contracts managers. Secondary validation drew from CMS Physician Fee Schedule releases, Medicare Advantage plan bid data, hospital procurement databases, and state-level scope-of-practice regulatory filings. Bottom-up panel size economics modeling triangulated against top-down market sizing from integrated delivery network reported lives.
Input-output matrices mapped attributed patient volumes through reimbursement pathway yields across service type, patient risk tier, care setting, and insurance category dimensions. Segmentation modeling incorporated chronic disease prevalence, telehealth adoption curves, and direct-to-employer contract penetration as industry-specific forecast inputs. CAGRs were derived from trend extrapolation of historical enrollment and reimbursement rate movements across the projection horizon.
Caveats apply where CMS Innovation Center model termination, state-level telehealth licensing reciprocity expansion, or physician supply pipeline contraction could materially shift the outlook. Forecasts reflect assumptions regarding Medicare Advantage penetration sustainability and quality program incentive stability. A model refresh is warranted upon material change in CMS physician fee schedule update magnitude or Medicare Advantage benchmark rate methodology.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Healthcare Services
Acute Care Market
Healthcare Services
Assisted Living Market
Healthcare Services
Global Corporate Wellness Solutions Market
Healthcare Services
Retail Clinics Market
Healthcare Services
Global Mobile Clinics Market
Healthcare Services
Contract Manufacturing Services Market
Healthcare Services
US Value-Based Healthcare Service Market
Healthcare Services
Eastern Europe Online Pharmacy Market
Healthcare Services
Global Healthcare Services Market
Healthcare Services
US Retail Clinics Market
Healthcare Services
US Integrated Delivery Network Market
Healthcare Services
Patient Transportation Market
Healthcare Services
Hospital Outsourcing Market
Healthcare Services
Private Healthcare Market
Healthcare Services
Tissue Banking Market
Healthcare Services
Funeral and Cremation Services Market