
 Pediatric Oncology Treatment Market | 2026-2036
Pediatric Oncology Treatment Market Size, Share, and Industry Trends Forecast 2026-2036
Pediatric Oncology Treatment Market Analytics
The United States is tilting toward expanded biologics manufacturing capacity for pediatric indications. Pfizer Inc. leverages its global development network to sustain pediatric trial pipelines across multiple tumor types. Novartis AG anchors its position through specialized CAR-T manufacturing capabilities that serve relapsed leukemia populations. Bristol Myers Squibb Company differentiates via integrated immuno-oncology platforms targeting neuroblastoma and lymphoma subtypes.
Pediatric oncology treatment encompasses therapeutic interventions designed to eliminate or control malignant cell proliferation in patients under eighteen years of age, typically requiring weight-based dosing protocols and age-adjusted toxicity thresholds to accommodate developing organ systems. These treatments serve the primary commercial purpose of extending disease-free survival while preserving long-term neurocognitive and endocrine function in a demographically distinct patient population. Immunotherapy represents the fastest-expanding modality as checkpoint inhibitors and cellular therapies command premium reimbursement and attract venture funding for pediatric-specific indications. Chemotherapy retains the largest patient volume footprint but faces margin compression from biosimilar competition and established generic availability. Targeted therapy occupies a concentrated high-value niche where biomarker-defined subsets justify specialized diagnostic and therapeutic bundling.
The FDA, EMA, and WHO collectively govern pediatric oncology treatment standards through the Pediatric Research Equity Act, the EU Paediatric Regulation, and the WHO Essential Medicines List for children, which mandate dedicated trial designs and influence national reimbursement decisions. These frameworks shape demand by requiring age-appropriate formulation development and extended pharmacovigilance, raising barriers for manufacturers lacking pediatric development infrastructure. Stakeholders must monitor evolving regulatory expectations around real-world evidence generation and adaptive trial designs to sustain market access for novel modalities.
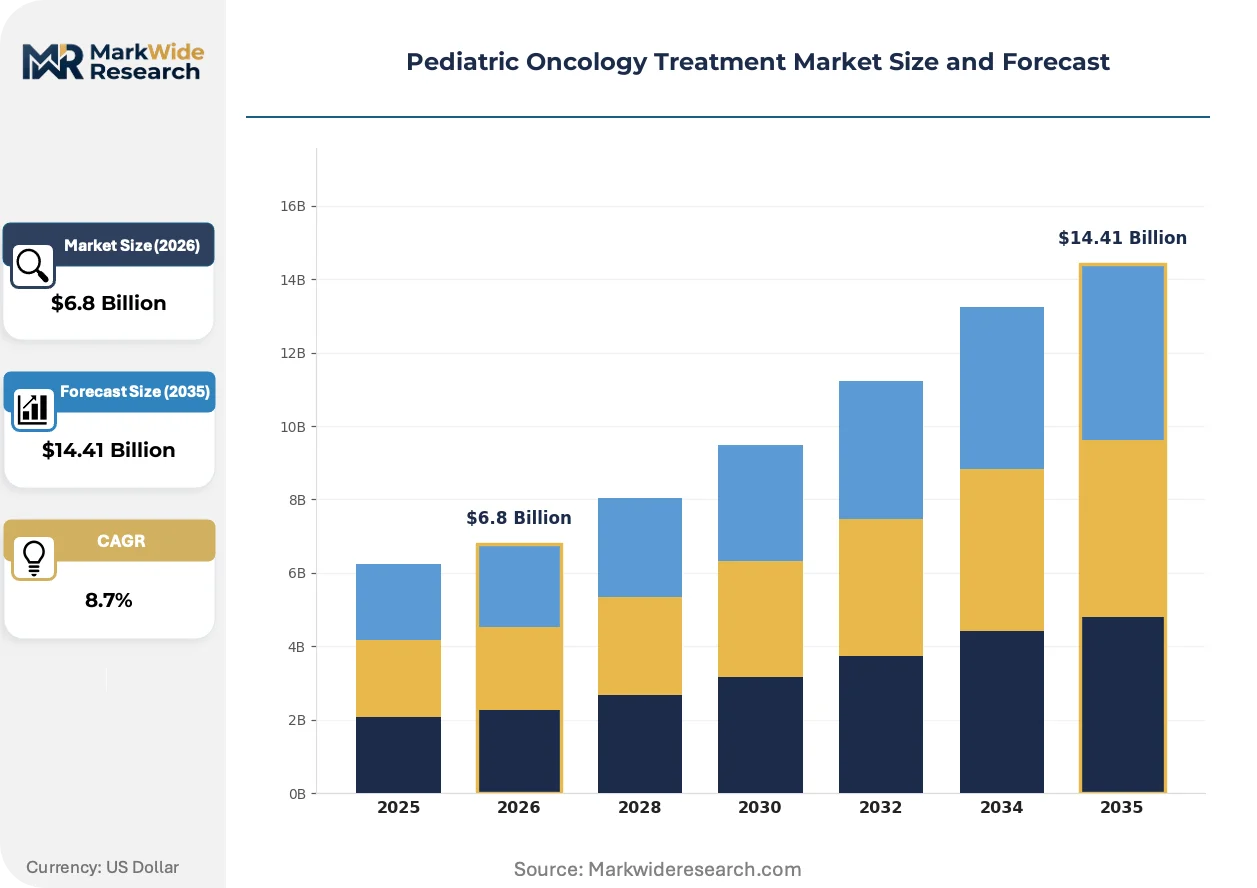
Market Dynamics
The Pediatric Oncology Treatment Market is experiencing structural compression as CAR-T manufacturing capabilities concentrate among a handful of specialized biologics producers, while the FDA's Pediatric Research Equity Act forces parallel adult-pediatric trial designs that accelerate enrollment but strain sponsor resources.
Growth Catalysts
- Regulatory Mandates:The FDA's Pediatric Research Equity Act compels sponsors to submit pediatric study plans alongside adult oncology applications, expanding trial pipelines for childhood cancers.
- Cellular Therapy Infrastructure:Academic medical centers in the United States are building dedicated CAR-T infusion units to capture relapsed leukemia populations requiring chimeric antigen receptor manufacturing.
- Biosimilar Substitution:Generic chemotherapy availability is compressing treatment costs and extending access to platinum-based regimens in previously underserved pediatric populations.
Market Restraints
- Biologics Manufacturing Concentration:Viral vector production for gene-modified cell therapies clusters in North American and European contract manufacturing organizations, creating single-source dependencies.
- Formulation Complexity:Weight-based dosing requirements for developing organ systems necessitate age-appropriate liquid or dispersible tablet development, raising formulation costs above adult equivalents.
- Reimbursement Friction:Medicaid state-level variation in coverage for cellular therapies creates access gaps that delay treatment initiation for publicly insured pediatric patients.
Strategic Opportunities
- Real-World Evidence Generation:The FDA's expanded acceptance of external control arms and registry data creates pathways for post-approval pediatric indication expansion without dedicated placebo-controlled trials.
- Neuroblastoma Immunotherapy:Anti-GD2 antibody consolidation therapy represents an underpenetrated application where biomarker-defined subsets justify premium pricing for minimal residual disease populations.
- Academic Partnership Models:Children's Oncology Group consortium sites offer sponsors pre-qualified trial networks that compress site activation timelines for rare pediatric tumor studies.
Industry Challenges
- Pediatric Formulation Expertise Scarcity:Pharmaceutical development programs lack sufficient toxicologists and pharmacokineticists trained in juvenile animal study design and extrapolation methodologies.
- Long-Term Follow-Up Infrastructure:Survivorship programs require decades of cardiac, endocrine, and neurocognitive monitoring that strains hospital capacity and reimbursement mechanisms.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Pediatric Oncology Treatment Market |
| Market Size in 2026 | $6.8 Billion |
| Market Size in 2035 | $14.41 Billion |
| CAGR (2026 – 2036) | 8.7% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Product Type: Chemotherapy, Radiation Therapy, Immunotherapy, Targeted Therapy End User: Pediatric Hospitals, Specialized Clinics, Research Institutions, Outpatient Facilities Application: Leukemia, Neuroblastoma, Wilms Tumor, Lymphoma Delivery Mode: Intravenous, Oral, Subcutaneous, Intrathecal |
| Companies Covered | Pfizer Inc., Novartis AG, F. Hoffmann-La Roche Ltd., Bristol Myers Squibb Company, Merck & Co., Inc., Sanofi S.A., AbbVie Inc., Takeda Pharmaceutical Company Limited, GlaxoSmithKline plc, Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Pediatric Oncology Treatment Market Evolving Landscape
CAR-T cell engineering and bispecific antibody platforms are collapsing the historical boundary between hematologic and solid tumor treatment paradigms in pediatric oncology, forcing reinvestment across manufacturing and clinical trial infrastructure.
Next-generation sequencing-based minimal residual disease monitoring is collapsing the clinical trial endpoint landscape for acute lymphoblastic leukemia, replacing morphologic remission assessments with molecular relapse detection. Academic medical centers in the United States are adopting these assays for routine surveillance, compressing the window between molecular recurrence and salvage therapy initiation. This molecular precision is collapsing the statistical power requirements for Phase II studies, enabling smaller cohort sizes for rare pediatric indications.
The EMA's Paediatric Investigation Plan requirements are mandating age-appropriate formulation development earlier in the product lifecycle, forcing sponsors to invest in dispersible tablet and oral solution technologies before adult market authorization. This regulatory sequencing is compressing development timelines for European market entry while raising barriers for manufacturers lacking pediatric infrastructure. Oncology sponsors are responding by embedding juvenile toxicology studies into Phase I adult programs to avoid post-approval regulatory delays.
Consolidated procurement by children's hospital networks is displacing individual institutional purchasing for high-cost cellular therapies, with group purchasing organizations negotiating outcomes-based contracts that tie reimbursement to twelve-month event-free survival. This contracting evolution is concentrating buying power among large pediatric health systems in the United States, marginalizing standalone community hospitals. The shift is most visible in leukemia and lymphoma categories where CAR-T products command six-figure price points and require specialized infusion center capabilities.
Pediatric Oncology Treatment Market Segmentation
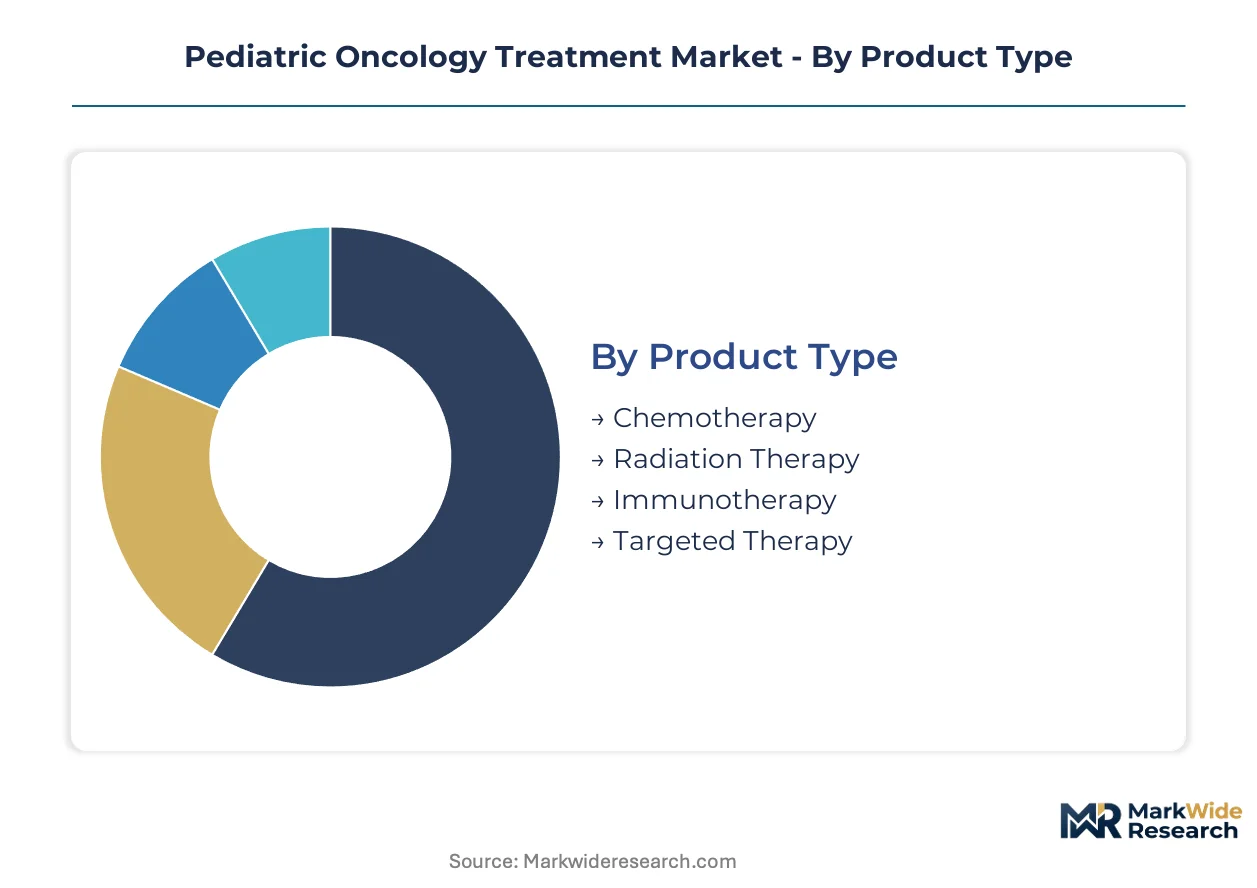
Pediatric oncology treatment segments reflect divergent reimbursement pathways and manufacturing requirements. Product type determines regulatory filing strategy, while end user concentration shapes distribution economics and site-of-care investment priorities.
Product Type:
Cost tier stratification across product categories separates commodity chemotherapy from premium cellular therapies with distinct margin profiles.
- Immunotherapy:Chimeric antigen receptor T-cell therapies and checkpoint inhibitors command premium pricing through specialized manufacturing. Demand concentrates at academic medical centers in the United States where CAR-T infusion units anchor relapsed leukemia treatment pathways.
- Targeted Therapy:Biomarker-directed small molecules require companion diagnostic bundling and pharmacogenomic testing infrastructure. Prescribing concentrates in neuroblastoma and solid tumor subsets where ALK inhibitors and MEK inhibitors demonstrate defined response rates.
- Chemotherapy:Platinum-based and alkylating agents face biosimilar competition with compressed margins.
- Radiation Therapy:Proton beam facilities require capital-intensive infrastructure with limited pediatric-specific capacity.
Immunotherapy holds installed capacity. Targeted therapy is rotating up the share rankings.
End User:
Customer type fragmentation across delivery settings creates distinct procurement and compliance requirements for sponsors.
- Pediatric Hospitals:Comprehensive cancer centers with dedicated oncology units manage complex multi-agent regimens and cellular therapy administration. Volume concentrates at Children's Oncology Group consortium sites in the United States where trial enrollment infrastructure supports investigational therapy access.
- Specialized Clinics:Focused hematology-oncology practices deliver maintenance chemotherapy and surveillance monitoring. Demand clusters in metropolitan areas with established survivorship programs addressing cardiac and endocrine late effects.
- Research Institutions:Academic medical centers anchor Phase I/II pediatric trial networks.
- Outpatient Facilities:Ambulatory infusion centers handle stable chemotherapy administration with lower overhead.
Pediatric hospitals hold installed capacity. Specialized clinics are rotating up the share rankings.
Application:
Disease-specific treatment paradigms vary dramatically in addressable population size and therapeutic maturity.
- Leukemia:Acute lymphoblastic leukemia represents the largest pediatric oncology population with established chemotherapy backbones and expanding CAR-T salvage options. Treatment concentrates at centers with minimal residual disease monitoring capabilities and dedicated stem cell transplant units.
- Neuroblastoma:High-risk disease requires multimodal therapy combining induction chemotherapy, surgery, radiation, and anti-GD2 immunotherapy. Care concentrates at specialized centers with MIBG therapy capabilities and experienced surgical oncology teams.
- Lymphoma:Hodgkin and non-Hodgkin subtypes follow adult-derived protocols with pediatric modifications.
- Wilms Tumor:Renal malignancy management relies on surgical expertise and established cooperative group protocols.
Leukemia holds installed capacity. Neuroblastoma is rotating up the share rankings.
Delivery Mode:
Route of administration determines formulation development requirements and site-of-care economics.
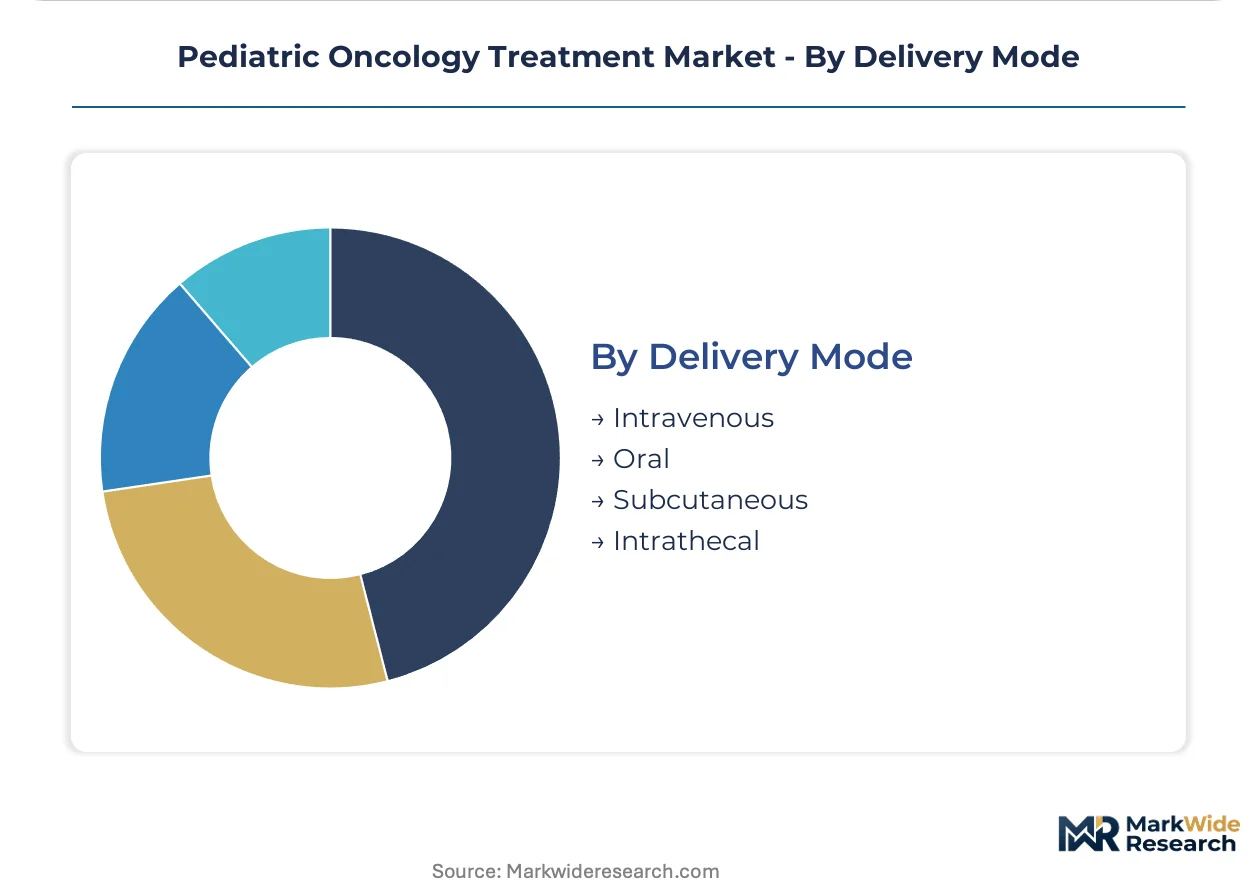
- Intravenous:Infusion-dependent therapies including cytotoxic chemotherapy and monoclonal antibodies require vascular access infrastructure and nursing supervision. Administration concentrates at hospital-based infusion centers with pediatric sedation capabilities.
- Oral:Age-appropriate liquid and dispersible tablet formulations enable outpatient maintenance therapy. Demand clusters where adherence programs and family education resources support home administration of mercaptopurine and other chronic medications.
- Subcutaneous:Interferon and supportive care agents allow reduced site-of-care requirements.
- Intrathecal:CNS-directed therapy requires specialized procedural capabilities and neurosurgical backup.
Intravenous holds installed capacity. Oral is rotating up the share rankings.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
CAR-T manufacturing capacity clusters among contract organizations in the United States and Switzerland, while academic medical centers in Germany and Japan build specialized pediatric infusion units to capture relapsed leukemia populations. The FDA, EMA, and Japan's PMDA each mandate pediatric study plans, creating parallel regulatory pathways that strain sponsor resources but expand trial access.
United States
Academic medical centers in Boston, Houston, and Memphis anchor the majority of Phase I/II pediatric cancer trials through Children's Oncology Group consortium sites. The FDA's Pediatric Research Equity Act compels sponsors to submit pediatric study plans alongside adult oncology applications. Philadelphia and Seattle host specialized CAR-T manufacturing facilities serving relapsed leukemia populations requiring chimeric antigen receptor cell production.
Germany
University hospitals in Heidelberg and Berlin maintain dedicated pediatric oncology units with integrated stem cell transplant capabilities. The EMA's Paediatric Investigation Plan mandates age-appropriate formulation development before adult market authorization. The Rhine-Ruhr and Bavarian hospital networks consolidate procurement for high-cost cellular therapies, negotiating outcomes-based contracts tied to event-free survival metrics.
Switzerland
Basel anchors biologics manufacturing infrastructure with specialized viral vector production for gene-modified cell therapies. Swissmedic enforces pediatric development requirements aligned with EMA frameworks but with accelerated review timelines for orphan indications. The Lake Geneva corridor concentrates pharmaceutical R&D facilities with dedicated juvenile toxicology expertise.
Japan
Pediatric cancer centers in Tokyo and Osaka expand minimal residual disease monitoring capabilities for acute lymphoblastic leukemia surveillance. The PMDA's Sakigake designation system fast-tracks pediatric oncology drugs with breakthrough potential. The Kansai region hosts contract manufacturing organizations building GMP-compliant capacity for Asian-market cell therapy production.
United Kingdom
London's Great Ormond Street Hospital and Manchester's Royal Manchester Children's Hospital lead pediatric early-phase trial enrollment. The MHRA operates under retained EU Paediatric Regulation obligations post-Brexit, maintaining equivalent pediatric study requirements. The Oxford-Cambridge-London golden triangle concentrates immuno-oncology research partnerships between academic institutions and biotech sponsors.
Pediatric Oncology Treatment Market Competitive Landscape
Integrated pharmaceutical conglomerates and specialized biologics manufacturers split the market between broad oncology portfolios and concentrated cell therapy capabilities. The competitive structure tilts toward consolidation as CAR-T manufacturing expertise concentrates among sponsors with captive viral vector production. Three archetypes dominate: diversified Big Pharma with pediatric infrastructure, CAR-T specialists with manufacturing scale, and biotech licensors with platform technologies. Dominant competitive moves include academic medical center partnerships for trial access and backward integration into viral vector production to secure supply.
Within the diversified pharmaceutical tier, Pfizer Inc. and Novartis AG occupy positions reflecting contrasting strategic emphases on global development networks versus specialized manufacturing capabilities. Bristol Myers Squibb Company anchors the immuno-oncology specialist archetype. These three entities exemplify how scale-driven sponsors leverage existing infrastructure to meet PREA-mandated pediatric study requirements while CAR-T-focused players concentrate manufacturing investment in North American and European hubs.
| Leading Market Players |
|---|
| Pfizer Inc. |
| Novartis AG |
| F. Hoffmann-La Roche Ltd. |
| Bristol Myers Squibb Company |
| Merck & Co., Inc. |
| Sanofi S.A. |
| AbbVie Inc. |
| Takeda Pharmaceutical Company Limited |
| GlaxoSmithKline plc |
| Others |
Value Network & Pricing Analysis
CAR-T manufacturing undercapacity in North American contract facilities is driving sponsor behavior toward captive viral vector production and premium pricing postures for relapsed leukemia therapies. This utilization squeeze feeds directly into procurement consolidation by children's hospital networks seeking to secure limited manufacturing slots through outcomes-based contracting.
Pricing Analysis
The FDA's Pediatric Research Equity Act dictates the pricing tier structure by mandating parallel pediatric development that raises fixed costs for sponsors. Pricing stratifies across premium cellular therapies, standard targeted small molecules, and economy chemotherapy tiers where biosimilar competition compresses margins. Cost compression in the chemotherapy segment is intensifying because of generic substitution and platinum-agent commoditization. Medicaid-insured patient populations exhibit highest price sensitivity, while commercially insured families at academic medical centers demonstrate lowest sensitivity due to comprehensive coverage for cellular therapies.
Supply Chain Analysis
Export controls on viral vector manufacturing equipment limit technology transfer to emerging biologics producers, concentrating production in the United States, Switzerland, and Germany. Viral vector production draws from plasmid DNA, specialized cell lines, and GMP-grade reagents as critical inputs. Single-source vulnerability runs through the limited number of contract manufacturing organizations qualified for pediatric CAR-T production. Distribution runs through children's hospital networks with dedicated infusion capabilities rather than community oncology practices.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Fragmentation across pediatric oncology creates entry niches as biomarker-defined subsets proliferate and regional trial infrastructure remains unevenly distributed. The shift toward minimal residual disease monitoring as a standard endpoint is fragmenting treatment protocols and creating specialized service opportunities.
For Market Incumbents: Build regulatory submission expertise as a moat by embedding juvenile toxicology studies into Phase I adult programs. Expand backward integration into viral vector production to secure supply for CAR-T pipelines. Consolidate trial access through exclusive partnerships with Children's Oncology Group consortium sites to lock out emerging competitors.
For New Entrants and Emerging Players: Southeast Asian pediatric oncology markets remain underpenetrated by cellular therapy sponsors, presenting white-space opportunities for regional licensing partnerships. Target neuroblastoma immunotherapy as the most penetrable indication where anti-GD2 antibody consolidation therapy lacks established competitors. Pursue academic medical center joint ventures as the primary go-to-market angle to access pre-qualified trial networks.
For Investors and Strategic Acquirers: Recurring-revenue conversion is highest among platform-technology biotechs with multiple pediatric indication expansion pathways. Long-term viability over the next decade hinges on pipeline depth beyond initial approved indications. Acquisition targets should display CAR-T manufacturing capabilities or bispecific antibody platforms. Watch FDA pediatric study plan submission volumes as the signal indicating sponsor commitment and market expansion timing.
| Strategic Initiative | Industry Significance |
|---|---|
| Pediatric Study Plan Submission | FDA PREA compliance accelerates trial enrollment through parallel adult-pediatric designs. |
| CAR-T Manufacturing Scale-Up | Captive viral vector production insulates supply from contract manufacturing bottlenecks. |
| Academic Medical Center Partnership | Children's Oncology Group access compresses site activation timelines for rare tumor studies. |
| Real-World Evidence Generation | Registry data pathways enable post-approval indication expansion without placebo-controlled trials. |
| Juvenile Toxicology Integration | Early embedding into adult Phase I programs avoids European regulatory delays from EMA Paediatric Investigation Plans. |
Research Methodology
Cross-validation between regulatory filing databases and hospital procurement records anchors the qualitative findings in this analysis. Primary interviews with pediatric oncology drug development executives, regulatory affairs leads, hospital procurement managers, and payer access specialists were combined with secondary validation from FDA filings, EMA submissions, ClinicalTrials.gov, and formulary databases. Bottom-up patient population estimates and top-down market sizing triangulate to produce converged figures.
Calibration against historical approval timelines and reimbursement decision patterns informs the analytical framework across the projection horizon. Segmentation dimensions modeled include treatment line, dosage form, administration route, and regional regulatory cluster. CAGRs were derived from epidemiological trend analysis and therapy penetration assumptions. Forecast inputs incorporate pediatric trial enrollment velocity and cellular therapy manufacturing capacity expansion plans.
Macroeconomic conditions sit as an overlay; deviation in Medicaid funding levels and biologics reimbursement policy would shift the trajectory. Forecasts reflect assumptions around regulatory pathway stability and manufacturing scale-up execution. Material shifts in FDA pediatric study plan requirements or EMA Paediatric Investigation Plan enforcement would require updated calibration.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Pediatrics
Pediatric Obesity Management Market
Pediatrics
Paediatric Spasticity Treatment Market
Pediatrics
Pediatric Asthma Treatment Market
Pediatrics
Paediatric Neuropsychiatric Disorders Treatment Market
Pediatrics
Pediatric Growth Hormone Deficiency Market
Pediatrics
Pediatrics Medicine Market
Pediatrics
Middle East and Africa Pediatric Healthcare Market
Pediatrics
Pediatric Nasal Cannula Market
Pediatrics
Paediatric Influenza Treatment Market
Pediatrics
Global Pediatric Radiology Market
Pediatrics
Autism Service Platform Market
Pediatrics
Paediatric Wheelchairs Market
Pediatrics
Pediatric Craniosynostosis Treatment Market
Pediatrics
Pediatric Catheter Market
Pediatrics
Pediatric Perfusion Products Market
Pediatrics
Pediatric Tube Feeding Market