
 Outpatient Clinics Market | 2026-2036
Outpatient Clinics Market Size, Share, and Industry Trends Forecast 2026-2036
Outpatient Clinics Market Outlook
CMS site-neutral payment policy is hardening the cost-of-entry calculus for hospital-affiliated outpatient clinics seeking Medicare reimbursement parity. HCA Healthcare leverages its scale across freestanding emergency departments and urgent care networks to sustain geographic density in high-growth Sun Belt metros. Kaiser Permanente anchors its integrated model through captive insurance and in-house specialist staffing, competing on total cost of care rather than visit volume.
Outpatient clinics are healthcare delivery facilities that provide diagnosis, treatment, and preventive services without overnight patient admission, typically operating through physician-led teams with on-site laboratory, imaging, and minor procedural capabilities including endoscopy, arthroscopy, and infusion therapy. Specialty care and urgent care represent the fastest-expanding service type segments, with urgent care capturing walk-in volume diverted from overcrowded emergency departments and specialty care commanding premium reimbursement for cardiology, orthopedics, and gastroenterology procedures. The payment model dimension shows value-based arrangements gaining traction among employers and insurance providers seeking to cap episodic costs, while fee-for-service still dominates in smaller independent practices with limited actuarial infrastructure.
US regulation shapes this market through CMS reimbursement rules, HIPAA data interoperability mandates, and state-level certificate-of-need laws that restrict facility expansion in 35 states. FDA oversight of in-clinic medical devices and OSHA workplace safety standards further constrain operational design and capital deployment timelines. Stakeholders must monitor whether Medicare Advantage penetration shifts site-of-service incentives faster than traditional fee-for-schedule adjustments can adapt.
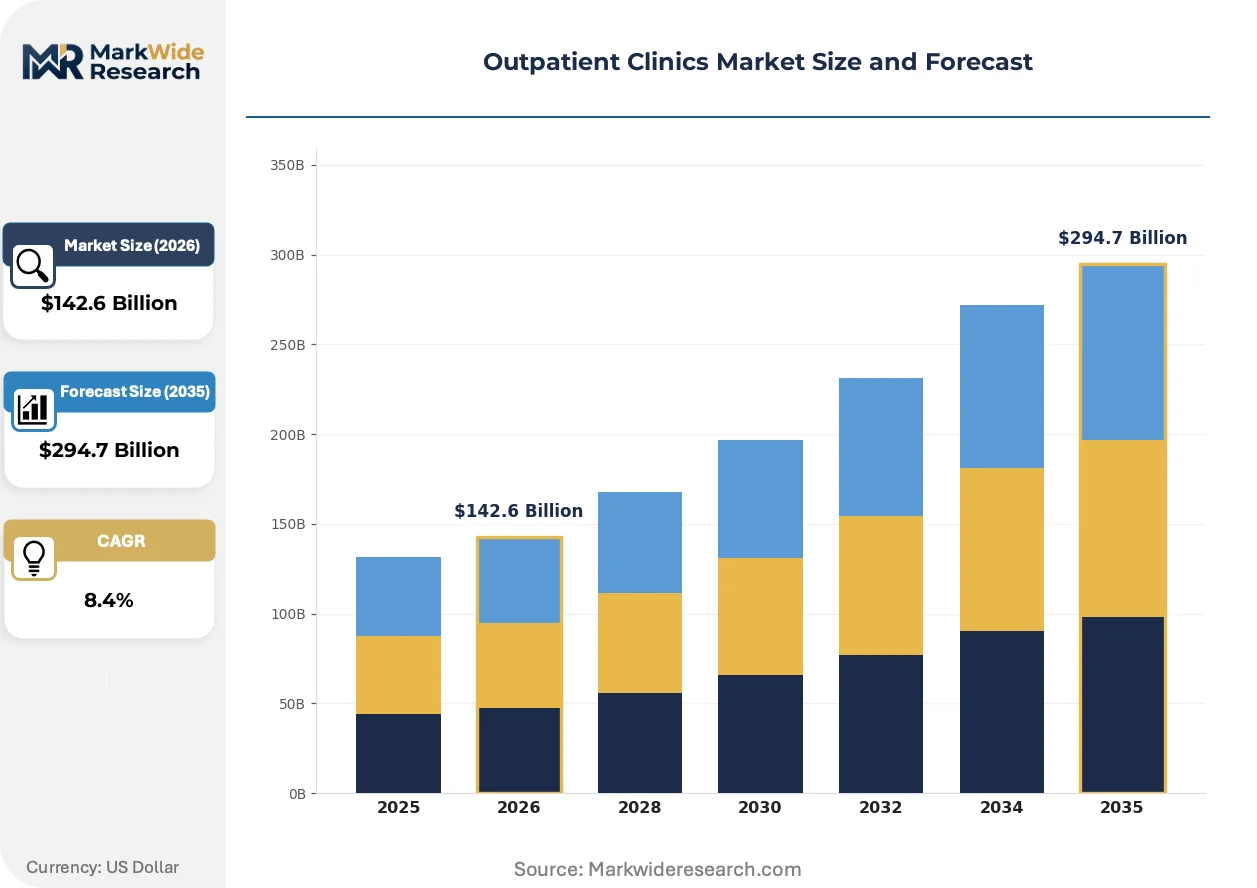
Market Dynamics
CMS site-neutral payment policy is hardening the cost-of-entry calculus for hospital-affiliated outpatient clinics seeking Medicare reimbursement parity, forcing capital allocation toward freestanding ambulatory surgery centers and urgent care networks.
Growth Catalysts
- Employer-sponsored specialty utilization:Large self-insured employers are directing cardiology and orthopedic volume toward outpatient settings to capture lower episode costs and reduce emergency department diversion.
- Texas-Florida-California cluster density:Population migration to Sun Belt metros is concentrating demand in metropolitan statistical areas with favorable certificate-of-need environments and expedited facility licensing.
- Value-based payment infrastructure:Medicare Advantage penetration and bundled payment pilots are aligning site-of-service incentives with total cost-of-care metrics rather than visit volume.
Market Restraints
- Certificate-of-need supply concentration:Thirty-five states restrict facility expansion through CON laws, entrenching incumbent hospital systems and blocking independent clinic entry in protected service areas.
- CMS reimbursement compression:Site-neutral payment rules eliminate off-campus hospital outpatient department rate premiums, compressing margins for capital-intensive specialty service lines.
- Labor cost volatility:Specialist physician and certified registered nurse anesthetist shortages are driving compensation inflation above procedure reimbursement growth rates.
Strategic Opportunities
- Ambulatory surgery center carve-outs:Joint venture structures between physicians and health systems in Texas and Florida enable de novo ASC development with reduced regulatory friction.
- Telehealth-physical hybrid models:Integration of remote patient monitoring with in-clinic procedural capability is expanding addressable catchment areas beyond traditional drive-time radii.
- IRA site-of-service incentives:Medicare drug price negotiation provisions are redirecting infusion therapy volume toward lower-cost community oncology clinics.
Industry Challenges
- EHR interoperability gaps:HIPAA data exchange mandates remain technically fragmented, forcing redundant clinical documentation across hospital-affiliated and independent clinic networks.
- OSHA workplace safety compliance:Infection control and bloodborne pathogen standards require capital-intensive facility modifications for minor procedure suites.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Outpatient Clinics Market |
| Market Size in 2026 | $142.6 Billion |
| Market Size in 2035 | $294.7 Billion |
| CAGR (2026 – 2036) | 8.4% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: Primary Care, Specialty Care, Urgent Care, Rehabilitation End User: Individuals, Families, Employers, Insurance Providers Procedure Type: Diagnostic Imaging, Minor Surgeries, Preventive Care, Therapeutic Treatments Payment Model: Out-of-Pocket, Managed Care, Fee-for-Service, Value-Based |
| Companies Covered | HCA Healthcare, Johns Hopkins Medicine, Ascension, Summa Health, Atlantic Health System, Kaiser Permanente, NYU Langone Health, NewYork-Presbyterian, Tenet Healthcare, Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Outpatient Clinics Market Strategic Shifts
Digital health infrastructure is rewriting how outpatient clinics capture, route, and monetize patient volume across competing sites of service.
Remote patient monitoring platforms combined with AI-enabled triage algorithms are rewriting the traditional primary care referral pathway. Large employer health plans and Medicare Advantage organizations are deploying these tools to intercept emergency department-bound patients. The structural consequence is compressing the addressable market for hospital-affiliated urgent care networks while expanding same-day access capacity at independent clinics.
CMS site-neutral payment final rules are eliminating rate differentials between on-campus and off-campus hospital outpatient departments. The industrial consequence is accelerating divestiture of non-core outpatient assets by integrated delivery networks. Cardiology and gastroenterology service lines in Florida and California are most affected, with health systems responding through joint venture ASC structures that preserve physician alignment while shedding facility cost burdens.
Self-insured employers are unbundling specialty care from traditional PPO networks and contracting directly with outpatient clinics for bundled episodes. Direct-to-employer channel disruption is replacing intermediary payer relationships in manufacturing and logistics sectors. This pattern is most visible in Texas metropolitan areas where large employers operate self-funded health plans with sufficient covered lives to justify dedicated clinic capacity.
Outpatient Clinics Market Segmentation
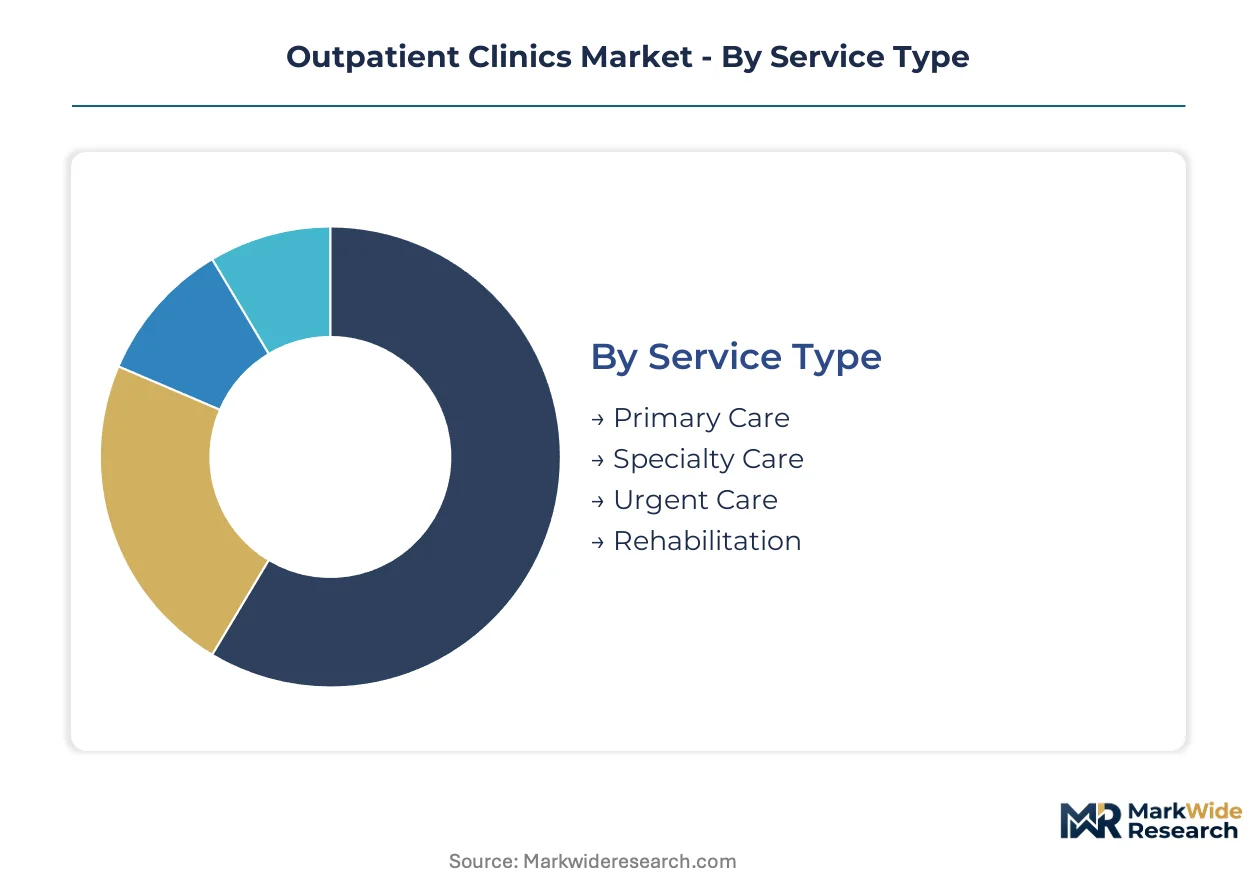
Outpatient clinic operators configure service portfolios around reimbursement mechanics and patient acquisition economics. Segment-level positioning determines capital intensity, staffing ratios, and regulatory exposure across competing sites of service.
Service Type:
Technical sophistication and procedural capability define competitive differentiation across service lines.
- Specialty Care:Cardiology, orthopedics, and gastroenterology procedures command premium reimbursement through dedicated procedure suites and specialist physician staffing. Demand concentrates in employer-sponsored populations seeking bundled episode pricing for high-cost interventions, with Texas and Florida metros showing dense ASC development.
- Urgent Care:Walk-in diagnostic and minor treatment capacity operates through extended hours and rapid throughput protocols. Volume is diverting from overcrowded hospital emergency departments in Sun Belt migration corridors, particularly California metropolitan statistical areas with favorable certificate-of-need environments.
- Primary Care:Preventive and chronic disease management services anchor patient panel relationships and referral pipeline control.
- Rehabilitation:Physical and occupational therapy protocols support post-acute recovery and workers compensation case management.
Mature deployment sits with Primary Care. Newer deployment is concentrated in Specialty Care.
End User:
Procurement authority and risk-bearing status reshape contracting terms and site-of-service incentives.
- Employers:Large self-insured entities direct specialty volume through direct contracts and narrow network arrangements. Manufacturing and logistics sectors in Texas are unbundling cardiology and orthopedic episodes from traditional PPO structures.
- Insurance Providers:Medicare Advantage organizations and commercial carriers deploy utilization management to steer patients toward lower-cost ambulatory settings. Site-of-service incentives align with total cost-of-care metrics rather than visit volume.
- Individuals:Cash-pay and high-deductible plan patients select clinics based on transparent pricing and accessibility.
- Families:Multi-member household utilization patterns favor convenient locations and extended operating hours.
Volume leadership rests with Insurance Providers. Fastest expansion is occurring among Employers.
Procedure Type:
Capital equipment requirements and regulatory classification determine facility licensing pathways and reimbursement tiers.
- Minor Surgeries:Endoscopy, arthroscopy, and ophthalmology procedures require certified procedure suites and anesthesia capability. Joint venture structures between physicians and health systems in Florida enable de novo ASC development with reduced regulatory friction.
- Diagnostic Imaging:MRI, CT, and ultrasound capacity supports same-day diagnosis and specialist referral acceleration. CMS site-neutral payment rules are compressing rate differentials between hospital-affiliated and independent imaging centers.
- Preventive Care:Screening protocols and wellness examinations drive patient panel acquisition and risk stratification.
- Therapeutic Treatments:Infusion therapy and injection protocols are redirecting toward community oncology clinics under IRA site-of-service incentives.
Revenue concentration favors Minor Surgeries. Steepest expansion trajectory is visible in Diagnostic Imaging.
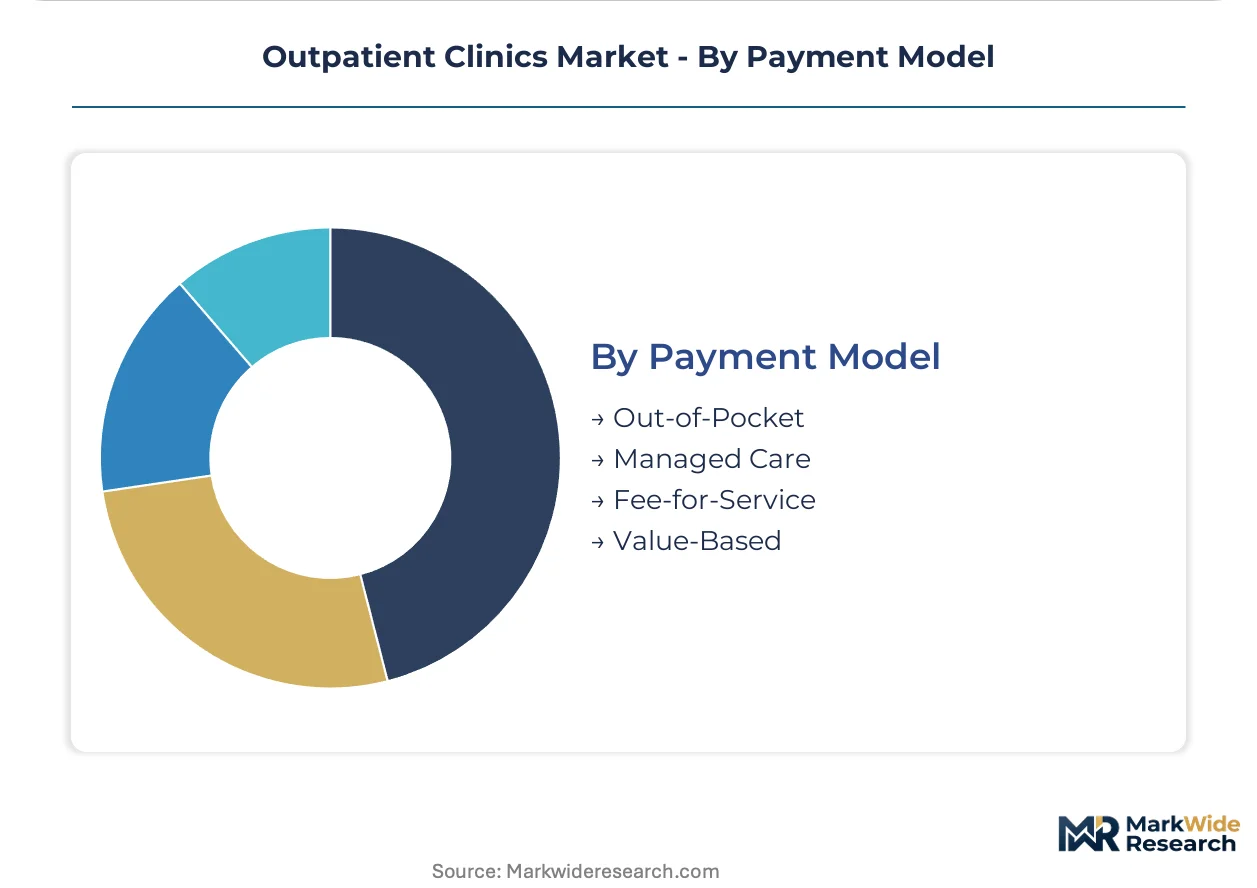
Payment Model:
Revenue predictability and administrative burden vary sharply across contractual structures.
- Value-Based:Bundled episodes and capitation arrangements align clinic economics with outcome metrics and cost containment. Medicare Advantage penetration is accelerating adoption among clinics with sufficient actuarial infrastructure.
- Fee-for-Service:Per-visit reimbursement dominates smaller independent practices with limited risk-bearing capability. Margins face compression from CMS site-neutral payment final rules eliminating off-campus hospital outpatient department premiums.
- Managed Care:PPO and HMO network participation requires prior authorization compliance and discounted rate acceptance.
- Out-of-Pocket:Cash pricing transparency attracts high-deductible plan patients and uninsured populations.
Established volume flows through Fee-for-Service. Structural shift is concentrating in Value-Based.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Texas Opportunity Zones and Florida Qualified Opportunity Funds are concentrating ambulatory surgery center investment in Sun Belt metropolitan corridors. Population migration patterns and favorable certificate-of-need environments are reshaping facility deployment economics across high-growth tax-advantaged districts.
United States
Employer-sponsored specialty utilization and Medicare Advantage penetration are redirecting cardiology and orthopedic volume toward outpatient settings. CMS site-neutral payment rules are eliminating rate premiums for off-campus hospital outpatient departments. The Texas-Florida-California cluster anchors ASC development, with Houston and Dallas-Fort Worth metros showing dense joint venture formation between physicians and health systems.
Germany
Ambulatory care restructuring under the Hospital Structure Reform Act is accelerating day-clinic specialization in orthopedics and ophthalmology. EMA medical device regulations and BfArM digital health approvals are shaping procedure suite certification requirements. The North Rhine-Westphalia and Bavaria regions concentrate outpatient surgical capacity, with Munich and Cologne anchoring multi-specialty clinic networks.
United Kingdom
NHS England elective recovery targets are expanding independent sector capacity for diagnostic and minor surgical procedures. CQC registration requirements and MHRA device oversight constrain facility licensing timelines. The Greater London and Greater Manchester clusters are absorbing diverted NHS waiting list volume through independent outpatient operators.
India
Cash-pay demand for elective procedures and medical tourism corridors are driving corporate outpatient chain expansion. CDSCO medical device rules and state-level clinical establishment acts regulate facility licensing. The Maharashtra and Karnataka metros—Mumbai, Pune, Bangalore—anchor multi-city day-care surgery networks targeting NRI and domestic insured populations.
Australia
Private health insurance tiered coverage is steering elective surgery toward day hospitals and specialist clinics. TGA device regulation and state health department licensing govern procedure suite accreditation. The New South Wales and Victoria markets—Sydney and Melbourne corridors—concentrate ambulatory surgical center investment aligned with private insurer network contracts.
Outpatient Clinics Market Competitive Environment
United States health systems anchor one tier through integrated delivery networks and captive insurance structures; European and Asia-Pacific specialists hold position through public-private partnership models and medical tourism corridors. Market structure tilts toward consolidation among multi-state operators with scale to absorb CMS reimbursement compression. Three archetypes dominate: vertically integrated payer-provider combinations, physician-led joint venture platforms, and corporate chains with standardized procedure protocols. Competitive moves center on ASC carve-out joint ventures and telehealth-physical hybrid integration to extend catchment radii.
Within the integrated payer-provider tier, Kaiser Permanente exemplifies total-cost-of-care competition through captive insurance and in-house specialist staffing. HCA Healthcare and Tenet Healthcare occupy positions among the scale-driven multi-state operators leveraging geographic density across freestanding emergency departments and urgent care networks. These three entities represent distinct capital deployment strategies—captive integration, acquisition-led expansion, and joint venture physician alignment—reflecting divergent responses to site-neutral reimbursement pressure.
| Leading Market Players |
|---|
| HCA Healthcare |
| Johns Hopkins Medicine |
| Ascension |
| Summa Health |
| Atlantic Health System |
| Kaiser Permanente |
| NYU Langone Health |
| NewYork-Presbyterian |
| Tenet Healthcare |
| Others |
Value Chain & Pricing Dynamics
Medical device raw material indices, particularly titanium alloy and specialty polymer benchmarks, cascade through outpatient clinic supply chains into tiered service pricing. CMS site-neutral payment rules compress rate differentials between hospital-affiliated and independent facilities, forcing procurement teams to rebalance capital equipment sourcing toward lower-cost certified suppliers.
Pricing Analysis
Short lead-time premiums for imaging equipment and procedure suite installations command 15-25% markups over standard delivery schedules in high-demand Sun Belt metros. Three-tier pricing structure across premium, standard, and economy levels segments by certification grade (Joint Commission accreditation vs state licensure only) and geographic delivery cost. Pricing pressure stems from CMS reimbursement compression eliminating off-campus hospital outpatient department rate premiums. Self-insured employers show least price sensitivity due to bundled episode contracting, while high-deductible individual patients drive hardest bargain for transparent cash pricing.
Supply Chain Analysis
FDA 510(k) clearance and state facility licensing requirements gate entry for imaging equipment and procedure suite vendors, concentrating qualified supplier pools. Equipment manufacturing concentrates in the United States, Germany, and Japan for advanced diagnostic and surgical platforms. Supply chains draw from semiconductor components, rare earth magnets for MRI systems, and sterile disposable consumables. Single-source vulnerability runs through specialized anesthesia machine and endoscope suppliers. Distribution runs through health system GPO contracts, direct manufacturer relationships, and regional medical equipment distributors serving independent clinic networks.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
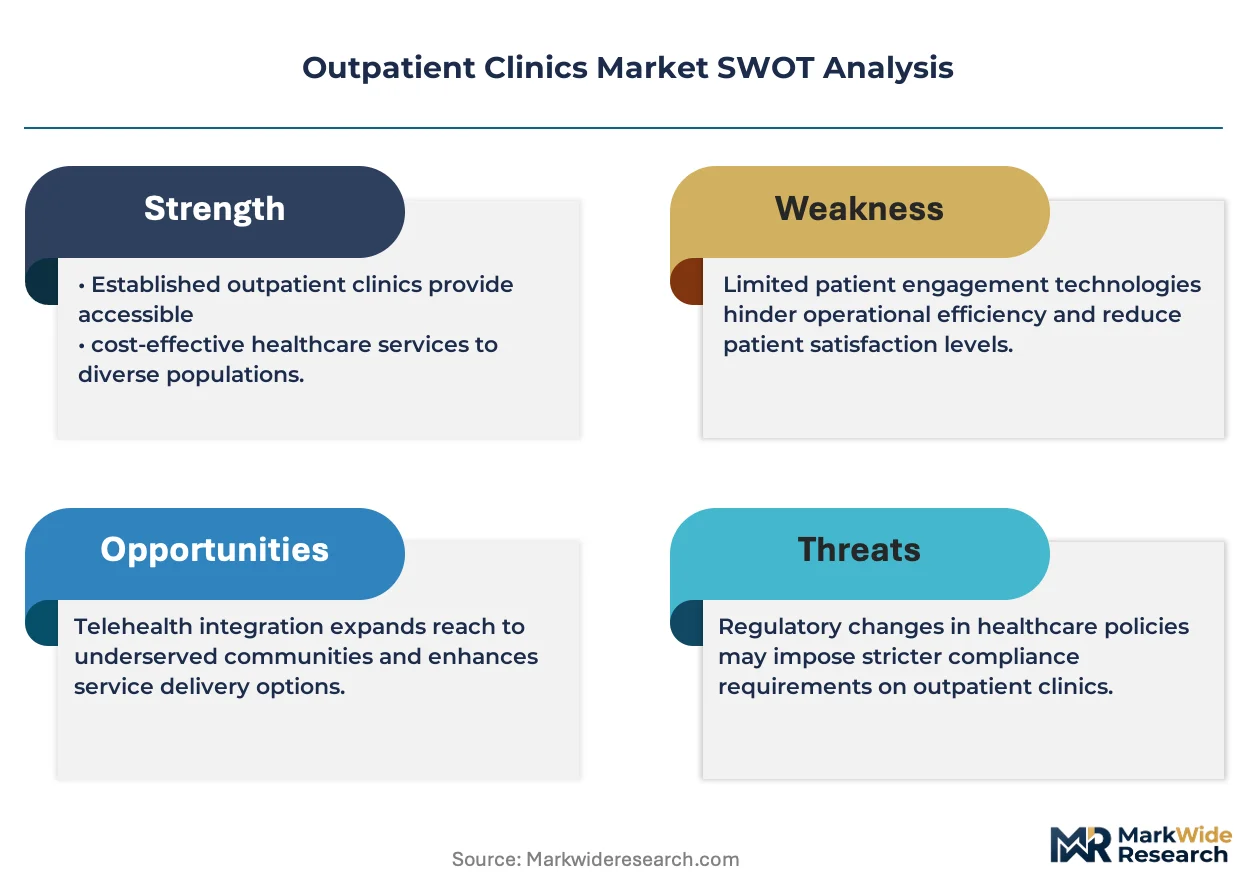
The outpatient clinic sector sits in a technology-transition phase as remote patient monitoring platforms and AI-enabled triage algorithms displace traditional referral pathways and emergency department diversion models.
For Market Incumbents: Deepen captive payer relationships through Medicare Advantage plan sponsorship and direct employer contracting to offset CMS fee-for-service compression. Acquire independent specialty practices in Texas and Florida Opportunity Zones to secure de novo ASC development rights before certificate-of-need saturation. Prioritize EHR interoperability investments to reduce redundant documentation costs across hospital-affiliated networks. For New Entrants and Emerging Players: Capture employer-sponsored specialty carve-out contracts in manufacturing and logistics sectors unbundling cardiology and orthopedic episodes from traditional PPO structures. The most penetrable white space sits in telehealth-physical hybrid models extending catchment radii beyond traditional drive-time constraints. Pursue joint venture ASC structures with health systems seeking to shed facility cost burdens under site-neutral payment rules. For Investors and Strategic Acquirers: Distressed-cycle entries favor physician-led joint venture platforms in Texas and Florida metros with expedited facility licensing and favorable CON environments. Long-term viability hinges on total-cost-of-care contracting capability rather than visit volume metrics. Watch Medicare Advantage penetration rates as the inflection indicator for site-of-service incentive alignment.| Strategic Initiative | Industry Significance |
|---|---|
| ASC Joint Venture Formation | Enables physician alignment while shedding facility cost burdens under CMS site-neutral rules. |
| Telehealth-Physical Hybrid Integration | Expands addressable catchment areas beyond traditional drive-time radii for specialty services. |
| Direct Employer Contracting | Captures bundled episode volume from self-insured manufacturing and logistics sector plans. |
| Medicare Advantage Plan Sponsorship | Aligns site-of-service incentives with total cost-of-care metrics rather than visit volume. |
| EHR Interoperability Investment | Reduces redundant clinical documentation costs across hospital-affiliated clinic networks. |
Study Parameters
Document review covered CMS reimbursement rulemakings, state certificate-of-need statutes, FDA 510(k) clearance databases, and hospital procurement records, complemented by interviews with ambulatory surgery center administrators, health system strategy officers, GPO contract managers, and Medicare Advantage plan executives. Secondary validation drew from CMS Medicare cost reports, state health department licensing data, and ambulatory surgical facility accreditation records. Bottom-up clinic capacity and utilization estimates were triangulated against top-down payer claims data across the analysis window.
Historical volume trajectories were cross-referenced against panel input from payer strategists and facility operators to anchor projection assumptions. The analytical framework modeled service type, payment model, procedure category, and geographic regulatory cluster dimensions throughout the forecast period. CAGRs were derived from segmented growth rate reconciliation against macro healthcare expenditure trends. Forecast inputs incorporated Medicare Advantage penetration assumptions, site-neutral payment implementation timelines, and Sun Belt population migration patterns.
Forecast confidence holds firmest in the near-window; longer-horizon outcomes carry greater sensitivity to CMS reimbursement rule changes and state-level CON law modifications. Forecasts reflect documented assumptions about employer-sponsored plan design evolution and specialty physician supply constraints. A model refresh is warranted upon material change in Medicare Advantage site-of-service incentive structures or federal certificate-of-need preemption legislation.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Healthcare Services
Medical Case Management Services Market
Healthcare Services
Medical Devices and Equipment Logistics Market
Healthcare Services
Retail Clinics Market
Healthcare Services
Healthcare Patent Filing Outsourcing Market
Healthcare Services
United States Senior Living Market
Healthcare Services
Canada Senior Living Market
Healthcare Services
Europe Pharmaceutical Cold Chain Logistics Market
Healthcare Services
Global Healthcare Provider Network Management Market
Healthcare Services
Life Science Trade Lane Design and Qualification Services Market
Healthcare Services
Inhaled and Intranasal Products Contract Service Providers Market
Healthcare Services
Medical Recruitment Market
Healthcare Services
US Hospice Market
Healthcare Services
Michigan Urgent Care Center Market
Healthcare Services
Global Mobile Clinics Market
Healthcare Services
Per Diem Nurse Staffing Market
Healthcare Services
Global Cord Blood Banking Services Market