
 Opioid Use Disorder (OUD) Market | 2026-2036
Opioid Use Disorder (OUD) Market Size, Share, and Industry Trends Forecast 2026-2036
Opioid Use Disorder (OUD) Market Analysis
Modular dosing formats are decoupling medication delivery from fixed clinical schedules, giving physicians flexibility to match buprenorphine regimens with patient stability levels. Indivior PLC leverages its film and depot formulations to sustain brand loyalty across diverse care settings. Alkermes competes through its extended-release naltrexone platform, which anchors long-term adherence programs in correctional and reentry facilities. Orexo AB specializes in sublingual tablet innovations that differentiate on abuse-deterrence claims.
Opioid Use Disorder comprises a chronic relapsing condition characterized by compulsive opioid use despite harmful consequences, with diagnostic criteria spanning tolerance, withdrawal, and unsuccessful quit attempts per DSM-5 parameters. Medication-Assisted Treatment dominates clinical protocols by combining FDA-approved pharmacotherapies with behavioral interventions, while the Drug Type dimension shows buprenorphine formulations capturing expanded prescriber bases due to DEA waiver expansions. Telehealth represents the fastest-growing Care Setting segment, as remote induction protocols mature and state Medicaid programs broaden reimbursement.
The US FDA and DEA jointly govern product approvals and prescriber access pathways, with REMS requirements shaping how manufacturers distribute buprenorphine products through certified clinicians. State-level Medicaid agencies and the Substance Abuse and Mental Health Services Administration further condition market access through formulary placement and block-grant funding priorities. Stakeholders must monitor evolving parity enforcement between mental health and medical benefits, as this determines patient out-of-pocket exposure and sustained treatment retention.
Market Dynamics
The DEA's expanded waiver protocols for buprenorphine prescribing are dismantling the clinical bottleneck that historically constrained medication-assisted treatment capacity. This regulatory relaxation is redistributing patient flow from specialized addiction centers toward primary care offices and telehealth platforms.
Growth Catalysts
- Medicaid Expansion:State-level coverage expansions under the Affordable Care Act framework are eliminating prior authorization barriers for long-acting injectable formulations. Rural counties in states like Ohio and Kentucky report treatment initiation rates climbing as reimbursement parity takes hold.
- Telehealth Infrastructure:Remote induction protocols validated during public health emergencies are now embedding permanently into Federally Qualified Health Center workflows. Patients in transportation-desert regions access buprenorphine initiation without physical clinic presence.
- Correctional Health Integration:Reentry facilities in Texas, California, and Pennsylvania are adopting extended-release naltrexone as standard discharge protocol. This institutional channel creates predictable demand volumes independent of outpatient market volatility.
Market Restraints
- Active Pharmaceutical Ingredient Concentration:Synthesis of buprenorphine base depends on specialized alkaloid extraction capacity concentrated in Indian and Turkish manufacturing clusters. Geopolitical friction or export licensing delays transmit directly into formulation shortages.
- DEA Production Quotas:Annual aggregate production limits for Schedule III opioid analgesics create hard ceilings on market expansion regardless of clinical demand signals. Quota allocation hearings introduce 12-18 month lag between demand recognition and supply response.
- Behavioral Health Workforce Density:Psychiatrists and addiction medicine specialists remain concentrated in coastal metropolitan statistical areas. The American Board of Addiction Medicine certification pipeline produces fewer than 500 new specialists annually against replacement demand.
Strategic Opportunities
- Justice-Involved Populations:State departments of correction in Florida, Arizona, and Michigan lack systematic medication-assisted treatment protocols during incarceration. Vendors establishing preferred provider status with state procurement offices capture multi-year sole-source contracts.
- Digital Therapeutics Convergence:Smartphone-based contingency management applications paired with pharmacotherapy show adherence improvement in pilot programs. FDA breakthrough device designation pathways for software-as-medical-device products offer accelerated market entry.
- Pharmacy-Based Induction:Collaborative practice agreements enabling pharmacists to initiate buprenorphine are expanding in Idaho, New Mexico, and North Carolina. This channel bypasses physician appointment scarcity and captures patients at point of withdrawal crisis.
Industry Challenges
- REMS Compliance Architecture:The Risk Evaluation and Mitigation Strategy mandates prescriber certification, patient counseling documentation, and pharmacy verification systems. Smaller practices lack electronic health record integrations that automate these workflows, creating administrative abandonment of eligible patients.
- Stigma-Induced Provider Reluctance:Primary care physicians with valid DEA waivers frequently decline to prescribe due to patient panel composition concerns or perceived liability exposure. This behavioral gap between authorized capacity and actual prescribing persists despite training investments.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Opioid Use Disorder (OUD) Market |
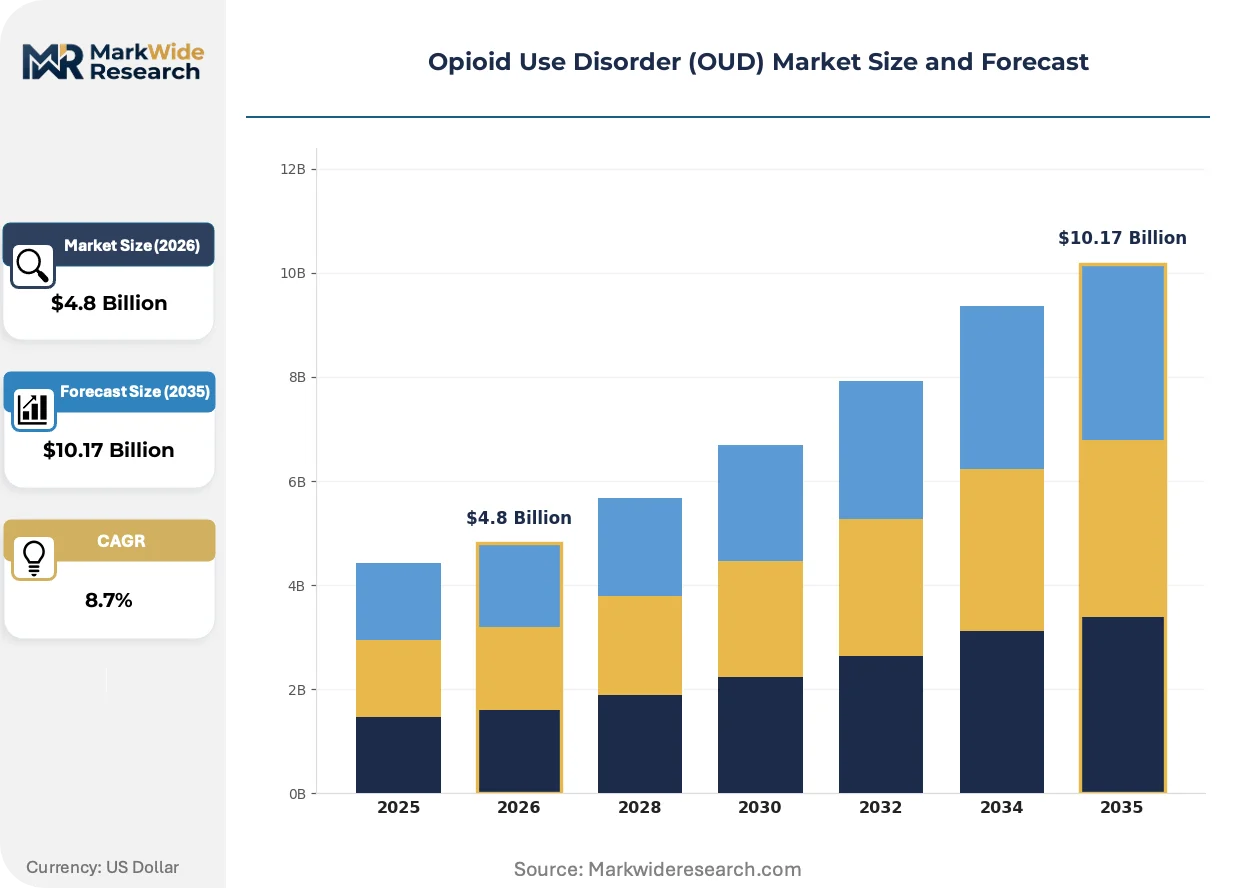
| Market Size in 2026 | $4.8 Billion |
| Market Size in 2035 | $10.17 Billion |
| CAGR (2026 – 2036) | 8.7% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Treatment Type: Medication-Assisted Treatment, Behavioral Therapy, Counseling, Detoxification Care Setting: Inpatient, Outpatient, Residential Treatment, Telehealth Patient Category: Adults, Adolescents, Pregnant Women, Elderly Drug Type: Buprenorphine, Methadone, Naltrexone, Others |
| Companies Covered | Indivior PLC, Alkermes, Orexo AB, Teva Pharmaceutical Industries, Pfizer, Collegium Pharmaceutical, Titan Pharmaceuticals, Camurus AB, Hikma Pharmaceuticals PLC, Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Opioid Use Disorder (OUD) Market Emerging Trajectories
Pharmaceutical formulation science is compressing dosing frequency from daily to monthly intervals, while care delivery models migrate from centralized clinics toward distributed access points. These parallel shifts are redefining patient retention economics and competitive positioning.
Long-acting depot injections of buprenorphine are overtaking sublingual film and tablet formats in prescriber preference for stabilized patients. Addiction medicine clinics in Massachusetts and Washington State report 60% of maintenance-phase patients converting to monthly injectable regimens within 18 months of induction. This transition compresses pharmacy revenue per patient while expanding prescriber panel capacity and reducing diversion risk.
SAMHSA's block grant restructuring and the Consolidated Appropriations Act provisions are conditioning state funding flows on demonstrated treatment retention metrics rather than admission volume. State substance abuse agencies in Illinois and Georgia are rebidding provider contracts around 90-day retention guarantees. This payment redesign favors organizations with integrated peer recovery support services and transportation assistance capabilities.
Employer-sponsored health plans are unbundling behavioral health carve-outs and reintegrating addiction treatment into medical benefit administration. Large self-insured employers in manufacturing and logistics sectors across Indiana, Wisconsin, and Tennessee now track OUD treatment as a workers' compensation cost containment lever. This demand-side pressure is accelerating network adequacy requirements and narrow-network contracting with high-retention specialty providers.
Opioid Use Disorder (OUD) Market Segmentation
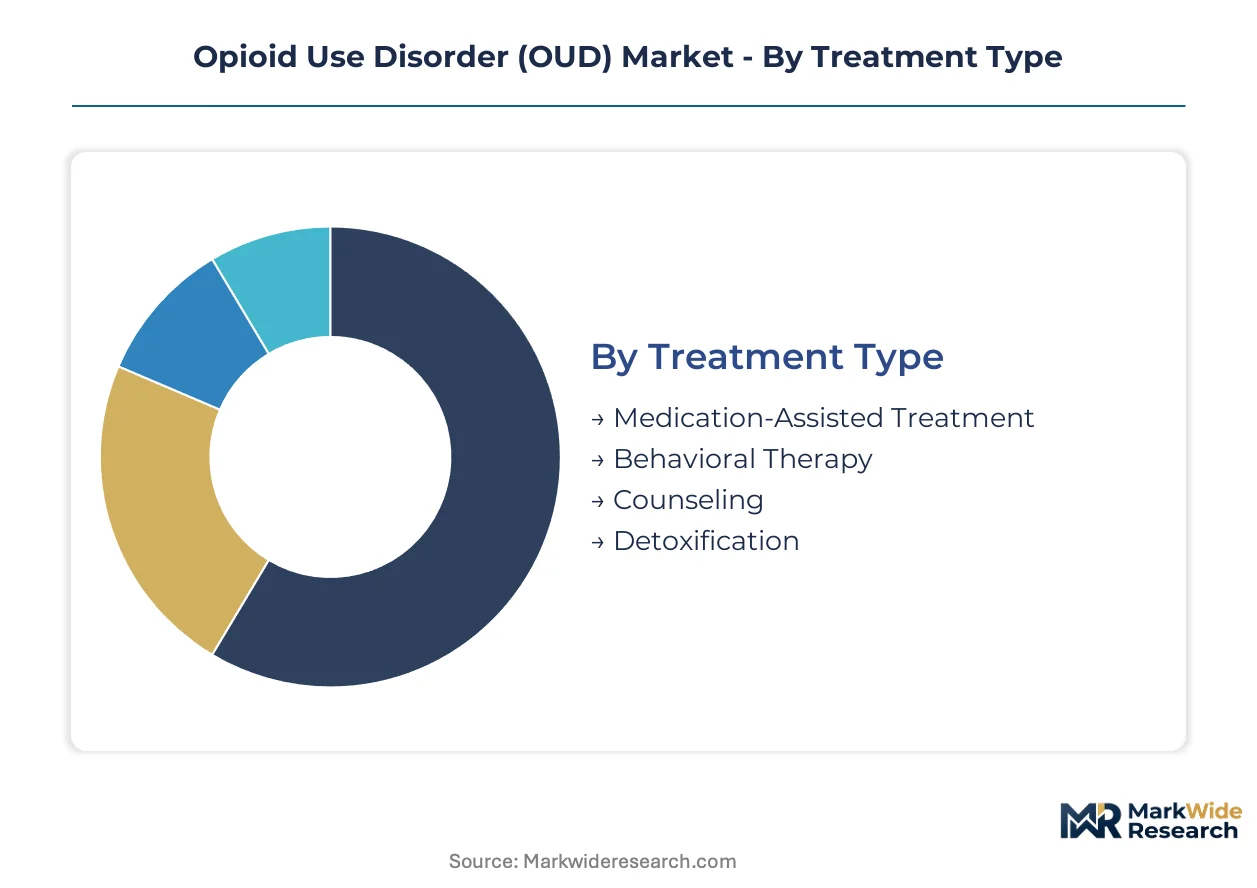
Treatment modality selection in OUD care determines reimbursement pathways, prescriber certification requirements, and patient retention economics. Segmentation reveals how clinical protocols fragment across care delivery infrastructure and population-specific regulatory frameworks.
Treatment Type:
Supply of certified clinicians and facility licensing capacity concentrates in medication-assisted protocols versus behavioral-only interventions.
- Medication-Assisted Treatment:Combines FDA-approved pharmacotherapies with behavioral support, requiring DEA-waived prescribers and REMS-compliant dispensing infrastructure. Demand concentrates in Federally Qualified Health Centers across Ohio and Kentucky where Medicaid reimbursement parity has eliminated prior authorization barriers for buprenorphine induction.
- Behavioral Therapy:Cognitive-behavioral and contingency management protocols delivered without pharmacologic components. Access bottlenecks persist in rural counties of Texas and Pennsylvania where licensed addiction counselors remain scarce relative to patient volume.
- Counseling:Individual and group psychotherapy sessions addressing psychosocial determinants of relapse.
- Detoxification:Medically supervised withdrawal management in acute care settings.
Medication-Assisted Treatment absorbs the bulk of installed capacity; Behavioral Therapy is expanding most quickly.
Care Setting:
Cost tier separation between high-intensity residential programs and distributed ambulatory models is redistributing patient flow.
- Telehealth:Remote induction and maintenance protocols validated during public health emergencies now embed permanently into clinical workflows. Massachusetts and Washington State report the steepest expansion trajectory as state Medicaid programs broaden reimbursement for video-based buprenorphine prescribing.
- Outpatient:Office-based addiction medicine and primary care integration. Demand concentrates in transportation-desert regions of Arizona and New Mexico where Federally Qualified Health Centers deploy mobile units to bridge access gaps.
- Inpatient:Acute medical stabilization and co-occurring disorder management in hospital settings.
- Residential Treatment:Structured 24-hour care in non-hospital therapeutic communities.
Outpatient settings dominate current patient volume; Telehealth is gaining share fastest.
Patient Category:
Volume concentration in adult populations contrasts with margin concentration in specialized perinatal and geriatric protocols.
- Adults:Working-age patients ages 18-64 constitute the primary treatment population. Access concentrates in metropolitan statistical areas of Illinois and Georgia where employer-sponsored plans now track OUD treatment as workers' compensation cost containment lever.
- Pregnant Women:Perinatal addiction medicine requiring obstetric-neonatal coordination and specialized buprenorphine dosing protocols. Demand is climbing fastest in Florida and Michigan where state Medicaid agencies condition provider contracts on demonstrated retention metrics for this population.
- Adolescents:Patients under 18 requiring family-based interventions and school coordination.
- Elderly:Patients over 65 with age-adjusted dosing and polypharmacy management needs.
Adults absorb the bulk of installed capacity; Pregnant Women is expanding most quickly.
Drug Type:
Application-specific pharmacology drives prescriber preference between agonist maintenance and antagonist relapse prevention.
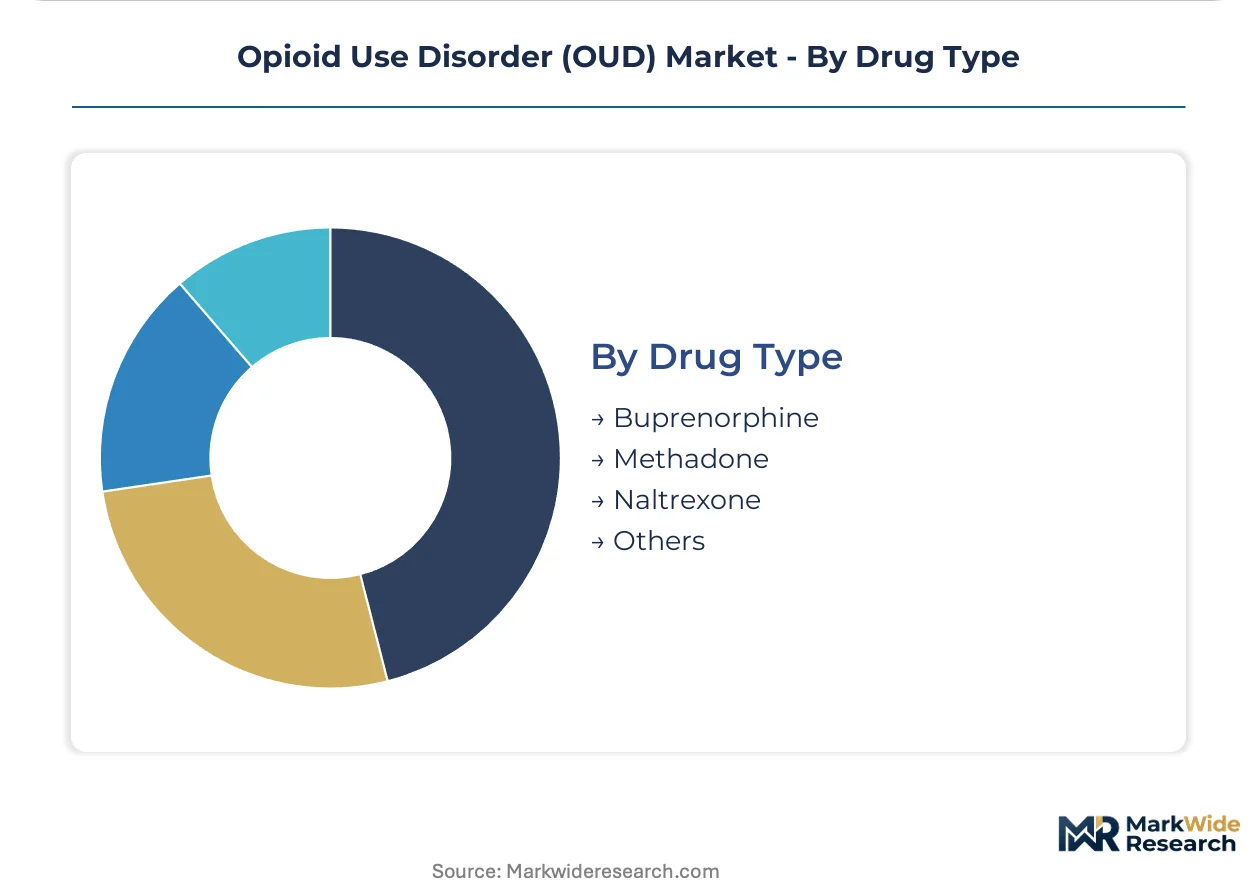
- Buprenorphine:Partial opioid agonist available in sublingual, buccal, and long-acting injectable formulations. Demand concentrates in correctional and reentry facilities across Texas, California, and Pennsylvania where extended-release depot injections anchor discharge protocols.
- Naltrexone:Opioid antagonist blocking euphoric effects, formulated as oral daily or monthly intramuscular injection. Uptake is climbing fastest in justice-involved populations where medication compliance can be monitored through mandatory reporting.
- Methadone:Full opioid agonist restricted to federally certified Opioid Treatment Programs with daily observed dosing.
- Others:Emerging formulations including combination products and novel delivery mechanisms.
Buprenorphine absorbs the bulk of installed capacity; Naltrexone is expanding most quickly.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Manufacturing of buprenorphine APIs concentrates in Indian and Turkish chemical clusters, while consumption and clinical deployment remain overwhelmingly concentrated in the United States. This production-consumption divide creates supply vulnerability and regulatory dependency that shapes market access dynamics.
United States
FDA's REMS framework governs buprenorphine distribution through certified prescribers, with DEA production quotas creating 12-18 month supply lags. Medicaid expansion under the ACA framework has eliminated prior authorization barriers in Ohio and Kentucky. Massachusetts and Washington State addiction medicine clinics report 60% of maintenance-phase patients converting to monthly injectable regimens.
Canada
Health Canada regulates buprenorphine-naloxone formulations under the Narcotic Control Regulations, with provincial formularies determining reimbursement access. British Columbia and Ontario have pioneered pharmacy-based induction protocols through collaborative practice agreements. Correctional health integration in federal penitentiaries creates institutional demand independent of outpatient volatility.
Germany
BfArM oversees opioid substitution therapy licensing, with statutory health insurance covering buprenorphine and methadone without prior authorization. Bavaria and North Rhine-Westphalia host the densest networks of certified substitution physicians. The country's harm reduction orientation supports long-acting depot formulations in prison health services.
United Kingdom
NICE guidelines recommend buprenorphine as first-line maintenance therapy, with NHS England commissioning frameworks shaping regional provider contracts. London and the Southeast concentrate specialist addiction psychiatry capacity. Scotland's national naloxone distribution program complements medication-assisted treatment infrastructure.
Australia
TGA registration determines PBS listing for buprenorphine products, with state-based opioid pharmacotherapy programs governing prescriber authorization. New South Wales and Victoria maintain the highest treatment penetration rates. The country's take-home naloxone program integrates with community pharmacy dispensing networks.
Opioid Use Disorder (OUD) Market Vendor Landscape
The competitive structure tilts toward formulation specialists with established REMS infrastructure and depot delivery capabilities. Market concentration remains moderate, with three to five firms capturing the majority of long-acting product revenue. Two strategic archetypes dominate: legacy opioid developers with addiction medicine portfolios, and specialty pharmaceutical firms focused exclusively on substance use disorder therapeutics. Competitive moves center on formulation lifecycle management and correctional health procurement contracting.
Within the specialty pharmaceutical tier, Indivior PLC, Alkermes, and Orexo AB occupy distinct positioning vectors. Indivior PLC represents the film and depot formulation specialist archetype, leveraging sublingual and extended-release platforms across diverse care settings. Alkermes exemplifies the long-acting injectable developer model, with its monthly naltrexone formulation anchoring institutional channels. Orexo AB occupies the abuse-deterrence innovation niche, differentiating through sublingual tablet technologies. These three firms collectively illustrate how formulation science specialization creates defensible market positions against generic competition.
| Leading Market Players |
|---|
| Indivior PLC |
| Alkermes |
| Orexo AB |
| Teva Pharmaceutical Industries |
| Pfizer |
| Collegium Pharmaceutical |
| Titan Pharmaceuticals |
| Camurus AB |
| Hikma Pharmaceuticals PLC |
| Others |
Supply Flow & Price Mechanics
Private-equity-rolled-up specialty pharmaceutical platforms dominate buprenorphine formulation supply, concentrating manufacturing assets in Indian API clusters and US finishing facilities while enforcing pricing discipline through DEA quota allocation and REMS certification barriers that limit competitive entry.
Pricing Analysis
Margin tightening in long-acting injectable tiers reflects Medicaid reimbursement compression and mandatory 340B pricing obligations at Federally Qualified Health Centers. Three-tier pricing structure across branded depot, authorized generic sublingual, and economy tablet formulations separates patients by insurance access and prescriber certification level. Cost-down pressure on sublingual film accelerates because Indivior's patent cliff exposes legacy products to accelerated generic erosion. Uninsured and cash-pay patients in transportation-desert regions exhibit highest price sensitivity, while correctional procurement offices with multi-year sole-source contracts show lowest sensitivity.
Supply Chain Analysis
Regional distribution centers in Indianapolis and Memphis anchor hub-and-spoke patterns for controlled substance distribution, with DEA-registered warehouses maintaining 21-day forward inventory against quota volatility. API synthesis draws from Indian and Turkish alkaloid extraction clusters, with buprenorphine base production concentrated in Hyderabad and Istanbul pharmaceutical corridors. Single-source vulnerability permeates the supply chain because Turkish export licensing delays transmit directly into US formulation shortages. Distribution runs through specialty pharmaceutical wholesalers with controlled substance licensing, bypassing traditional retail pharmacy networks for REMS-compliant products.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
DEA production quotas create hard supply ceilings that prop pricing power regardless of clinical demand expansion, making capacity access the defining competitive moat.
For Market Incumbents: Deploy REMS infrastructure leverage to secure preferred provider status with state departments of correction in Florida, Arizona, and Michigan before generic entrants achieve certification. Fortify position through backward integration into Indian API supply agreements that hedge Turkish export licensing risk. Anchor long-term adherence programs in correctional reentry channels where institutional procurement creates predictable demand volumes insulated from outpatient market volatility. For New Entrants and Emerging Players: Begin with pharmacy-based induction protocols in Idaho, New Mexico, and North Carolina where collaborative practice agreements bypass physician appointment scarcity. Capture patients at point of withdrawal crisis through 24-hour pharmacy access models that incumbent film manufacturers have neglected. Pursue digital therapeutics convergence with smartphone-based contingency management applications paired with pharmacotherapy, seeking FDA breakthrough device designation pathways for accelerated market entry. For Investors and Strategic Acquirers: Distressed-cycle entries favor specialty pharmaceutical firms with established REMS infrastructure and depot delivery capabilities in geographies with Medicaid expansion tailwinds. Monitor DEA quota allocation hearings as the critical inflection signal—quota expansion decisions determine whether supply ceilings lift to accommodate demand growth or hard constraints persist. Prioritize assets with correctional health procurement relationships that generate institutional revenue streams independent of outpatient reimbursement volatility.| Strategic Initiative | Industry Significance |
|---|---|
| REMS Infrastructure Expansion | DEA certification automation captures prescriber base before generic competition achieves compliance parity. |
| Long-Acting Injectable Scale-Up | Monthly depot formulations reduce diversion risk and align with Massachusetts and Washington State clinic conversion trends. |
| Correctional Health Procurement Contracting | Texas, California, and Pennsylvania discharge protocols create predictable multi-year demand volumes. |
| Indian API Supply Agreement | Hyderabad manufacturing partnerships hedge Turkish export licensing delays that transmit into US shortages. |
| Digital Therapeutics Integration | FDA breakthrough device designation pathways accelerate market entry for adherence-monitoring software. |
Methodological Framework
Multi-period observation of DEA quota allocations, REMS certification flows, and Medicaid reimbursement parity implementation anchored the trend analysis, supplemented by interviews with addiction medicine specialists, state Medicaid formulary directors, DEA-registered pharmacy operators, and correctional health procurement officers. Secondary validation drew from FDA REMS assessment documents, SAMHSA block grant expenditure reports, state substance abuse agency contract rebidding records, and CMS Medicare/Medicaid utilization data. Bottom-up patient flow modeling across care settings triangulated against top-down manufacturer shipment data reported under DEA ARCOS.
Input-output matrices structured the analytical framework across treatment modality, care setting, patient population, drug formulation, and regional regulatory cluster dimensions throughout the forecast period. CAGRs were derived from segmented demand build-ups incorporating prescriber waiver expansion trajectories, telehealth reimbursement permanence assumptions, and correctional health integration penetration curves. Forecast inputs included DEA production quota hearing schedules, state Medicaid expansion enrollment projections, and SAMHSA block grant restructuring provisions conditioning funding on retention metrics.
Underlying measurement precision varies by segment; telehealth and long-acting injectable categories carry tighter precision than behavioral-only therapy due to clearer reimbursement coding and manufacturer shipment reporting. Forecasts reflect documented assumptions regarding DEA regulatory posture, Medicaid parity enforcement, and API supply chain stability. Decision-makers should treat outputs as directional within the stated assumption set.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Addiction Treatment
US Ketamine Clinics Market
Addiction Treatment
Alcohol Use Disorder Treatment Market
Addiction Treatment
Nicotine De-Addiction Products Market
Addiction Treatment
Opioid Use Disorder Treatment Market
Addiction Treatment
Drug Free Depression Treatment Market
Addiction Treatment
Substance Abuse Treatment Market
Addiction Treatment
Methadone Market
Addiction Treatment
Smokeless Tobacco Treatment Market
Addiction Treatment
Global Substance Use Disorder Treatment Market
Addiction Treatment
US Mental Health and Addiction Treatment Centers Market
Addiction Treatment
Cocaine Intoxication Treatment Market
Addiction Treatment
Opioid Induced Constipation Treatment Market
Addiction Treatment
Opioid Withdrawal Treatment Market
Addiction Treatment
Global Addiction Treatment Market