
 Micro-Hospitals Market | 2026-2036
Micro-Hospitals Market Size, Share, and Industry Trends Forecast 2026-2036
Micro-Hospitals Market Outlook
Buyer fragmentation across suburban municipalities and employer coalitions is repositioning procurement patterns for micro-hospital developers. Emerus Holdings leverages joint-venture partnerships with regional health systems to scale its standardized facility model. SCL Health anchors its presence across Colorado's Front Range with vertically integrated emergency and surgical capabilities. Nutex Health competes through physician ownership structures that align operator incentives with utilization targets.
Micro-hospitals are compact acute-care facilities typically housing 8-50 licensed beds, equipped with emergency departments, operating rooms, and diagnostic imaging suites on footprints under 100,000 square feet, designed to deliver hospital-level services in underserved submarkets without the capital burden of full-scale medical centers. Inpatient care and emergency services segments dominate current revenue pools as these core offerings justify 24/7 staffing and licensure. Telemedicine integration within the technology segment is expanding fastest as remote specialist coverage enables broader service menus without on-site subspecialty labor.
FDA oversight of point-of-care diagnostic devices and CMS conditions of participation for hospital licensure shape facility design and equipment selection across US markets. State-level certificate-of-need programs and CON exemptions in Texas and Florida directly determine where micro-hospitals achieve regulatory approval for emergency departments and inpatient beds. Stakeholders must monitor how site-neutral payment rule evolution and state Medicaid managed-care contracting affect the profitability of low-acuity inpatient admissions versus shifted outpatient volumes.
Market Dynamics
CMS site-neutral payment policies are compressing reimbursement differentials between micro-hospitals and full-scale medical centers, forcing capital deployment toward lower-acuity inpatient models that preserve margin on standardized DRG codes.
Growth Catalysts
- Certificate-of-need exemptions:Texas and Florida state frameworks bypass traditional CON barriers for emergency departments under 50 beds, accelerating facility permitting timelines.
- Ambulatory surgery migration:Orthopedic and gastrointestinal procedures are shifting from inpatient stays to 23-hour observation models suited to micro-hospital footprints.
- Telemedicine infrastructure:Remote specialist coverage enables 24/7 neurology and cardiology consults without on-site subspecialty labor costs.
Market Restraints
- Construction cost escalation:Medical-grade HVAC and imaging suite buildouts require specialized contractors concentrated in Dallas-Fort Worth and Denver metropolitan areas.
- CMS conditions of participation:Hospital licensure mandates 24/7 emergency physician staffing, creating fixed labor costs that strain sub-20-bed facilities.
- Full-service hospital substitution:Health systems in saturated markets steer commercially insured patients toward flagship campuses with broader subspecialty depth.
Strategic Opportunities
- Employer coalition contracting:Self-insured municipal and corporate purchasers in Colorado's Front Range are negotiating direct-to-facility pricing for urgent and surgical episodes.
- Medicaid managed-care carve-outs:State contracting reforms in Texas create capitated payment pools for low-acuity inpatient admissions in underserved counties.
- Point-of-care diagnostics convergence:FDA-cleared portable CT and laboratory analyzers compress diagnostic turnaround times without centralized lab dependency.
Industry Challenges
- Emergency medicine staffing pipelines:Rural and suburban markets face acute shortages of board-certified emergency physicians willing to staff overnight rotations.
- EHR integration complexity:Micro-hospital operators must reconcile proprietary patient records with parent health system Epic or Cerner deployments.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Micro-Hospitals Market |
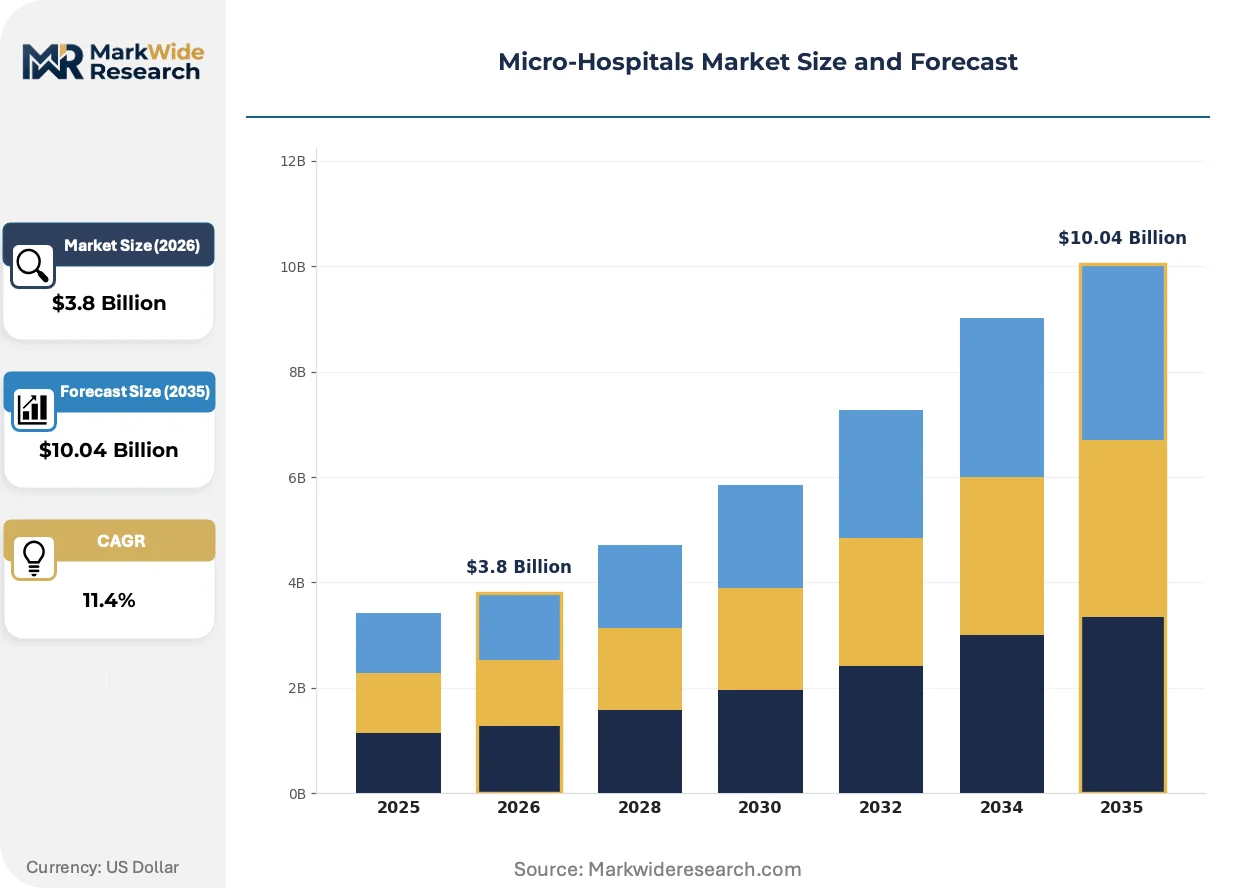
| Market Size in 2026 | $3.8 Billion |
| Market Size in 2035 | $10.04 Billion |
| CAGR (2026 – 2036) | 11.4% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Facility Type: Urgent Care Centers, Community Clinics, Specialty Clinics, Walk-in Clinics Service Type: Inpatient Care, Outpatient Services, Emergency Care, Surgical Services Technology: Telemedicine, Electronic Health Records, Diagnostic Imaging, Patient Monitoring Systems End User: Patients, Insurers, Healthcare Providers, Employers |
| Companies Covered | SCL Health, Baptist Health System, Emerus Holdings, Allegheny Health Network, Nutex Health, Dignity Health, Christus Health, WellSpan Health, Baylor Scott & White, Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Micro-Hospitals Market Strategic Shifts
Facility design and care delivery models are converging around standardization, remote connectivity, and payer-driven site selection that favors suburban accessibility over downtown medical district density.
Telemedicine-enabled specialist coverage is expanding into emergency and perioperative settings as the dominant connectivity layer for micro-hospital operations. Regional health systems in Texas and Colorado are deploying teleradiology and teleneurology platforms across multiple compact facilities simultaneously. This technology compression is expanding into markets previously deemed too small for subspecialty service menus, redefining catchment area economics.
FDA oversight of point-of-care diagnostic devices is tightening premarket review pathways for AI-augmented imaging systems deployed in low-acuity settings. Device manufacturers must now demonstrate equivalence to centralized laboratory accuracy standards for portable analyzers. Emergency departments with high Medicaid payer mixes face the steepest compliance burden as they adopt rapid diagnostic protocols for chest pain and stroke triage.
Suburban municipalities and employer coalitions are consolidating procurement authority through direct facility contracting that bypasses traditional health system networks. Municipalities in Florida's I-4 corridor negotiate bundled rates for emergency and surgical episodes with single-facility operators. This purchasing consolidation is most visible in markets where commercial insurance penetration exceeds 65 percent and deductible exposure drives price-sensitive site selection.
Micro-Hospitals Market Segmentation
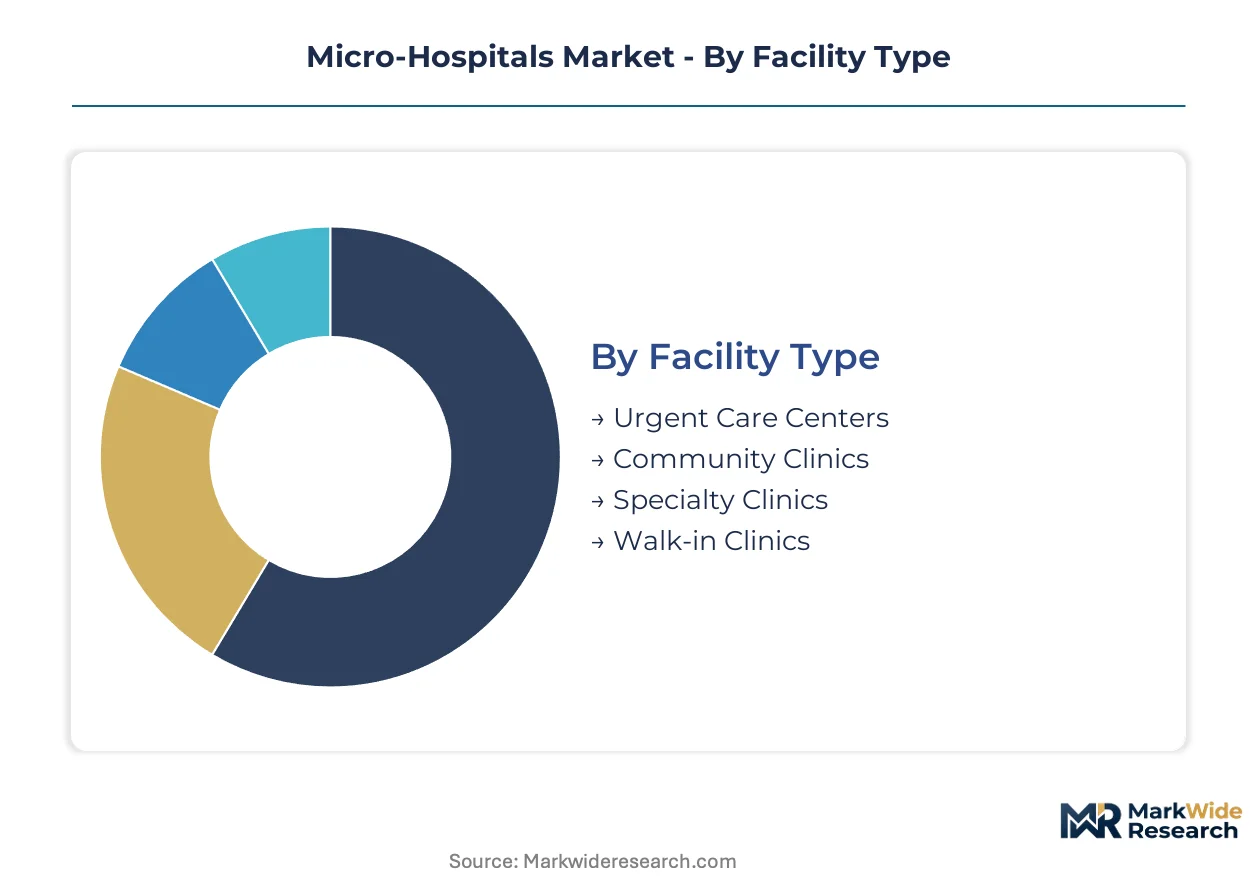
Micro-hospitals occupy a unique position between ambulatory centers and full-service hospitals, requiring precise segmentation to capture how facility configuration, service mix, and technology integration determine capital efficiency and reimbursement capture.
Facility Type:
Facility replacement cycles accelerate as health systems retire aging outpatient assets and redeploy capital toward standardized micro-hospital footprints with embedded emergency capabilities.
- Urgent Care Centers:These 8-12 bed facilities combine extended-hour urgent care with limited observation beds, capturing suburban demand for unscheduled acute episodes without full emergency department licensure. Texas health systems deploy this format in Dallas-Fort Worth exurbs where CON exemptions apply to sub-50-bed emergency operations.
- Community Clinics:Larger 20-35 bed configurations integrate primary care, imaging, and 23-hour surgical observation under single licensure. Colorado's Front Range health systems anchor these facilities in municipalities with 65,000-150,000 population and limited hospital competition.
- Specialty Clinics:Procedure-focused footprints concentrate orthopedic or cardiovascular services with dedicated operating suites and same-day discharge protocols.
- Walk-in Clinics:Minimal-bed formats emphasize rapid diagnostic triage with telemedicine backstop for specialist consultation.
Community Clinics sits at the top of the volume ranking, with Urgent Care Centers climbing the fastest.
Service Type:
Service line economics vary sharply by payer mix and acuity threshold, with margin compression on standardized DRG codes forcing selective procedure migration.
- Inpatient Care:Licensed bed utilization concentrates on medical observation and short-stay surgical admissions requiring overnight monitoring. Florida systems face CMS site-neutral payment compression on these admissions, pushing operators toward higher-acuity patient selection within micro-hospital constraints.
- Emergency Care:24/7 emergency department operations justify facility licensure and attract commercially insured volume through ambulance diversion agreements. Staffing costs dominate economics as rural markets compete for board-certified emergency physicians.
- Outpatient Services:Scheduled diagnostic and therapeutic encounters fill daytime capacity and cross-subsidize overnight fixed costs.
- Surgical Services:Orthopedic and gastrointestinal procedures shift from inpatient to 23-hour observation models suited to compact footprints.
Emergency Care commands the highest revenue per encounter, though Surgical Services demonstrates the steepest expansion trajectory as ambulatory migration accelerates.
Technology:
Technology deployment patterns reflect a cost-tier structure where premium connectivity investments enable service menu expansion without proportional labor increases.
- Telemedicine:Remote specialist coverage platforms enable 24/7 neurology, cardiology, and critical care consultation across multiple facilities from centralized hubs. Texas health systems achieve subspecialty coverage in markets previously deemed too small for on-site staffing.
- Diagnostic Imaging:Portable CT and point-of-care ultrasound systems compress turnaround times for chest pain and stroke protocols. FDA premarket review pathways for AI-augmented imaging tighten compliance burdens on high-Medicaid facilities.
- Electronic Health Records:Epic and Cerner integration requirements create implementation complexity for joint-venture micro-hospitals reconciling proprietary records with parent system architectures.
- Patient Monitoring Systems:Continuous telemetry and automated early-warning scoring reduce nursing intensity for observation-bed populations.
Telemedicine claims the largest share of new capital allocation, while Diagnostic Imaging delivers the fastest payback on throughput metrics.
End User:
Customer concentration patterns reveal procurement authority consolidation among purchasers with direct financial exposure to site-of-care pricing differentials.
- Healthcare Providers:Regional health systems and physician-owned operators drive facility development through joint-venture structures and certificate-of-need applications. Emerus Holdings scales through standardized partnership templates with not-for-profit systems.
- Employers:Self-insured municipal and corporate purchasers in Colorado and Florida negotiate direct-to-facility bundled rates for urgent and surgical episodes, bypassing traditional network intermediaries.
- Patients:High-deductible plan beneficiaries exercise price-sensitive site selection for scheduled procedures.
- Insurers:Medicaid managed-care plans and commercial carriers influence site selection through narrow network design and prior authorization requirements.
Healthcare Providers account for the dominant share of facility commissioning decisions, though Employer direct contracting is gaining share fastest in commercially concentrated markets.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Emergency medicine physician concentration in Texas and Colorado anchors facility development patterns for micro-hospital operators. Rural and suburban health systems deploy compact inpatient models where board-certified staffing pools remain scarce.
United States
Texas health systems exploit certificate-of-need exemptions for emergency departments under 50 beds, accelerating permitting in Dallas-Fort Worth exurbs. CMS site-neutral payment policies compress reimbursement differentials between micro-hospitals and full-scale medical centers. Emerus Holdings scales joint-venture partnerships across Houston and San Antonio metropolitan clusters.
Florida
Commercial insurance penetration exceeding 65 percent in the I-4 corridor drives price-sensitive site selection for urgent and surgical episodes. State CON frameworks bypass traditional barriers for compact emergency facilities. Municipal coalitions negotiate direct-to-facility bundled rates with single-facility operators in Orlando and Tampa submarkets.
Colorado
SCL Health anchors vertically integrated emergency and surgical capabilities across the Front Range where population density supports 20-35 bed configurations. Self-insured municipal purchasers negotiate direct contracting for scheduled procedures. Denver-Aurora metropolitan expansion creates catchment area opportunities in previously underserved mountain corridor counties.
Germany
Hospital infrastructure modernization programs under the Hospital Future Act (KHZG) incentivize digitization of compact acute-care formats. EMA oversight of point-of-care diagnostic devices shapes equipment selection for rural emergency departments. Bavarian health networks pilot telemedicine-enabled specialist coverage in Alpine corridor communities with limited subspecialty access.
United Kingdom
NHS England site selection criteria favor community-based urgent treatment centers with embedded observation capacity. MHRA regulation of AI-augmented imaging systems tightens compliance for rapid diagnostic protocols. Greater Manchester and West Midlands health systems deploy compact facilities to reduce ambulance diversion from overstretched district general hospitals.
Micro-Hospitals Market Competitive Environment
Diversified conglomerates compete with focused pure-play specialists across the micro-hospitals landscape. Regional health systems with broad geographic footprints anchor joint-venture structures, while physician-owned operators concentrate ownership incentives around utilization targets. Three archetypes dominate: standardized facility developers, vertically integrated health system affiliates, and specialty-procedure focused ventures. Strategic moves center on partnership templating for rapid facility rollout and direct employer contracting that bypasses traditional network intermediaries.
Among US-based operators, Emerus Holdings exemplifies the standardized partnership model through joint-venture templates with not-for-profit health systems. SCL Health anchors the vertically integrated archetype across Colorado's Front Range with embedded emergency and surgical capabilities. Nutex Health occupies the physician-ownership tier, aligning operator incentives with targeted utilization patterns.
| Leading Market Players |
|---|
| SCL Health |
| Baptist Health System |
| Emerus Holdings |
| Allegheny Health Network |
| Nutex Health |
| Dignity Health |
| Christus Health |
| WellSpan Health |
| Baylor Scott & White |
| Others |
Value Chain & Pricing Dynamics
Board-certified emergency physician concentration in Dallas-Fort Worth and Denver metropolitan areas creates labor-cost differentials that widen pricing-tier spreads between premium-staffed community clinics and economy-tier urgent care formats.
Pricing Analysis
Bundled episode rates for emergency and surgical encounters compete against unbundled fee-for-service billing across payer contracts. Three-tier pricing structure across premium, standard, and economy levels separates physician-owned specialty clinics from health system joint ventures and municipal urgent care formats. Price differentiation hinges on emergency department licensure status and telemedicine-enabled subspecialty coverage depth. Pricing pressure stems from CMS site-neutral payment compression on low-acuity inpatient admissions. Self-insured employer coalitions in Colorado and Florida exhibit highest price sensitivity, while commercially insured patients with high deductibles drive site selection based on transparency tools.
Supply Chain Analysis
Domestic-content mandates for medical-grade HVAC and imaging suite components under Buy America provisions reshape sourcing toward US-based specialized contractors concentrated in Texas, Colorado, and Florida. Medical imaging equipment draws from German and Japanese OEM supply chains, while point-of-care diagnostic analyzers source from US and South Korean manufacturers. Supply chain risk centers on single-source vulnerability for AI-augmented imaging systems awaiting FDA premarket clearance. Distribution runs through regional health system procurement consortia and GPO contracts that aggregate demand across multiple micro-hospital joint ventures.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Micro-hospitals function as stable compounders where ambulatory surgery migration and CON exemption policies generate predictable facility deployment cycles across suburban markets.
For Market Incumbents: Lock in emergency medicine staffing pipelines through multi-year contracts with regional physician groups before rural shortages intensify. Deepen backward integration into telemedicine infrastructure to reduce per-facility specialist coverage costs. Consolidate catchment area dominance by preempting competitor CON applications in Texas and Florida exurbs. For New Entrants and Emerging Players: Self-insured municipal coalitions in Colorado's mountain corridor counties represent the most penetrable buyer archetype for direct-to-facility contracting. Target 8-12 bed urgent care formats in Texas CON-exempt zones where health systems lack presence. Pursue joint-venture structures with not-for-profit systems seeking capital-light expansion rather than greenfield development. For Investors and Strategic Acquirers: Regional health systems with vertically integrated service lines are the most active acquirer in this space, seeking standardized facility platforms for rapid geographic fill-in. Acquisition target archetypes include physician-owned operators with established CON approvals and emergency department licenses. Watch Medicaid managed-care carve-out policy announcements in Texas as the signal for inflection in low-acuity admission profitability.| Strategic Initiative | Industry Significance |
|---|---|
| Certificate-of-Need Preemption | Early CON application filing in Texas and Florida secures exclusive emergency service territories before competitors mobilize. |
| Telemedicine Infrastructure Deployment | Teleradiology and teleneurology platforms enable subspecialty coverage in markets below on-site staffing thresholds. |
| Employer Direct Contracting | Bundled rate negotiations with self-insured municipal coalitions bypass traditional network intermediaries in Colorado. |
| Physician Ownership Restructuring | Alignment of operator incentives with utilization targets through joint-venture equity participation improves capital efficiency. |
| Point-of-Care Diagnostic Integration | FDA-cleared portable CT and laboratory analyzers reduce turnaround times without centralized lab dependency. |
Study Parameters
Bottom-up facility deployment modeling reconciled against top-down health system capital expenditure tracking forms the analytical core of this study. Primary interviews with micro-hospital operators, emergency medicine staffing agencies, state CON review board administrators, and GPO contract managers combined with secondary validation against CMS Medicare cost reports, state health facility licensing databases, and hospital procurement consortium filings. Triangulation across these sources anchors volume and value estimates.
Input-output matrices map licensed bed capacity, emergency department visit volumes, and surgical procedure migration patterns across facility type and service line segments over the projection horizon. Segmentation dimensions include facility configuration tier, payer mix concentration, technology integration depth, and geographic regulatory cluster. CAGRs derive from facility replacement cycle analysis and health system joint-venture announcement tracking. Forecast inputs incorporate CMS site-neutral payment rule evolution and state Medicaid managed-care contracting reforms.
Underlying measurement precision varies by segment; emergency care and surgical service lines carry tighter precision than telemedicine technology adoption curves. Forecasts reflect assumptions regarding CON exemption policy continuity and emergency physician supply stability. Regulatory reversal on site-neutral payments or sudden staffing pipeline constriction could revise deployment trajectories. Within these boundaries, the analytical envelope holds.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Healthcare Facilities
US Skilled Nursing Facility and Rehabilitation Market
Healthcare Facilities
US Skilled Nursing Facility Market
Healthcare Facilities
Private Office-Based Clinics Market
Healthcare Facilities
Qatar Senior Living Market
Healthcare Facilities
Assisted Living Facilities Market
Healthcare Facilities
Trauma Care Centers Market
Healthcare Facilities
Confinement Center Market
Healthcare Facilities
Ambulatory Surgical Centers Market
Healthcare Facilities
Asia-Pacific Smart Hospital Market
Healthcare Facilities
US and Europe Ambulatory Surgery Centers Market
Healthcare Facilities
US Assisted Living Facility Market
Healthcare Facilities
Hospital Lighting Market
Healthcare Facilities
Mobile Hospitals Market
Healthcare Facilities
Longevity Clinic Chain Infrastructure Market
Healthcare Facilities
US Ambulatory Surgery Centers Market
Healthcare Facilities
Global Healthcare Architecture Market