
 Medically Supervised Weight Loss Services Market | 2026-2036
Medically Supervised Weight Loss Services Market Size, Share, and Industry Trends Forecast 2026-2036
Medically Supervised Weight Loss Services Market Foresight
Subscription-based membership models and third-party leasing of clinical space are reshaping capital deployment for new entrants in medically supervised weight loss. Cleveland Clinic leverages its integrated health system architecture to anchor comprehensive metabolic programs across multiple states. Medi-Weightloss specializes in franchise-operated clinic networks that extend branded protocols without direct facility ownership. NYU Langone Hospitals competes through academic medical center credibility and embedded bariatric surgery referral pathways.
Medically supervised weight loss services constitute physician-directed programs combining caloric restriction, behavioral modification, pharmacotherapy, and exercise prescription under clinical monitoring with defined outcome metrics. These programs operate through structured protocols requiring baseline metabolic assessment, periodic biomarker tracking, and multidisciplinary care team coordination to reduce obesity-related comorbidity burden. Pharmaceutical interventions command premium positioning within service type segmentation due to drug cost pass-through and specialized prescriber requirements. Telehealth delivery mode exhibits the fastest structural expansion as asynchronous monitoring and virtual coaching reduce per-patient labor intensity while maintaining reimbursement eligibility. End user segmentation tilts toward hospitals and clinics capturing insurance-contracted volume, while private practices navigate direct-pay and cash-based models.
FDA oversight of anti-obesity medications and CMS reimbursement determinations for intensive behavioral therapy shape program design and patient access thresholds in the United States. State-level scope-of-practice regulations for nurse practitioners and dietitians further constrain or enable service scaling depending on jurisdiction. OSHA workplace wellness incentives and evolving HIPAA guidance on digital health data portability add compliance dimensions to platform architecture. Stakeholders must monitor formulary tier placement for GLP-1 agents and state Medicaid expansion decisions as these directly alter addressable patient populations and program economics.
Market Dynamics
GLP-1 receptor agonist coverage expansion through employer-sponsored health plans is restructuring patient access economics and forcing clinic operators to redesign staffing models around pharmaceutical protocol management.
Growth Catalysts
- Intensive Behavioral Therapy Reimbursement:CMS coverage determinations for obesity counseling sessions expand addressable patient pools in Medicare-contracted clinics.
- Telehealth Asynchronous Monitoring:Virtual coaching platforms reduce per-patient labor intensity while maintaining HIPAA-compliant reimbursement eligibility across state lines.
- Employer Wellness Incentive Structures:OSHA-aligned workplace wellness programs embed obesity management as a covered benefit, driving volume into supervised programs.
Market Restraints
- GLP-1 Drug Cost Pass-Through:Pharmaceutical acquisition costs consume 60-70% of program revenue, compressing clinic margin structures.
- State Scope-of-Practice Fragmentation:Nurse practitioner prescribing authority varies by jurisdiction, constraining service scaling in restrictive states.
- Medicaid Formulary Tier Placement:State-level coverage decisions for anti-obesity medications create patchwork access that limits patient acquisition in lower-income demographics.
Strategic Opportunities
- Third-Party Clinical Space Leasing:Asset-light franchise models reduce capital deployment requirements for geographic expansion.
- Integrated Health System Partnerships:Academic medical center credibility anchors metabolic program referral pathways and bariatric surgery pipelines.
- FDA Accelerated Approval Pathway:Streamlined pharmaceutical intervention options enable rapid protocol updates and competitive differentiation.
Industry Challenges
- Multidisciplinary Care Team Coordination:Recruiting credentialed dietitians and exercise physiologists strains labor markets in competitive geographies.
- Digital Health Data Portability Compliance:Evolving HIPAA guidance on platform architecture requires continuous infrastructure investment.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Medically Supervised Weight Loss Services Market |
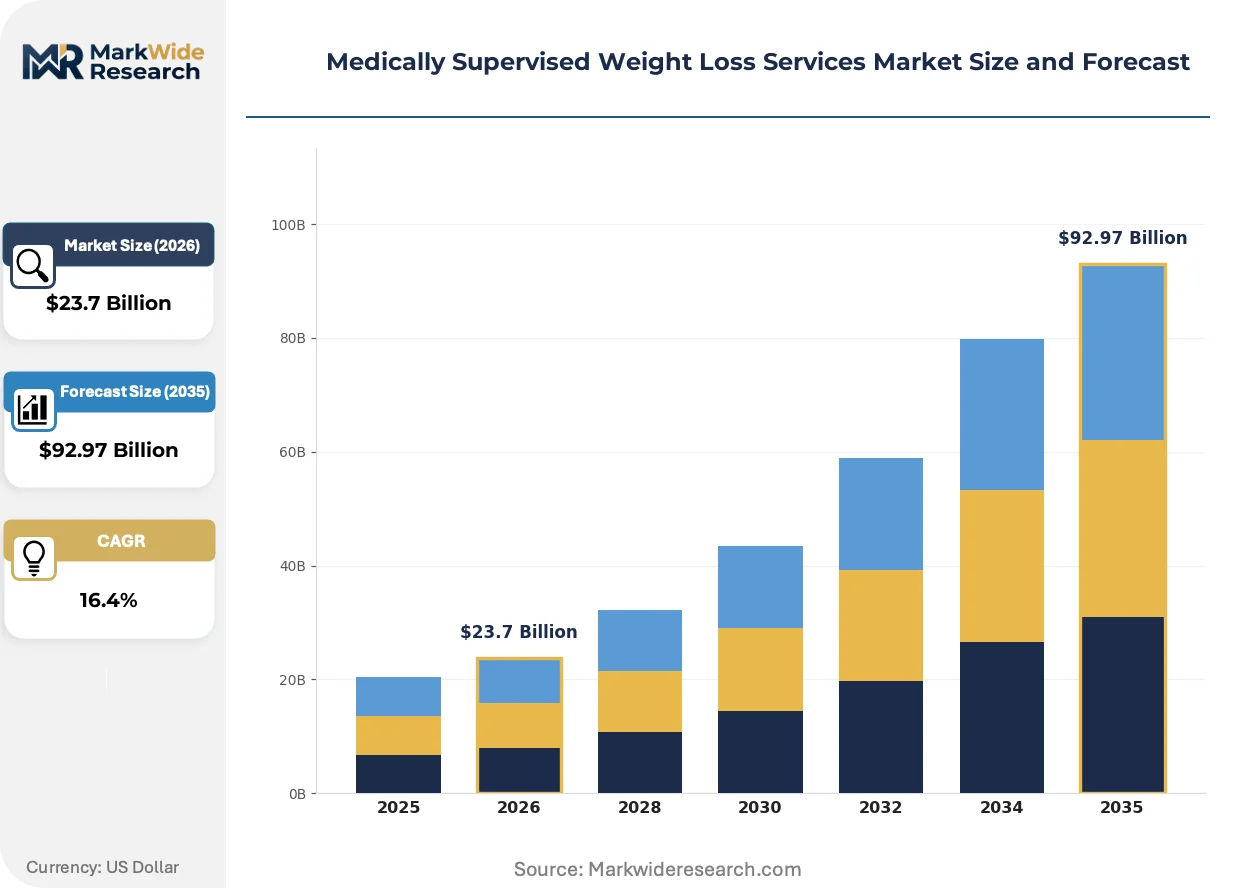
| Market Size in 2026 | $23.7 Billion |
| Market Size in 2035 | $92.97 Billion |
| CAGR (2026 – 2036) | 16.4% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: Nutrition Counseling, Behavioral Therapy, Pharmaceutical Interventions, Physical Activity Coaching Delivery Mode: In-Person Sessions, Telehealth, Group Classes, Online Programs End User: Clinics, Hospitals, Private Practices, Wellness Centers Program Duration: Short-Term Plans, Long-Term Programs, Maintenance Plans, Intensive Weekends |
| Companies Covered | Cleveland Clinic, Duke Diet & Fitness Center, Cooper Clinic, Medical Weight Loss Clinic, Medi-Weightloss, UCLA Health, NYU Langone Hospitals, Geisinger Medical Center, Scripps Clinic, Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Medically Supervised Weight Loss Services Market Shifts & Advancements
Technology convergence and reimbursement model evolution are compressing traditional clinic economics while elevating platform-enabled delivery architectures. Three developments are restructuring competitive positioning.
Continuous glucose monitoring integration with mobile coaching applications is hybridizing metabolic assessment protocols. Integrated health systems deploy these combined sensor-software stacks to reduce in-person visit frequency. The technology is hybridizing asynchronous care models with synchronous clinical oversight, collapsing traditional visit-based revenue structures.
FDA oversight of compounded semaglutide products is tightening quality assurance requirements for clinic-affiliated pharmacies. The agency's enforcement actions against unapproved manufacturing facilities are redirecting patient volume toward branded pharmaceutical channels. Hospital-based programs with established formulary relationships capture displaced demand from compounding-dependent competitors.
Direct-pay membership models are displacing insurance-contracted volume in private practice settings. Patients seeking expedited access to GLP-1 prescriptions bypass prior authorization delays through cash-based arrangements. This behavioral shift concentrates in metropolitan markets with high deductible health plan penetration and limited in-network supervised program availability.
Medically Supervised Weight Loss Services Market Segmentation
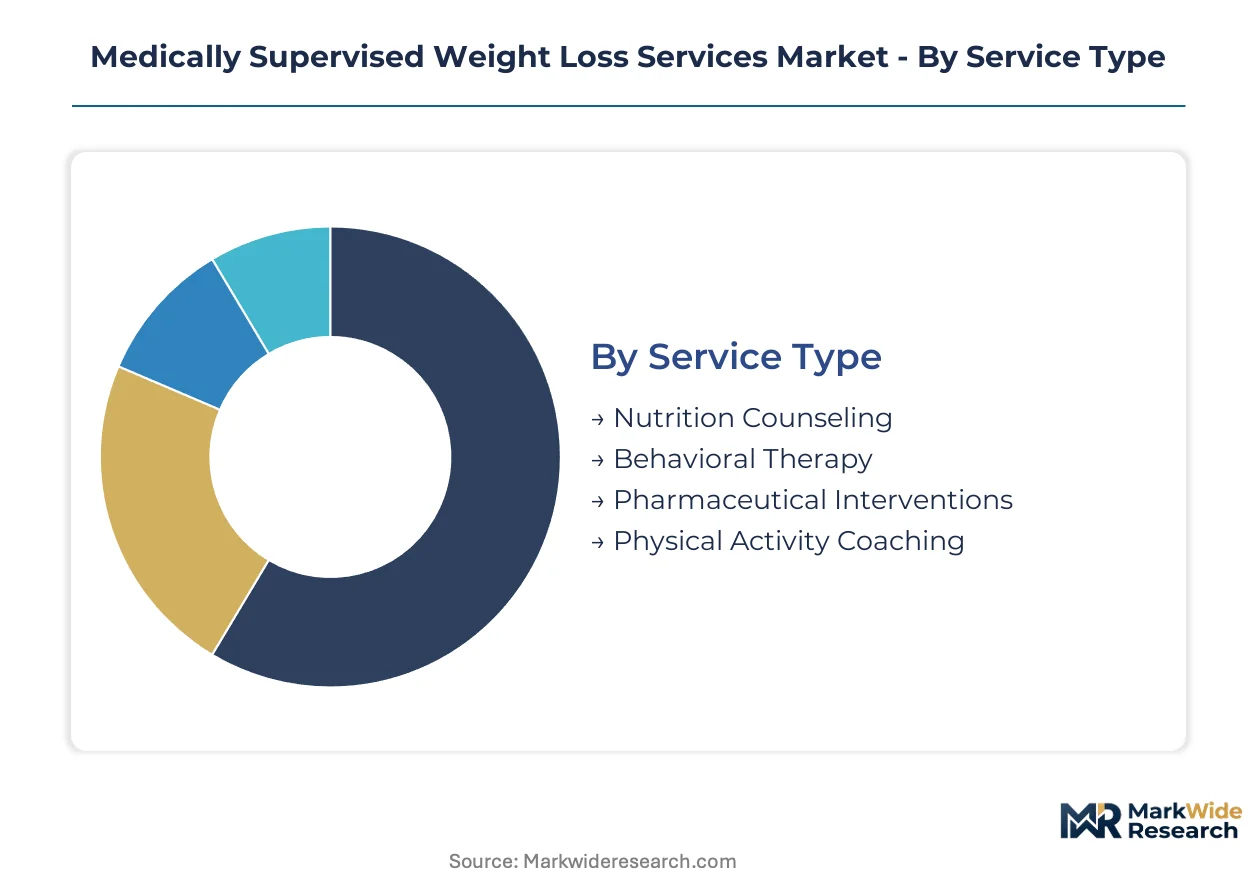
Service differentiation across medically supervised weight loss programs determines reimbursement eligibility, patient acquisition costs, and clinical staffing requirements. Segment boundaries increasingly blur as hybrid delivery models combine pharmaceutical protocols with digital monitoring platforms.
Service Type:
Cost tier stratification separates physician-directed interventions from allied health professional services, with reimbursement rates scaling to prescriber credential requirements.
- Pharmaceutical Interventions:GLP-1 receptor agonist protocols require specialized prescriber licensing and drug cost pass-through arrangements. Demand concentrates in hospital-based programs across the United States where integrated formularies negotiate favorable tier placement with commercial payers facing employer wellness mandate pressure.
- Behavioral Therapy:Intensive lifestyle modification sessions follow CMS-structured protocols with defined visit frequency and outcome documentation standards. Medicare-contracted clinics in Florida and Arizona capture volume from aging demographics with obesity-related comorbidity burdens.
- Nutrition Counseling:Registered dietitian services anchor multidisciplinary care teams with state scope-of-practice variations affecting supervision requirements.
- Physical Activity Coaching:Exercise physiologist-led movement prescriptions complete metabolic program architectures with biometric tracking integration.
Pharmaceutical Interventions holds installed capacity. Behavioral Therapy is rotating up the share rankings.
Delivery Mode:
Patient volume distribution reflects reimbursement policy evolution and labor cost pressures reshaping clinical economics.
- Telehealth:Asynchronous monitoring platforms reduce per-patient labor intensity through automated biomarker tracking and AI-assisted coaching workflows. Private practices in Texas and California deploy these architectures to bypass geographic constraints on specialist availability.
- In-Person Sessions:Traditional clinic visits retain premium positioning for baseline metabolic assessment and pharmaceutical initiation requiring physical examination. Academic medical centers in New York and Massachusetts anchor high-touch protocols with embedded bariatric surgery referral pathways.
- Group Classes:Scaled behavioral interventions lower per-patient delivery costs while maintaining HIPAA-compliant outcome documentation.
- Online Programs:Self-directed digital curricula serve maintenance-phase patients with reduced clinical oversight requirements.
Telehealth is gaining share fastest. In-Person Sessions retains the highest average revenue per patient encounter.
End User:
Facility type determines payer mix, capital deployment requirements, and regulatory compliance architecture.
- Hospitals:Integrated health systems leverage existing infrastructure for metabolic program expansion with EHR-embedded referral workflows. Cleveland Clinic and NYU Langone anchor multi-state networks capturing employer-sponsored health plan volume.
- Clinics:Franchise-operated networks extend branded protocols without direct facility ownership. Medi-Weightloss deploys this model across suburban markets with high deductible health plan penetration.
- Private Practices:Direct-pay membership models bypass prior authorization delays for patients seeking expedited GLP-1 access.
- Wellness Centers:Corporate on-site programs embed obesity management within OSHA-aligned workplace wellness incentive structures.
Hospitals hold installed capacity. Clinics are rotating up the share rankings.
Program Duration:
Enrollment architecture shapes patient lifetime value and clinical resource allocation across intervention phases.
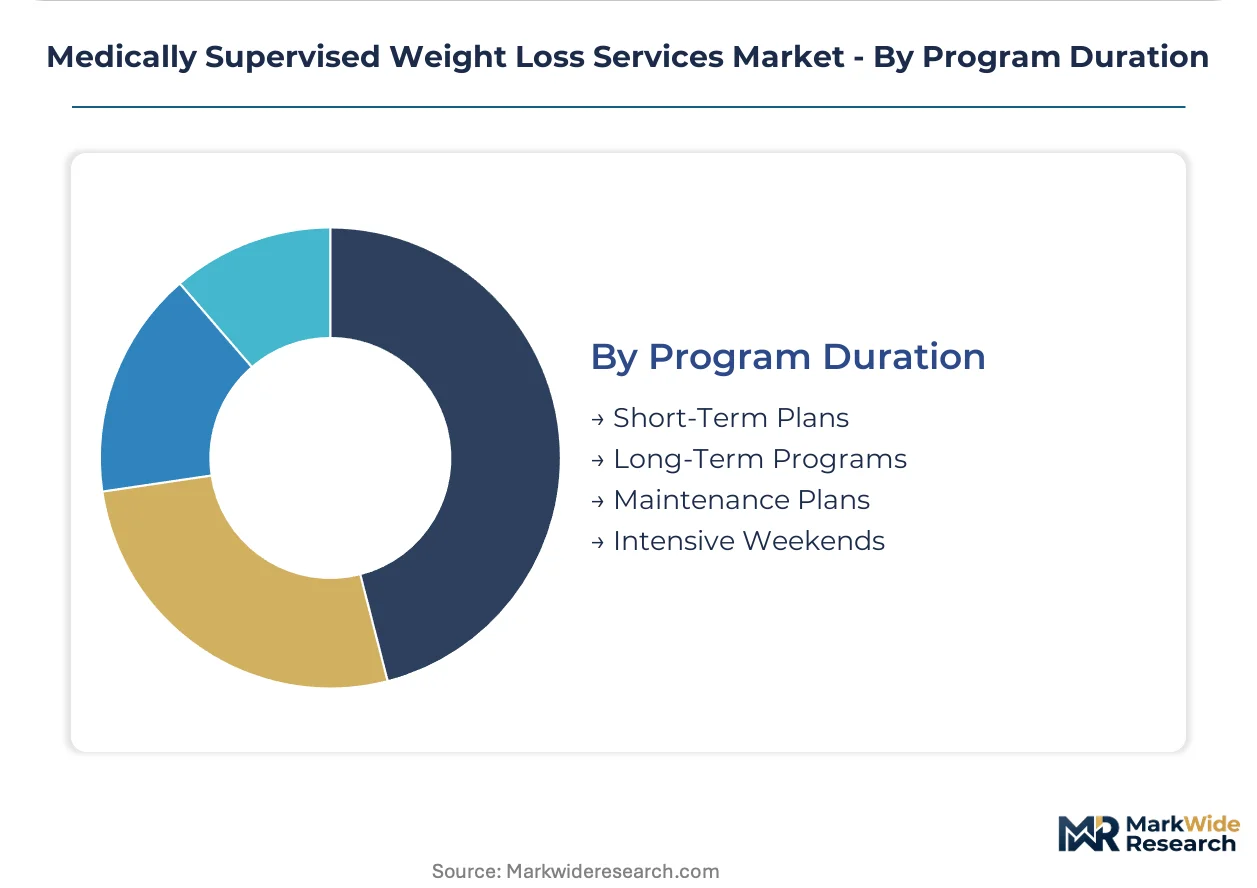
- Long-Term Programs:Sustained engagement models spanning 12-24 months address chronic disease management requirements with periodic biomarker reassessment. Demand concentrates in Medicare Advantage-contracted facilities serving populations with established obesity-related comorbidities.
- Maintenance Plans:Reduced-frequency monitoring preserves weight loss outcomes with lower per-patient service intensity. Telehealth platforms in Colorado and Washington deploy asynchronous coaching to sustain engagement at reduced labor cost.
- Short-Term Plans:Intensive initial intervention packages target pre-surgical weight loss requirements.
- Intensive Weekends:Condensed immersion protocols serve time-constrained professional demographics with premium direct-pay pricing.
Long-Term Programs hold installed capacity. Maintenance Plans are expanding most quickly.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Employer wellness mandate expansion and pharmaceutical reimbursement policy divergence are redrawing patient access maps across major economies. Integrated health systems in high-income markets capture volume through formulary negotiations, while emerging markets struggle with patchwork coverage for anti-obesity interventions.
United States
CMS coverage determinations for intensive behavioral therapy and GLP-1 formulary tier placement drive clinic network expansion. FDA accelerated approval pathways for semaglutide products enable rapid protocol updates in hospital-based programs. The Cleveland Clinic anchors multi-state metabolic networks across Ohio, Florida, and Nevada, capturing employer-sponsored plan volume through integrated EHR referral workflows.
Germany
EMA centralized marketing authorization for obesity pharmacotherapy streamlines cross-border protocol standardization. The country's statutory health insurance system covers medical nutrition therapy for BMI thresholds above defined limits, expanding addressable patient pools. Berlin and Munich host academic medical center clusters where university hospitals embed bariatric surgery pathways within supervised weight loss programs.
United Kingdom
NICE technology appraisals for liraglutide and semaglutide reshape National Health Service commissioning decisions for tiered weight management services. NHS England's Diabetes Prevention Programme expansion creates referral pipelines into clinically supervised interventions. London's academic health science centers compete for research trial volume while regional integrated care systems in Manchester and Birmingham scale community-based delivery models.
Japan
PMDA regulatory pathways for anti-obesity medications maintain stringent efficacy requirements that limit pharmaceutical intervention options within supervised programs. METI workplace wellness incentive structures embed metabolic health screening within mandatory annual health examinations. Tokyo and Osaka concentrate private clinic networks serving corporate health insurance subscribers with direct-pay arrangements for expedited specialist access.
Australia
TGA scheduling decisions for GLP-1 receptor agonists determine pharmaceutical availability through hospital formularies versus community pharmacy dispensing. Medicare Benefits Schedule item numbers for chronic disease management plans subsidize allied health professional services within multidisciplinary weight loss programs. Sydney and Melbourne anchor private practice clusters targeting high-deductible health plan subscribers with subscription-based membership models.
Medically Supervised Weight Loss Services Market Competitive Landscape
Channel-controlling players compete with product-specialist players across fragmented service delivery architectures. The market structures around three tiers: integrated health systems with captive referral networks, franchise-operated clinic chains with asset-light expansion models, and independent private practices with direct-pay positioning. Consolidation pressure concentrates among mid-scale clinic operators facing GLP-1 drug cost pass-through compression. Dominant competitive moves include third-party clinical space leasing partnerships and telehealth platform licensing to bypass geographic constraints on specialist availability.
Within the integrated health system tier, Cleveland Clinic and NYU Langone Hospitals anchor multi-state metabolic program networks. Cleveland Clinic exemplifies the academic medical center archetype with embedded bariatric surgery referral pathways and employer-contracted volume capture. NYU Langone occupies a position bridging research trial access with clinical service delivery across the Northeast corridor. Medi-Weightloss represents the franchise-operated model, extending branded protocols through third-party clinic operators without direct facility ownership burdens.
| Leading Market Players |
|---|
| Cleveland Clinic |
| Duke Diet & Fitness Center |
| Cooper Clinic |
| Medical Weight Loss Clinic |
| Medi-Weightloss |
| UCLA Health |
| NYU Langone Hospitals |
| Geisinger Medical Center |
| Scripps Clinic |
| Others |
Supply & Pricing Matrix
GLP-1 receptor agonist manufacturing concentration in Denmark and the United States concentrates margin capture upstream with Novo Nordisk and Eli Lilly, forcing downstream clinic operators to absorb drug cost pass-through through direct-pay membership models or compressed multidisciplinary staffing ratios.
Pricing Analysis
Prescriber credential tier creates the primary spread between hospital-based pharmaceutical protocols and allied health professional services, with FDA-accredited metabolic programs commanding premium positioning against state-licensed dietitian-led alternatives. Three-tier pricing structure across premium, standard, and economy levels stratifies by program intensity and biomarker monitoring frequency. Pricing pressure stems from GLP-1 acquisition costs consuming program revenue, compressing clinic margins. Employer-sponsored health plan subscribers exhibit lowest price sensitivity due to coverage mandates, while cash-paying patients in high-deductible markets drive demand for stripped-down behavioral therapy packages.
Supply Chain Analysis
FDA enforcement actions against unapproved semaglutide compounding facilities restrict pharmaceutical flow into clinic-affiliated pharmacies, redirecting patient volume toward branded channels with established formulary relationships. Active pharmaceutical ingredient sourcing draws from India and China for generic metabolic medications, while patented GLP-1 analog production centers on Denmark and the United States. Single-source vulnerability concentrates in Novo Nordisk's Wegovy supply allocation decisions. Distribution runs through integrated health system formularies, specialty pharmacy networks, and direct-to-clinic wholesale arrangements.

Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Buyer power is concentrating among integrated health systems with employer-contracted volume, fragmenting access for independent private practices navigating direct-pay models.
For Market Incumbents: Harden formulary negotiation capabilities against GLP-1 cost pass-through by embedding bariatric surgery referral pathways that capture lifetime patient value. Deepen backward integration into telehealth platform development to reduce per-patient labor intensity and defend margin position against asynchronous coaching entrants.
For New Entrants and Emerging Players: Establish a beachhead in maintenance-phase telehealth monitoring, the most penetrable segment where asynchronous biomarker tracking reduces credentialing barriers. Target state Medicaid expansion jurisdictions with nurse practitioner scope-of-practice liberalization, deploying subscription-based membership models that bypass prior authorization delays.
For Investors and Strategic Acquirers: Capital is best deployed toward franchise-operated clinic networks with asset-light expansion models and established GLP-1 protocol licensing. Long-term viability hinges on CMS reimbursement durability for intensive behavioral therapy. Watch state Medicaid formulary tier placement decisions as the primary inflection indicator for addressable patient pool expansion.
| Strategic Initiative | Industry Significance |
|---|---|
| Telehealth Platform Licensing | Reduces per-patient labor intensity while maintaining HIPAA-compliant reimbursement eligibility across state lines. |
| Hospital System Partnership | Captures employer-sponsored plan volume through EHR-embedded referral workflows and bariatric surgery pipelines. |
| FDA Submission Pathway | Accelerates pharmaceutical protocol updates for semaglutide products within supervised program offerings. |
| Third-Party Clinical Space Leasing | Enables geographic expansion without direct facility ownership burdens for franchise-operated networks. |
| Reimbursement Strategy Development | Secures CMS coverage determinations for intensive behavioral therapy sessions in Medicare-contracted clinics. |
Research Methodology
A spread of perspectives from bariatric surgeons, formulary directors at commercial payers, nurse practitioner clinic operators, and GLP-1 pharmaceutical account managers converged on the working assumptions. Primary interviews combined with secondary validation from FDA approval databases, CMS Medicare coverage determinations, state scope-of-practice regulatory filings, and employer wellness plan design documents. Bottom-up patient volume estimates triangulated against top-down pharmaceutical shipment data.
Demand-supply balance modeling across the analysis window integrated service type segmentation, delivery mode adoption curves, and end-user facility economics. Segmentation dimensions included pharmaceutical intervention intensity, telehealth versus in-person visit mix, and program duration architecture. CAGRs derived from patient enrollment trajectories, reimbursement policy evolution timelines, and GLP-1 formulary expansion patterns. Forecast inputs incorporated FDA accelerated approval pathway utilization rates and state Medicaid expansion decisions.
Sensitivities concentrate around CMS reimbursement determinations for intensive behavioral therapy and state-level GLP-1 formulary tier placement. Forecasts reflect documented assumptions on employer wellness mandate expansion and telehealth parity law durability. Material shifts in FDA enforcement posture toward compounded semaglutide or Medicare Advantage obesity coverage would require updated calibration.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Healthcare Services
Medical Case Management Services Market
Healthcare Services
Metabolomics Services Market
Healthcare Services
Medical Billing Outsourcing Market
Healthcare Services
Global Retirement Home Services Market
Healthcare Services
US Medical Billing Outsourcing Market
Healthcare Services
Direct-To-Patient Healthcare Logistics Market
Healthcare Services
United States Senior Living Market
Healthcare Services
Retail Clinics Market
Healthcare Services
China Fertility Services Market
Healthcare Services
Global Healthcare Contract Development and Manufacturing Organization Market
Healthcare Services
Global Contract Sterilization Market
Healthcare Services
Packaging and Labeling (Healthcare) Services Market
Healthcare Services
Outpatient Clinics Market
Healthcare Services
Contract Manufacturing Services Market
Healthcare Services
Western Europe Medical Recruitment Market
Healthcare Services
Hospice and Palliative Care Centers Market