
 Hospice Market | 2026-2036
Hospice Market Size, Share, and Industry Trends Forecast 2026-2036
Hospice Market Outlook
A capital-intensity divergence between national chains and regional operators is redrawing competitive boundaries in hospice services. VITAS Healthcare Corporation leverages its vertically integrated pharmacy and durable medical equipment capabilities to sustain margin compression in labor-heavy markets. Amedisys anchors its position through concentrated geographic clusters that dominate Medicare Advantage contracting in the Southeast. Compassus differentiates via specialized cardiac and neurological care pathways that command premium reimbursement rates from private insurance payers.
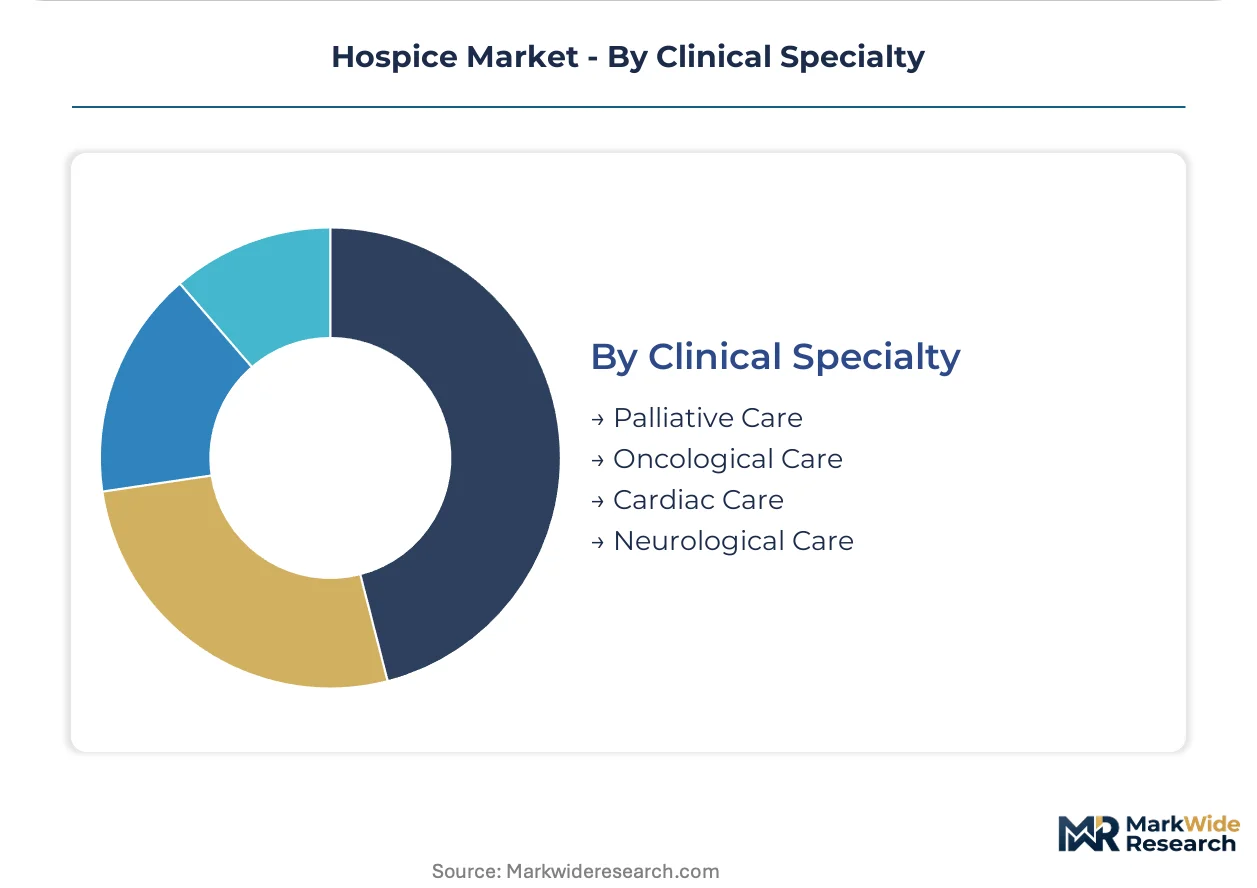
Hospice comprises interdisciplinary end-of-life care delivered through nursing, physician oversight, psychosocial support, and symptom management protocols, typically initiated when curative treatment ceases and life expectancy falls below six months per clinical certification. The primary purpose centers on quality-of-life optimization for terminally ill patients through pain control, family counseling, and spiritual care coordination rather than curative intervention. Home care services lead volume distribution due to Medicare reimbursement structures favoring lower-acuity settings, while inpatient care commands concentrated margin pools from crisis-level continuous nursing. Palliative care represents the fastest-growing clinical specialty as hospitals integrate advance care planning earlier in disease progression, whereas oncological care remains the mature revenue base tied to established cancer center referral networks.
The Centers for Medicare & Medicaid Services shapes demand through hospice capitation rates and quality reporting mandates under the Hospice Quality Reporting Program, while state-level Departments of Health enforce facility licensing and staffing ratio requirements that directly determine market access. The U.S. Department of Health and Human Services periodically revises the Medicare hospice benefit conditions of participation, forcing operators to recalibrate clinical documentation and interdisciplinary team composition. Stakeholders must monitor emerging state Medicaid expansion of concurrent curative and hospice services, as policy shifts here will determine whether dual-eligible populations become addressable or remain locked out of integrated care models.
Market Dynamics
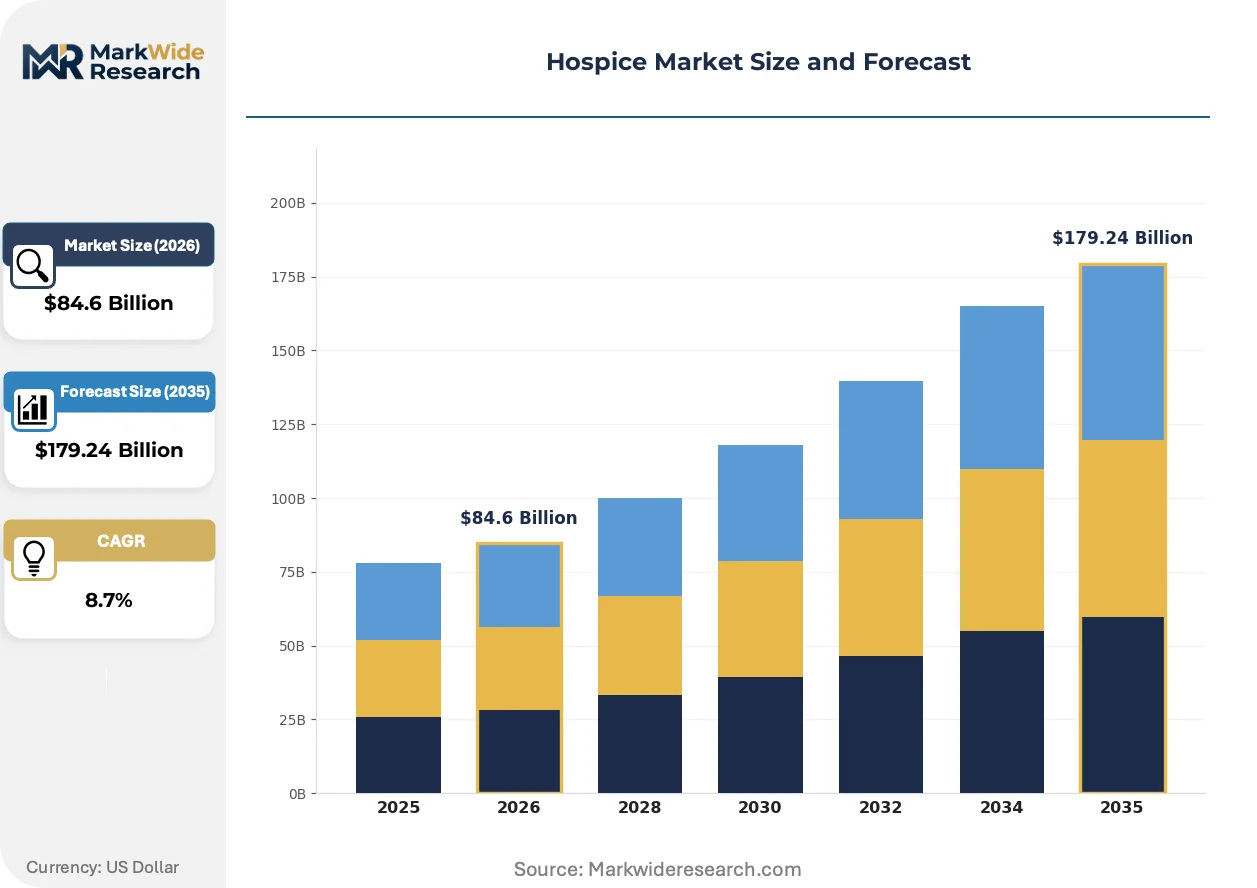
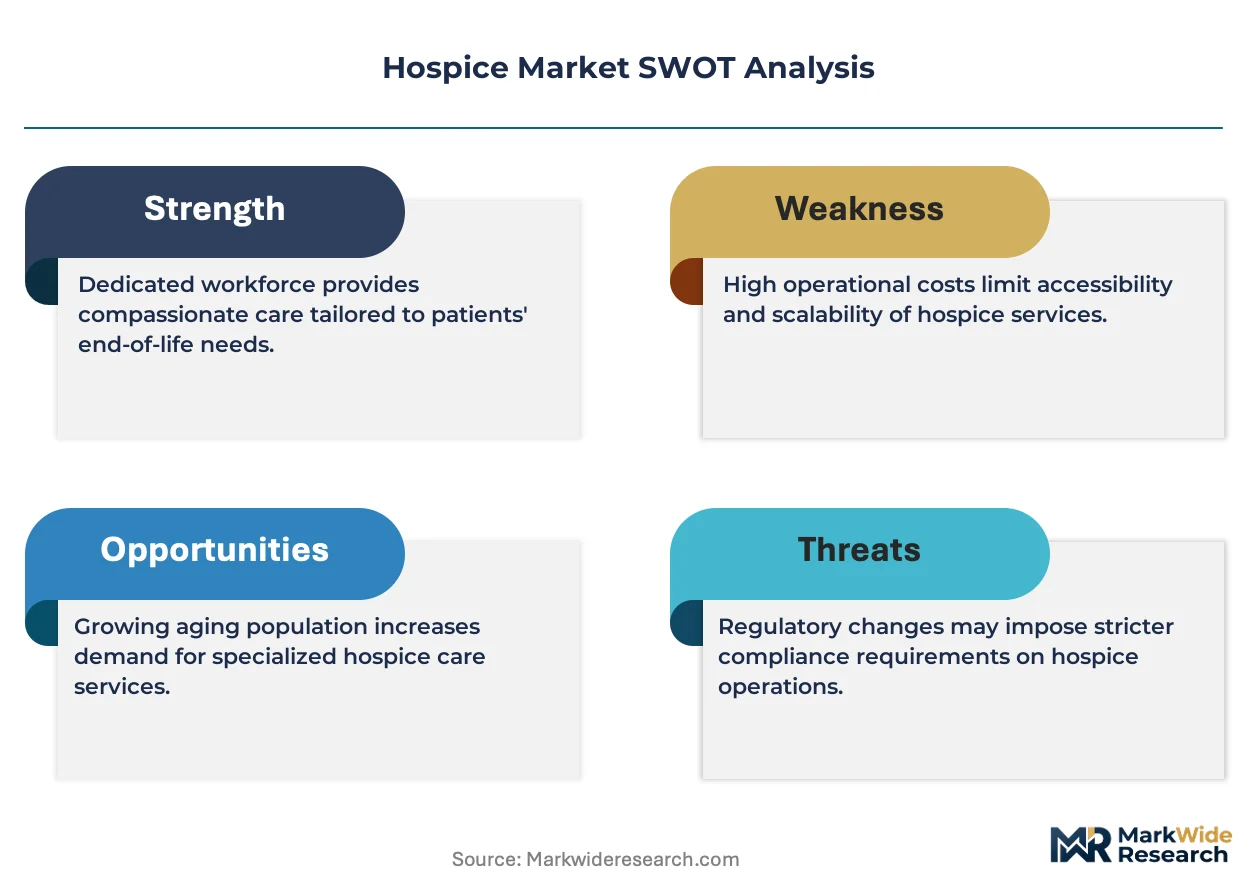
Medicare capitation rate adjustments and concurrent care policy experiments are compressing operator margins while redistributing patient volume toward home-based settings. This reimbursement architecture forces hospice providers to reconfigure interdisciplinary team staffing ratios and pharmacy cost structures.
Growth Catalysts
- Concurrent Curative-Hospice Waivers:CMS demonstration projects in select states now permit chemotherapy and hospice services simultaneously, expanding addressable patient populations previously excluded by the six-month prognosis rule.
- Medicare Advantage Penetration:Managed care organizations in Florida, Arizona, and Texas are carving in hospice benefits with preferential network contracting, accelerating patient flow to contracted agencies.
- Telehealth Symptom Monitoring:Remote patient monitoring platforms enable continuous nursing oversight between scheduled visits, satisfying CMS conditions of participation while reducing labor mileage costs.
Market Restraints
- Registered Nurse Labor Scarcity:Hospice agencies in Texas metro corridors face vacancy rates exceeding 25% for case manager positions, forcing sign-on bonus inflation that erodes per-patient margins.
- Pharmaceutical Cost Volatility:Opioid analgesics and antiemetic protocols face unpredictable price swings due to DEA production quota adjustments and compounding pharmacy regulatory actions.
- Certificate-of-Need Thresholds:Tennessee, Kentucky, and several Southeastern states maintain CON requirements for inpatient hospice facilities, blocking de novo market entry regardless of demonstrated need.
Strategic Opportunities
- Medicaid Expansion States:North Carolina's recent Medicaid expansion creates first-time eligibility for dual-eligible populations previously excluded from integrated hospice benefit structures.
- Palliative Care Bridge Programs:Hospital-at-home initiatives in Arizona and Colorado permit earlier hospice engagement through advance care planning reimbursement codes.
- Value-Based Insurance Design:CMS Innovation Center models reward reduced emergency department utilization, creating shared savings pools for hospice agencies with embedded crisis-response capabilities.
Industry Challenges
- Chaplaincy and Social Work Recruitment:Hospice agencies struggle to staff mandated psychosocial disciplines at CMS-required ratios, particularly in rural service areas where clinical labor pools are shallow.
- Electronic Health Record Interoperability:Point-to-point data exchange between hospice platforms and hospital admission-discharge-transfer systems remains technically fragmented, delaying care transitions.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Hospice Market |
| Market Size in 2026 | $84.6 Billion |
| Market Size in 2035 | $179.24 Billion |
| CAGR (2026 – 2036) | 8.7% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Service Type: Inpatient Care, Home Care, Respite Care, Continuous Care Care Setting: Residential Facility, Hospital, Home, Hospice Center Payer Type: Medicare, Medicaid, Private Insurance, Self-Payment Clinical Specialty: Palliative Care, Oncological Care, Cardiac Care, Neurological Care |
| Companies Covered | Amedisys, Gentiva Hospice, VITAS Healthcare Corporation, AccentCare, Brookdale Senior Living Solutions, Chemed Corporation, LHC Group, Compassus, Kindred Healthcare, Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Hospice Market Strategic Shifts
Technology-enabled care coordination and regulatory pressure for quality transparency are restructuring how hospice agencies deploy clinical labor and report outcomes. These forces favor operators with embedded analytics capabilities.
Remote patient monitoring hardware paired with predictive analytics is fragmenting traditional visit-based care models. Medicare-certified agencies in Sun Belt states deploy continuous vital sign streaming to identify symptom escalation before crisis intervention becomes necessary. This telemetry infrastructure compresses emergency transport utilization while extending nurse case manager panel sizes beyond conventional ratios.
CMS Hospice Quality Reporting Program mandates are intensifying documentation burdens on interdisciplinary teams. The requirement to submit CAHPS hospice survey data and HIS quality measures directly influences Medicare Advantage network inclusion decisions. Agencies in competitive Florida markets respond by hiring dedicated quality improvement specialists and implementing real-time documentation workflows.
Family caregiver burden is reshaping site-of-service preferences toward residential hospice facilities with 24-hour nursing presence. Adult children in dual-income households increasingly reject home hospice when continuous bedside vigilance becomes impractical. This behavioral pivot concentrates margin pools in Georgia and South Carolina markets where freestanding inpatient units command premium per-diem rates from private insurance payers.
Hospice Market Segmentation
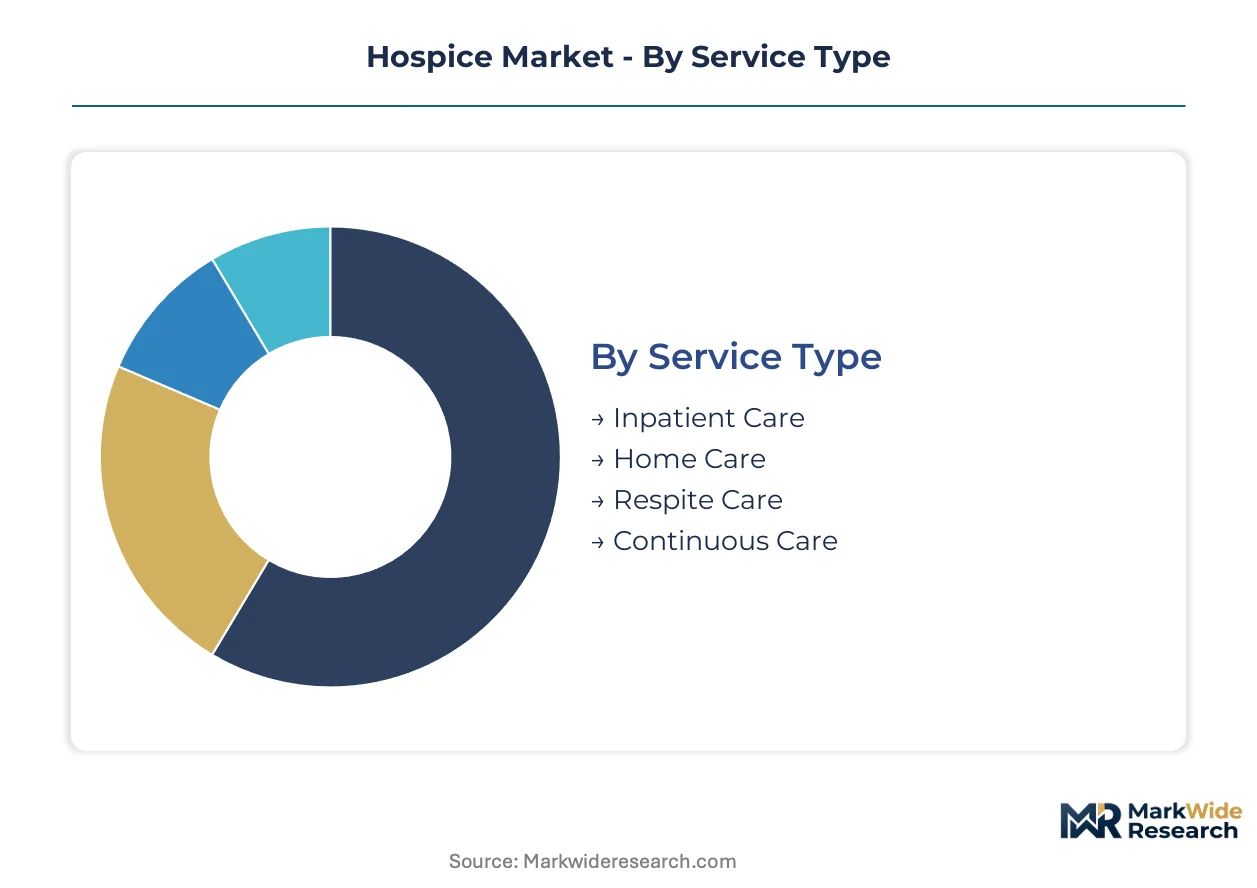
Hospice market segmentation reveals how reimbursement structures and clinical capabilities determine profitability across service lines. Operators must align capital deployment with where margin pools concentrate versus where volume flows.
Service Type:
Margin pools concentrate in crisis-intervention services where per-diem rates exceed routine care multiples, while routine home care dominates patient-day volume.
- Home Care:Medicare-certified nursing, aide, and therapy visits delivered in patient residences. Demand clusters in Florida retirement corridors and Arizona Sun Belt communities where aging-in-place preferences minimize facility transfers.
- Inpatient Care:24-hour skilled nursing in dedicated hospice units or contracted hospital beds for acute symptom management. Crisis-level continuous nursing commands premium reimbursement from private insurance payers in Georgia and South Carolina markets.
- Continuous Care:Short-term intensive nursing at home during medical crises. CMS reimbursement rates for this level exceed routine care, attracting operator investment in rapid-response nursing pools.
- Respite Care:Temporary inpatient stays providing family caregiver relief. Limited Medicare benefit days constrain volume, though Medicaid expansion states are testing extended respite authorization.
The dominant share belongs to Home Care, while Continuous Care is closing the gap fastest.
Care Setting:
Capital requirements vary dramatically across settings, with freestanding facilities demanding property investment while home-based models scale through labor recruitment.
- Home:Patient residences where Medicare reimbursement favors lower-acuity delivery. Texas metro corridors show highest penetration as hospital-at-home initiatives expand eligibility.
- Residential Facility:Dedicated hospice properties with 24-hour nursing presence. Adult children in dual-income households increasingly select this option when bedside vigilance becomes impractical.
- Hospice Center:Purpose-built inpatient units offering palliative-focused architecture. Certificate-of-need restrictions in Tennessee and Kentucky block de novo entry regardless of demonstrated need.
- Hospital:Contracted beds within acute-care facilities for crisis stabilization. Hospital-based palliative teams in Colorado and Arizona are integrating earlier hospice engagement through advance care planning codes.
Home settings generate the greatest patient-day volume, though Residential Facility placements are expanding most quickly.
Payer Type:
Reimbursement rate dispersion across payers creates portfolio optimization imperatives for multi-payer operators.
- Medicare:Federal capitation covering hospice benefit for eligible beneficiaries. CMS rate adjustments and quality reporting mandates under the Hospice Quality Reporting Program directly influence operator margins.
- Private Insurance:Employer-sponsored and individual plans often supplement Medicare cost-sharing or cover non-hospice palliative services. Specialized cardiac and neurological care pathways command premium rates from these payers.
- Medicaid:State-administered coverage for low-income and dual-eligible populations. North Carolina's recent expansion creates first-time eligibility for populations previously excluded from integrated benefit structures.
- Self-Payment:Direct patient or family funding for services outside benefit coverage. Limited scale concentrates in luxury residential facilities and non-covered complementary therapies.
Medicare holds the dominant share, with Private Insurance gaining ground fastest through Medicare Advantage carve-in contracts.
Clinical Specialty:
Specialization depth determines network inclusion decisions and reimbursement tier access.
- Oncological Care:Cancer-centered hospice services tied to established oncology referral networks. Mature revenue base with predictable referral flows from hospital-based cancer centers.
- Palliative Care:Symptom-focused services delivered earlier in disease progression before hospice eligibility. Hospitals integrate this specialty fastest as advance care planning reimbursement expands.
- Cardiac Care:Heart failure and cardiovascular disease pathways requiring specialized nursing protocols. Premium reimbursement rates from private insurers reward documented outcomes in reduced emergency department utilization.
- Neurological Care:Dementia, ALS, and Parkinson's disease management with extended prognosis trajectories. Complex symptom profiles demand interdisciplinary team expertise that fewer agencies maintain.
Oncological Care retains the largest share, though Palliative Care is expanding most rapidly as hospitals integrate earlier engagement models.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
Price sensitivity in hospice services diverges sharply between Medicare-dependent rural markets and private-insurance-rich metropolitan corridors. Sun Belt retirement destinations command premium per-diem rates through specialized cardiac and neurological pathways. Northern industrial states with aging manufacturing workforces exhibit tighter margin compression under capitated Medicaid structures.
United States
Medicare-certified agencies in Florida, Arizona, and Texas drive bed-day expansion through aging-in-place preferences and retiree population density. The Centers for Medicare & Medicaid Services shapes demand through hospice capitation rates and quality reporting mandates under the Hospice Quality Reporting Program. Dallas-Fort Worth and Houston metro corridors face registered nurse vacancy rates exceeding 25 percent for case manager positions.
Germany
Palliative care integration into statutory health insurance creates reimbursement stability for outpatient hospice services. The country's national pharmaceutical regulator enforces strict opioid prescribing protocols that influence symptom management cost structures. Bavaria and North Rhine-Westphalia concentrate specialized inpatient hospice facilities with 24-hour nursing presence.
Japan
Super-aging demographics accelerate demand for home-based end-of-life care as hospital bed capacity constraints intensify. METI promotes telehealth infrastructure development for remote symptom monitoring between scheduled nursing visits. Tokyo and Osaka prefectures concentrate hospital-at-home initiatives that permit earlier hospice engagement through advance care planning reimbursement.
United Kingdom
NHS Continuing Healthcare funding creates mixed payer dynamics alongside private insurance carve-outs for residential hospice placements. The Care Quality Commission enforces facility licensing and staffing ratio requirements that directly determine market access. London and Southeast England concentrate freestanding inpatient units commanding premium rates from private insurance payers.
Canada
Provincial health authority contracting patterns favor integrated health systems with embedded palliative care bridge programs. Health Canada oversees the national pharmaceutical regulator's oversight of opioid analgesic distribution for terminal symptom management. Ontario and British Columbia lead hospital-at-home expansion that compresses emergency transport utilization through continuous vital sign streaming.
Hospice Market Competitive Environment
A small set of integrated leaders sits above a broader specialist tier in hospice services, with capital-intensity divergence redrawing competitive boundaries. National chains leverage vertically integrated pharmacy and durable medical equipment capabilities to sustain margin compression in labor-heavy markets. Regional operators anchor positions through concentrated geographic clusters that dominate Medicare Advantage contracting. The dominant competitive moves include strategic partnerships with hospital systems for referral network access and portfolio diversification into palliative care bridge programs.
Within the integrated national tier, VITAS Healthcare Corporation and Amedisys occupy positions exemplifying divergent scale strategies. VITAS represents the vertically integrated archetype with captive pharmacy and equipment capabilities. Amedisys exemplifies geographic clustering dominance in Medicare Advantage contracting corridors. Compassus sits within the specialized clinical pathway segment, anchoring premium reimbursement access through cardiac and neurological care differentiation.
| Leading Market Players |
|---|
| Amedisys |
| Gentiva Hospice |
| VITAS Healthcare Corporation |
| AccentCare |
| Brookdale Senior Living Solutions |
| Chemed Corporation |
| LHC Group |
| Compassus |
| Kindred Healthcare |
| Others |
Value Chain & Pricing Dynamics
Capitated Medicare reimbursement contracts lock in predictable per-diem revenue streams while tethering hospice operators to fixed cost structures for nursing labor and pharmacy procurement across Texas, Florida, and Arizona markets. This payment architecture forces agencies to optimize supply chain responsiveness within rigid price ceilings set by CMS rate adjustments.
Pricing Analysis
After-sales service revenue from continuous care and crisis intervention tiers drives lifetime patient value beyond routine home care reimbursements. Three-tier pricing structure across premium specialty pathways, standard Medicare-certified services, and economy Medicaid-funded programs stratifies margin pools. Price differentiation hinges on clinical certification levels under CMS Hospice Quality Reporting Program mandates and geographic labor cost dispersion. Pricing pressure stems from registered nurse vacancy rates exceeding 25 percent in Dallas-Fort Worth corridors, forcing sign-on bonus inflation. Medicare Advantage carve-in contracts exhibit lowest price sensitivity due to preferential network exclusivity, while Medicaid expansion states face acute cost compression.
Supply Chain Analysis
DEA production quota adjustments for opioid analgesics create pharmaceutical supply chokepoints that disrupt symptom management protocols across U.S. hospice networks. Active pharmaceutical ingredient sourcing concentrates in India and China, while medical device and durable equipment manufacturing anchors in domestic U.S. production hubs. Raw material dependencies span controlled-substance narcotics, antiemetic compounds, and telemetry hardware for remote patient monitoring. Single-source vulnerability pervades specialized compounding pharmacy networks serving palliative care protocols. Distribution runs through Medicare-certified home health agencies, inpatient facility contracting, and hospital-at-home program partnerships.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Hospice platforms face an interoperability inflection as electronic health record fragmentation between agency systems and hospital admission-discharge-transfer networks creates ecosystem chokepoints. CMS mandates for quality data exchange are forcing API-level integration investments that reshape competitive moats.
For Market Incumbents: Consolidate geographic clustering dominance in Medicare Advantage contracting corridors before regional operators capture preferred network status. Acquire specialized cardiac and neurological care pathway capabilities to command premium reimbursement tiers from private insurance payers. Vertical integration into captive pharmacy and durable medical equipment supply buffers margin compression from labor cost inflation. Defend against telehealth-enabled new entrants by embedding predictive analytics into remote patient monitoring infrastructure.
For New Entrants and Emerging Players: Differentiate on palliative care bridge program integration with hospital-at-home initiatives in Arizona and Colorado markets where advance care planning reimbursement codes permit earlier hospice engagement. Target Medicaid expansion states such as North Carolina where dual-eligible populations previously excluded from integrated benefit structures now represent first-time addressable demand. Pursue white-space opportunities in rural service areas where chaplaincy and social work staffing shortages block incumbent expansion. Deploy direct-to-hospital sales models that bypass traditional physician referral network bottlenecks.
For Investors and Strategic Acquirers: Capital is best deployed toward vertically integrated mid-cap specialists with embedded pharmacy capabilities and concentrated Sun Belt geographic footprints that dominate Medicare Advantage contracting. Long-term viability over the coming decade hinges on regulatory navigation capacity as CMS experiments with concurrent curative-hospice waivers and value-based payment models. Acquisition target archetypes include agencies with proven quality reporting infrastructure and telehealth-enabled care coordination platforms. Watch for inflection signals in state Medicaid expansion patterns and concurrent care policy experiments that determine addressable population expansion.
| Strategic Initiative | Industry Significance |
|---|---|
| Palliative Care Bridge Program Integration | Hospital-at-home initiatives in Arizona and Colorado compress emergency transport utilization through earlier hospice engagement. |
| Medicare Advantage Network Exclusivity | Preferred contracting in Florida, Texas, and Arizona corridors locks in patient flow volume against regional competitors. |
| Telehealth Symptom Monitoring Deployment | Continuous vital sign streaming extends nurse case manager panel sizes while satisfying CMS conditions of participation. |
| Specialized Clinical Pathway Certification | Cardiac and neurological care differentiation commands premium reimbursement rates from private insurance payers. |
| Quality Reporting Infrastructure Investment | Real-time CAHPS and HIS documentation workflows secure Medicare Advantage network inclusion in competitive Florida markets. |
Study Parameters
Cross-validation between CMS Medicare hospice claims data and state-level Department of Health facility licensing records anchors the qualitative findings in observable regulatory compliance patterns. Primary interviews with hospice agency executives, Medicare Advantage contracting officers, hospital palliative care directors, and CMS policy specialists inform operational constraint mapping. Secondary sources include Medicare cost report filings, Hospice Quality Reporting Program datasets, state Medicaid expansion policy documents, and FDA controlled-substance distribution records. Bottom-up patient-day volume modeling triangulates against top-down reimbursement flow analysis.
Sensitivity analysis across concurrent care policy scenarios, Medicare capitation rate adjustment bands, and registered nurse labor supply elasticity shapes the forecast framework. Segmentation dimensions span service type, care setting, payer category, and clinical specialty pathways across the projection horizon. CAGRs derive from patient-day volume trajectories weighted by per-diem reimbursement tier mix. Industry-specific inputs include CMS demonstration project expansion timelines and state-level Certificate-of-Need regulatory status.
The analysis sits within stated boundaries; outcomes outside sustained Medicare reimbursement stability and gradual Medicaid expansion would require recalibration. Forecasts reflect assumptions regarding telehealth regulatory permanence and labor market tightening in Sun Belt metro corridors. Practitioners should keep alternative scenarios live as CMS Innovation Center payment model experiments and state-level concurrent curative-hospice waiver expansions evolve.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Healthcare Services
South Korea Healthcare Cold Chain Logistics Market
Healthcare Services
US Hospice Care Market
Healthcare Services
China Fertility Services Market
Healthcare Services
Global Healthcare Contract Development and Manufacturing Organization Market
Healthcare Services
Medical Devices and Equipment Logistics Market
Healthcare Services
Blood Bank Market
Healthcare Services
Hospital Command Center Operations Market
Healthcare Services
Global Perfusion Services Market
Healthcare Services
Spa Services Market
Healthcare Services
Healthcare Patent Filing Outsourcing Market
Healthcare Services
Transitional Care Management Services Market
Healthcare Services
US Retail Clinics Market
Healthcare Services
Funeral Goods and Services Market
Healthcare Services
Canada Corporate Wellness Market
Healthcare Services
Europe Medical Affairs Outsourcing Market
Healthcare Services
Global Cord Blood Banking Services Market