
 Group Health Insurance Market | 2026-2036
Group Health Insurance Market Size, Share, and Industry Trends Forecast 2026-2036
Group Health Insurance Market Outlook
Mid-sized employers is reorganizing the buyer landscape as they expand beyond basic coverage minimums toward comprehensive family plans. UnitedHealth Group leverages its integrated Optum care delivery network to control costs across employer contracts. Elevance Health sustains regional dominance through Blue Cross Blue Shield affiliate structures. CVS Health anchors pharmacy benefit integration within its Aetna employer book.
Group health insurance constitutes employer-sponsored medical coverage pooled across employee populations, typically structured through risk-sharing arrangements with annual deductible thresholds, coinsurance ratios, and negotiated provider network rates. Its primary purpose is to distribute healthcare financial risk across larger pools while securing discounted medical service access through managed care mechanisms. Preferred Provider Organization plans retain the largest enrollment share due to flexibility demands, while High Deductible Health Plans capture the fastest growth trajectory as employers shift cost exposure to workers. Self-insured arrangements dominate among corporations with over one thousand lives, creating distinct margin pools for administrative-services-only vendors and stop-loss carriers.
Employer plan design operates under overlapping federal frameworks including ERISA preemption standards, ACA essential health benefit mandates administered through HHS, and state insurance department solvency oversight. IRS code sections 105 and 106 govern the tax-exempt status of employer premium contributions, directly shaping plan affordability and participation rates. Stakeholders must monitor state-level public option expansions and Medicaid buy-in proposals that could erode the employer-sponsored coverage foundation.
Market Dynamics
Mid-sized employer mandates under the Affordable Care Act employer provisions are reshaping coverage depth requirements, forcing carriers to restructure actuarial models around family-tier benefit floors rather than individual minimums.
Growth Catalysts
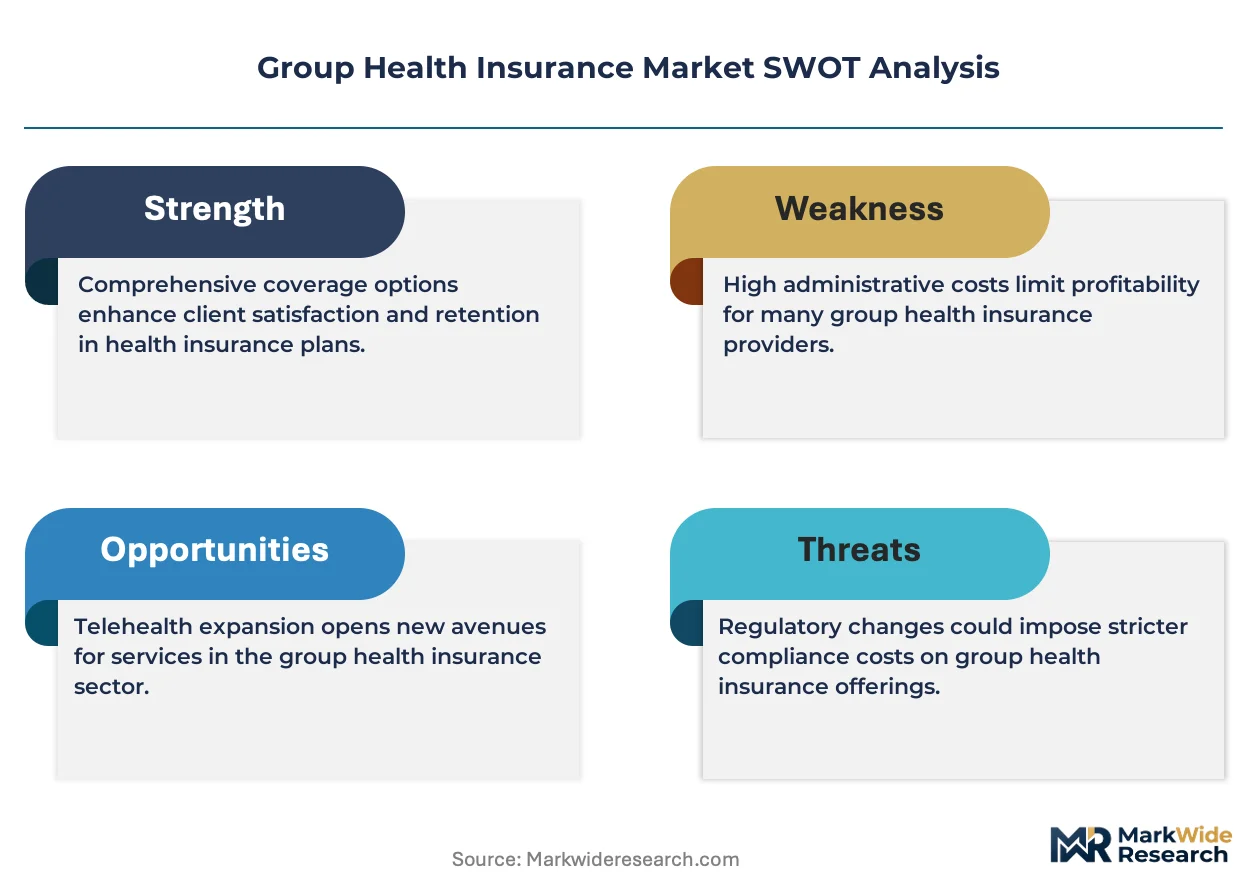
- ACA Employer Mandate Expansion:Mid-sized firms with 50-99 full-time equivalent employees now face phased coverage obligations, expanding the addressable employer pool for fully-insured products.
- Telehealth Infrastructure Maturation:Virtual care platforms integrated into plan designs reduce per-episode costs while expanding network reach for rural employee populations.
- Pharmacy Benefit Integration:Employers demand consolidated medical-pharmacy data streams to manage specialty drug spend, favoring carriers with captive PBM capabilities.
Market Restraints
- Medical Cost Inflation:Hospital consolidation in metropolitan markets compresses carrier negotiation leverage, pushing premium growth above wage inflation benchmarks.
- Stop-Loss Market Concentration:Reinsurance capacity for self-insured employers concentrates among a limited pool of specialty underwriters, creating attachment point volatility.
- State Regulatory Fragmentation:ERISA preemption gaps allow state insurance departments to impose conflicting network adequacy standards, raising compliance overhead for multi-state employers.
Strategic Opportunities
- Direct Primary Care Integration:Employers in Texas and Florida are piloting DPC wrap arrangements that bypass traditional fee-for-service primary care reimbursement.
- Centers of Excellence Carve-Outs:High-cost musculoskeletal and oncology episodes migrate to narrow network destinations with bundled pricing guarantees.
- Individual Coverage HRA Expansion:IRS Notice 2019-87 enables employers to fund individual market premiums through tax-advantaged arrangements, creating new distribution pathways.
Industry Challenges
- Actuarial Talent Scarcity:Pricing teams struggle to recruit professionals capable of modeling emerging risk adjustment methodologies under HHS-HCC frameworks.
- Legacy Core System Modernization:Mainframe-dependent carriers face integration friction when connecting to cloud-native care management platforms.
- Network Directory Accuracy:State attorneys general enforce stringent provider data validation requirements, imposing operational penalties for outdated listings.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Group Health Insurance Market |
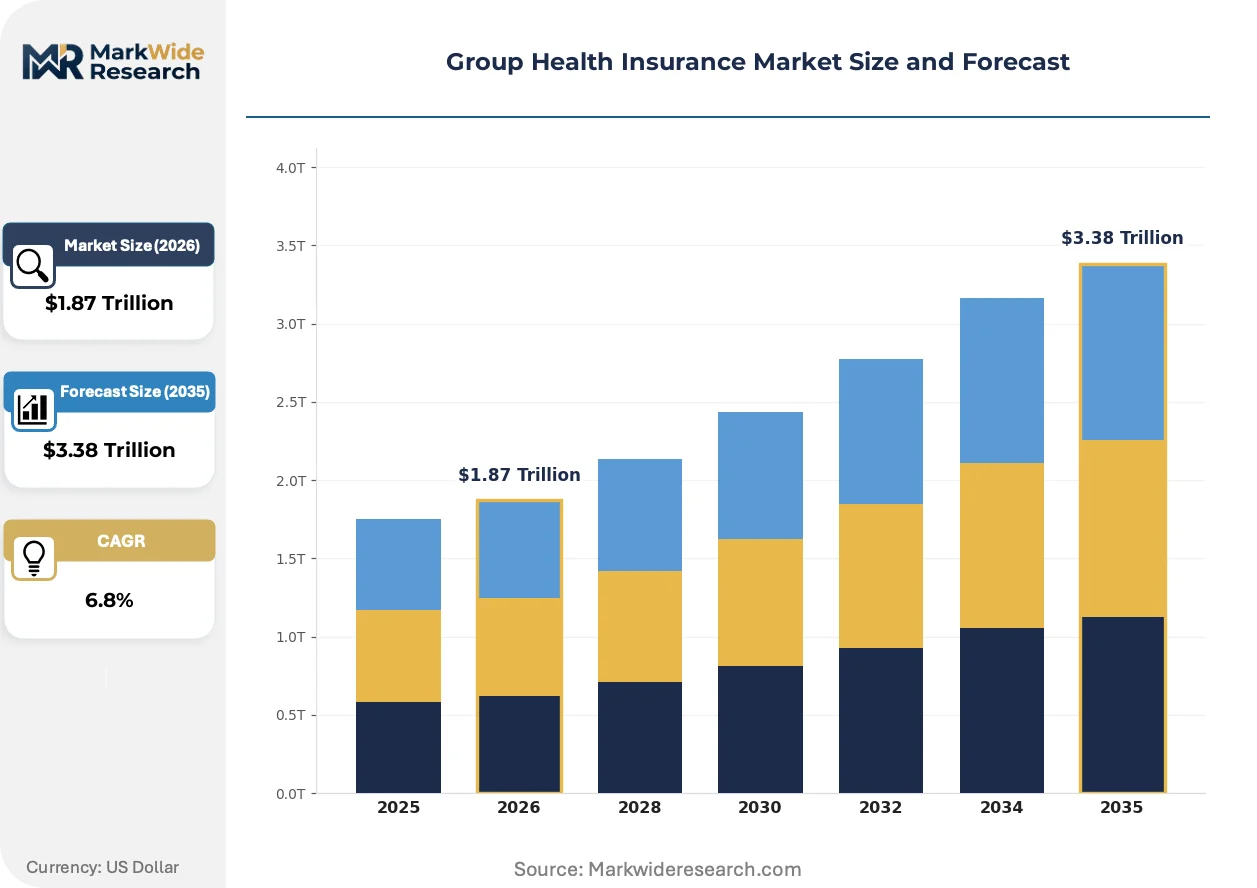
| Market Size in 2026 | $1.87 Trillion |
| Market Size in 2035 | $3.38 Trillion |
| CAGR (2026 – 2036) | 6.8% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Customer Type: Corporations, Small Businesses, Nonprofits, Educational Institutions Plan Type: Health Maintenance Organization, Preferred Provider Organization, Exclusive Provider Organization, High Deductible Health Plan Service Model: Self-Insured, Fully Insured, Level-Funded, Stop-Loss Coverage Level: Individual, Family, Employee Plus One, Group |
| Companies Covered | UnitedHealth Group, Elevance Health, CVS Health, Kaiser Permanente, Centene Corporation, Humana, Health Care Service Corporation, Cigna, Molina Healthcare, Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Group Health Insurance Market Strategic Shifts
Artificial intelligence is penetrating claims adjudication and prior authorization workflows, compressing administrative cost structures while raising new regulatory scrutiny around algorithmic bias in coverage determinations.
Machine learning models trained on historical claims patterns are displacing manual utilization review processes in large employer contracts. Anthem and Cigna pilot deployments reduce prior authorization turnaround from 72 hours to real-time determinations for routine procedures. This compression is displacing traditional nurse reviewer headcount while shifting liability exposure toward algorithmic error coverage in E&O policies.
The No Surprises Act independent dispute resolution framework imposes federal arbitration requirements for out-of-network billing disputes. Emergency departments and air ambulance operators face binding payment determinations that cap patient responsibility at in-network cost-sharing levels. Self-insured employers in California and New York report reduced balance billing exposure, though arbitration filing volumes strain IDR entity capacity.
Employer procurement teams now demand episode-based cost transparency tools rather than traditional premium-quote comparisons. Third-party administrators respond by embedding real-time claims analytics dashboards into annual renewal negotiations. This behavioral shift concentrates most visibly among manufacturing employers in the Midwest seeking to benchmark surgical spend against regional Medicare rates.
Group Health Insurance Market Segmentation

Group health insurance carriers structure product portfolios across four intersecting dimensions that determine pricing models, regulatory obligations, and network configuration requirements. Each segmentation axis carries distinct margin profiles and compliance frameworks that shape carrier go-to-market strategies.
Customer Type:
ERISA preemption standards apply uniformly across all employer categories, yet ACA employer mandate thresholds create divergent compliance burdens based on full-time equivalent headcount.
- Corporations:Self-insured arrangements dominate among entities exceeding one thousand covered lives, generating administrative-services-only revenue streams for third-party administrators. Risk retention groups and captive insurance structures concentrate demand in Texas, Delaware, and Vermont domiciles where regulatory capital requirements favor large employer sponsorship.
- Small Businesses:Fully-insured products absorb underwriting risk entirely onto carrier balance sheets, with SHOP exchange participation concentrated in states operating federally-facilitated marketplaces. Premium tax credit eligibility through IRC Section 45R drives plan selection behavior among firms with fewer than twenty-five full-time equivalents.
- Nonprofits:Section 501(c)(3) status unlocks distinct funding vehicles including 403(b) retirement integration and church plan exemptions from certain ERISA reporting requirements. Demand clusters among healthcare systems and educational service organizations with mission-aligned benefit philosophies.
- Educational Institutions:Public school districts navigate state-specific collective bargaining frameworks that mandate specific benefit tiers, while private universities leverage endowment-backed self-insurance with stop-loss attachment points calibrated to academic calendar cash flows.
Established volume favors Corporations; emerging adoption favors Small Businesses.
Plan Type:
Cost tier differentiation separates broad network flexibility from managed care gatekeeping intensity, with IRS high-deductible qualification standards creating additional tax-advantaged savings account eligibility.
- Health Maintenance Organization:Gatekeeper primary care models require member selection of a designated physician coordinator prior to specialist referral. Kaiser Permanente and similar integrated delivery systems anchor HMO enrollment in California, Hawaii, and mid-Atlantic markets where capitation rates align with provider system ownership.
- Preferred Provider Organization:Tiered network structures maintain out-of-network benefit access at reduced reimbursement rates, capturing the largest enrollment share among employer-sponsored populations. Flexibility demands from multi-state workforces sustain PPO dominance despite premium differentials versus managed care alternatives.
- Exclusive Provider Organization:Hybrid positioning combines HMO-style network restriction with absent primary care referral requirements, gaining traction among employers seeking middle-ground cost containment without utilization management friction.
- High Deductible Health Plan:IRS-qualified designs paired with health savings accounts shift first-dollar cost exposure to employees while reducing premium expenditures. Steepest expansion trajectory reflects employer cost-shifting strategies and employee tax-advantaged savings accumulation preferences.
Established volume favors Preferred Provider Organization; emerging adoption favors High Deductible Health Plan.
Service Model:
Risk-bearing configuration determines capital requirements, profit recognition timing, and regulatory oversight intensity across state insurance departments versus federal ERISA jurisdiction.
- Self-Insured:Employers assume direct claim liability, purchasing administrative services and stop-loss protection separately. Large manufacturing employers in the Midwest and technology firms in Washington and California dominate this segment, attracted by ERISA preemption of state benefit mandates and cash flow advantages from claim payment timing control.
- Fully Insured:Carriers assume complete underwriting risk, collecting fixed premiums regardless of claim experience. Small and mid-sized employers lacking actuarial infrastructure default to this model, with state premium tax obligations and guaranteed-issue requirements under ACA community rating rules.
- Level-Funded:Hybrid structures cap employer claim liability while offering premium stability resembling fully-insured arrangements. Regional carriers in Texas and Florida have pioneered this segment for employers with 25-100 lives seeking self-insurance benefits without maximum liability exposure.
- Stop-Loss:Reinsurance products protecting self-insured employers against catastrophic claim accumulation, with specific and aggregate attachment points calibrated to employer risk tolerance. Specialty underwriters concentrate capacity among a limited pool of carriers, creating pricing volatility in attachment point markets.
Established volume favors Fully Insured; emerging adoption favors Level-Funded.
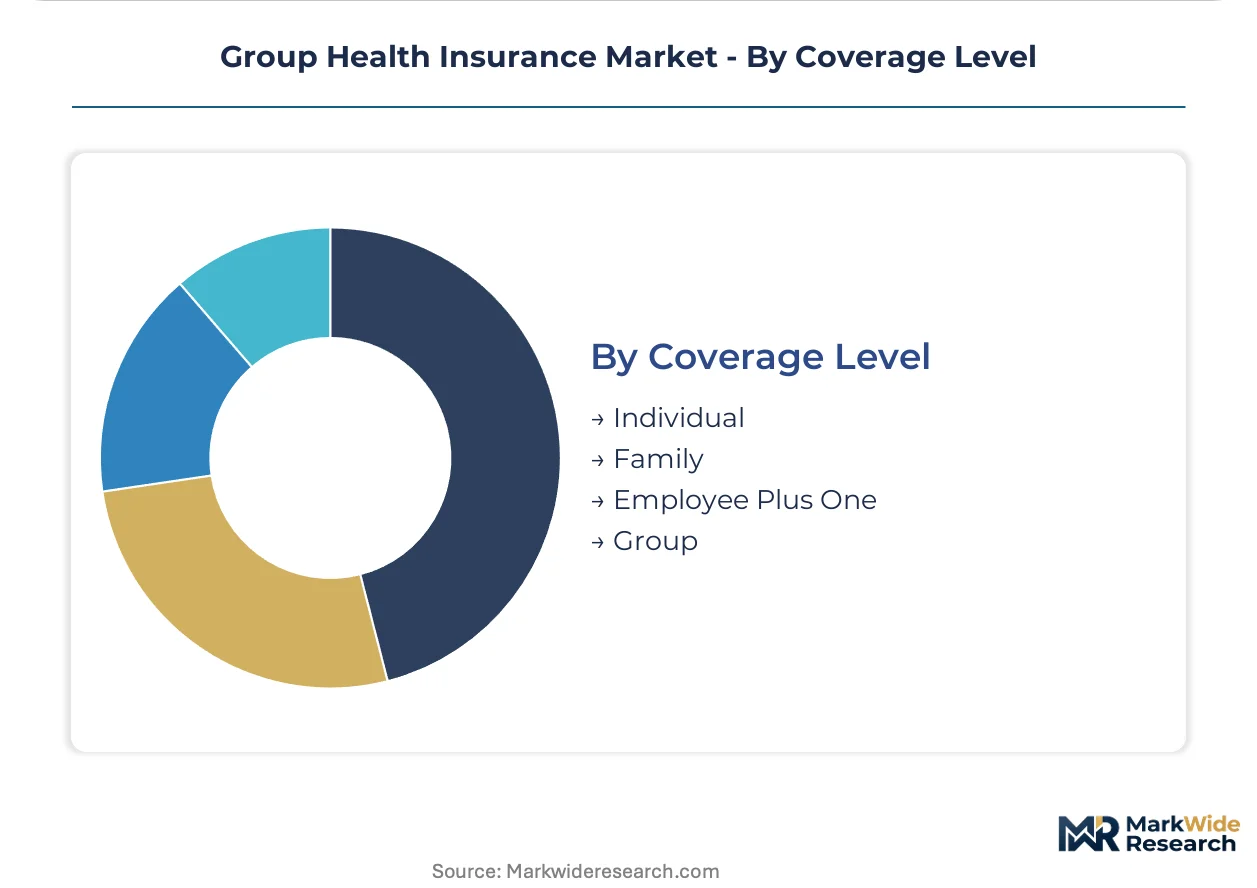
Coverage Level:
Benefit tier structure shapes actuarial valuation, with family coverage carrying distinct risk adjustment implications under HHS-HCC methodologies.
- Individual:Single-employee coverage carries lowest premium expenditure but highest per-capita administrative loading due to fixed enrollment processing costs. Younger workforce demographics in technology and professional services sectors show concentration here.
- Family:Employer plus spouse plus dependent tiers generate the highest premium volume per enrolled employee, with pediatric essential health benefit mandates under ACA driving coverage depth requirements. Mid-sized employer mandate expansion is reshaping actuarial models around family-tier benefit floors.
- Employee Plus One:Two-party coverage captures couples without dependent children, common among early-career professionals and empty-nest employee populations approaching Medicare eligibility.
- Group:Multi-life underwriting arrangements pool risk across affiliated employer entities, common among franchise systems, trade associations, and professional employer organizations operating under common control or industry affinity structures.
Established volume favors Family; emerging adoption favors Employee Plus One.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
The Interstate 95 corridor connects employer-dense metropolitan clusters from Boston to Washington DC, anchoring the highest concentration of group health insurance enrollment density in North America. This infrastructure corridor supports rapid provider network expansion and real-time claims processing infrastructure.
United States
Employer-sponsored family coverage dominates premium volume as mid-sized firms expand ACA mandate compliance. HHS administers essential health benefit standards while IRS Sections 105 and 106 govern tax-exempt premium contributions. Texas and Florida lead level-funded product innovation among 25-100 life employers seeking self-insurance alternatives.
Germany
Dual public-private health financing creates employer supplementary coverage demand for executive tiers and occupational health services. BfArM regulates digital health application reimbursement under DiGA fast-track pathways. Munich and Frankfurt financial services clusters drive corporate group policy customization for international assignee populations.
United Kingdom
NHS capacity constraints push large employers toward private medical insurance as recruitment and retention instruments. FCA conduct standards apply to insurance distribution alongside Prudential Regulation Authority solvency oversight. London's professional services density sustains bespoke large corporate risk arrangements.
Japan
Society-managed health insurance associations and government-managed schemes create fragmented employer contribution structures. PMDA evaluates digital therapeutics for reimbursement integration. Tokyo and Osaka manufacturing corridors sustain comprehensive coverage for lifetime employment cohorts.
Canada
Provincial single-payer gaps in prescription drugs, dental, and vision sustain employer-sponsored supplementary market expansion. Health Canada regulates medical device coverage while provincial insurance supervisors oversee carrier solvency. Ontario and Quebec financial services clusters anchor group benefits administration infrastructure.
Group Health Insurance Market Competitive Environment
Concentration sits with integrated health systems and diversified managed care conglomerates. The vendor base stratifies across three functional tiers: vertically integrated delivery systems owning captive provider networks, diversified carriers with pharmacy benefit management capabilities, and regional Blue Cross Blue Shield affiliates with state-level regulatory expertise. Dominant competitive moves include direct primary care network construction and specialty pharmacy carve-out integration.
Within the integrated delivery tier, Kaiser Permanente exemplifies closed-system capitation with geographic concentration in California and Hawaii. UnitedHealth Group occupies a position spanning administrative services, pharmacy benefits through Optum, and care delivery assets. Elevance Health anchors regional Blue Cross Blue Shield dominance through affiliate structures across fourteen states.
| Leading Market Players |
|---|
| UnitedHealth Group |
| Elevance Health |
| CVS Health |
| Kaiser Permanente |
| Centene Corporation |
| Humana |
| Health Care Service Corporation |
| Cigna |
| Molina Healthcare |
| Others |
Value Chain & Pricing Dynamics
Ninety-day claim adjudication cycles anchor carrier cash flow management and directly shape premium rate-setting authority across employer contract negotiations. This working capital interval concentrates pricing power among carriers with captive pharmacy benefit capabilities and integrated care delivery assets, while squeezing margins for administrative-services-only vendors dependent on faster claim turnover.
Pricing Analysis
Volume-discount tiering structures stratify across self-insured, level-funded, and fully-insured arrangements, with premium-mid-economy pricing differentiation reflecting employer size and risk-bearing preference. Price differentiation hinges on network breadth and stop-loss attachment point selection, with metropolitan hospital consolidation intensifying cost compression in PPO tiers. Small businesses with fewer than fifty lives exhibit highest price sensitivity due to fixed administrative loading, while Fortune 1000 self-insured employers leverage captive reinsurance for rate stability.
Supply Chain Analysis
Inbound logistics costs for specialty pharmaceutical distribution through cold-chain networks concentrate supply risk in United States, Ireland, and Singapore hub configurations. Raw material dependencies span active pharmaceutical ingredients, biologics manufacturing capacity, and medical device components. Single-source vulnerability in gene therapy manufacturing feeds pricing volatility for employer pharmacy benefit managers. Distribution runs through three-tier structures linking manufacturers to pharmacy benefit managers to retail and mail-order dispensaries.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Incumbents face substitution pressure from individual coverage HRA arrangements and public option expansions that could erode employer-sponsored coverage foundations. Defense requires reinforcing the employer value proposition against these alternative financing mechanisms.
For Market Incumbents: Consolidate administrative scale through third-party administrator acquisitions to defend against level-funded competitors. Deepen captive pharmacy benefit integration to offset medical cost inflation from hospital consolidation. Anchor network adequacy in Texas and Florida where regulatory arbitrage sustains margin.
For New Entrants and Emerging Players: Differentiate on direct primary care wrap arrangements bypassing fee-for-service reimbursement. Target mid-sized employers with 50-99 lives facing phased ACA mandate obligations. Pursue level-funded product innovation for employers seeking self-insurance benefits without maximum liability exposure.
For Investors and Strategic Acquirers: Carve-out targets emerge from regional Blue Cross Blue Shield affiliates with state-level regulatory expertise but subscale administrative infrastructure. Long-term viability centers on carriers with integrated pharmacy benefit capabilities and care delivery assets. Monitor state Medicaid buy-in proposals as inflection signals for employer coverage erosion.
| Strategic Initiative | Industry Significance |
|---|---|
| Pharmacy Benefit Integration | Consolidated medical-pharmacy data streams enable specialty drug spend management for self-insured employers. |
| Direct Primary Care Network Construction | DPC wrap arrangements in Texas and Florida bypass traditional fee-for-service primary care reimbursement models. |
| Level-Funded Product Expansion | Hybrid structures capture mid-sized employers seeking self-insurance benefits without catastrophic claim exposure. |
| Centers of Excellence Carve-Outs | Bundled pricing guarantees for musculoskeletal and oncology episodes reduce high-cost claim volatility. |
| Telehealth Infrastructure Deployment | Virtual care platforms reduce per-episode costs while extending network reach to rural employee populations. |
Study Parameters
A spread of perspectives from benefits directors, carrier actuarial leads, third-party administrator executives, and stop-loss underwriters converged on the working assumptions underlying employer-sponsored coverage demand. Primary fieldwork combined structured interviews with secondary validation through NAIC statutory filings, CMS Medicare Advantage rate books, ERISA plan document databases, and employer benefits survey archives. Bottom-up enrollment data triangulated against top-down premium volume estimates across the analysis window.
Segmentation dimensions modeled span employer size tier, plan type configuration, risk-bearing arrangement, and coverage level structure throughout the forecast period. CAGRs derived from historical premium growth patterns adjusted for medical cost inflation and regulatory mandate phase-ins. Forecast inputs incorporated ACA employer mandate expansion trajectories and telehealth utilization trend lines.
Material uncertainties — state public option legislation, Medicaid buy-in proposals, and hospital consolidation pace — sit outside the modeled envelope. Forecasts reflect assumptions regarding ERISA preemption continuity and employer mandate enforcement. Outcomes outside this envelope would require model recalibration.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Insurance
UK Travel Insurance Market
Insurance
Indonesia Private Health Insurance Market
Insurance
Germany Car Insurance Market
Insurance
Medical Claims Processing Services Market
Insurance
China Online Insurance Market
Insurance
Estonia Property and Casualty Insurance Market
Insurance
Solar Panel Warranty Insurance Market
Insurance
Microinsurance Market
Insurance
Boiler Insurance Market
Insurance
Parametric Insurance Market
Insurance
IoT Insurance Market
Insurance
Aviation Insurance Market
Insurance
Global Boats and Yacht Insurance Market
Insurance
United States Commercial Insurance Market
Insurance
Insurance Aggregators Market
Insurance
Norway Property and Casualty Insurance Market