
 Global Pediatric Clinical Trials Market | 2026-2036
Global Pediatric Clinical Trials Market Size, Share, and Industry Trends Forecast 2026-2036
Global Pediatric Clinical Trials Market Foresight
The EU Paediatric Regulation is realigning cost-of-entry calculus for contract research organizations serving European sponsors. IQVIA Inc. leverages its integrated data-science platform to anchor multi-site pediatric recruitment across North America and Europe. ICON plc sustains competitive position through specialized rare-disease and pediatric therapeutic units that navigate complex ethical-review requirements. Medpace, Inc. differentiates via its therapeutic-focus model, concentrating operational expertise in oncology and infectious-disease trials for adolescent and infant populations.
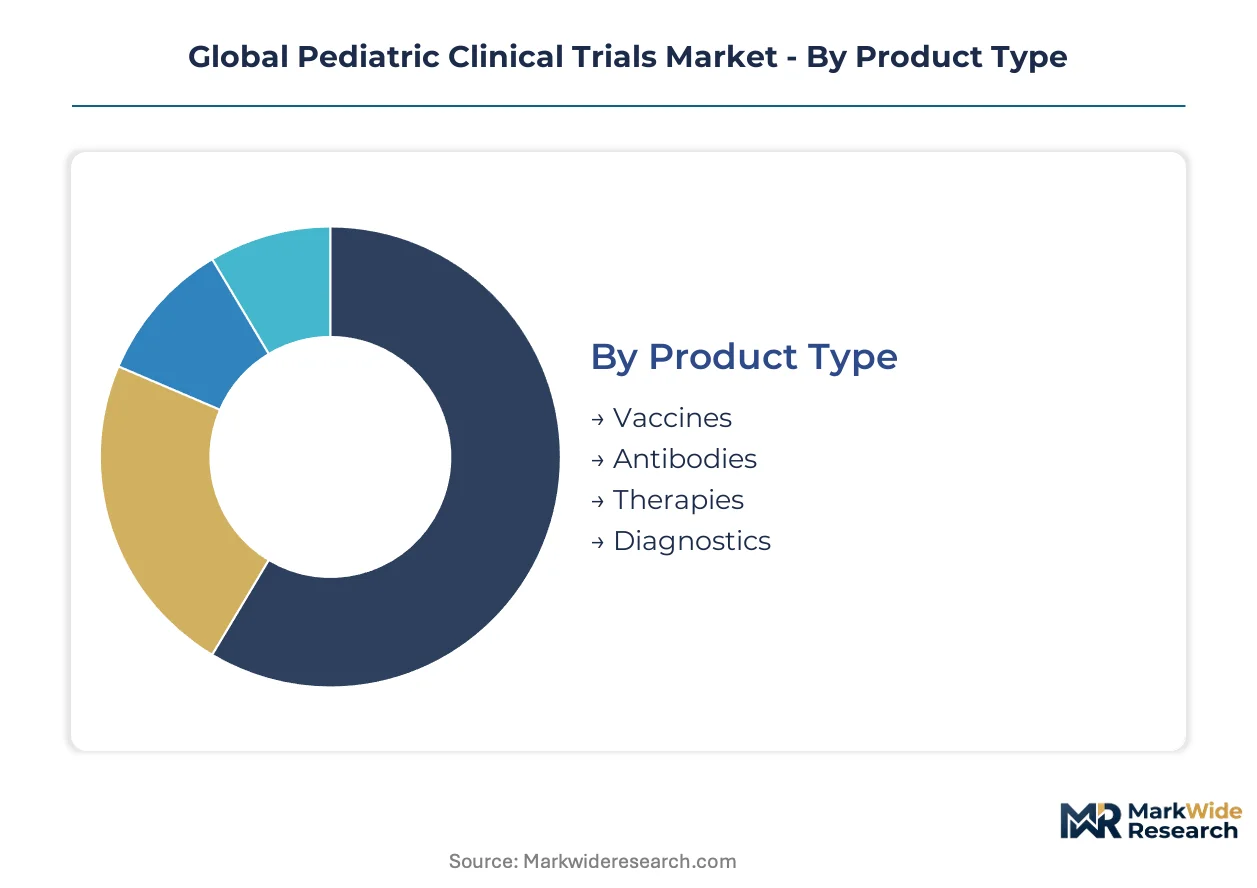
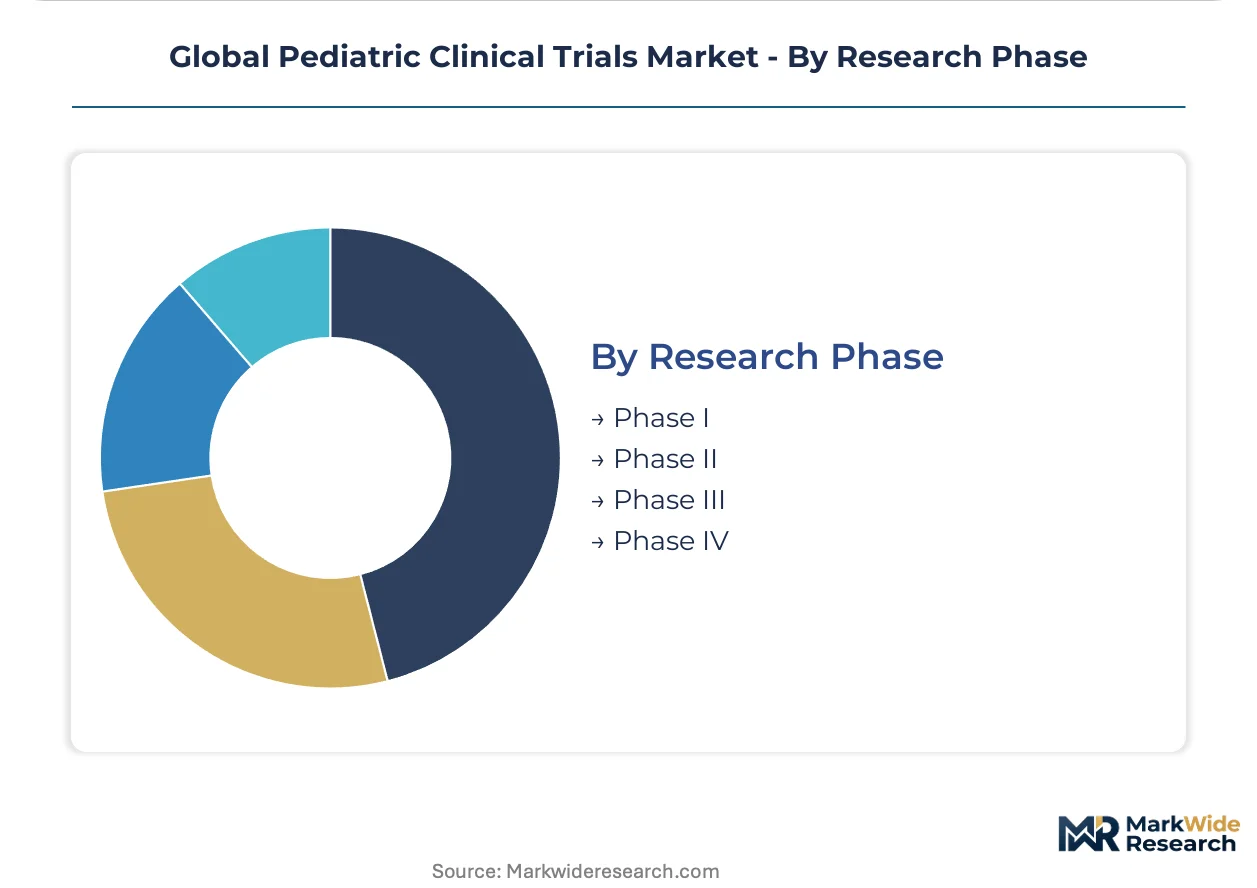
Pediatric clinical trials constitute structured biomedical research protocols designed to evaluate safety, efficacy, and dosing of interventions in subjects from birth through adolescence, typically stratified by developmental pharmacokinetic parameters including organ-maturity indices and weight-adjusted exposure metrics. These studies generate evidence for regulatory submissions and prescribing guidance where adult data cannot be extrapolated due to ontogenic differences in drug metabolism and receptor expression. The vaccines segment dominates trial volume owing to universal immunization schedules and established surrogate-endpoint pathways, while the antibodies category captures expanding margin pools as monoclonal and bispecific constructs target pediatric-exclusive indications including neuroblastoma and primary immunodeficiency. Phase III research commands the largest operational expenditure share, though Phase I pediatric pharmacokinetic studies are accelerating as sponsors front-load age-appropriate dosing validation under FDA and EMA mandate timelines.
The FDA, EMA, and WHO pediatric standards frameworks collectively shape protocol design, endpoint selection, and market-access timelines across jurisdictions. FDA's Pediatric Research Equity Act and EMA's Paediatric Investigation Plans require sponsors to submit pediatric development strategies concurrently with adult programs, compressing traditional sequential timelines. WHO's International Clinical Trials Registry Platform and pediatric-specific good clinical practice guidance further standardize transparency and ethical oversight expectations. Stakeholders must monitor evolving regulatory convergence between FDA and EMA on adolescent extrapolation criteria and real-world evidence acceptance for label extensions.
Market Dynamics
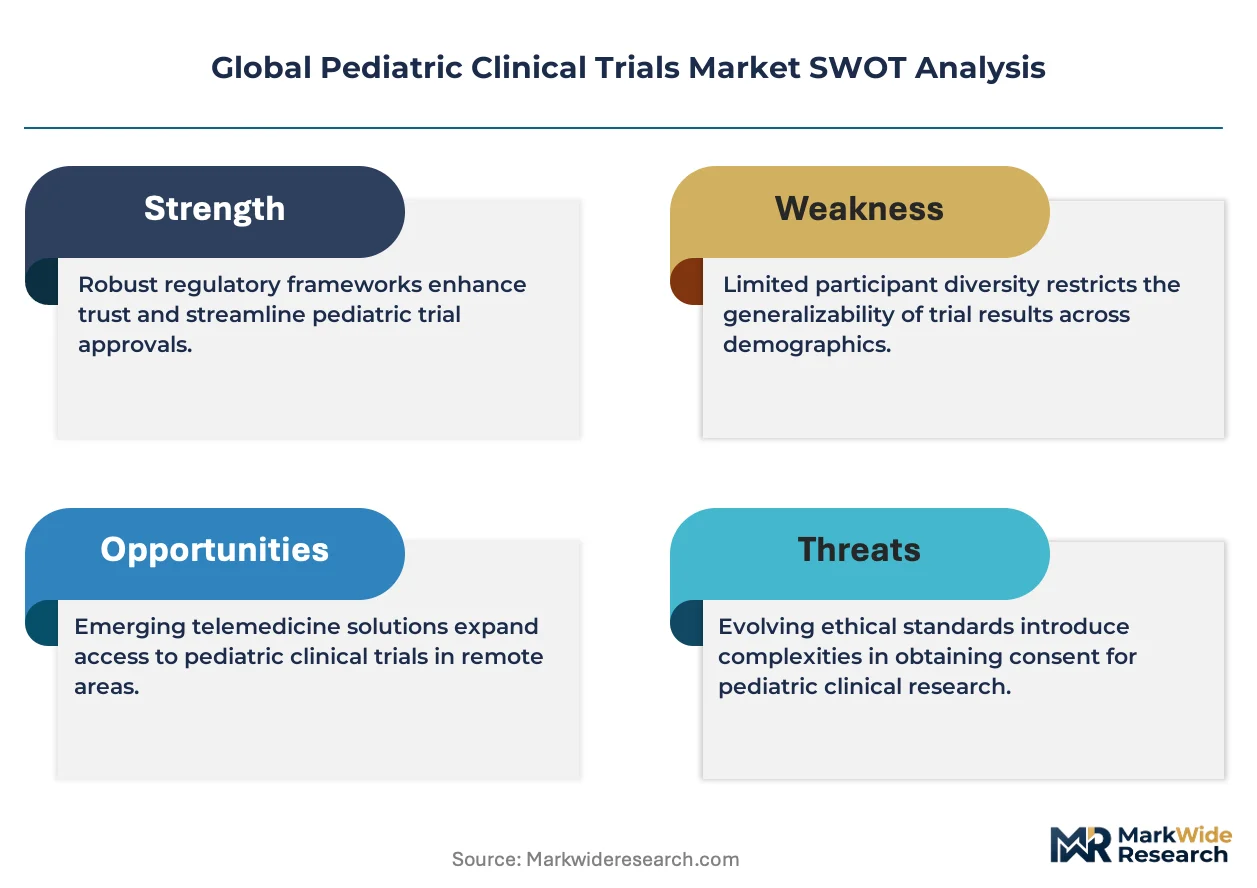
Regulatory convergence between FDA and EMA pediatric mandates is compressing development timelines and forcing sponsors to front-load age-appropriate trial design before adult data maturity, restructuring how contract research organizations allocate site networks and expertise.
Growth Catalysts
- EMA Paediatric Investigation Plans:Mandatory parallel pediatric development strategies accelerate sponsor investment in neonatal and adolescent protocols across European trial sites.
- Oncology biologics pipeline:Surging monoclonal and bispecific antibody programs for neuroblastoma and pediatric-exclusive malignancies expand addressable trial volume.
- Site density concentration in Germany and the United Kingdom:Established ethical-review infrastructure and specialized pediatric hospital networks reduce recruitment friction for complex protocols.
Market Restraints
- Qualified investigator scarcity:Limited pediatric subspecialists with GCP certification and neonatal pharmacology expertise constrains site activation timelines.
- Ethical-review fragmentation:Institutional review board variability across US states and EU member states creates protocol amendment cycles that extend study start-up duration.
- Placebo-controlled design limitations:EMA and FDA ethical guidelines restrict control-arm construction for life-threatening pediatric conditions, complicating efficacy demonstration.
Strategic Opportunities
- Real-world evidence pathways:FDA's expanding acceptance of registry-derived safety data for label extensions opens post-approval pediatric indication expansion without dedicated trials.
- Decentralized trial technologies:Remote monitoring and direct-to-patient dosing models unlock recruitment in dispersed geographies including Australia and Canada.
- Rare disease incentive stacking:EMA's orphan designation combined with FDA's Rare Pediatric Disease Priority Review Voucher program amplifies return on investment for ultra-small populations.
Industry Challenges
- Developmental pharmacology expertise gaps:Sponsors struggle to source clinical pharmacologists capable of modeling ontogenic enzyme maturation and weight-adjusted exposure metrics.
- Sample volume constraints:Micro-sampling technologies and sparse pharmacokinetic designs remain undervalidated for infants below two years, limiting data quality.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Global Pediatric Clinical Trials Market |
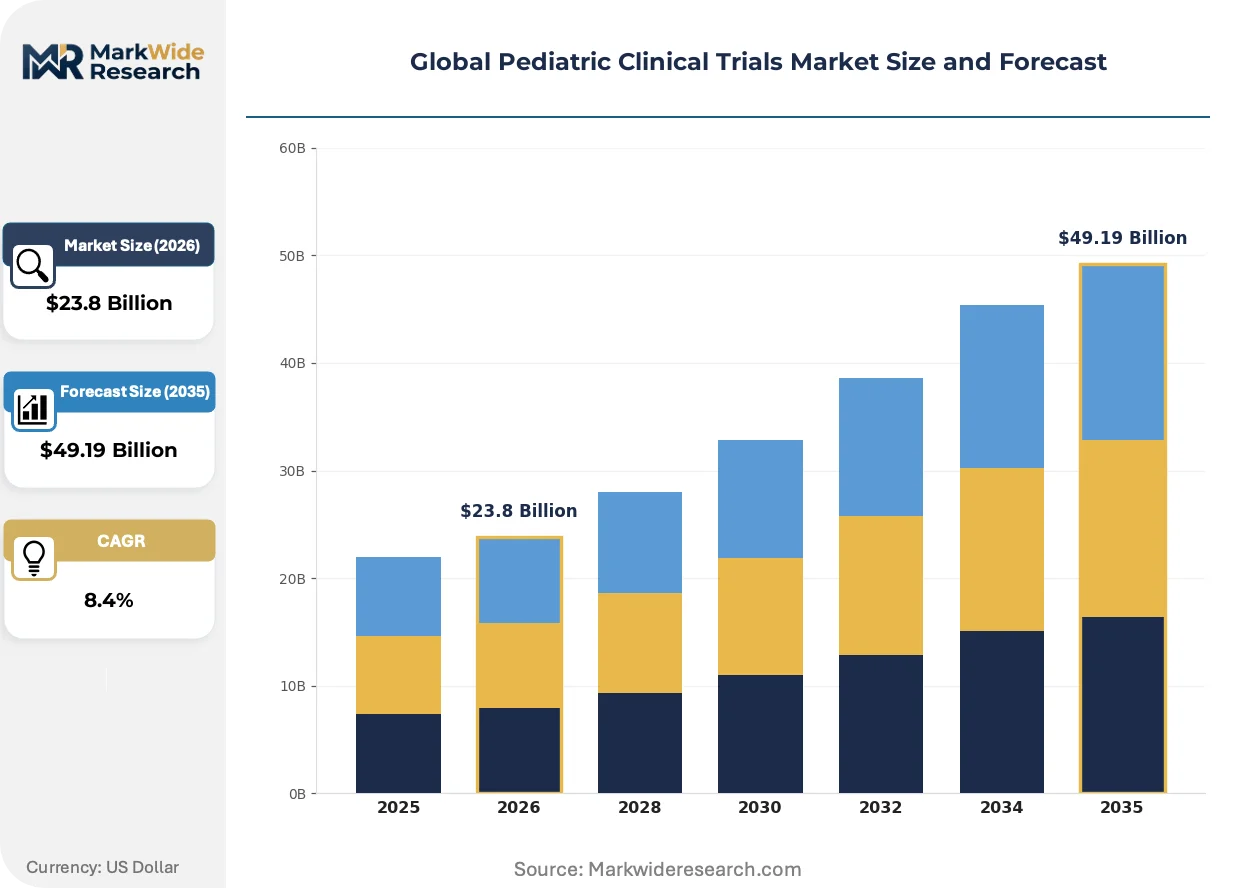
| Market Size in 2026 | $23.8 Billion |
| Market Size in 2035 | $49.19 Billion |
| CAGR (2026 – 2036) | 8.4% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Product Type: Vaccines, Antibodies, Therapies, Diagnostics Delivery Mode: Oral, Intravenous, Inhalation, Topical Age Group: Infants, Toddlers, Preschoolers, Adolescents Research Phase: Phase I, Phase II, Phase III, Phase IV |
| Companies Covered | IQVIA Inc., ICON plc, Syneos Health, Medpace, Inc., Thermo Fisher Scientific Inc., Premier Research, Laboratory Corporation of America, QPS Holdings, Parexel International, Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Global Pediatric Clinical Trials Market Shifts & Advancements
Distributed data capture and adaptive protocol architectures are dissolving traditional site-centric trial models, enabling sponsors to reach dispersed pediatric populations while compressing enrollment duration through real-time endpoint monitoring.
Decentralized clinical trial platforms incorporating wearable biosensors and telemedicine visits are decentralizing geographic access barriers for adolescent participants with chronic conditions. Sponsors running Type 1 diabetes and asthma protocols deploy these tools to maintain engagement across suburban and rural catchment areas. The structural result is decentralizing investigator-site monopoly over patient touchpoints and redistributing data generation toward home-based environments.
EMA's 2024 refinement of extrapolation guidance for adolescent populations is forcing sponsors to pre-specify physiologic similarity arguments before Phase III initiation. Pediatric oncology and immunology programs face the steepest compliance burden as regulators demand mechanistic rationale bridging adult receptor expression data to pediatric pharmacodynamics. German and French sponsors are responding by embedding juvenile toxicology studies earlier in development cascades.
Hospital network procurement consolidation is compressing site selection timelines as integrated delivery systems in the United States and National Health Service trusts in the United Kingdom centralize trial participation decisions through single contracting entities. Pediatric academic medical centers in Boston and London now coordinate multi-site feasibility through shared governance structures, displacing traditional sponsor-site bilateral negotiations.
Global Pediatric Clinical Trials Market Segmentation
Pediatric clinical trials demand precise segmentation to match developmental pharmacology with regulatory submission pathways. Each category reflects distinct operational constraints, from micro-sampling limits in infants to ethical-review complexity in adolescent oncology protocols.
Product Type:
Vaccines anchor the standardization end of the spectrum with established surrogate endpoints and universal immunization schedules, while antibodies and cell therapies push toward bespoke trial architectures for rare pediatric indications.
- Vaccines:Large-scale immunogenicity studies leverage established correlates of protection and streamlined safety databases. Demand concentrates in Gavi-eligible countries and US CDC schedule alignment programs, where procurement scale justifies dedicated pediatric bridging trials.
- Antibodies:Monoclonal and bispecific constructs require weight-adjusted dosing validation and juvenile toxicology bridging. Neuroblastoma and primary immunodeficiency programs in Germany and the United Kingdom drive protocol volume as EMA Paediatric Investigation Plans mandate earlier pediatric entry.
- Therapies:Small-molecule and gene therapy candidates span metabolic disorders and hematologic conditions.
- Diagnostics:Companion imaging and biomarker assays support trial endpoint validation across infectious disease and oncology indications.
Most installed capacity flows through Vaccines. Expansion is steepest in Antibodies.
Delivery Mode:
Route selection determines site infrastructure requirements and caregiver burden, with oral formulations minimizing clinical contact frequency and intravenous delivery demanding specialized pediatric infusion centers.
- Oral:Solutions and dispersible tablets accommodate swallowing capability limitations across age strata. Palatability testing and age-appropriate excipient safety drive formulation development costs for sponsors targeting preschool populations in India and Brazil.
- Intravenous:Central line access and infusion tolerance require hospital-based administration with anesthesiology standby. US children's hospitals in Boston and Philadelphia anchor recruitment for complex biologic infusions in primary immunodeficiency and oncology.
- Inhalation:Nebulizer and dry-powder devices demand age-matched lung-function coordination.
- Topical:Transdermal patches and creams minimize systemic exposure for dermatologic and local anesthetic indications.
Volume concentrates in Oral delivery. Margin expansion is strongest in Intravenous.
Age Group:
Developmental pharmacology maturity varies sharply across ontogenic stages, forcing sponsors to stratify protocols by hepatic enzyme induction patterns and renal clearance maturation timelines.
- Infants:Birth through twelve months presents the steepest ethical-review barriers and micro-sampling constraints. Neonatal pharmacokinetic studies in French and UK maternity networks generate critical ontogenic enzyme data for FDA submission requirements.
- Adolescents:Physiologic similarity arguments to adult populations enable extrapolation pathways, though EMA's 2024 guidance demands pre-specified mechanistic rationale. US and German sponsors embed juvenile toxicology earlier to support adolescent Phase III entry.
- Toddlers:One to three years requires adapted behavioral assessment tools and caregiver-intensive monitoring.
- Preschoolers:Three to five years bridges toddler dependence and school-age cooperation capabilities.
Recruitment volume peaks in Adolescents. Regulatory complexity is highest in Infants.
Research Phase:
Phase allocation determines capital intensity and timeline risk, with early-phase studies absorbing developmental pharmacology expertise costs and late-phase trials scaling across multi-site networks.
- Phase III:Pivotal efficacy studies command the largest operational expenditure share across global site networks. FDA and EMA mandate timelines compress traditional sequential development, forcing sponsors to activate US, German, and Japanese sites in parallel for pediatric-exclusive indications.
- Phase I:Pediatric pharmacokinetic studies are accelerating as sponsors front-load age-appropriate dosing validation. Sparse sampling designs and population PK modeling in Australian and Canadian academic centers reduce blood volume requirements for infant cohorts.
- Phase II:Dose-ranging and preliminary efficacy signals guide Phase III design.
- Phase IV:Post-approval safety surveillance and label expansion studies leverage registry data.
Operational spending concentrates in Phase III. Front-loading is most pronounced in Phase I.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
The pediatric clinical trials industry traces its modern regulatory foundation to the 1997 FDA Modernization Act in the United States, which first mandated pediatric studies for new drug applications. This legislative precedent catalyzed parallel frameworks across Germany, the United Kingdom, and Japan, establishing the current multi-jurisdictional compliance architecture.
United States
Specialized pediatric hospital networks in Boston, Philadelphia, and Cincinnati anchor recruitment for complex neonatal and adolescent oncology protocols. FDA's Pediatric Research Equity Act and Rare Pediatric Disease Priority Review Voucher program compress development timelines while amplifying sponsor return on investment. The Boston Children's Hospital and Cincinnati Children's Hospital Medical Center coordinate multi-site feasibility through shared governance structures.
Germany
Established ethical-review infrastructure and dense site networks in Berlin, Munich, and Heidelberg reduce recruitment friction for EMA Paediatric Investigation Plan compliance. EMA's 2024 extrapolation guidance refinement demands pre-specified mechanistic rationale for adolescent populations. German sponsors embed juvenile toxicology studies earlier in development cascades to support Phase III entry.
United Kingdom
National Health Service trust centralization streamlines trial participation decisions through single contracting entities in London, Birmingham, and Manchester. The UK Medicines and Healthcare products Regulatory Agency aligns with FDA on adolescent extrapolation criteria. London's Great Ormond Street Hospital and Birmingham Children's Hospital anchor specialized pediatric pharmacokinetic studies.
Japan
PMDA pediatric guidelines and growing biologics pipeline demand accelerate investment in neonatal and adolescent protocols across Tokyo, Osaka, and Nagoya academic medical centers. Japan's aging demographic paradoxically intensifies pediatric oncology focus as sponsors target pediatric-exclusive malignancies. The National Center for Child Health and Development in Tokyo coordinates multi-site networks.
Australia
Sparse pharmacokinetic sampling designs and population PK modeling in Melbourne, Sydney, and Brisbane academic centers reduce blood volume requirements for infant cohorts. The Therapeutic Goods Administration pediatric framework supports front-loaded age-appropriate dosing validation. Royal Children's Hospital Melbourne anchors Phase I pediatric pharmacology expertise.
Global Pediatric Clinical Trials Market Competitive Landscape
The competitive structure tilts toward integrated data-science platforms and specialized therapeutic units. Large-scale contract research organizations with multi-continental site networks dominate operational expenditure share, while mid-tier specialists capture margin pools in rare-disease and pediatric-exclusive indications. Two strategic archetypes prevail: platform-anchored full-service providers and therapeutic-focus boutique operators. Dominant competitive moves include therapeutic-area diversification and site-network geographic expansion.
Within the integrated-platform tier, IQVIA Inc. and ICON plc represent archetypes of data-science anchoring and specialized rare-disease unit construction. Medpace, Inc. exemplifies the therapeutic-focus model, concentrating operational expertise in discrete pediatric populations. These three entities collectively illustrate how competitive positioning in this market depends on either technological infrastructure depth or clinical-domain specialization.
| Leading Market Players |
|---|
| IQVIA Inc. |
| ICON plc |
| Syneos Health |
| Medpace, Inc. |
| Thermo Fisher Scientific Inc. |
| Premier Research |
| Laboratory Corporation of America |
| QPS Holdings |
| Parexel International |
| Others |
Supply & Pricing Matrix
EMA's 2024 extrapolation guidance refinement gates qualified supply for premium-tier pediatric trial services, compressing margins for CROs lacking juvenile toxicology capabilities while rewarding certified providers with pricing power in adolescent oncology protocols.
Pricing Analysis
Project-based contracting with milestone-triggered payments dominates pediatric clinical trial services, separating full-service platform providers from boutique therapeutic specialists on certification depth and site-network density. Price differentiation rests on FDA and EMA regulatory track record, with German and US sponsors paying premiums for proven Paediatric Investigation Plan submission success. Cost compression in standard-tier pharmacokinetic studies is intensifying because mid-tier CROs are replicating sparse-sampling methodologies. Academic medical centers and emerging biotech sponsors exhibit the sharpest price sensitivity, while large pharmaceutical sponsors prioritize regulatory certainty over unit cost.
Supply Chain Analysis
Regional distribution centers in Boston, London, and Berlin anchor hub-and-spoke site activation patterns for pediatric trial materials and investigator training. Supply concentrates in the United States, Germany, and the United Kingdom, where specialized pediatric hospital networks and ethical-review infrastructure reduce protocol amendment cycles. Cold-chain biologics logistics, micro-sampling collection devices, and juvenile toxicology study materials constitute critical input dependencies. Single-source vulnerability in qualified pediatric investigator pools constrains site activation timelines. Distribution runs through centralized contracting entities at NHS trusts and US integrated delivery systems.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
Pediatric clinical trials offer margin-expansion pathways as regulatory mandates front-load Phase I investment and real-world evidence pathways reduce post-approval trial costs for label extensions.
For Market Incumbents: Extend therapeutic specialization into rare-disease pediatric indications where EMA orphan designation and FDA Rare Pediatric Disease Priority Review Voucher programs amplify client willingness to pay premium fees. Deepen site-network control through exclusive partnerships with academic medical centers in Cincinnati, London, and Berlin to defend against platform-anchored competitors. Juvenile toxicology capability scarcity represents the primary threat to margin maintenance. For New Entrants and Emerging Players: Telemedicine-enabled decentralized trial platforms unlock white-space access in dispersed geographies including Australia and Canada, where sparse populations previously excluded sponsors from viable recruitment. Target adolescent chronic disease protocols in Type 1 diabetes and asthma, where wearable biosensors reduce site-dependency and caregiver burden. A direct-to-sponsor digital channel bypasses traditional site-feasibility bottlenecks. For Investors and Strategic Acquirers: Roll-up economics work for mid-tier CROs with pediatric therapeutic focus because EMA's Paediatric Investigation Plan mandates are compressing sponsor procurement timelines and favoring pre-qualified vendor panels. The 5-10 year viability window rests on regulatory convergence between FDA and EMA sustaining front-loaded development investment. Acquisition targets should demonstrate juvenile toxicology study execution and established relationships with German and UK ethical-review boards. The signal to watch is FDA's expanding real-world evidence guidance for pediatric label expansions.| Strategic Initiative | Industry Significance |
|---|---|
| Juvenile Toxicology Study Integration | EMA's 2024 guidance demands earlier embedding to support adolescent Phase III entry timelines. |
| Decentralized Trial Platform Deployment | Wearable biosensors and telemedicine unlock recruitment in Australian and Canadian dispersed populations. |
| Real-World Evidence Pathway Investment | FDA's expanding registry-derived safety acceptance enables post-approval indication expansion without dedicated trials. |
| Pediatric Site Network Consolidation | Exclusive partnerships with Boston and London academic medical centers displace bilateral sponsor negotiations. |
| Rare Disease Incentive Stacking | EMA orphan designation combined with FDA Priority Review Vouchers amplifies ROI for ultra-small pediatric populations. |
Research Methodology
Multiple input streams — primary interviews with pediatric clinical operations directors, regulatory affairs leads at biopharmaceutical sponsors, and site feasibility managers at academic medical centers — were reconciled against secondary validation from FDA Pediatric Research Equity Act filings, EMA Paediatric Investigation Plan submissions, ClinicalTrials.gov registry data, and WHO International Clinical Trials Registry Platform records. Bottom-up site activation and recruitment timelines were triangulated with top-down CRO revenue segmentation across service lines.
Historical pediatric trial completion rates were cross-referenced against expert panel assessments of regulatory timeline compression effects across the projection horizon. The analytical framework modeled segmentation by product type, age group, research phase, and regional regulatory cluster. CAGRs were derived from sponsor pipeline analysis and front-loading pattern identification in Phase I pharmacokinetic studies. Forecast inputs incorporated EMA extrapolation guidance implementation and FDA real-world evidence pathway expansion.
The model assumes a particular technology adoption path for decentralized trial platforms and micro-sampling devices; alternative pathways for wearable biosensor validation or telemedicine regulatory acceptance would alter the outlook for recruitment cost structures and site-network economics. Forecasts reflect documented assumptions regarding regulatory convergence timing and sponsor budget allocation priorities. Decision-makers should treat outputs as directional within the stated assumption set.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Pediatrics
Pediatric HIV Infection Treatment Market
Pediatrics
Autism Service Platform Market
Pediatrics
OTC Pediatric Healthcare Market
Pediatrics
Paediatric Influenza Treatment Market
Pediatrics
Pediatric Growth Hormone Deficiency Market
Pediatrics
Middle East and Africa Pediatric Healthcare Market
Pediatrics
Pediatrics Medicine Market
Pediatrics
Pediatric Craniosynostosis Treatment Market
Pediatrics
Pediatric Perfusion Products Market
Pediatrics
Pediatric Nasal Cannula Market
Pediatrics
Paediatric Wheelchairs Market
Pediatrics
Pediatric Home Healthcare Market
Pediatrics
Pediatric Healthcare Market
Pediatrics
Pediatric Oncology Treatment Market
Pediatrics
Pediatric Dental Market
Pediatrics
Pediatric Asthma Treatment Market