
 Disruptive Behavior Disorder (DBD) Treatment Market | 2026-2036
Disruptive Behavior Disorder (DBD) Treatment Market Size, Share, and Industry Trends Forecast 2026-2036
Disruptive Behavior Disorder (DBD) Treatment Market Insights
Consolidation among pediatric mental health clinic chains is restructuring how DBD treatment services reach patients. Eli Lilly leverages its established psychiatry portfolio to sustain formulary access for DBD-related pharmacotherapy. Pfizer competes through diversified CNS development programs that anchor its position in adolescent behavioral health.
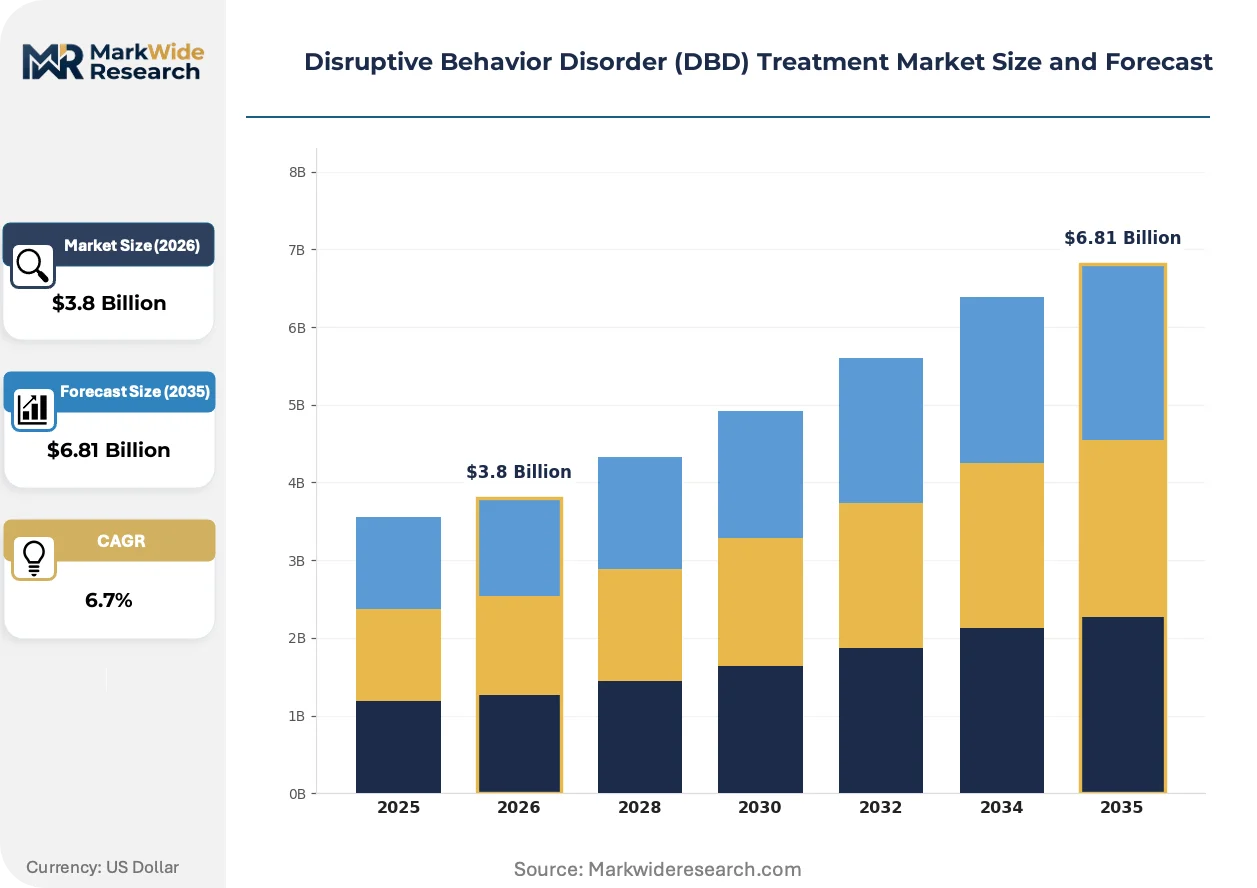
Disruptive Behavior Disorder treatment encompasses multimodal interventions targeting oppositional defiant disorder and conduct disorder through pharmacological agents, structured behavioral protocols, and family-systems approaches. Medication and Cognitive Behavioral Therapy segments dominate current utilization patterns, while telehealth delivery modes represent the fastest-expanding access channel as reimbursement parity laws mature. Parent Management Training occupies a specialized niche with concentrated margin pools among certified provider networks.
The FDA's pediatric exclusivity provisions and DEA scheduling requirements for stimulant formulations shape prescriber behavior and product development timelines. State-level Medicaid agencies and commercial payors increasingly mandate measurement-based care documentation for DBD therapy authorization. Stakeholders must monitor evolving prior authorization criteria and digital therapeutic classification decisions that will determine reimbursement scalability.
Market Dynamics
Prior authorization mandates from commercial insurers are restructuring patient access pathways, forcing providers to reconfigure service delivery around documentation-intensive measurement-based care protocols.
Growth Catalysts
- Medicaid Expansion:State-level Medicaid agencies in the United States are broadening behavioral health carve-outs, extending reimbursement coverage for Parent Management Training interventions.
- Telehealth Parity Laws:State legislatures across the United States are enacting reimbursement parity statutes that compel commercial payors to compensate virtual DBD therapy at in-person rates.
- Measurement-Based Care:Structured symptom-tracking protocols are becoming standard documentation requirements, creating standardized outcome metrics that justify continued therapy authorization.
Market Restraints
- DEA Scheduling Friction:Stimulant medications for pediatric DBD carry Schedule II classification, imposing inventory controls and prescriber registration burdens that limit pharmacy participation.
- Specialist Supply Concentration:Board-certified child and adolescent psychiatrists cluster in major metropolitan corridors, leaving rural and exurban regions with severe provider scarcity.
- Behavioral Intervention Labor Intensity:Cognitive Behavioral Therapy and Parent Management Training require sustained clinician-patient contact hours that resist productivity scaling.
Strategic Opportunities
- Digital Therapeutic Classification:FDA breakthrough device designation pathways for software-based DBD interventions could unlock novel reimbursement codes and prescriber adoption channels.
- School-Based Delivery:District-level contracts for on-site behavioral health services represent underpenetrated access points that bypass traditional clinic-based referral bottlenecks.
- Integrated Care Convergence:Partnerships between pediatric primary care networks and specialized DBD clinics are creating stepped-care models that capture patients earlier in symptom progression.
Industry Challenges
- Workforce Pipeline Constraints:Accredited training programs for Parent Management Training certification produce insufficient graduates to match expanding Medicaid reimbursement eligibility.
- Interoperability Friction:Electronic health record systems used by pediatric mental health clinics lack standardized interfaces with school-based information platforms, fragmenting care coordination.
- Prior Authorization Burden:Commercial payor documentation requirements for behavioral therapy sessions consume substantial administrative capacity without corresponding reimbursement for care coordination activities.
Report Scope
MarkWide Research| Attributes | Details |
|---|---|
| Report Title | Disruptive Behavior Disorder (DBD) Treatment Market |
| Market Size in 2026 | $3.8 Billion |
| Market Size in 2035 | $6.81 Billion |
| CAGR (2026 – 2036) | 6.7% |
| Historical Year | 2020-2024 |
| Base Year | 2025 |
| Forecast Period | 2026-2036 |
| Segmentation | Product Type: Medication, Therapy, Counseling, Support Groups Delivery Mode: In-person, Online, Hybrid, Telehealth End User: Children, Adolescents, Families, Educational Institutions Therapy Technique: Cognitive Behavioral Therapy, Parent Management Training, Play Therapy, Dialectical Behavior Therapy |
| Companies Covered | Eli Lilly, Pfizer, Novartis, Johnson & Johnson, Takeda Pharmaceutical, Shire, Teva Pharmaceuticals, GlaxoSmithKline, Sun Pharmaceutical, Others |
| Regions Covered | North America: US, Canada, Mexico Europe: Germany, Italy, France, UK, Spain, Denmark, Sweden, Austria, Belgium, Finland, Turkey, Poland, Russia, Greece, Switzerland, Netherlands, Norway, Portugal, Rest of Europe Asia Pacific: China, Japan, India, South Korea, Indonesia, Malaysia, Kazakhstan, Taiwan, Vietnam, Thailand, Philippines, Singapore, Australia, New Zealand, Rest of Asia Pacific South America: Brazil, Argentina, Colombia, Chile, Peru, Rest of South America Middle East & Africa: Saudi Arabia, UAE, Qatar, South Africa, Israel, Kuwait, Oman, North Africa, West Africa, Rest of MEA |
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Disruptive Behavior Disorder (DBD) Treatment Market Trends and Innovations
Telehealth infrastructure maturation is compressing geographic barriers to specialized DBD care, while regulatory frameworks evolve to classify and reimburse digital interventions.
Telehealth delivery platforms are decentralizing access to specialized DBD services by connecting rural and underserved families with board-certified child psychiatrists and behavioral therapists. School districts and community health centers are adopting these platforms at accelerating pace to circumvent regional specialist shortages. This technology is decentralizing the traditional hub-and-spoke model of academic medical center dominance, redistributing clinical capacity toward distributed care networks.
The FDA's pediatric exclusivity provisions are extending market protection timelines for sponsors conducting pediatric-specific efficacy trials, altering development program prioritization. Pharmaceutical sponsors are redirecting resources toward formulations with demonstrated pediatric bioequivalence to capture these exclusivity incentives. Adolescent behavioral health divisions within major psychiatry portfolios are most affected, accelerating trial enrollment timelines to secure priority review vouchers.
Family systems approaches are displacing individual-focused intervention models as primary payors demand documented caregiver engagement metrics. Pediatric mental health clinics are restructuring intake protocols to mandate multi-generational participation, replacing single-patient referral pathways. This shift is most visible in United States commercial insurance networks where measurement-based care documentation now tracks parental attendance as a condition for continued authorization.
Disruptive Behavior Disorder (DBD) Treatment Market Segmentation
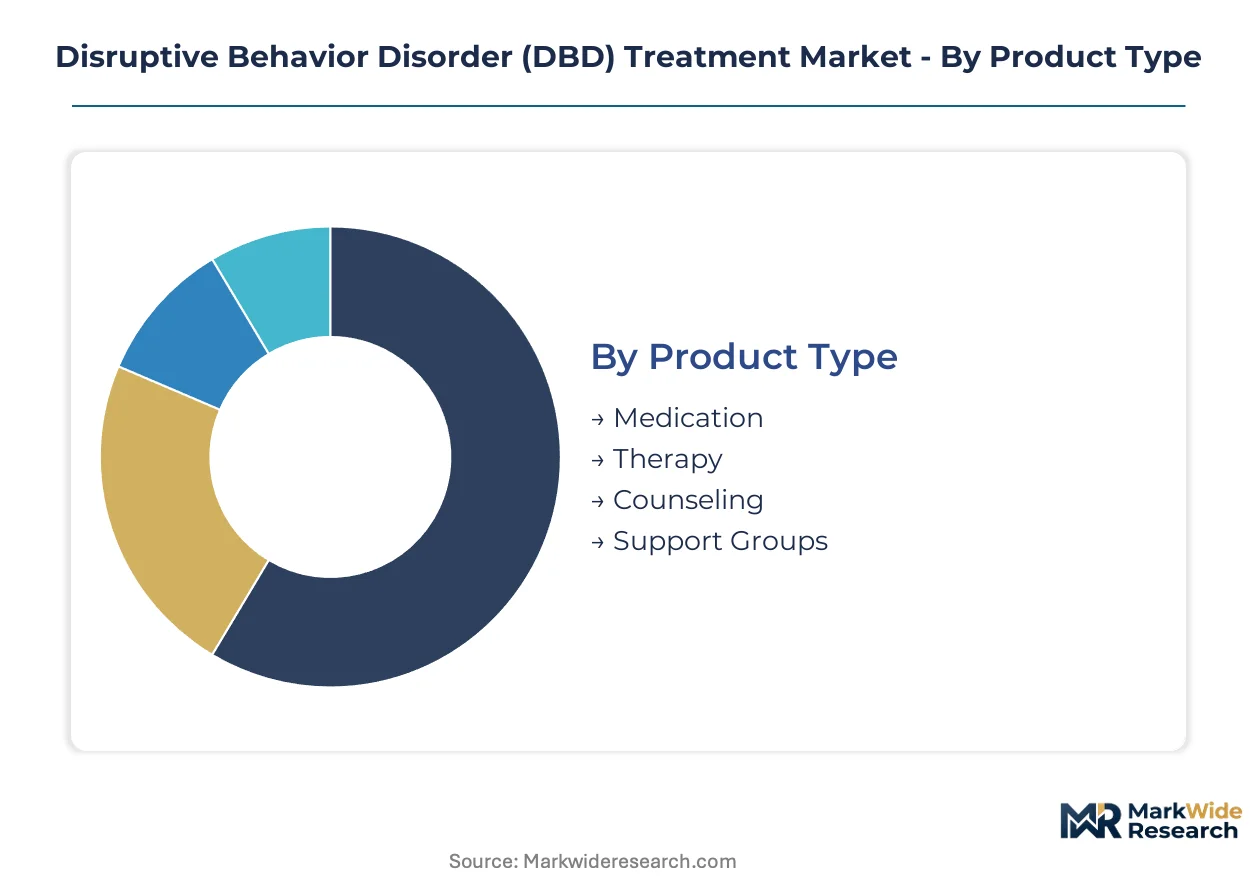
Segmentation in the DBD treatment market reveals how reimbursement pathways and prescriber preferences fragment across intervention modalities. Understanding these divisions exposes where Medicaid carve-outs and commercial prior authorization rules create divergent margin structures.
Product Type:
Cost tier determines access velocity, with pharmacological interventions clearing reimbursement faster than labor-intensive behavioral protocols.
- Medication:Stimulant and non-stimulant formulations carry Schedule II DEA classification, requiring locked inventory systems and monthly prescriber registration verification. Demand concentrates among Medicaid-enrolled children in the United States where state formularies mandate generic substitution protocols.
- Therapy:Structured behavioral protocols including individual and group modalities demand documented symptom-tracking under measurement-based care mandates. Commercial insurers in the United States increasingly require session-level outcome reporting as a condition for continued authorization.
- Counseling:Shorter-duration supportive interventions target milder symptom presentations with lower reimbursement tiers.
- Support Groups:Peer-led models operate largely outside insurance reimbursement, funded through school district contracts and community health grants.
Medication leads on scale; Therapy leads on momentum.
Delivery Mode:
Volume distribution tracks regulatory parity maturation, with virtual channels expanding fastest where state legislatures have enacted reimbursement equivalence statutes.
- Telehealth:Video-based psychiatric consultation and therapy sessions bypass geographic specialist scarcity, connecting rural families with board-certified child psychiatrists. United States state parity laws now compel commercial payors to reimburse virtual DBD care at in-person rates, accelerating platform adoption.
- In-person:Clinic-based delivery remains the gold standard for initial diagnostic assessment and medication management, particularly for stimulant prescribing that requires physical examination protocols. Major metropolitan corridors in the United States retain concentration of accredited providers.
- Online:Asynchronous digital therapeutic platforms and self-guided modules occupy an emerging classification space pending FDA breakthrough device determinations.
- Hybrid:Blended models combining periodic in-person assessment with ongoing virtual touchpoints optimize clinician productivity while maintaining care continuity.
In-person leads on scale; Telehealth gains share fastest.
End User:
Customer type dictates intervention intensity, with pediatric populations triggering the most stringent FDA labeling and Medicaid documentation requirements.
- Children:Patients under 12 years face the most restrictive stimulant prescribing protocols and mandatory caregiver participation requirements. United States FDA pediatric exclusivity provisions incentivize sponsors to conduct age-specific efficacy trials.
- Adolescents:Teenage patients access broader pharmacological options including non-stimulant alternatives, though DEA scheduling still imposes dispensing limits. This segment shows the steepest expansion trajectory as school-based screening identifies more cases.
- Families:Multi-generational treatment units are becoming the standard unit of care as insurers mandate documented caregiver engagement metrics.
- Educational Institutions:School districts represent underpenetrated contract opportunities for on-site behavioral health service delivery.
Children leads on scale; Adolescents leads on momentum.
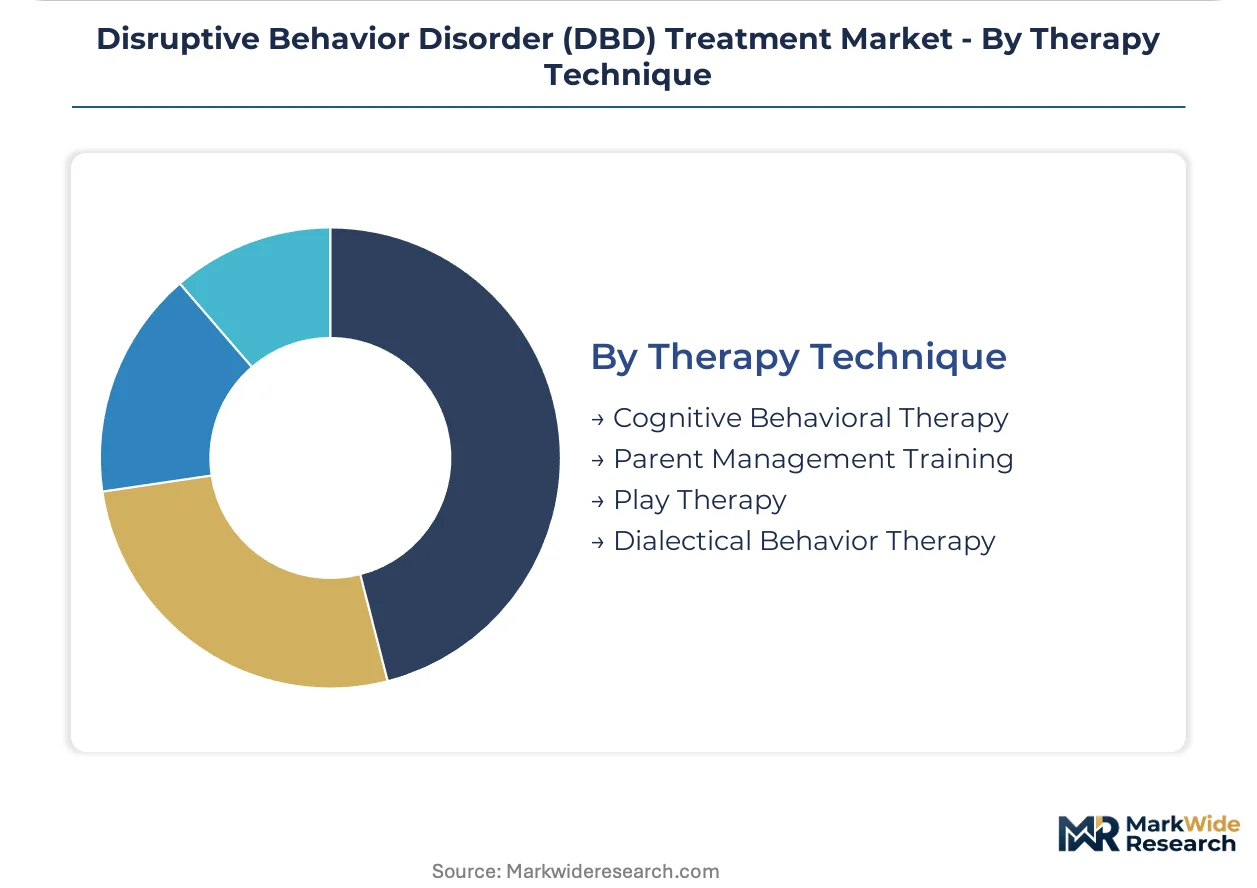
Therapy Technique:
Margin concentration follows certification scarcity, with specialized training pipelines constraining supply of evidence-based modalities.
- Cognitive Behavioral Therapy:Structured protocols targeting oppositional defiant disorder symptoms require sustained clinician-patient contact that resists productivity scaling. Demand concentrates in United States commercial insurance networks where prior authorization mandates documentation of session-specific behavioral targets.
- Parent Management Training:Caregiver-focused interventions address family-system dynamics through standardized curricula with measurable engagement metrics. Medicaid agencies in the United States are broadening reimbursement eligibility, though accredited training programs produce insufficient graduates to match demand.
- Play Therapy:Developmentally adapted interventions for younger children occupy a niche with limited insurance recognition.
- Dialectical Behavior Therapy:Emotion regulation protocols adapted for adolescent conduct disorder presentations show expanding adoption in residential treatment settings.
Cognitive Behavioral Therapy leads on scale; Parent Management Training leads on momentum.
Need this report tailored to your region?
Request specific countries, segments, or companies — tailored to your requirements.
Regional Outlook
The United States concentrates far more DBD treatment infrastructure than any other country, while Germany and Japan maintain narrower but specialized pediatric psychiatry networks. National regulatory frameworks and reimbursement policies create divergent access pathways across these markets.
United States
Commercial insurers and Medicaid agencies drive demand through prior authorization mandates and behavioral health carve-outs. FDA pediatric exclusivity provisions incentivize sponsors to conduct age-specific efficacy trials for stimulant formulations. Major metropolitan corridors including Boston, New York, and Los Angeles cluster board-certified child psychiatrists and specialized DBD clinics.
Germany
Statutory health insurance funds expand reimbursement for structured behavioral protocols targeting oppositional defiant disorder. The country's national pharmaceutical regulator maintains strict labeling requirements for pediatric psychopharmacology. Industrial concentration in North Rhine-Westphalia and Bavaria supports specialized pediatric mental health service networks.
Japan
PMDA review pathways for pediatric indications shape development timelines for adolescent behavioral health compounds. METI initiatives promote digital therapeutic adoption in school-based mental health screening programs. Tokyo and Osaka metropolitan areas concentrate academic medical centers with dedicated child psychiatry divisions.
United Kingdom
NHS England commissioning frameworks prioritize measurement-based care documentation for DBD therapy authorization. NICE guidelines influence prescribing patterns for non-stimulant alternatives in conduct disorder presentations. London and the Southeast region anchor specialized Tier 4 child and adolescent mental health services.
Canada
Provincial health plans vary in coverage for Parent Management Training interventions across Ontario, Quebec, and British Columbia. Health Canada maintains pediatric labeling requirements aligned with FDA frameworks. Toronto and Vancouver clusters support academic research programs in family-systems approaches to DBD.
Disruptive Behavior Disorder (DBD) Treatment Market Competitive Landscape
Diversified conglomerates compete with focused pure-play specialists across the DBD treatment landscape, creating a tiered competitive structure. Large pharmaceutical sponsors leverage established psychiatry portfolios to sustain formulary access, while emerging digital therapeutic developers pursue FDA breakthrough device pathways. Three archetypes dominate: diversified CNS majors, pediatric-focused biopharmaceutical divisions, and software-based intervention developers. Consolidation through strategic partnerships and portfolio diversification represents the primary competitive dynamic, with geographic expansion into school-based delivery channels as a secondary thrust.
Within the diversified pharmaceutical tier, Eli Lilly and Pfizer exemplify established CNS portfolio strategies, while Takeda Pharmaceutical represents Japanese-sponsored pediatric behavioral health capabilities. Novartis and Johnson & Johnson occupy positions spanning both pharmacological and digital therapeutic development vectors. These anchors reflect how scale-driven sponsors balance mature psychiatry franchises against emerging regulatory pathways for software-based interventions.
| Leading Market Players |
|---|
| Eli Lilly |
| Pfizer |
| Novartis |
| Johnson & Johnson |
| Takeda Pharmaceutical |
| Shire |
| Teva Pharmaceuticals |
| GlaxoSmithKline |
| Sun Pharmaceutical |
| Others |
Pricing and Supply Chain Analysis
Certification-tier divergence between board-certified Parent Management Training providers and generalist behavioral therapists manifests in both reimbursement rates and workforce pipeline configurations across United States Medicaid agencies. Premium-tier reimbursement attaches to accredited training credentials that require multi-year fellowship completion, while supply chain constraints in rural corridors force patients toward lower-reimbursed telehealth alternatives.
Pricing Analysis
Capacity additions in school-based behavioral health service lines are reshaping price floors for traditional clinic-based delivery. Three-tier pricing structure across premium-certified, standard-licensed, and economy-tier generalist providers dominates reimbursement schedules. Price differentiation stems from FDA pediatric exclusivity status for pharmacological interventions and state-level Medicaid carve-out generosity. Pricing pressure intensifies as commercial insurers expand prior authorization documentation requirements without corresponding care coordination payments. Medicaid-enrolled children exhibit highest price sensitivity, while self-insured employer plans demonstrate lowest sensitivity to session-level cost variation.
Supply Chain Analysis
Reverse-logistics flows for unused stimulant medications impose DEA-mandated destruction protocols that inflate pharmacy inventory carrying costs. Supply concentrates among United States compounders for immediate-release formulations, while extended-release production draws from Ireland and Germany facilities. Raw material dependencies include methylphenidate API from Indian manufacturers, amphetamine salts from domestic DEA-registered facilities, and behavioral therapy labor from accredited training programs. Single-source vulnerability pervades board-certified child psychiatrist availability in exurban regions. Distribution runs through three-channel structure: retail pharmacy chains for medication, clinic networks for in-person therapy, and platform-as-a-service vendors for telehealth delivery.
Get the full picture before you read further.
Download a free sample with table of contents, companies, segments, and methodology.
Analyst Recommendations
This market functions as a geographic-arbitrage play where state-level Medicaid reimbursement generosity in Massachusetts and California contrasts with prior authorization stringency in Texas and Florida, creating margin dispersion for multi-state provider networks.
For Market Incumbents: Acquire specialized Parent Management Training certification programs to lock in workforce pipeline control against emerging digital therapeutic substitutes. Eli Lilly and Pfizer should deepen backward integration into pediatric trial infrastructure to capture FDA exclusivity incentives before non-stimulant formulations erode stimulant market position. Consolidate clinic network footprints in metropolitan corridors where specialist supply concentration sustains pricing power. For New Entrants and Emerging Players: Rural school districts represent the most penetrable buyer archetype for telehealth-enabled behavioral health contracts that bypass traditional referral bottlenecks. Target Medicaid-managed care organizations in expansion states with measurement-based care platforms that automate prior authorization documentation. Pursue district-level RFPs for on-site counselor placement as the primary go-to-market angle. For Investors and Strategic Acquirers: Consolidation pressure builds where workforce certification scarcity intersects with expanding reimbursement eligibility under state Medicaid behavioral health carve-outs. Five-to-ten-year viability favors platforms combining telehealth infrastructure with proprietary training curricula. Acquisition target archetype: regional clinic chains with established school district contracts and accredited Parent Management Training capacity. Monitor FDA breakthrough device determinations for digital therapeutics as the signal indicating reimbursement code scalability.| Strategic Initiative | Industry Significance |
|---|---|
| Digital Therapeutic FDA Submission | Breakthrough device designation unlocks novel reimbursement codes for software-based DBD interventions. |
| School District Contract Expansion | District-level behavioral health RFPs bypass traditional clinic referral bottlenecks in underserved regions. |
| Parent Management Training Certification | Accredited curricula scarcity creates margin pools as Medicaid agencies broaden reimbursement eligibility. |
| Telehealth Platform Integration | State parity laws compel commercial payors to reimburse virtual care at in-person rates. |
| Pediatric Exclusivity Trial Investment | FDA provisions extend market protection timelines for sponsors conducting age-specific efficacy studies. |
Research Methodology
Multiple input streams — structured interviews with child and adolescent psychiatrists, regulatory affairs specialists at pharmaceutical sponsors, Medicaid agency behavioral health directors, and school district procurement officers — were reconciled against secondary validation from FDA pediatric exclusivity filings, state Medicaid carve-out policy documents, ClinicalTrials.gov enrollment data, and commercial formulary databases. Bottom-up patient-volume estimates across medication, therapy, and digital therapeutic segments were triangulated against top-down spending projections from payer claims data.
Data-stream reconciliation applied analytical frameworks across the projection horizon, modeling segmentation by intervention modality, delivery mode, end-user age cohort, and therapy technique certification tier. CAGRs were derived from elasticity-adjusted utilization trajectories incorporating DEA scheduling friction, workforce pipeline constraints, and telehealth parity law adoption curves. Forecast inputs included state-level Medicaid expansion timelines, FDA breakthrough device determination probabilities, and school district behavioral health contract award velocities.
Underlying measurement precision varies by segment; medication utilization carries tighter precision than emerging digital therapeutic categories where classification remains unsettled. Forecasts reflect assumptions regarding reimbursement parity maturation and measurement-based care mandate diffusion that could revise substantially upon regulatory or legislative inflection. Practitioners should monitor state Medicaid agency prior authorization rulemaking and FDA digital therapeutic classification decisions for early signals.
Need Custom Data?
Can't find what you're looking for? Our analysts can build a custom report tailored to your exact requirements.
1,000+
Global Clients
150+
Countries Covered
65,000+
Reports Available
Frequently Asked Questions
Why Work With MWR
Trusted by 1,000+ businesses across 150+ countries for high-stakes market decisions.
Ready to access intelligence that moves business?
Browse Reports →Trusted by Global Leaders
From Fortune-level organizations to global SMEs, we provide intelligence for high-stakes decisions.
Multi-Language Support
Research available in French, German, Spanish, Chinese, and more.
ISO & IAF Certified
Globally aligned quality standards ensuring methodological discipline and data integrity.
Competitive Relevance
Free inclusion of 3–4 additional companies of your choice in every report.
Customized Insights
Tailored intelligence for market entry, niche expansion, or competitive benchmarking.
Post-Sale Assistance
Dedicated coordination to help interpret findings and address queries post-delivery.
Cutting-Edge Methods
Structured data collection, advanced analytics, and expert validation for reliable forecasts.
Value for Investment
Credible, structured intelligence at a cost that makes strategic sense.
What Our Clients Say
My team needed the real numbers on AI spending for our Reinvention Services work. MarkWide delivered. No fluff, just a clear look at where the money is actually going. It saved us about three weeks of guesswork.
Accenture
We recently leaned on MarkWide Research for a deep dive into the evolving snacking habits within Southeast Asia. Their report on the premium biscuit segment was exceptionally detailed, providing us with the specific consumer sentiment data we needed to refine our regional flavor strategy. It wasn't just a data dump; the cultural nuances they captured helped us avoid several localization pitfalls.
Mondelez
Director of Global Consumer Insights
For a recent engagement in the automotive sector, we needed rigorous, independent verification of EV battery recycling capacities. MWR delivered a report that made our work easier. Their ability to segment the competitive landscape by chemical composition and regional throughput was exactly the kind of 'hard-to-find' intel that our team was looking for.
BCG
We were looking for a report on Xcelerator ecosystem's potential and got in touch with MarkWide's team through one of my old colleagues who worked with them in the past. Their research team was incredibly polite and were always available for us which was important for my team as this was a custom project. Their methodology for tracking industrial IoT adoption gave our R&D heads the clarity needed to prioritize our next-gen sensor development.
Siemens
Head of Industrial Digitalization
During a recent M&A project, we needed a fast, reliable breakdown of the Fintech landscape in Southeast Asia. MarkWide came through with a report that was actually readable and focused on the metrics that matter. It saved my team a good week of primary research, which, given our timelines, was a massive win.
KPMG
Advisory Partner
We tapped MarkWide Research for a deep dive into the ESG reporting software market. At Deloitte, our clients expect us to have the most current insights, and this report didn't disappoint. It provided a breakdown of the competitive field that was far more detailed than what we were expecting.
Deloitte
Lead Consultant, Sustainability Services
For our semiconductor division at Samsung, the supply chain forecast from MarkWide was incredibly useful. It provided a realistic outlook on raw material availability that helped us refine our production timelines. No fluff, just the data we needed to make a tough call.
Samsung
The value for our organization comes from three things: depth of research, specificity of segments and being easy to work with. As important as the first two are, the third can't be underestimated. MarkWide Research, maybe more than any other research vendor, wants to know what is top of mind for our team and what big questions we are grappling to answer. Their customer first approach and high value engagement model have given us great analysis and excellent value for money.
3M
I can share that it was a positive experience wherein MarkWide Research demonstrated flexibility to adapt to our needs and delivered an excellent report that fits all our requirements. Personally, I liked the timely follow up by the team and we will definitively reach out in case more research support is required.
VITO
Related Reports
Specialty Medicine
Hunter Syndrome Treatment Market
Specialty Medicine
Global Parkinsons Disease Treatment Market
Specialty Medicine
Behcet's Syndrome Market
Specialty Medicine
Gallbladder Cancer Therapeutics Market
Specialty Medicine
Acute Hepatic Porphyria (APH) Market
Specialty Medicine
Global Appendicitis Market
Specialty Medicine
Global Melanoma Therapeutics Market
Specialty Medicine
Global Retinal Biologics Market
Specialty Medicine
Head and Neck Cancer Therapeutics Market
Specialty Medicine
Genital Warts (Condyloma Acuminatum) Market
Specialty Medicine
Global Thyroid Disorder Market
Specialty Medicine
Hemangioma Treatment Market
Specialty Medicine
Neurodegenerative Disease Market
Specialty Medicine
Kinase Inhibitor in Autoimmune Diseases Market
Specialty Medicine
Ankylosing Spondylitis Market
Specialty Medicine
Global Fuchs Endothelial Corneal Dystrophy (FECD) Market